

DWC Form RFA at a glance
What it is: DWC Form RFA (Effective 2/2014), the Request for Authorization for Medical Treatment, is required for the employee's treating physician to initiate the utilization review process required by Labor Code section 4610.
Who signs: A signature by the treating physician is mandatory.
A filled-in DWC Form RFA example: a physician requests physical therapy
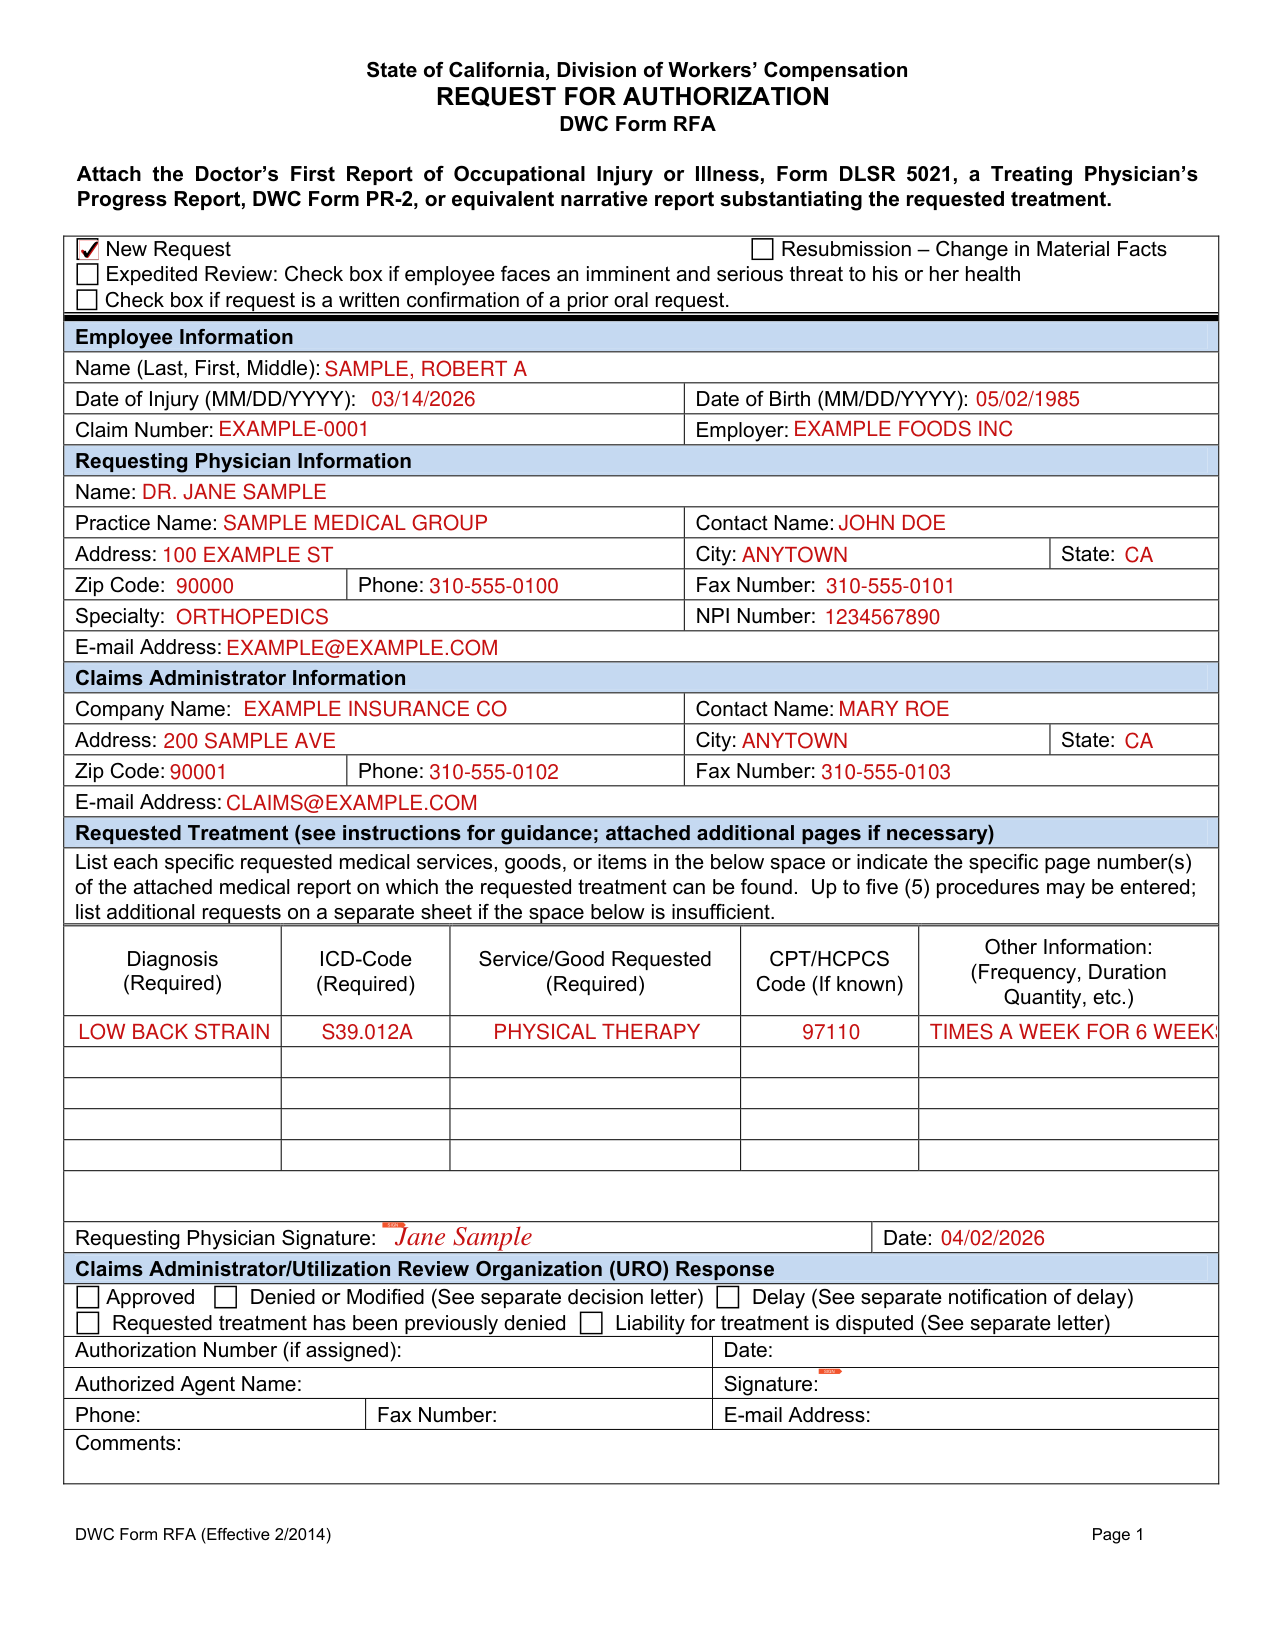
How to fill out DWC Form RFA, box by box
New Request or Resubmission

Check the appropriate box at the top of the form. Indicate whether this is a new treatment request for the employee or the resubmission of a previously denied request based on a change in material facts regarding the employee's condition.
A resubmission is appropriate if the facts that provided the basis for the initial utilization review decision have subsequently changed such that the decision is no longer applicable to the employee's current condition.
Expedited Review and written confirmation of a prior oral request

A request for expedited review must be supported by documentation substantiating the employee's condition.
Expedited Review: Check box if employee faces an imminent and serious threat to his or her health. Check box if request is a written confirmation of a prior oral request.
Employee Information, Requesting Physician Information and Claims Administrator Information

The requesting physician must complete all identifying information regarding the employee, the claims administrator, and the physician.
Requested Treatment
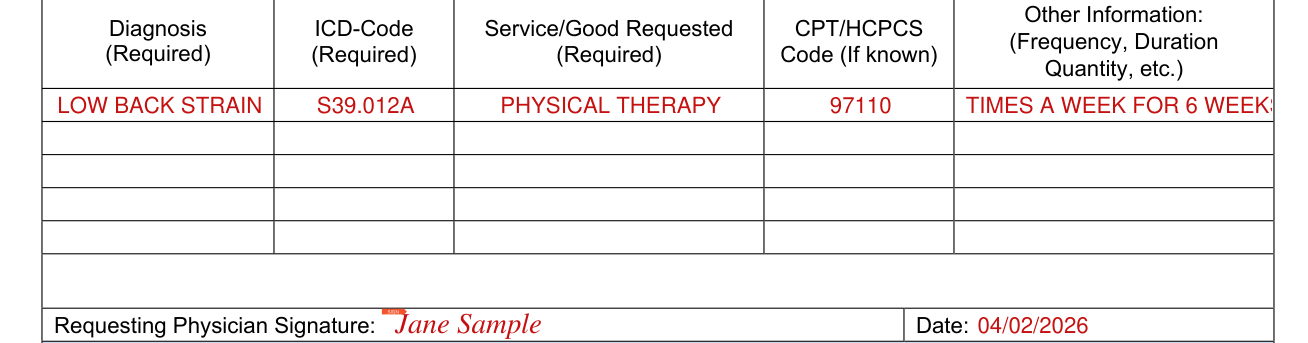
The DWC Form RFA must contain all the information needed to substantiate the request for authorization.
If the request is to continue a treatment plan or therapy, please attach documentation indicating progress, if applicable. List the diagnosis (required), the ICD Code (required), the specific service/good requested (required), and applicable CPT/HCPCS code (if known). Include, as necessary, the frequency, duration, quantity, etc. Reference to specific guidelines used to support treatment should also be included. For requested treatment that is: (a) inconsistent with the Medical Treatment Utilization Schedule (MTUS) found at California Code of Regulations, title 8, section 9792.20, et seq.; or (b) for a condition or injury not addressed by the MTUS, you may include scientifically based evidence published in peer-reviewed, nationally recognized journals that recommend the specific medical treatment or diagnostic services to justify your request.
Attach additional pages if necessary. Up to five (5) procedures may be entered; list additional requests on a separate sheet if the space is insufficient.
Requesting Physician Signature

Requesting Physician Signature: Signature/Date line is located under the requested treatment box.
Claims Administrator approval of requested treatment
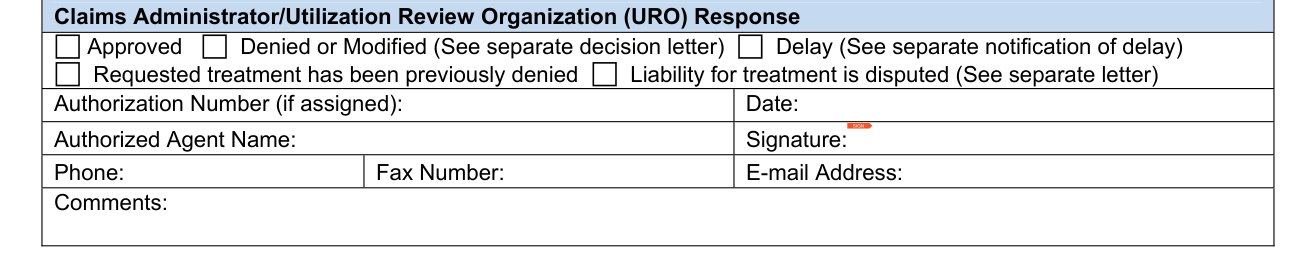
Upon receipt of the DWC Form RFA, a claims administrator must respond within the timeframes and in the manner set forth in Labor Code section 4610 and California Code of Regulations, title 8, section 9792.9.1.
To communicate its approval on requested treatment, the claims administrator may complete the lower portion of the DWC Form RFA and fax it back to the requesting provider.
(Use of the DWC Form RFA is optional when communicating approvals of treatment; a claims administrator may utilize other means of written notification.)
If multiple treatments are requested, indicate in comments section if any individual request is being denied or referred to utilization review.
Claims Administrator/Utilization Review Organization (URO) Response: Approved, Denied or Modified (See separate decision letter), Delay (See separate notification of delay), Requested treatment has been previously denied, Liability for treatment is disputed (See separate letter). Authorization Number (if assigned), Date, Authorized Agent Name, Signature, Phone, Fax Number, E-mail Address and Comments.
More rules for DWC Form RFA
The DWC Form RFA is not a separately reimbursable report under the Official Medical Fee Schedule, found at California Code of Regulations, title 8, section 9789.10 et seq.
Warning: Private healthcare information is contained in the Request for Authorization for Medical Treatment, DWC Form RFA. The form can only go to other treating providers and to the claims administrator.
Before you go
A Doctor's First Report of Occupational Injury or Illness, Form DLSR 5021, a Treating Physician's Progress Report, DWC Form PR-2, or equivalent narrative report substantiating the requested treatment must be attached.
Common questions about DWC Form RFA
Where do I file it?
This form can be mailed, faxed, or e-mailed to the address, fax number, or e-mail address designated by the claims administrator for this purpose.
Sources
[1] DWC Form RFA (Effective 2/2014), Request for Authorization, State of California, Division of Workers' Compensation (the Official source link on this page).
