


Form CDPH 283 B at a glance
What it is: CDPH 283 B (01/22) is the Certified Nurse Assistant (CNA) Initial Application.
Who signs: SECTION V: the Signature of Applicant and the Date. SECTION VI is completed by the registered nurse responsible for the general supervision of the training program, and only applies to students that have recently completed a CNA Training Program in CA.
A filled-in Form CDPH 283 B example: an applicant enrolling in a CNA training program

How to fill out Form CDPH 283 B, box by box
TYPE OF REQUEST

Under TYPE OF REQUEST, check here if you are enrolling in a CNA training program (complete sections I, II, III, IV, and V), or check here if you are requesting RECONSIDERATION for a previously revoked/denied certificate (complete sections I, II, III and V).
SECTION II (REQUIRED): Last Name, First Name, MI and Sex
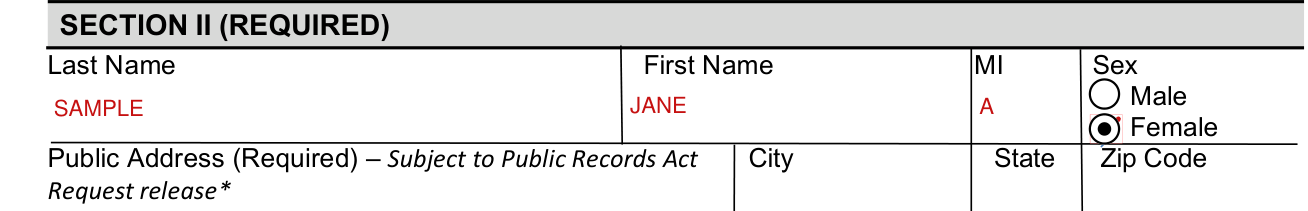
Under SECTION II (REQUIRED), enter the Last Name, First Name and MI, and mark Male or Female under Sex.
Public Address and Confidential Address
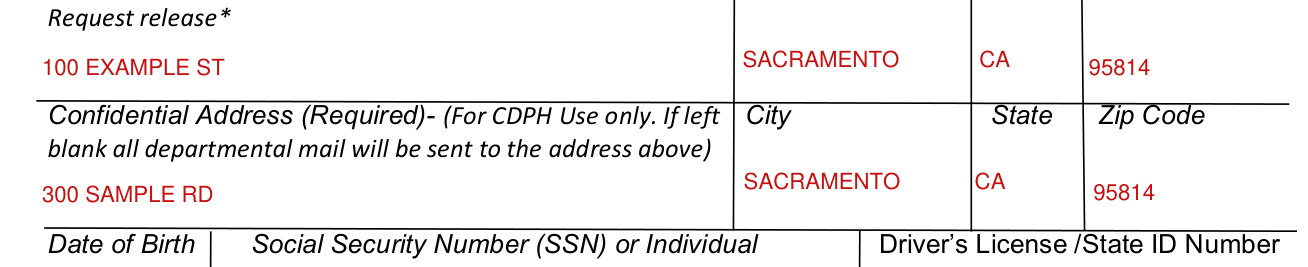
Enter the Public Address (Required), City, State and Zip Code; it is subject to Public Records Act Request release.
The California Department of Public Health will be required to release the address of record for certified nurse assistants, home health aides, certified hemodialysis technicians, and licensed nursing home administrators in response to a Public Records Act (PRA) request.
Enter the Confidential Address (Required), City, State and Zip Code, for CDPH use only; if left blank, all departmental mail will be sent to the Public Address.
Date of Birth, SSN or ITIN, and Driver's License /State ID Number
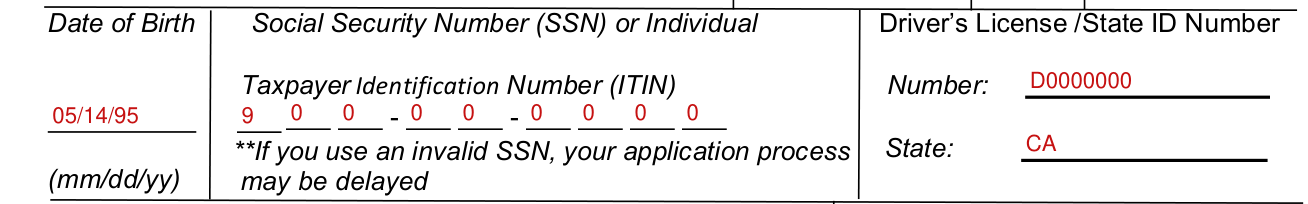
Enter the Date of Birth as mm/dd/yy.
Enter the Social Security Number (SSN) or Individual Taxpayer Identification Number (ITIN).
Enter the Driver's License /State ID Number and the State.
Phone Number, Email Address and text messages

Enter the Phone Number and the Email Address. This information will not be released to the public nor will it be displayed online.
By checking this box, you agree to receive text messages from the California Department of Public Health (CDPH) for reminders and notifications regarding your application and/or certification. You may receive up to 5 messages per month. Message and data rates may apply.
SECTION III (REQUIRED)

Under SECTION III (REQUIRED), mark Yes or No: have you been CONVICTED, at any time, of any crime, other than a minor traffic violation? You need not disclose any marijuana-related offenses specified in the marijuana reform legislation and codified at the Health and Safety Code, Sections 11361.5 and 11361.7.
Next to Yes No, if yes, list conviction, the Court of conviction and the Date.
Mark Yes or No: has any health-related licensing, certification or disciplinary authority taken adverse action (revoked, annulled, cancelled, suspended, etc.) against you?
Next to Yes No, enter the Type of License/Certificate, the License/Certificate Number and the Type of Action.
SECTION IV (IF APPLICABLE)
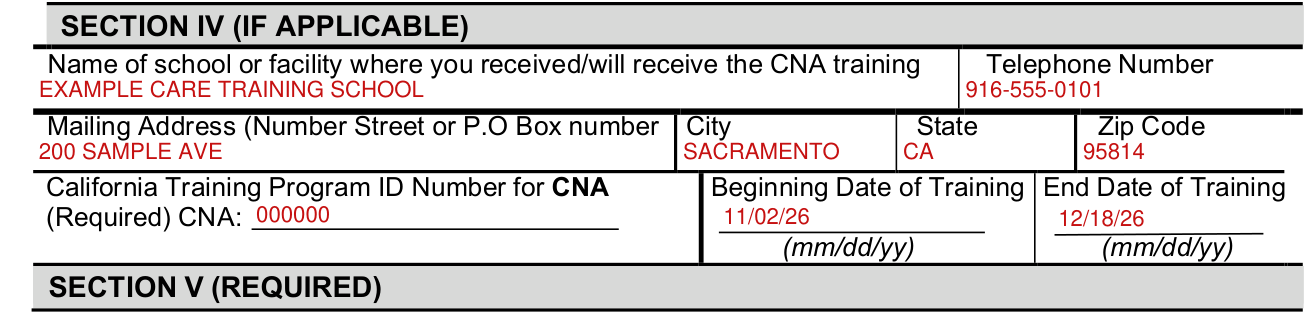
If you are enrolling in a CNA training program, complete SECTION IV (IF APPLICABLE): enter the Name of school or facility where you received/will receive the CNA training, the Telephone Number and the Mailing Address (Number Street or P.O Box number), City, State and Zip Code.
Enter the California Training Program ID Number for CNA (Required), the Beginning Date of Training and the End Date of Training, as mm/dd/yy.
SECTION V (REQUIRED)
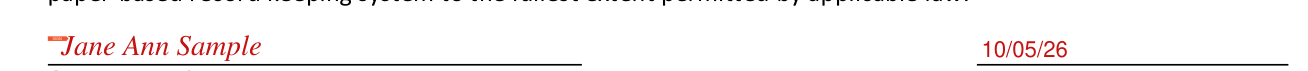
Under SECTION V (REQUIRED): by signing you certify under penalty and perjury under the applicable state and federal laws that the information contained in this application and supporting documents, is true and correct.
I further understand that any false, incomplete, or incorrect statements may result in denial of this application.
Sign on the Signature of Applicant line and enter the Date.
SECTION VI
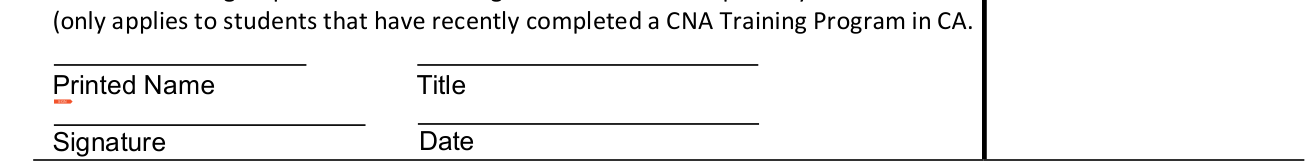
SECTION VI is to be completed by the registered nurse responsible for the general supervision of the training program: Printed Name, Title, signature and Signature Date. By signing, the registered nurse certifies that this individual has successfully completed state and federal nurse assistant training requirements and is eligible to take the Competency Evaluation (only applies to students that have recently completed a CNA Training Program in CA.
More rules for Form CDPH 283 B
Applicants who are unable to obtain electronic prints may complete the fingerprint card (FD-258) and submit two copies to the department.
After you apply
RECONSIDERATION
Under E) RECONSIDERATION, 1) if the applicant's CNA certificate was revoked or denied by the CDPH, after review of this application, the CDPH will reach out to the applicant for additional information/documentation as needed.
CNA RENEWAL INFORMATION and NAME AND ADDRESS CHANGES
Under C) CNA RENEWAL INFORMATION, 1) the initial CNA certificate is issued for two birthdays, not two calendar years, and will expire on your birthday.
CNA certificates must be renewed every two (2) years. You may renew your certificate any time within two (2) years after the expiration date. Under D) NAME AND ADDRESS CHANGES, 1) certificate holders shall notify CDPH within sixty (60) days of any change of address.
If requesting a name change, submit legal verification of the change (marriage certificate, divorce decree, or court documents). Failure to report a name or address change may result in the delay or loss of your certification.
Common questions about Form CDPH 283 B
Is there a deadline?
Under A) CNA APPLICANTS (complete sections I, II, III, IV, and V), 1) the applicant must submit to HWB, upon enrollment in the program and before patient contact, this completed Initial Application (CDPH 283 B) and a copy of the completed Request for Live Scan Services (BCIA 8016) form.
Where do I file it?
Mail or fax the application to the California Department of Public Health (CDPH) Licensing and Certification Division (L&C) Healthcare Workforce Branch (HWB), MS 3301, P.O. Box 997416, Sacramento, CA 95899-7416; the fax number is (916) 552-8785.
Are there fees?
Fingerprint cards (FD-258) must be accompanied by a $32.00 check or money order made payable to “The Department of Justice” (checked October 20, 2026). B) CRIMINAL RECORD CLEARANCE 1) All CNA applicants must undergo a criminal record review.
Sources
[1] Form CDPH 283 B (01/22), Certified Nurse Assistant (CNA) Initial Application, California Department of Public Health (the Official source link on this page).