


Physician Medical Report Form at a glance
What it is: Physician Medical Report Form: participation in the program is contingent upon CIEE International Study Programs staff receiving a completed medical report from you and your physician.
Who signs: The applicant fills out name, program and signature and then gives the form to the physician, who completes Physician's Name, Physician's Signature, Date, Physician's Address and Physician's Phone Number.
A filled-in Physician Medical Report Form example: an applicant fills out the top of the form

How to fill out Physician Medical Report Form, box by box
Name, program and signature

Please fill out your name, program and signature and then give this form to your physician.
Term(s) (check all that apply)

Check all that apply under Term(s): Summer, Fall, Spring, January/May, and enter the YEAR.
The physician's examination and replies

Your doctor should complete this report based on an examination within four months of the program departure date.
Note: It is CIEE's policy not to accept reports filled out by a parent-physician.
It is essential that your replies be based on a current and thorough physical examination and knowledge of the applicant's medical history.
1. How long have you known the applicant? 2. What is the date of the applicant's most current examination? 3. Are you the applicant's family physician, the applicant's College physician or Other? 4. What is the applicant's general state of health: Excellent, Good, Fair or Poor?
5. Please indicate the applicant's vital signs (at rest): a. Pulse Rate, b. Skin, c. Respiration, d. Temperature, e. Blood Pressure.
Yes or no questions 6 to 17
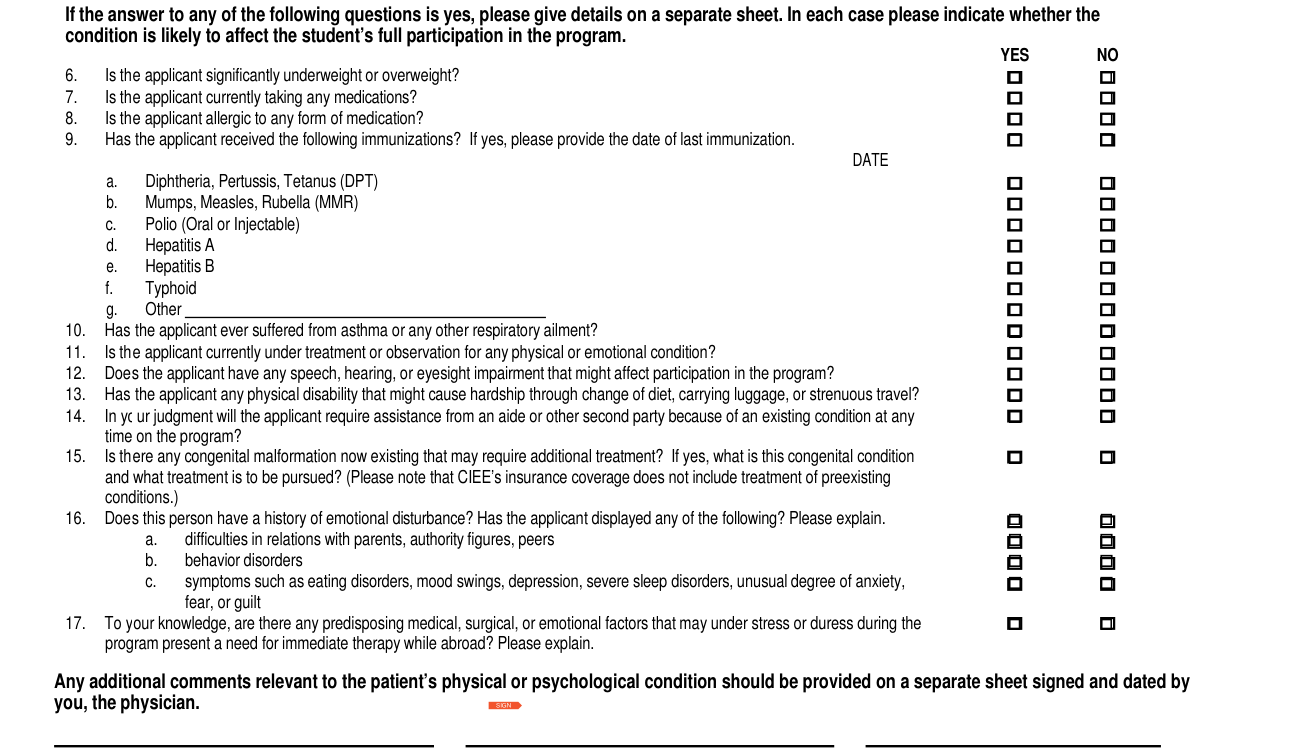
If the answer to any of the following questions is yes, please give details on a separate sheet. In each case please indicate whether the condition is likely to affect the student's full participation in the program.
YES NO: 6. Is the applicant significantly underweight or overweight? 7. Is the applicant currently taking any medications? 8. Is the applicant allergic to any form of medication?
9. Has the applicant received the following immunizations? If yes, please provide the date of last immunization: a. Diphtheria, Pertussis, Tetanus (DPT), b. Mumps, Measles, Rubella (MMR), c. Polio (Oral or Injectable), d. Hepatitis A, e. Hepatitis B, f. Typhoid, g. Other.
10. Has the applicant ever suffered from asthma or any other respiratory ailment? 11. Is the applicant currently under treatment or observation for any physical or emotional condition? 12. Does the applicant have any speech, hearing, or eyesight impairment that might affect participation in the program?
13. Has the applicant any physical disability that might cause hardship through change of diet, carrying luggage, or strenuous travel? 14. In your judgment will the applicant require assistance from an aide or other second party because of an existing condition at any time on the program?
15. Is there any congenital malformation now existing that may require additional treatment? If yes, what is this congenital condition and what treatment is to be pursued? (Please note that CIEE's insurance coverage does not include treatment of preexisting conditions.)
16. Does this person have a history of emotional disturbance? Has the applicant displayed any of the following? Please explain. a. difficulties in relations with parents, authority figures, peers, b. behavior disorders, c. symptoms such as eating disorders, mood swings, depression, severe sleep disorders, unusual degree of anxiety, fear, or guilt.
17. To your knowledge, are there any predisposing medical, surgical, or emotional factors that may under stress or duress during the program present a need for immediate therapy while abroad? Please explain.
Physician's name, signature and date

Physician's Name, Physician's Signature, Date, Physician's Address and Physician's Phone Number.
Any additional comments relevant to the patient's physical or psychological condition should be provided on a separate sheet signed and dated by you, the physician.
More rules for Physician Medical Report Form
If you have questions about this form, please contact CIEE at 1-800-407-8839.
Sources
[1] Physician Medical Report Form, CIEE International Study Programs (the Official source link on this page).