


Form DSD DC-163.10 at a glance
What it is: Medical Report For Conditions That May Impair Driving Safely (DSD DC-163.10), from the Office of the Secretary of State Driver Services Department.
Who signs: Sign on the signature of individual line and enter the date of signature. Section II, Medical Health, is to be completed by MD/DO and/or medical professional (NP/PA).
A filled-in Form DSD DC-163.10 example: a driver's medical report with one condition

How to fill out Form DSD DC-163.10, box by box
Section I, to be completed by the driver
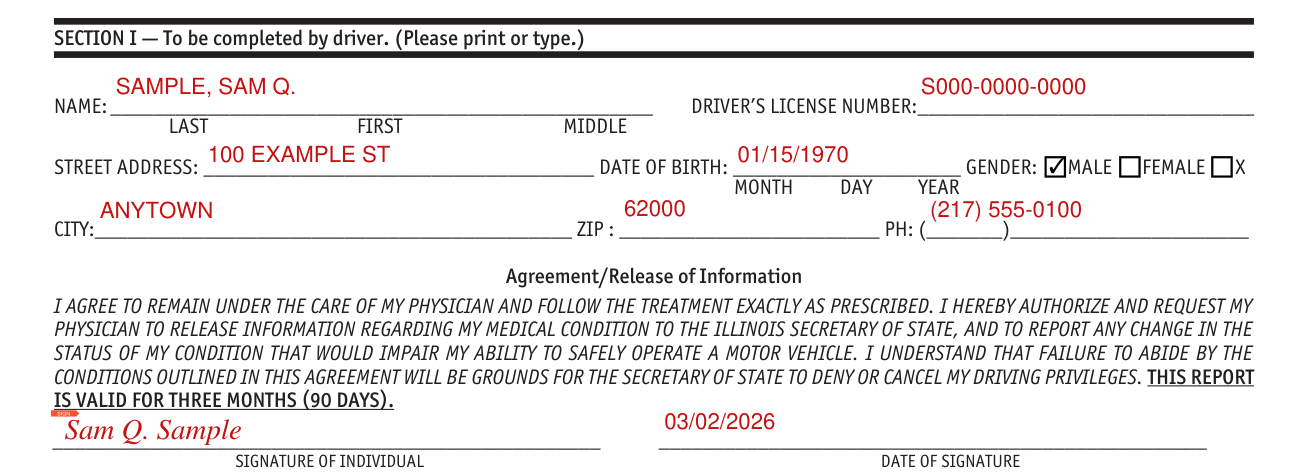
Section I is to be completed by the driver; print or type.
Enter the name (last, first, middle) and the driver's license number.
Enter the street address, the date of birth (month, day, year) and the gender: MALE, FEMALE or X.
Enter the city, the ZIP and the PH.
I agree to remain under the care of my physician and follow the treatment exactly as prescribed. Failure to abide by the conditions outlined in this agreement will be grounds for the Secretary of State to deny or cancel my driving privileges. This report is valid for three months (90 days).
Sign on the signature of individual line and enter the date of signature.
Medical Health Section II and medically and mentally fit to safely operate a motor vehicle

Section II, Medical Health, is to be completed by MD/DO and/or medical professional (NP/PA).
Enter the date of completion of Medical Health Section II.
Required: in your professional opinion, is this individual MEDICALLY AND MENTALLY FIT to safely operate a motor vehicle? Mark YES or NO.
Conditions
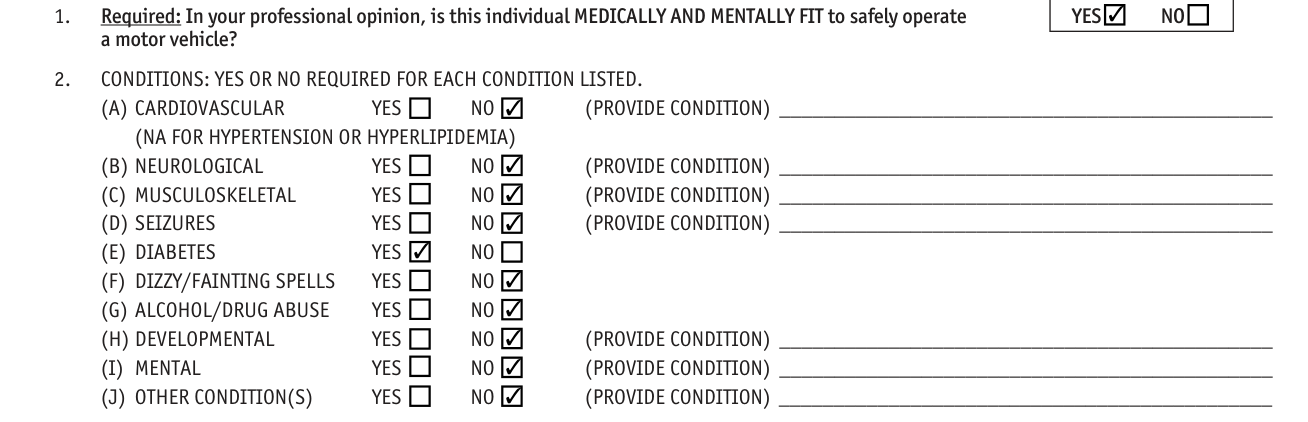
YES OR NO is required for each condition listed.
The conditions listed are cardiovascular, neurological, musculoskeletal, seizures, diabetes, dizzy/fainting spells, alcohol/drug abuse, developmental, mental and other condition(s).
For cardiovascular, neurological, musculoskeletal, seizures, developmental, mental and other condition(s), provide the condition.
For cardiovascular, NA for hypertension or hyperlipidemia.
Current medications
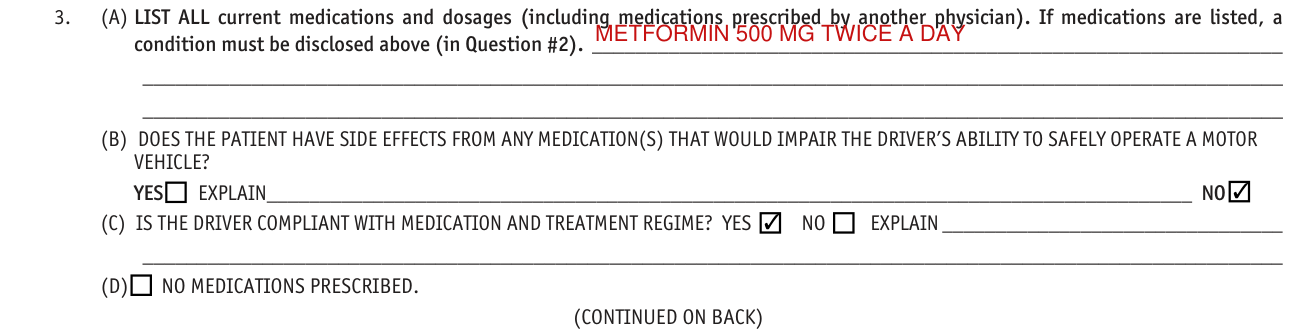
In Question 3 (A), list all current medications and dosages (including medications prescribed by another physician).
If medications are listed, a condition must be disclosed in Question #2, Conditions.
(B) Does the patient have side effects from any medication(s) that would impair the driver's ability to safely operate a motor vehicle? Mark YES or NO and explain.
(C) Is the driver compliant with medication and treatment regime? Mark YES or NO and explain.
(D) is the box for NO MEDICATIONS PRESCRIBED.
Current status of condition

Required: mark the current status of condition as (A) controlled, (B) not controlled: will not affect driving or (C) not controlled: may affect driving.
If Not Controlled is marked, you must provide details, which may include pertinent clinical information, i.e., test results, lab values.
Impaired ability and attack of unconsciousness

Required: in the past six months, has the driver's ability to safely operate a motor vehicle been impaired (for any reason), or has the driver experienced an attack of unconsciousness? Mark YES or NO and enter the date of attack.
If YES, you must provide details, which may include pertinent clinical information.
Enter the date of last impaired ability to safely operate a motor vehicle or attack of unconsciousness, and you must provide details, which may include pertinent clinical information.
Section III, Provider

Section III, Provider: how long have you been treating this driver?
Is the driver being treated by any other providers? Mark YES or NO.
If Question 2 is YES, enter the name of physician and contact information.
If treated by another provider, a statement regarding medical and mental fitness to operate a motor vehicle or a completed Medical Report is required by that provider.
Section IV, additional information and special restrictions

Section IV is for additional information, special restrictions, etc.
Section V, the MD/DO or medical professional signs
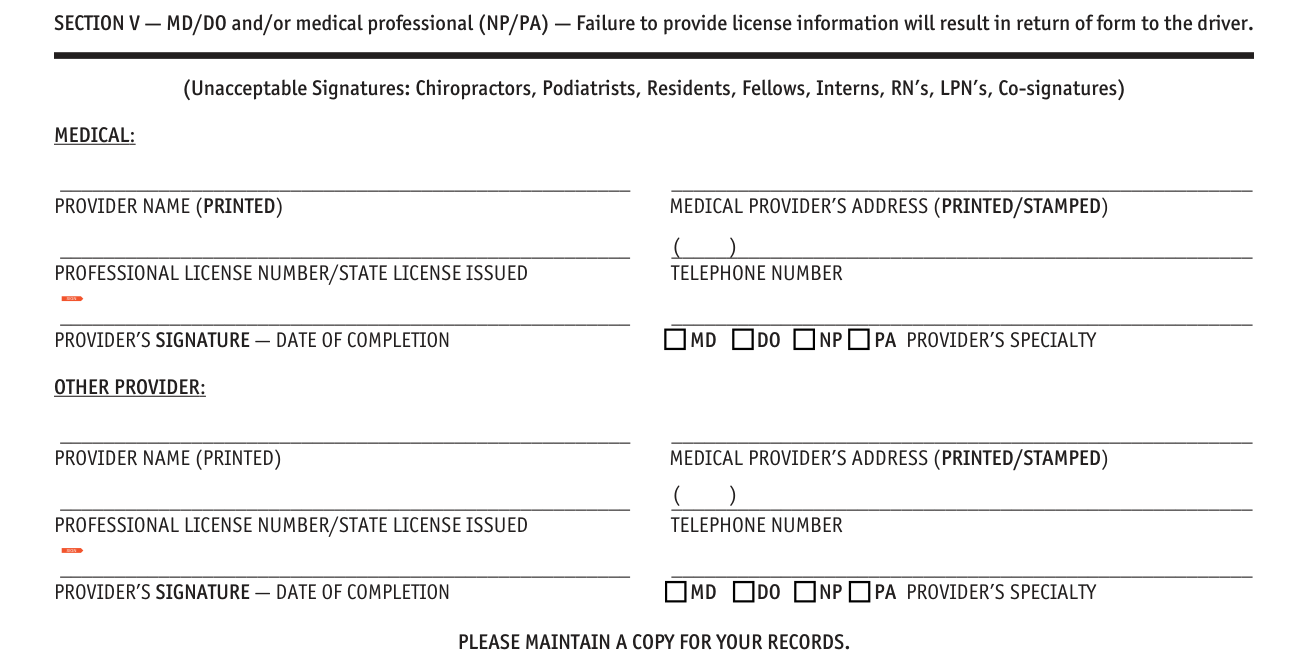
Section V is for the MD/DO and/or medical professional (NP/PA); failure to provide license information will result in return of form to the driver.
Unacceptable signatures: Chiropractors, Podiatrists, Residents, Fellows, Interns, RN's, LPN's, Co-signatures.
Under MEDICAL and under OTHER PROVIDER, enter the provider name (printed), the medical provider's address (printed/stamped), the professional license number/state license issued and the telephone number; sign with the date of completion and mark MD, DO, NP or PA as the provider's specialty.
More rules for Form DSD DC-163.10
Please maintain a copy for your records.
DRIVER ANALYSIS DIVISION, 2701 S. DIRKSEN PARKWAY, SPRINGFIELD, IL 62723.
Where to get help with Form DSD DC-163.10
See guidelines at ilsos.gov, search for Medical/Vision Conditions, for completion of the form.
Sources
[1] Form DSD DC-163.10 (February 2026), Medical Report For Conditions That May Impair Driving Safely, Office of the Secretary of State of Illinois (the Official source link on this page).