

Medical Report for Assessor at a glance
What it is: An Assessor issues this Medical Report to gather additional medical information, such as if the customer may benefit from a program of support and if the customer is eligible to enter the Supported Wage System.
Who signs: 13 Details of doctor completing this report: Signature.
The Medical Report must be fully completed by a treating doctor or specialist. This information will help the Australian Government Department of Human Services in determining: income support eligibility; if the customer may benefit from a program of support, for example rehabilitation or training; if the customer is eligible to enter the Supported Wage System.
A filled-in Medical Report for Assessor example: Customer's details and the Assessor lines on page 1

How to fill out Medical Report for Assessor, box by box
Customer's details
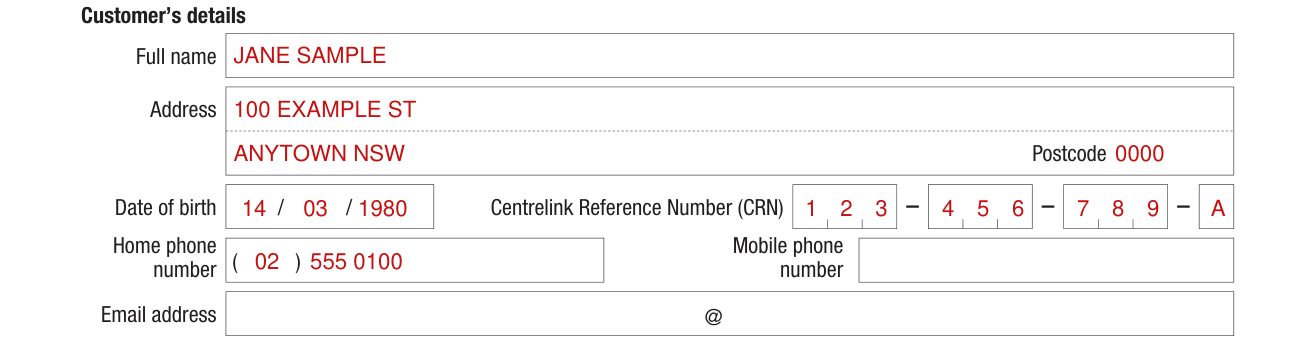
Make sure your details are completed: under Customer's details, enter Full name, Address, Postcode, Date of birth, Centrelink Reference Number (CRN), Home phone number, Mobile phone number and Email address.
To be completed by the Assessor issuing the Medical Report

The Assessor issuing the Medical Report completes the Full name, Organisation and Date.
More rules for Medical Report for Assessor
Contact your doctor and make an appointment to have the Medical Report completed. Make sure the doctor and their receptionist know that you will need this report completed, as a long consultation may be required. If your doctor does not Bulk Bill, your consultation fee may be more than usual because of the extra time taken to complete the report.
Please use black or blue pen.
The personal information that is provided to you for the purpose of this report must be kept confidential under section 202 of the Social Security (Administration) Act 1999. It cannot be disclosed to anyone else unless authorised by law.
Human Services, including staff from the Health Professional Advisory Unit, may make contact with you to discuss the information in your report. These contacts will only occur where information requires clarification.
If there are more than 2 conditions that have a significant impact on ability to function, attach a separate sheet with details.
If your situation is different
The patient and the conditions that have a significant impact on ability to function
This person has been my patient since / / or a patient at this practice since / /.
Does the patient have a medical condition that may significantly reduce their life expectancy? If No, you do not need to complete question 3; go to 4. If Yes, enter the Diagnosis and go to next question.
Is the average life expectancy of a person with this condition shorter than 24 months? If No, go to next question. If Yes, you do not need to complete questions 4 to 8; go to 9.
Does the patient have one or more medical conditions that have a significant impact on their ability to function? If No, you do not need to complete question 5; go to 6. If Yes, go to next question.
5 Give details about the conditions that have a significant impact on the patient's ability to function. List conditions in order of degree of impact on ability to function, starting with the condition with most impact.
Condition 1: A Diagnosis
Condition 1-condition with most impact, A Diagnosis: enter the Diagnosis, the Date of onset (if known) and the Date of diagnosis. The diagnosis is Presumptive or Confirmed. Are further investigations/tests planned to confirm the diagnosis? No or Yes. Is the diagnosis supported by further specialist opinion? If Yes, give details.
Enter the Name of the Psychiatrist/ Clinical Psychologist, the Audiologist/Ear, Nose and Throat specialist, the Ophthalmologist, or Other Name and specialty. Are the relevant specialist reports available? If Yes, mark Attached or Will provide on request.
Condition 1: B Current treatment
B Current treatment: Provide details of all current treatment for this condition (e.g. hospitalisation, surgery, medication and dosage, counselling, physical therapy, rehabilitation, frequency of treatment), with the Date commenced.
C Past treatment, D Specialist consultation, E Future/planned treatment and F Patient's compliance
C Past treatment: Provide details of past treatment for this condition, with the Treatment type, Date commenced and Duration of treatment.
D Specialist consultation: Have you or another doctor from your practice previously referred this patient to a specialist? If Yes, give details: Name, Specialty and Date of consultation.
E Future/planned treatment: Provide details of any further scheduled or proposed treatment with estimates of likely dates of commencement and expected duration.
F Patient's compliance with recommended treatment: mark Very compliant, Usually compliant, Rarely compliant or Uncertain. Detail any issues related to accessing or undertaking suitable treatment that affect the level of compliance.
G Current symptoms and H History
G Current symptoms: Describe current symptoms. Be specific and include severity, frequency and duration. Note: symptoms are those persisting despite treatment, aids, equipment or assistive technology.
H History: Provide details of underlying causes and contributing factors, results and dates of investigations/procedures and specialist consultations (e.g. radiology, pathology, RFTs, specialist reports).
Impact on ability to function: persist for and the next 2 years
i Details about how this condition and its treatment currently impact on the patient's ability to function: Be specific and consider the impacts on endurance, movement/dexterity, neurological/cognitive function, functions of consciousness, behaviour, planning, interpersonal relationships, sensory function, digestive, reproductive, continence function and need for care.
J The impact of this condition on the patient's ability to function is expected to persist for: Less than 3 months, 3-24 months or More than 24 months.
K Within the next 2 years the effect of this condition on the patient's ability to function is expected to: Resolve, Significantly improve, Slightly improve, Fluctuate, Remain unchanged, Deteriorate or Uncertain. Provide details.
For a second condition that has a significant impact on ability to function, go to Condition 2, on the next page. If there are no other conditions that have a significant impact on ability to function, go to question 6 on page 10.
Other medical conditions that are generally well managed and other information
Does the patient have any other medical conditions that are generally well managed and that cause minimal or limited impact on ability to function? If No, go to next question. If Yes, give details.
Is there any other information that you would like to provide? If No, go to next question. If Yes, give details.
Certification
Do you wish to provide medical certificate details on this report? If No, go to next question. If Yes, under Certification, I examined this person on / /. In my opinion this person is temporarily unfit for work or study from / / to / /, and can or cannot currently do their usual work or study or any other work for 8 hours or more per week.
Release of medical information
Release of medical information. Is there any information in this report which, if released to the patient, might be prejudicial to his/her physical or mental health? If No, go to next question. If Yes, identify the information and state why it should not be released directly to the patient.
Details of doctor completing this report
13 Details of doctor completing this report. Please print in BLOCK LETTERS or use a stamp. Enter Name, Professional qualifications, Address, Postcode and Phone number, then Signature, Date and Stamp (if applicable).
Common questions about Medical Report for Assessor
Where do I file it?
You can give this report and any attachments to your patient or you can return this report directly to Disability Services. However, if you answered 'Yes' at question 9, please make sure to return this report directly to Disability Services, Reply Paid 7806, CANBERRA BC ACT 2610.
Is there a penalty?
There are penalties for offences against section 202 of the Social Security (Administration) Act 1999.
Sources
[1] Medical Report for Assessor (SA433.1207), Australian Government Department of Human Services (the Official source link on this page).