

Cologuard Order Requisition Form at a glance
What it is: The COLOGUARD ORDER REQUISITION FORM of EXACT SCIENCES LABORATORIES, LLC orders the stool-based DNA test with hemoglobin immunoassay component.
Where and when to file: Fax the completed Cologuard Order Requisition Form to 844-870-8875.
Certification: I am a licensed healthcare provider authorized to order Cologuard.
A filled-in Cologuard Order Requisition Form example: a clinic orders Cologuard for a patient with private insurance
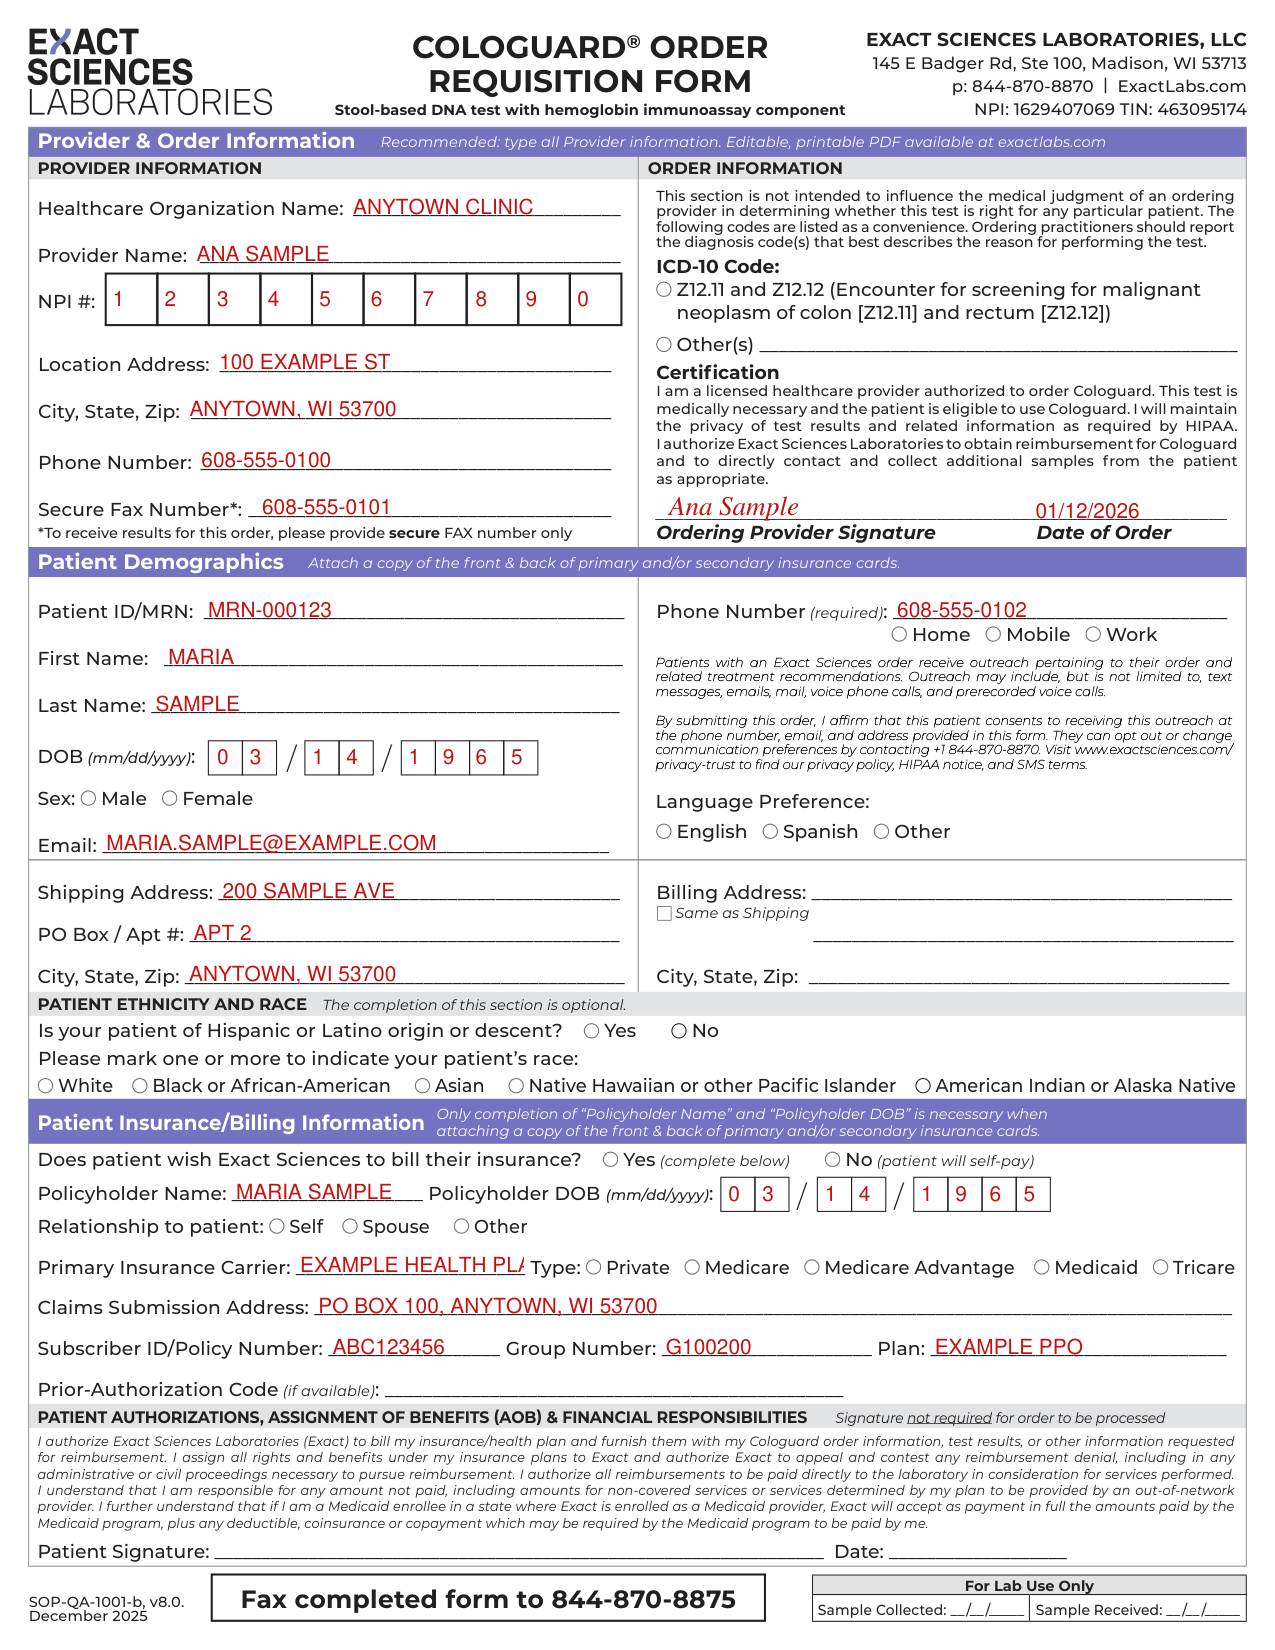
How to fill out Cologuard Order Requisition Form, box by box
Provider information

Provider & Order Information: Recommended: type all Provider information.
To receive results for this order, please provide secure FAX number only.
ICD-10 Code

ICD-10 Code: Z12.11 and Z12.12 (Encounter for screening for malignant neoplasm of colon [Z12.11] and rectum [Z12.12]).
Ordering practitioners should report the diagnosis code(s) that best describes the reason for performing the test. This section is not intended to influence the medical judgment of an ordering provider in determining whether this test is right for any particular patient.
Ordering provider certification and signature

This test is medically necessary and the patient is eligible to use Cologuard. I will maintain the privacy of test results and related information as required by HIPAA.
I authorize Exact Sciences Laboratories to obtain reimbursement for Cologuard and to directly contact and collect additional samples from the patient as appropriate.
Sign the Ordering Provider Signature line and write the Date of Order.
Patient Demographics

Patient Demographics: Attach a copy of the front & back of primary and/or secondary insurance cards.
Phone Number (required): mark Home, Mobile or Work.
Patients with an Exact Sciences order receive outreach pertaining to their order and related treatment recommendations. Outreach may include, but is not limited to, text messages, emails, mail, voice phone calls, and prerecorded voice calls. By submitting this order, I affirm that this patient consents to receiving this outreach at the phone number, email, and address provided in this form.
Patient ethnicity and race

PATIENT ETHNICITY AND RACE: The completion of this section is optional.
Is your patient of Hispanic or Latino origin or descent? Yes or No. Please mark one or more to indicate your patient's race: White, Black or African-American, Asian, Native Hawaiian or other Pacific Islander, American Indian or Alaska Native.
Patient Insurance/Billing Information
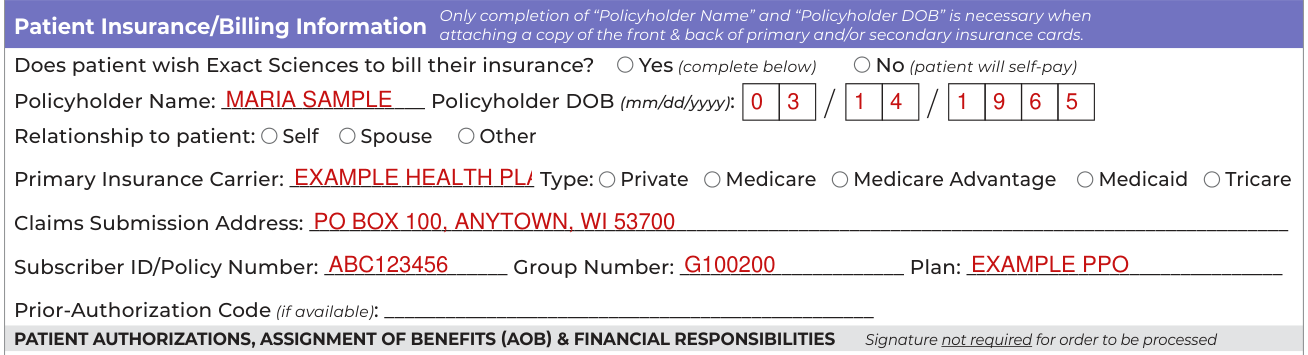
Patient Insurance/Billing Information: Does patient wish Exact Sciences to bill their insurance? Yes or No (patient will self-pay).
Only completion of “Policyholder Name” and “Policyholder DOB” is necessary when attaching a copy of the front & back of primary and/or secondary insurance cards.
Policyholder Name, Policyholder DOB (mm/dd/yyyy) and Relationship to patient: Self, Spouse or Other.
Primary Insurance Carrier, Type: Private, Medicare, Medicare Advantage, Medicaid or Tricare.
Enter the Prior-Authorization Code if it is available.
Patient authorizations, assignment of benefits (AOB) & financial responsibilities

PATIENT AUTHORIZATIONS, ASSIGNMENT OF BENEFITS (AOB) & FINANCIAL RESPONSIBILITIES: Signature not required for order to be processed.
I authorize Exact Sciences Laboratories (Exact) to bill my insurance/health plan and furnish them with my Cologuard order information, test results, or other information requested for reimbursement. I assign all rights and benefits under my insurance plans to Exact and authorize Exact to appeal and contest any reimbursement denial, including in any administrative or civil proceedings necessary to pursue reimbursement.
I understand that I am responsible for any amount not paid, including amounts for non-covered services or services determined by my plan to be provided by an out-of-network provider.
I further understand that if I am a Medicaid enrollee in a state where Exact is enrolled as a Medicaid provider, Exact will accept as payment in full the amounts paid by the Medicaid program, plus any deductible, coinsurance or copayment which may be required by the Medicaid program to be paid by me.
Common questions about Cologuard Order Requisition Form
Where do I file it?
Fax the completed Cologuard Order Requisition Form to 844-870-8875.
Sources
[1] Cologuard Order Requisition Form (SOP-QA-1001-b, v8.0, December 2025), Exact Sciences Laboratories, LLC (the Official source link on this page).
