


Commercial Insurance Questionnaire at a glance
What it is: Commercial Insurance Questionnaire: this form is not an insurance policy, it is general information necessary to prepare a quotation.
A filled-in Commercial Insurance Questionnaire example: a landscaper requests general liability

How to fill out Commercial Insurance Questionnaire, box by box
General information

Under GENERAL INFORMATION, enter the Applicant Name, Business Name and DBA (if applicable). For the Mailing Street Address, enter City, County, State, Zip, Phone, Fax and Email. Also enter the Location Street Address with City, County, State and Zip. Then enter the Principal Contact Name, Phone and Email.
Legal Entity

Under Legal Entity (Check one), check one of Corporation, LLC, Partnership, Individual, Not For Profit or Other (please specify).
Business details

Enter the Date Business Established, FEIN, SIC Code, Years in Operation and Years of Owner Experience in Industry.
Write the Description of Operations (Min. 10 Words).
Under Number of Employees, enter Full Time and Part Time, then the Gross Annual Payroll and the Gross Annual Revenue.
Insurance Coverage Requested

Under Insurance Coverage Requested (Check all that apply), check Business Owners Policy (BOP), General Liability, Professional Liability, Commercial Auto, Workers' Comp or Other.
Current insurance and the new policy

Enter the Current Insurance Carrier. If no insurance, enter “NONE”.
Enter the Current Policy Expiration Date, Current Policy Retroactive Date and Current Limits.
Enter the Desired Effective Date for New Policy, Desired Limits and Desired Deductible.
Property details

Under PROPERTY DETAILS, mark Yes or No for Are you requesting Property Coverage. If no, list the current carrier; if no current insurance, enter “NONE”. Also mark Yes or No for Is there Boiler Machinery Coverage Exposure, Is there Earthquake Sprinkler Leakage Exposure, Is there Underground Tank Leakage Exposure and Do employees handle cash.
Building Ownership

Under Building Ownership (Check one), check one of Owned, Triple Net Lease or Lease.
Location 1 and Building Information
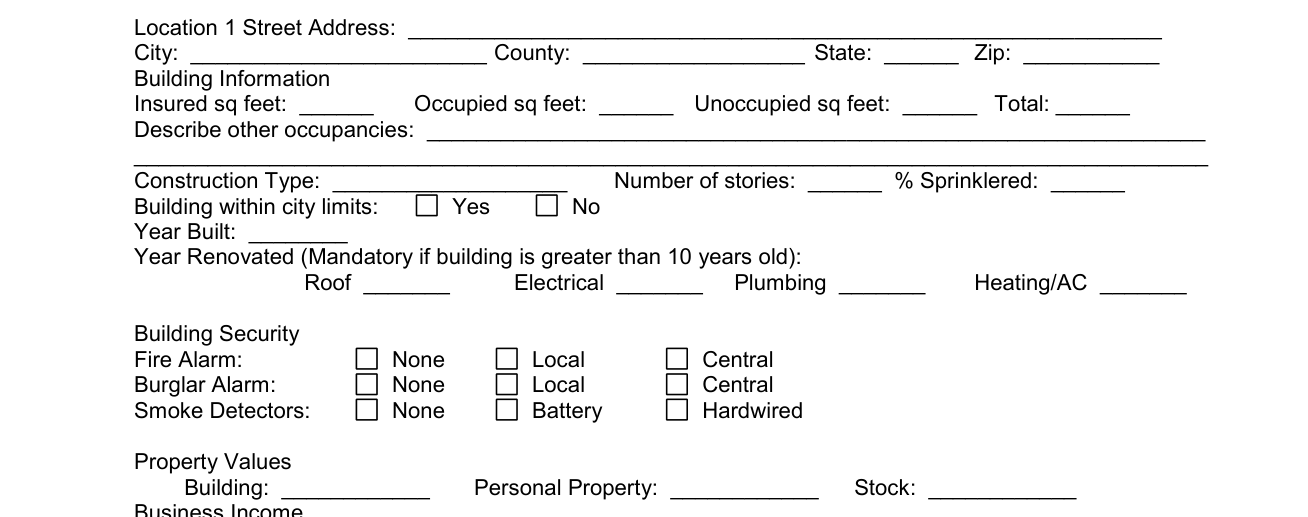
For Location 1, enter the Street Address, then City, County, State and Zip.
Under Building Information, enter Insured sq feet, Occupied sq feet, Unoccupied sq feet and Total. Then enter Describe other occupancies, Construction Type, Number of stories, % Sprinklered and Year Built, and mark Building within city limits Yes or No.
Year Renovated is mandatory if the building is greater than 10 years old.
Enter Roof, Electrical, Plumbing and Heating/AC.
Building Security and property values

Under Building Security, mark Fire Alarm as None, Local or Central, Burglar Alarm as None, Local or Central, and Smoke Detectors as None, Battery or Hardwired.
Under Property Values, enter Building, Personal Property and Stock. Under Business Income, enter Annual Gross Revenue and Estimate Annual Payroll.
Complete the Property section for all additional locations.
General liability
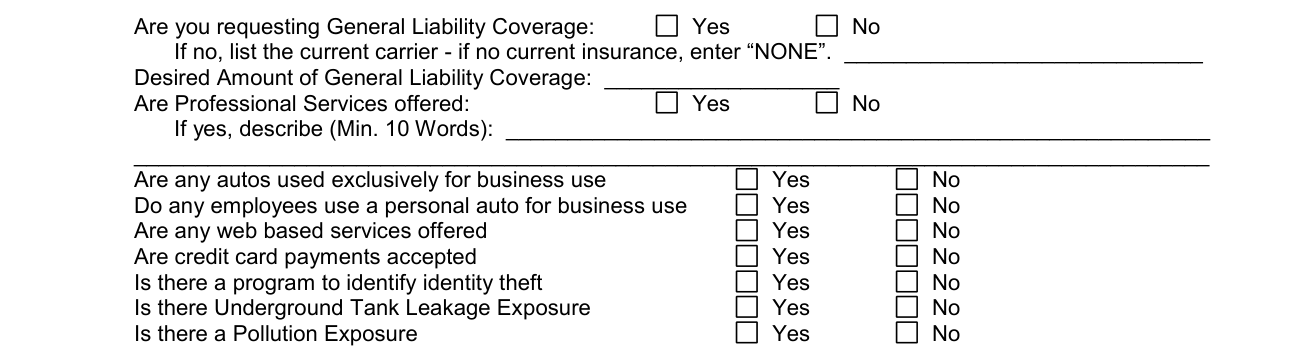
Under GENERAL LIABILITY, mark Yes or No for Are you requesting General Liability Coverage. Where it is No, write the current carrier, and enter “NONE” if there is no current insurance. Then enter the Desired Amount of General Liability Coverage.
Mark Yes or No for Are Professional Services offered. If yes, describe (Min. 10 Words).
Mark Yes or No for Are any autos used exclusively for business use, Do any employees use a personal auto for business use, Are any web based services offered, Are credit card payments accepted, Is there a program to identify identity theft, Is there Underground Tank Leakage Exposure and Is there a Pollution Exposure.
Professional liability
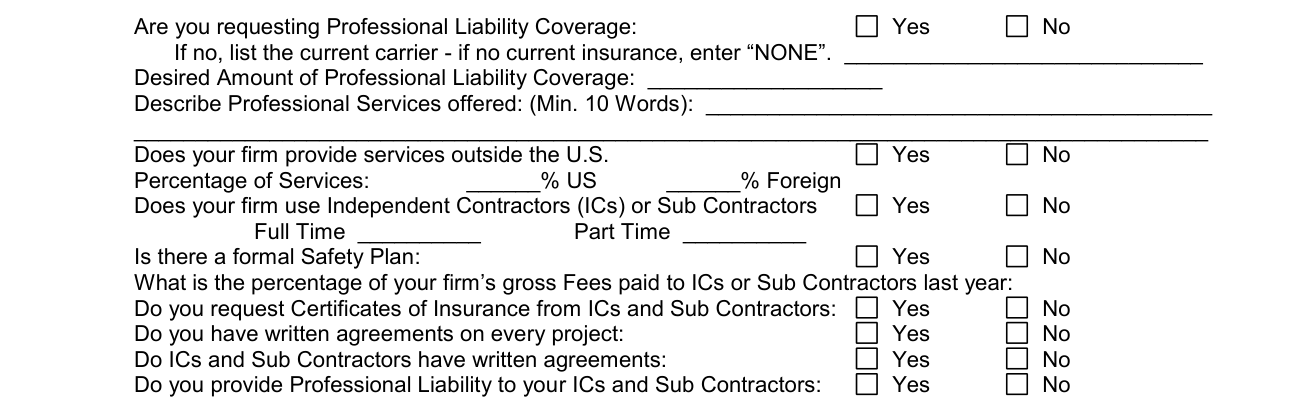
Under PROFESSIONAL LIABILITY, mark Yes or No for Are you requesting Professional Liability Coverage. On No, list the current carrier, or with no current insurance enter “NONE”. Then enter the Desired Amount of Professional Liability Coverage and Describe Professional Services offered (Min. 10 Words).
Mark Yes or No for Does your firm provide services outside the U.S. and enter the Percentage of Services, in the U.S. and Foreign.
Mark Yes or No for Does your firm use Independent Contractors (ICs) or Sub Contractors, and enter Full Time and Part Time.
Enter the percentage of your firm's gross Fees paid to ICs or Sub Contractors last year, then mark Yes or No for Is there a formal Safety Plan, Do you request Certificates of Insurance from ICs and Sub Contractors, Do you have written agreements on every project, Do ICs and Sub Contractors have written agreements and Do you provide Professional Liability to your ICs and Sub Contractors.
Allied medical and medical professional liability
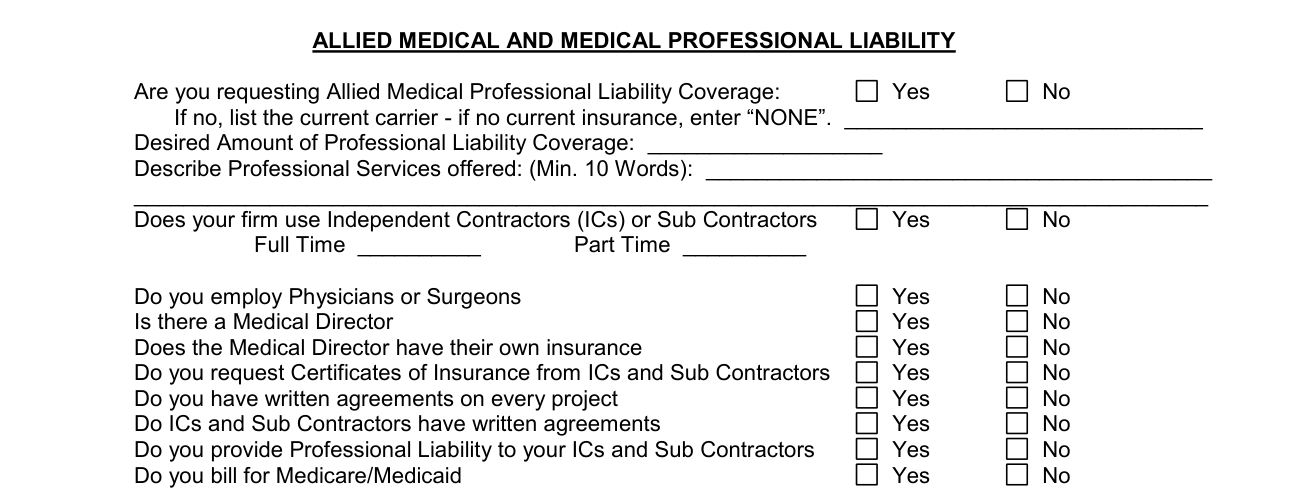
Under Allied Medical and Medical Professional Liability, mark Yes or No for Are you requesting Allied Medical Professional Liability Coverage. If No, write the current carrier, or “NONE” if you have no current insurance. Also enter a Desired Amount of Professional Liability Coverage, and Describe Professional Services offered (Min. 10 Words).
Mark Yes or No for Does your firm use Independent Contractors (ICs) or Sub Contractors, entering Full Time and Part Time, Do you employ Physicians or Surgeons, Is there a Medical Director, Does the Medical Director have their own insurance, Do you request Certificates of Insurance from ICs and Sub Contractors, Do you have written agreements on every project, Do ICs and Sub Contractors have written agreements, Do you provide Professional Liability to your ICs and Sub Contractors and Do you bill for Medicare/Medicaid.
Workers' compensation
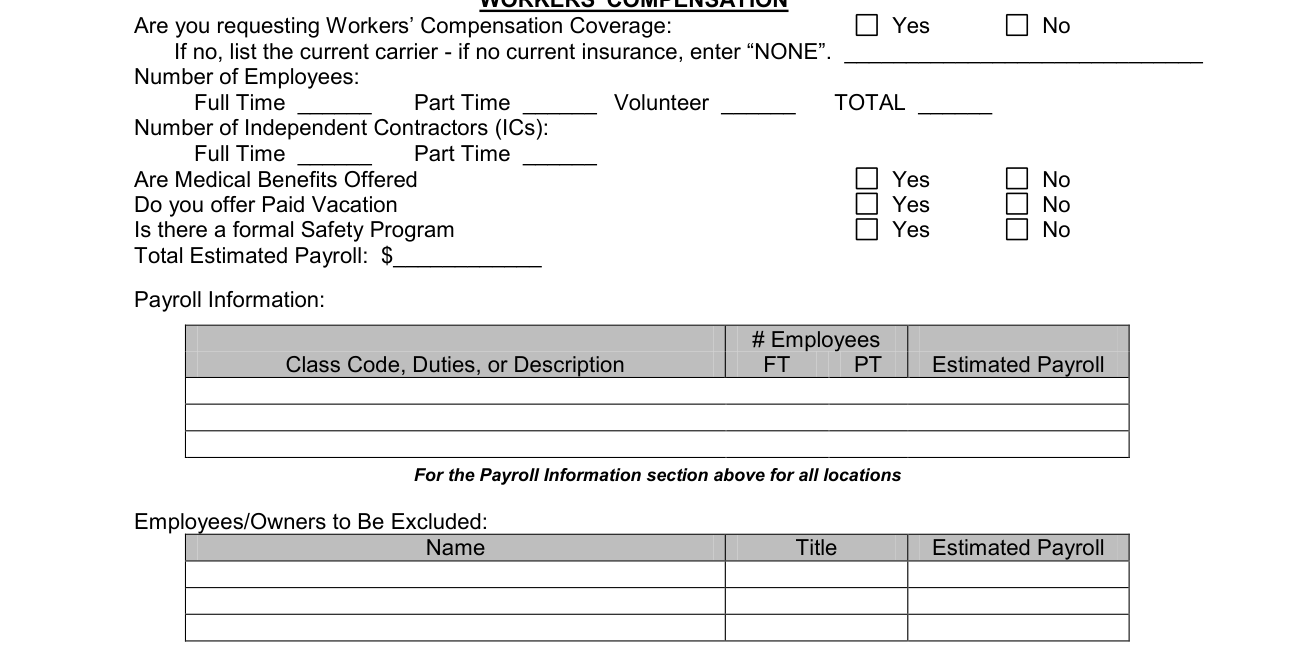
Under WORKERS' COMPENSATION, mark Yes or No for Are you requesting Workers' Compensation Coverage. Under No, list the current carrier; with no current insurance, enter “NONE”.
Enter the Number of Employees as Full Time, Part Time, Volunteer and TOTAL, and the Number of Independent Contractors (ICs) as Full Time and Part Time.
Mark Yes or No for Are Medical Benefits Offered, Do you offer Paid Vacation and Is there a formal Safety Program, then enter the Total Estimated Payroll.
Under Payroll Information, enter # Employees, Class Code, Duties, or Description, FT, PT and Estimated Payroll, for all locations.
Under Employees/Owners to Be Excluded, enter Name, Title and Estimated Payroll.
Additional coverage interests

Under ADDITIONAL COVERAGE INTERESTS, check all that apply: Commercial Umbrella, Buy/Sell Agreement, Crime/Employee Dishonesty, Cyber Liability, Directors and Officer Liability, Employment Practices Liability, Bonds, Medicare/Medicaid Billing E&O, Regulatory Shut Down or Other.
More rules for Commercial Insurance Questionnaire
Many carriers require a complete signed carrier application specific to their product offerings.
Sources
[1] Commercial Insurance Questionnaire (the served file; no issuer file found) (the Official source link on this page).