
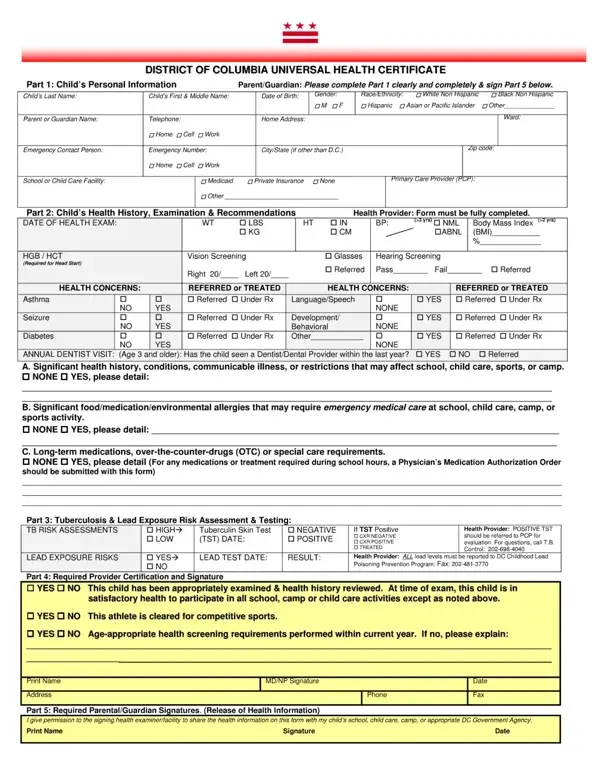

Universal Health Certificate at a glance
What it is: The Universal Health Certificate is the form to report your child's physical health to their school/child care facility, required by DC Official Code §38-602, with part 2-4 completed by a licensed medical professional.
Who signs: Sign on Parent/Guardian Signature and write the Date.
A filled-in Universal Health Certificate example: a parent fills in Part 1
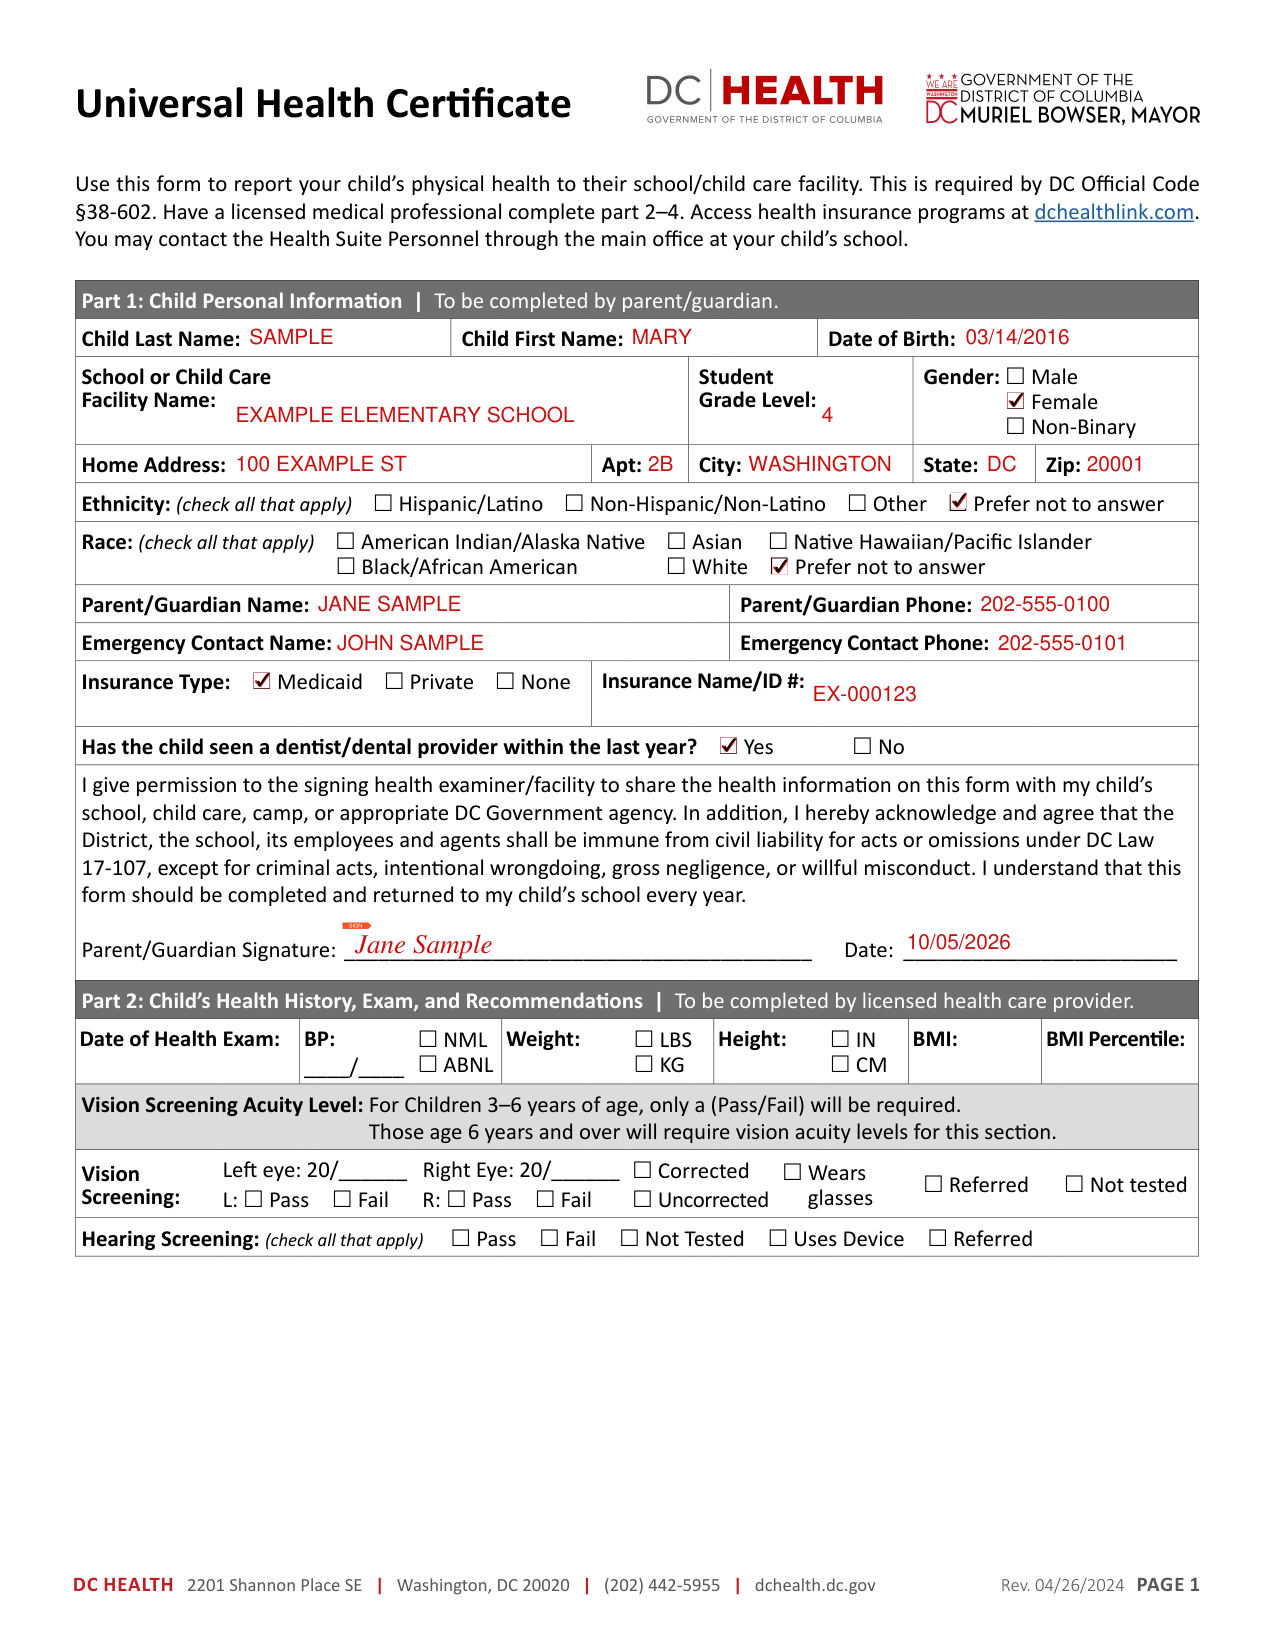
How to fill out Universal Health Certificate, box by box
Part 1: Child Personal Information
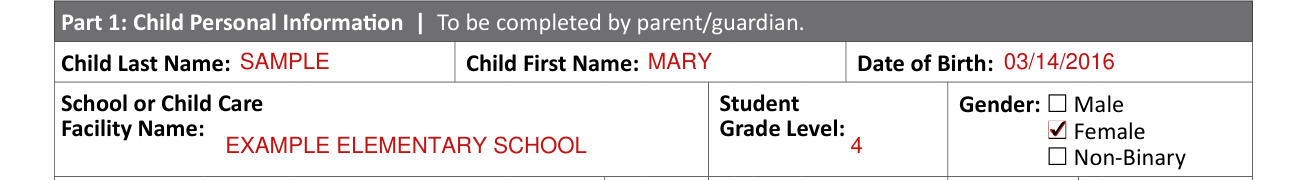
Part 1: Child Personal Information is to be completed by parent/guardian.
Enter the Child Last Name, Child First Name and Date of Birth.
Enter the School or Child Care Facility Name and the Student Grade Level, then mark Gender: Male, Female or Non-Binary.
Home Address
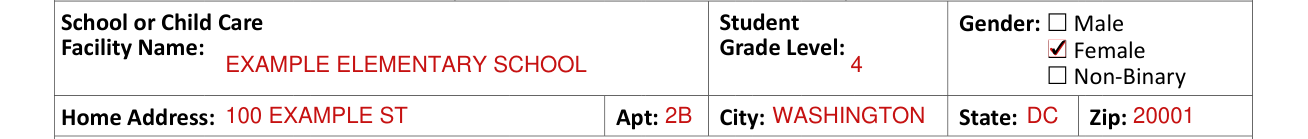
Enter the Home Address, Apt, City, State and Zip.
Ethnicity and Race
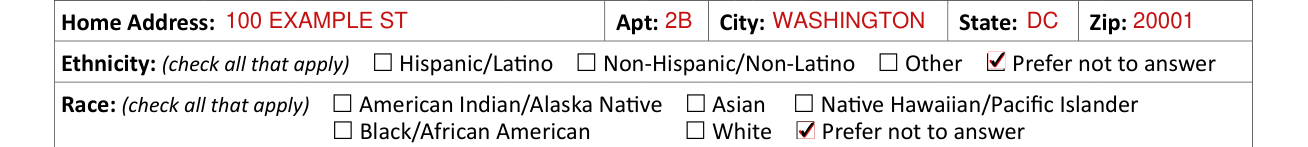
Ethnicity: check all that apply: Hispanic/Latino, Non-Hispanic/Non-Latino, Other, Prefer not to answer.
Race: check all that apply: American Indian/Alaska Native, Asian, Native Hawaiian/Pacific Islander, Black/African American, White, Prefer not to answer.
Parent/Guardian and Emergency Contact

Enter the Parent/Guardian Name and Parent/Guardian Phone, then the Emergency Contact Name and Emergency Contact Phone.
Insurance Type

Insurance Type: mark Medicaid, Private or None, then enter the Insurance Name/ID #.
Dentist

Mark Yes or No: has the child seen a dentist/dental provider within the last year?
Permission to share

By signing, you give permission to the signing health examiner/facility to share the health information on this form with your child's school, child care, camp, or appropriate DC Government agency. In addition, you acknowledge and agree that the District, the school, its employees and agents shall be immune from civil liability for acts or omissions under DC Law 17-107, except for criminal acts, intentional wrongdoing, gross negligence, or willful misconduct. This form should be completed and returned to your child's school every year.
Part 2: Exam and Recommendations

Part 2: Child's Health History, Exam, and Recommendations is to be completed by licensed health care provider.
Enter the Date of Health Exam, BP, Weight, Height, BMI and BMI Percentile.
Part 2: Vision Screening and Hearing Screening

Vision Screening Acuity Level: for Children 3-6 years of age, only a (Pass/Fail) will be required. Those age 6 years and over will require vision acuity levels for this section.
Vision Screening: enter the Left eye and Right Eye as 20/ and mark Pass or Fail for L and R; mark Corrected, Uncorrected, Wears glasses, Referred or Not tested.
Hearing Screening: check all that apply: Pass, Fail, Not Tested, Uses Device, Referred.
Part 2: Health Concerns
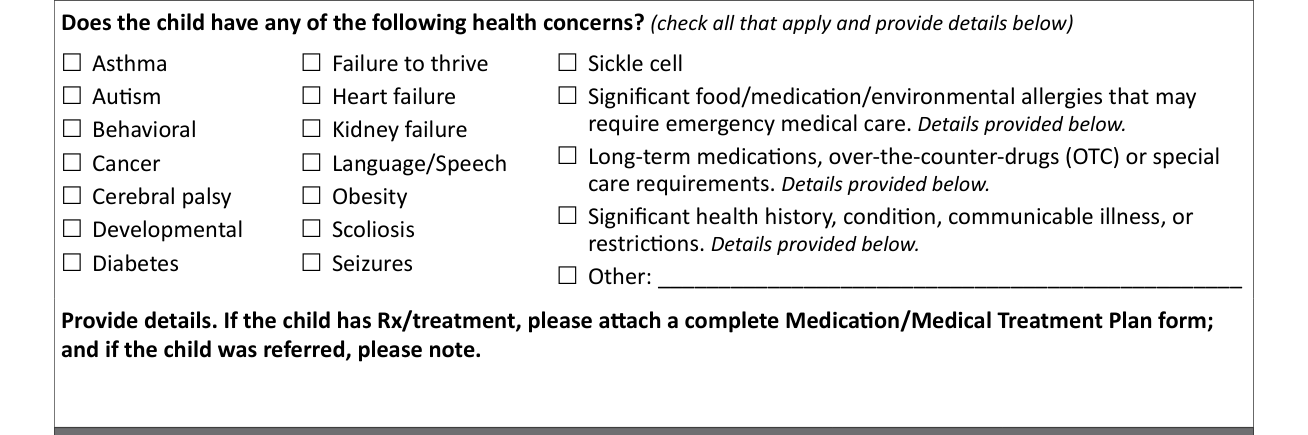
Does the child have any of the following health concerns? Check all that apply and provide details.
Significant food/medication/environmental allergies that may require emergency medical care. Details provided.
Long-term medications, over-the-counter-drugs (OTC) or special care requirements. Details provided.
Significant health history, condition, communicable illness, or restrictions. Details provided.
Provide details.
If the child has Rx/treatment, please attach a complete Medication/Medical Treatment Plan form; and if the child was referred, please note.
Part 2: TB Assessment
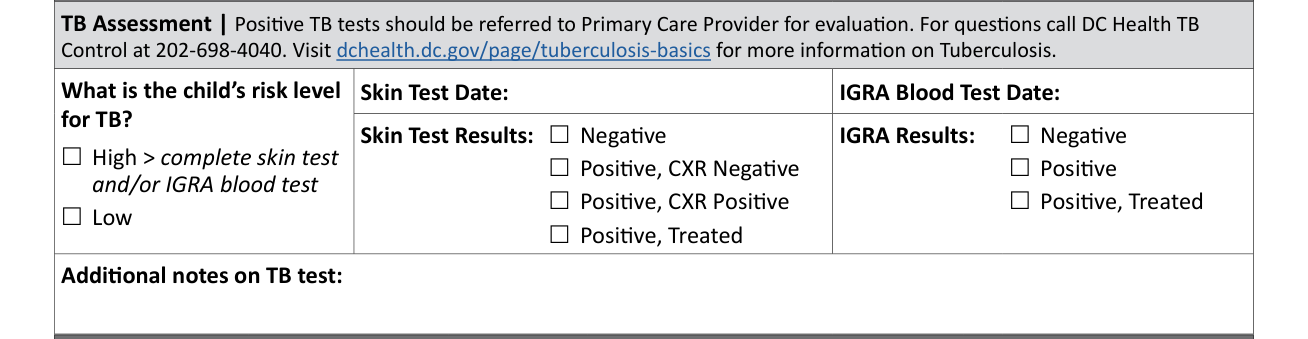
What is the child's risk level for TB? High > complete skin test and/or IGRA blood test. Low.
Positive TB tests should be referred to Primary Care Provider for evaluation.
For questions call DC Health TB Control at 202-698-4040.
Visit dchealth.dc.gov/page/tuberculosis-basics for more information on Tuberculosis.
Part 2: Lead Exposure Risk Screening
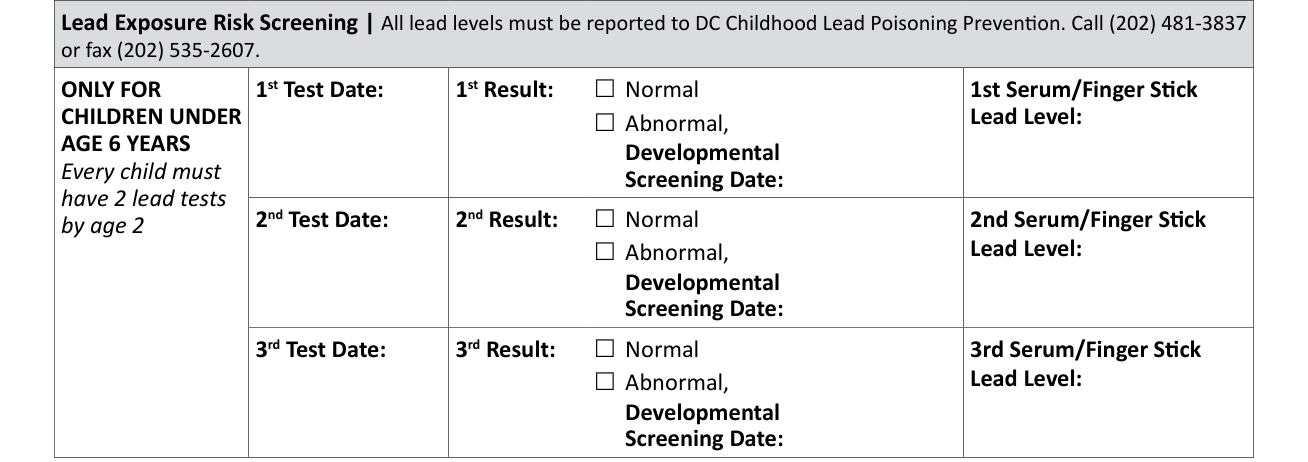
Only for children under age 6 years: every child must have 2 lead tests by age 2.
Lead Exposure Risk Screening: all lead levels must be reported to DC Childhood Lead Poisoning Prevention.
Call (202) 481-3837 or fax (202) 535-2607.
Part 3: Immunization Information
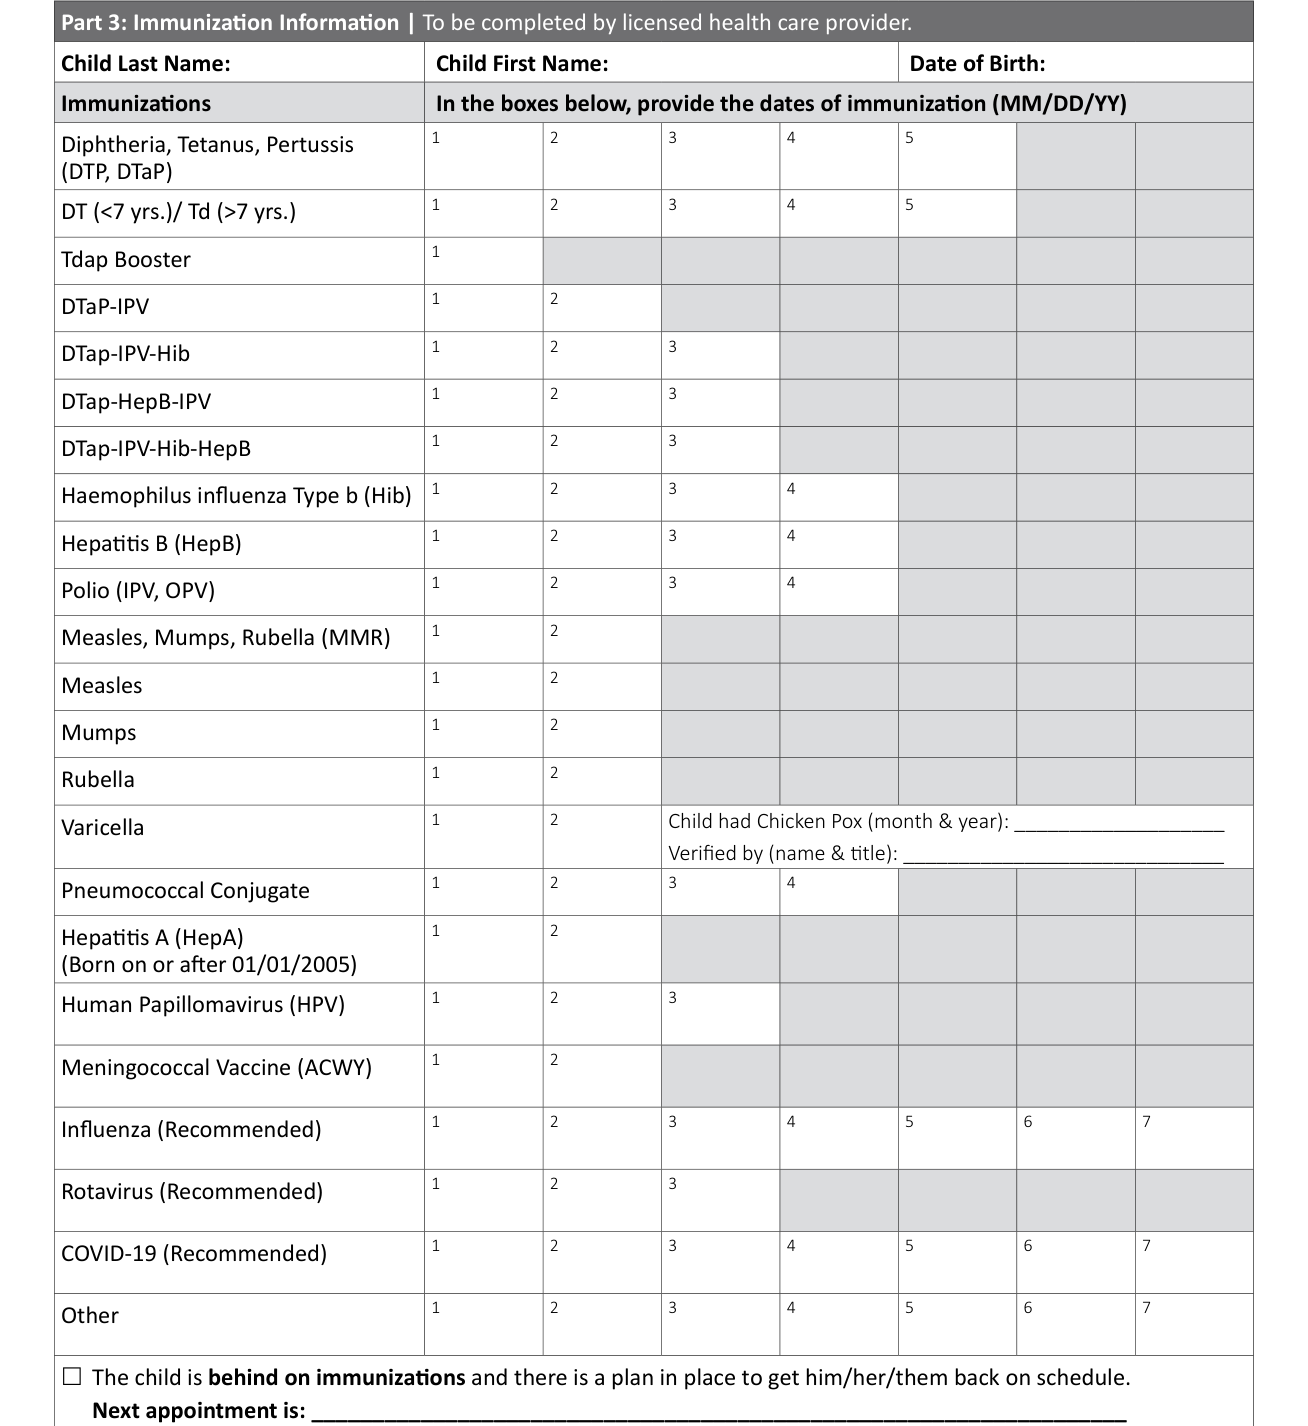
Part 3: Immunization Information is to be completed by licensed health care provider. In the boxes of Part 3, provide the dates of immunization (MM/DD/YY).
For Varicella, enter 1 and 2, or Child had Chicken Pox (month & year) and Verified by (name & title).
Hepatitis A (HepA) (Born on or after 01/01/2005).
The child is behind on immunizations and there is a plan in place to get him/her/them back on schedule.
Part 3: Medical Exemption and Alternative Proof of Immunity

Medical Exemption (if applicable): by signing you certify that the child has a valid medical contraindication(s) to being immunized at the time against Diphtheria, Tetanus, Pertussis, Hib, Hepb, Polio (All 3 serotypes), Measles, Mumps, Rubella, Varicella, Pneumococcal, Hepa, Meningococcal (ACWY), HPV or COVID-19.
Is this medical contraindication permanent or temporary? Permanent. Temporary until: (date).
Alternative Proof of Immunity (if applicable): by signing you certify that the child has laboratory evidence of immunity to Diphtheria, Tetanus, Pertussis, Hib, Hepb, Polio (All 3 serotypes), Measles, Mumps, Rubella, Varicella, Pneumococcal, Hepa or HPV, and that you have attached a copy of the titer results.
Part 4: Licensed Health Practitioner's Certifications
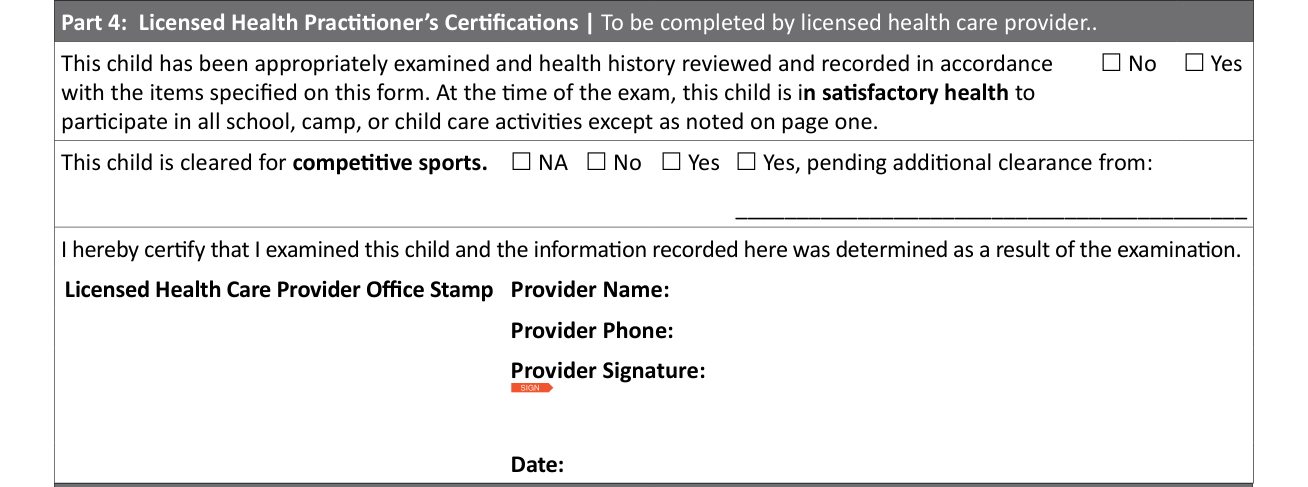
Part 4: Licensed Health Practitioner's Certifications is to be completed by licensed health care provider.
This child has been appropriately examined and health history reviewed and recorded in accordance with the items specified on this form.
At the time of the exam, this child is in satisfactory health to participate in all school, camp, or child care activities except as noted on page one. Mark No or Yes.
This child is cleared for competitive sports. Mark NA, No, Yes, or Yes, pending additional clearance.
By signing you certify that you examined this child and the information recorded here was determined as a result of the examination.
Enter the Provider Name and Provider Phone, sign on Provider Signature and write the Date.
Sources
[1] Universal Health Certificate (Rev. 04/26), DC Health (the Official source link on this page).