
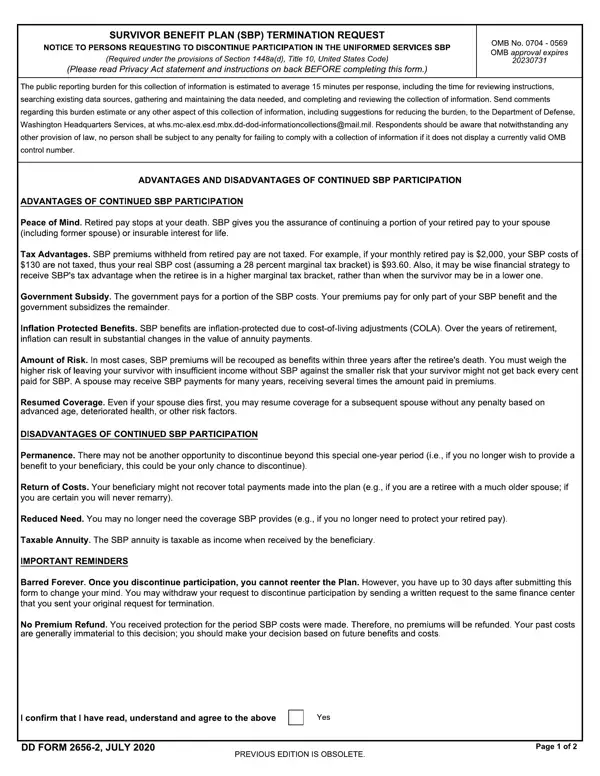

Form DD 2656-2 at a glance
What it is: Form DD 2656-2, the Survivor Benefit Plan (SBP) Termination Request, is used to voluntarily discontinue participation in the Survivor Benefit Plan (SBP).
Who signs: Read the statement carefully, then sign your name and indicate the date of your signature. Concurrence is required only if the current beneficiary is a legal spouse or former spouse. The termination form is only valid if the spouse or former spouse concurrence is witnessed by a Service-designated SBP Counselor or Notary Public.
A filled-in Form DD 2656-2 example: a retiree and spouse sign the termination
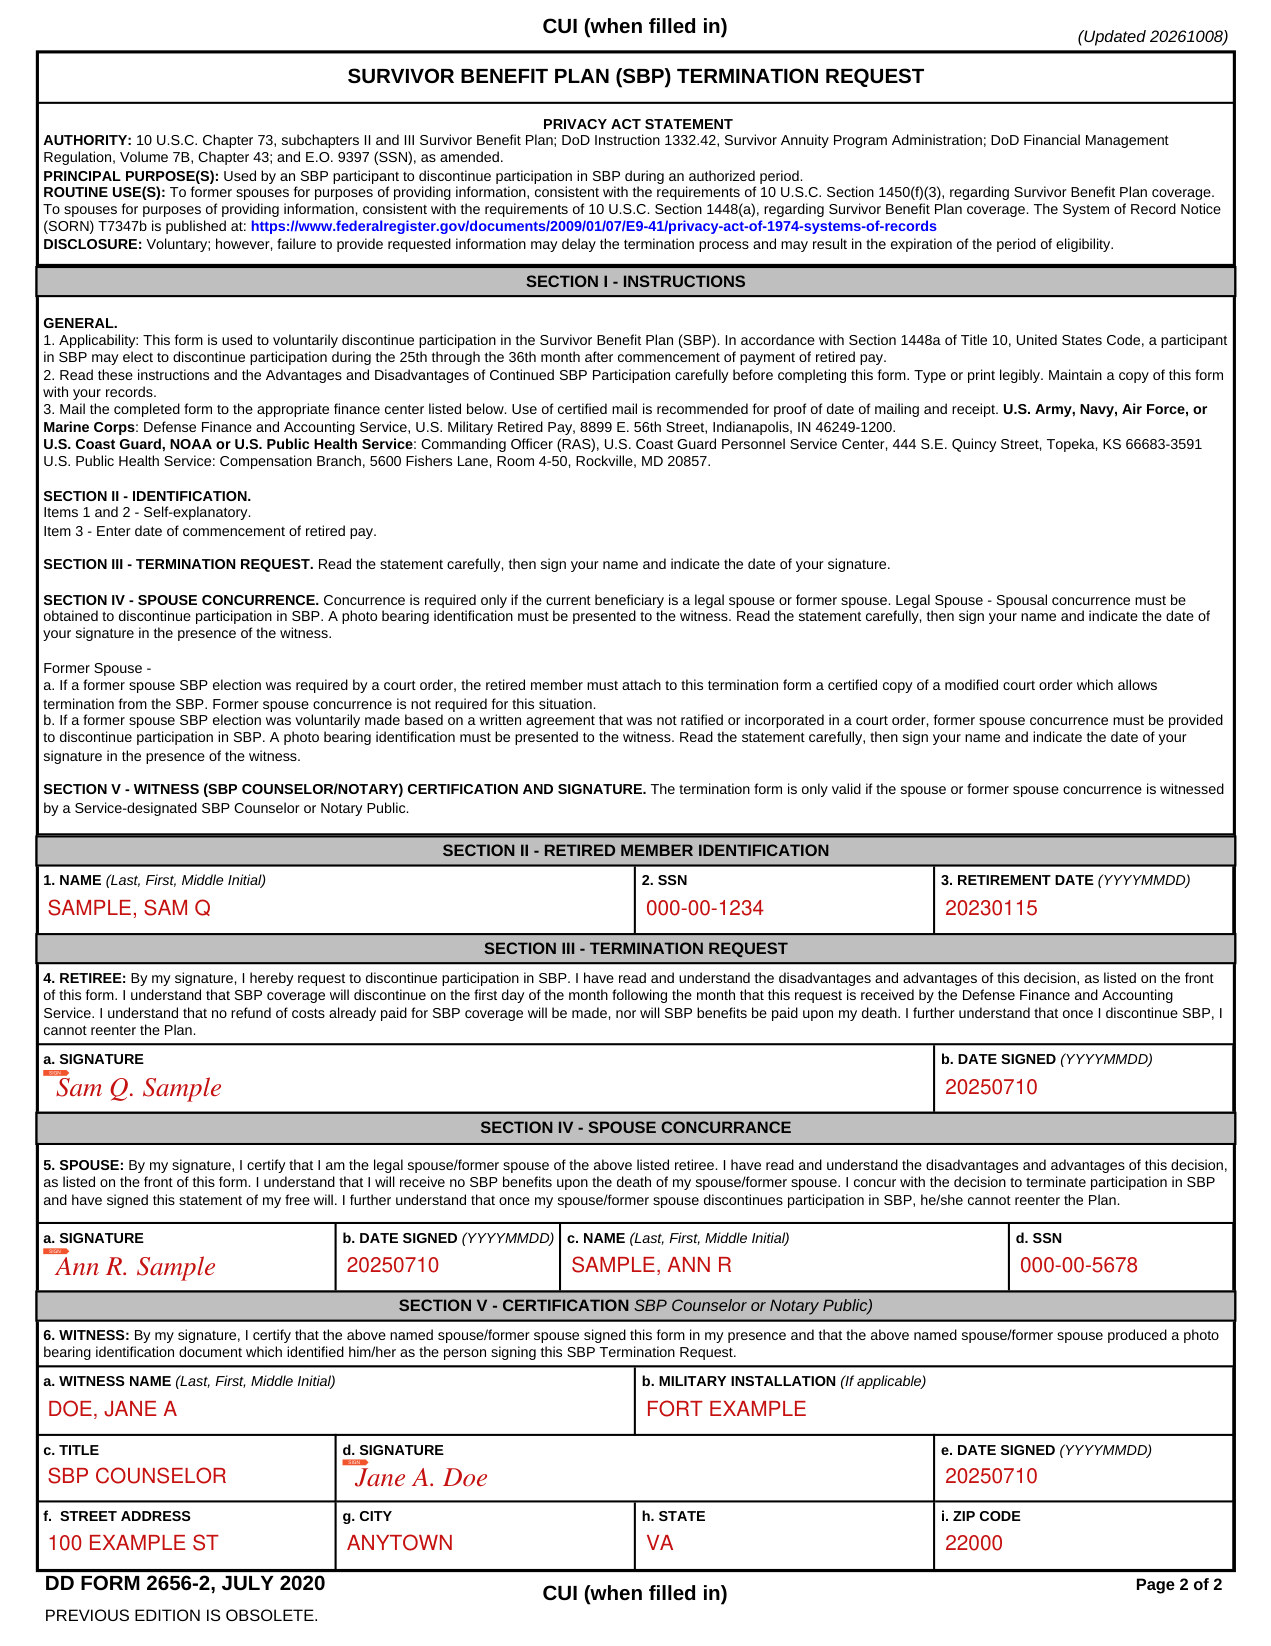
How to fill out Form DD 2656-2, box by box
Read, understand and agree to the above

Check Yes to confirm that you have read, understand and agree.
SECTION II - RETIRED MEMBER IDENTIFICATION

Items 1 and 2 are self-explanatory. In Item 3, enter the date of commencement of retired pay.
SECTION III - TERMINATION REQUEST

Read the statement carefully, then sign your name and indicate the date of your signature.
RETIREE: By your signature, you read and understand the disadvantages and advantages of this decision, as listed on the front of this form, you request to discontinue participation in SBP, and SBP coverage will discontinue on the first day of the month following the month that this request is received by the Defense Finance and Accounting Service.
No refund of costs already paid for SBP coverage will be made, nor will SBP benefits be paid upon your death. Once you discontinue SBP, you cannot reenter the Plan.
SECTION IV - SPOUSE CONCURRENCE
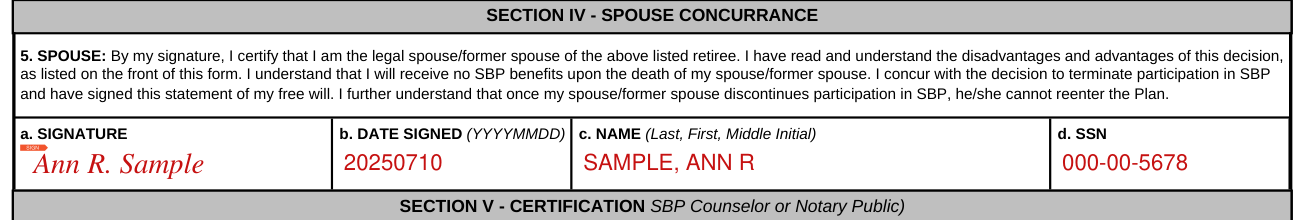
Legal Spouse: spousal concurrence must be obtained to discontinue participation in SBP.
A photo bearing identification must be presented to the witness. Read the statement carefully, then sign and date in the presence of the witness.
Former Spouse, a: If a former spouse SBP election was required by a court order, the retired member must attach to this termination form a certified copy of a modified court order which allows termination from the SBP. Former spouse concurrence is not required for this situation.
Former Spouse, b: If a former spouse SBP election was voluntarily made based on a written agreement that was not ratified or incorporated in a court order, former spouse concurrence must be provided to discontinue participation in SBP.
SPOUSE: By your signature, you certify that you are the legal spouse/former spouse of the retiree, and you concur with the decision to terminate participation in SBP.
You will receive no SBP benefits upon the death of your spouse/former spouse. You further understand that once your spouse/former spouse discontinues participation in SBP, he/she cannot reenter the Plan.
Enter the NAME (Last, First, Middle Initial) in c. and the SSN in d.
SECTION V - WITNESS (SBP COUNSELOR/NOTARY) CERTIFICATION AND SIGNATURE
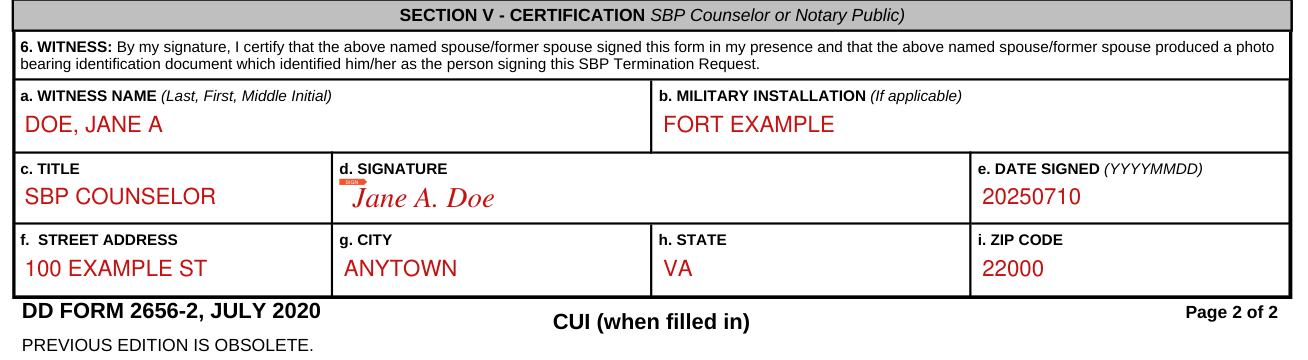
WITNESS: By your signature, you certify that the named spouse/former spouse signed this form in your presence and that the named spouse/former spouse produced a photo bearing identification document which identified him/her as the person signing this SBP Termination Request.
Enter the WITNESS NAME (Last, First, Middle Initial), MILITARY INSTALLATION (If applicable), TITLE, SIGNATURE, DATE SIGNED (YYYYMMDD), STREET ADDRESS, CITY, STATE and ZIP CODE.
More rules for Form DD 2656-2
Read these instructions and the Advantages and Disadvantages of Continued SBP Participation carefully before completing this form. Type or print legibly.
Maintain a copy of this form with your records.
Common questions about Form DD 2656-2
Is there a deadline?
In accordance with Section 1448a of Title 10, United States Code, a participant in SBP may elect to discontinue participation during the 25th through the 36th month after commencement of payment of retired pay.
Where do I file it?
Mail the completed form to the appropriate finance center. Use of certified mail is recommended for proof of date of mailing and receipt. U.S. Army, Navy, Air Force, or Marine Corps: Defense Finance and Accounting Service, U.S. Military Retired Pay, 8899 E. 56th Street, Indianapolis, IN 46249-1200. U.S. Coast Guard, NOAA or U.S. Public Health Service: Commanding Officer (RAS), U.S. Coast Guard Personnel Service Center, 444 S.E. Quincy Street, Topeka, KS 66683-3591. U.S. Public Health Service: Compensation Branch, 5600 Fishers Lane, Room 4-50, Rockville, MD 20857.
Sources
[1] Form DD 2656-2 (JULY 2020), Survivor Benefit Plan (SBP) Termination Request (the Official source link on this page).