


Aetna Group Life Proof of Death Claim Form (GC-1373-4) at a glance
What it is: This is the Proof of Death Group Life Insurance and Group Accidental Death Benefit Request, GC-1373-4.
Who signs: In G. Employer's Authorized Representative, SIGN: enter the Name, the Signature, the Date (MM/DD/YYYY) and at (city, state, zip).
What to bring and attach to Aetna Group Life Proof of Death Claim Form (GC-1373-4)
Submit this form, with attachments to the Life Insurance Service Center as soon as possible. The insured's death certificate*. Original beneficiary designation and any or all change of beneficiary requests. Enrollment forms (current and prior two years). If beneficiary(ies) are minor children: their birth certificates & Social Security numbers*, and Letters of Guardianship* or conservatorship of the estate of the minor child*. If beneficiary is the insured's estate: the Letters of Administration or Letters of Testamentary.* If beneficiary is a trust: provide copies of trust and letter of acceptance from trustee with Trust ID number. If designated beneficiary predeceased the employee: a copy of the beneficiary's death certificate and Aetna Affidavit of Sole Survivors completed by a family representative. If Accidental Death benefits are being claimed, submit police/accident, autopsy and toxicology reports with any available newspaper articles concerning the accident, if the reports are available.*
A filled-in Aetna Group Life Proof of Death Claim Form (GC-1373-4) example: an employer claims Term Life after an employee's death

How to fill out Aetna Group Life Proof of Death Claim Form (GC-1373-4), box by box
The Deceased's Name, Social Security Number, Birthdate, Date of Death, Age and Gender

Enter the Deceased's Name (last, first, middle initial), Relationship to Employee, Social Security Number, Birthdate (MM/DD/YYYY), Date of Death (MM/DD/YYYY), Age and Gender.
If deceased is known by any other name, provide Name (last, first, middle initial).
Enter the Last Residence: Street, City, State and Zip.
The Employee's Name, Social Security Number and Last Residence
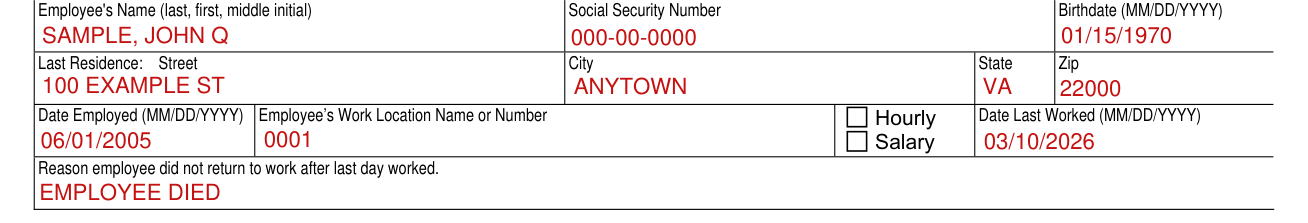
In B. Information About the Employee, enter the Employee's Name (last, first, middle initial), Social Security Number, Birthdate (MM/DD/YYYY) and Last Residence: Street, City, State and Zip.
Enter the Date Employed (MM/DD/YYYY), the Employee's Work Location Name or Number, Hourly or Salary, the Date Last Worked (MM/DD/YYYY) and the Reason employee did not return to work after last day worked.
The Employer's Name, Representative, Telephone Number and Fax Number
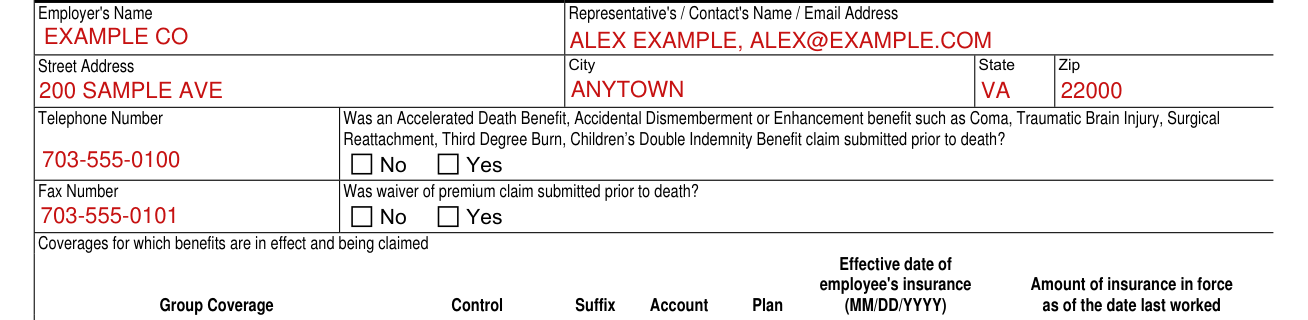
In C. Information About the Employee's Coverage, enter the Employer's Name, Representative's / Contact's Name / Email Address, Street Address, City, State, Zip, Telephone Number and Fax Number.
No or Yes: Was an Accelerated Death Benefit, Accidental Dismemberment or Enhancement benefit such as Coma, Traumatic Brain Injury, Surgical Reattachment, Third Degree Burn, Children's Double Indemnity Benefit claim submitted prior to death? No or Yes: Was waiver of premium claim submitted prior to death?
Group Coverage, Control, Suffix, Account and Plan

Under Group Coverage, for each coverage (Term Life (TRM1), Supplemental (TRM3), Dependent (TRM2), AD&PL (AD&D) (ADD1), Group Accident (GAC1), Paid-up (PUP1), Group Universal Life (GUL1)), enter Control, Suffix, Account, Plan, Effective date of employee's insurance (MM/DD/YYYY) and Amount of insurance in force as of the date last worked.
Earnings, premiums, converted group insurance and Aetna long term care policy
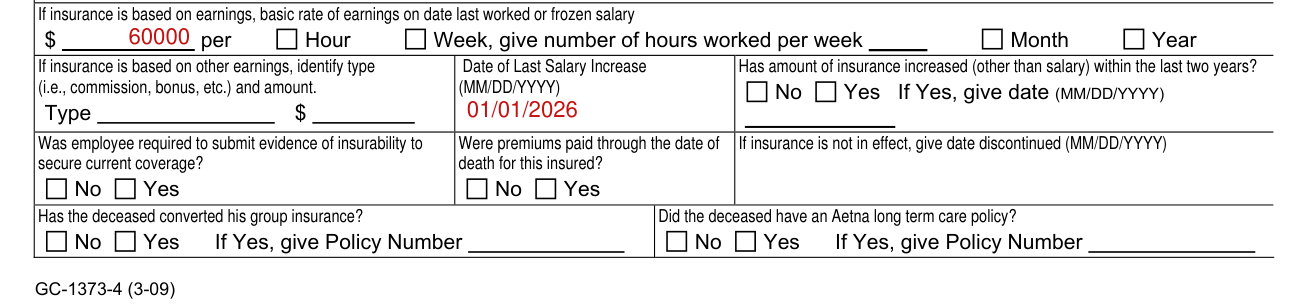
If insurance is based on earnings, enter the basic rate of earnings on date last worked or frozen salary in $ per Hour, Week, Month or Year, and give number of hours worked per week. If insurance is based on other earnings, identify type (i.e., commission, bonus, etc.) and amount.
Enter the Date of Last Salary Increase (MM/DD/YYYY). No or Yes: Has amount of insurance increased (other than salary) within the last two years? If Yes, give date (MM/DD/YYYY). No or Yes: Was employee required to submit evidence of insurability to secure current coverage?
No or Yes: Were premiums paid through the date of death for this insured? If insurance is not in effect, give date discontinued (MM/DD/YYYY).
No or Yes: Has the deceased converted his group insurance? If Yes, give Policy Number.
No or Yes: Did the deceased have an Aetna long term care policy? If Yes, give Policy Number.
The Beneficiary(ies) Name and Social Security Number
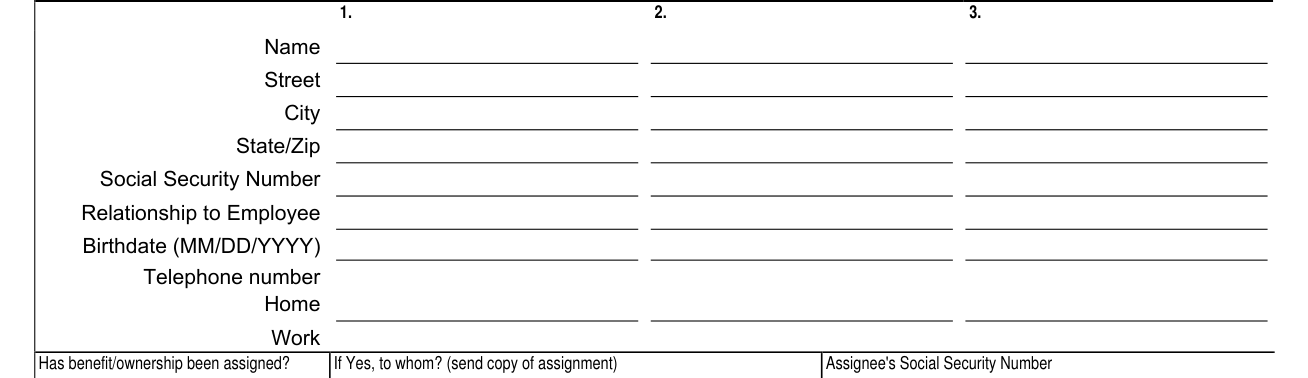
In D. Information About The Beneficiary(ies), for each of the Beneficiary(ies), enter the Name, Street, City, State/Zip, Social Security Number, Relationship to Employee and Birthdate (MM/DD/YYYY).
Enter the Telephone number, Home and Work.
No or Yes: Has benefit/ownership been assigned? If Yes, to whom? (send copy of assignment) and enter the Assignee's Social Security Number.
SIGN: Name, Signature and Date

In G. Employer's Authorized Representative, SIGN: enter the Name, the Signature, the Date (MM/DD/YYYY) and at (city, state, zip).
More rules for Aetna Group Life Proof of Death Claim Form (GC-1373-4)
Complete the deceased name on the top of Page 2 before the Life insurance claim is faxed to the office at 1-859-455-8650.
It is not necessary to follow-up with the original documents.
If you have any additional questions on the submission of this claim, contact the office at 1-888-772-9682. This information, where marked with *, should be supplied by the beneficiary or the beneficiary's representative.
Enter the deceased Name (last, first, middle initial) and Social Security Number under Page 2 Deceased Information and under Page 3 Deceased Information.
In E. Benefit Distribution Instructions, return the benefit payment directly to: Beneficiary, Employer (Checkbook to Beneficiary Only) or Other.
Common questions about Aetna Group Life Proof of Death Claim Form (GC-1373-4)
Where do I file it?
Mail this completed form to: SRC, an Aetna Company, Attn: Claim Department, PO Box 14079, Lexington, KY 40512-4079. Fax to: 1-859-455-8650. Phone: 1-888-772- 9682.
Is there a penalty?
Any person who knowingly and with intent to injure, defraud or deceive any insurance company or other person files an application for insurance or statement of claim containing any materially false information or conceals, for the purpose of misleading, information concerning any fact material thereto commits a fraudulent insurance act, which is a crime and subjects such person to criminal and civil penalties.
Sources
[1] Aetna Group Life Proof of Death Claim Form (GC-1373-4) (3-09) (the served file; no issuer file found) (the Official source link on this page).