


Form DLD-7 at a glance
What it is: DLD-7 is the CONFIDENTIAL PHYSICIANS REPORT.
Who signs: The Signature of Authorized Physician, APRN or PA. The Patient's Signature and Date.
A filled-in Form DLD-7 example: a physician reports on a patient with epilepsy
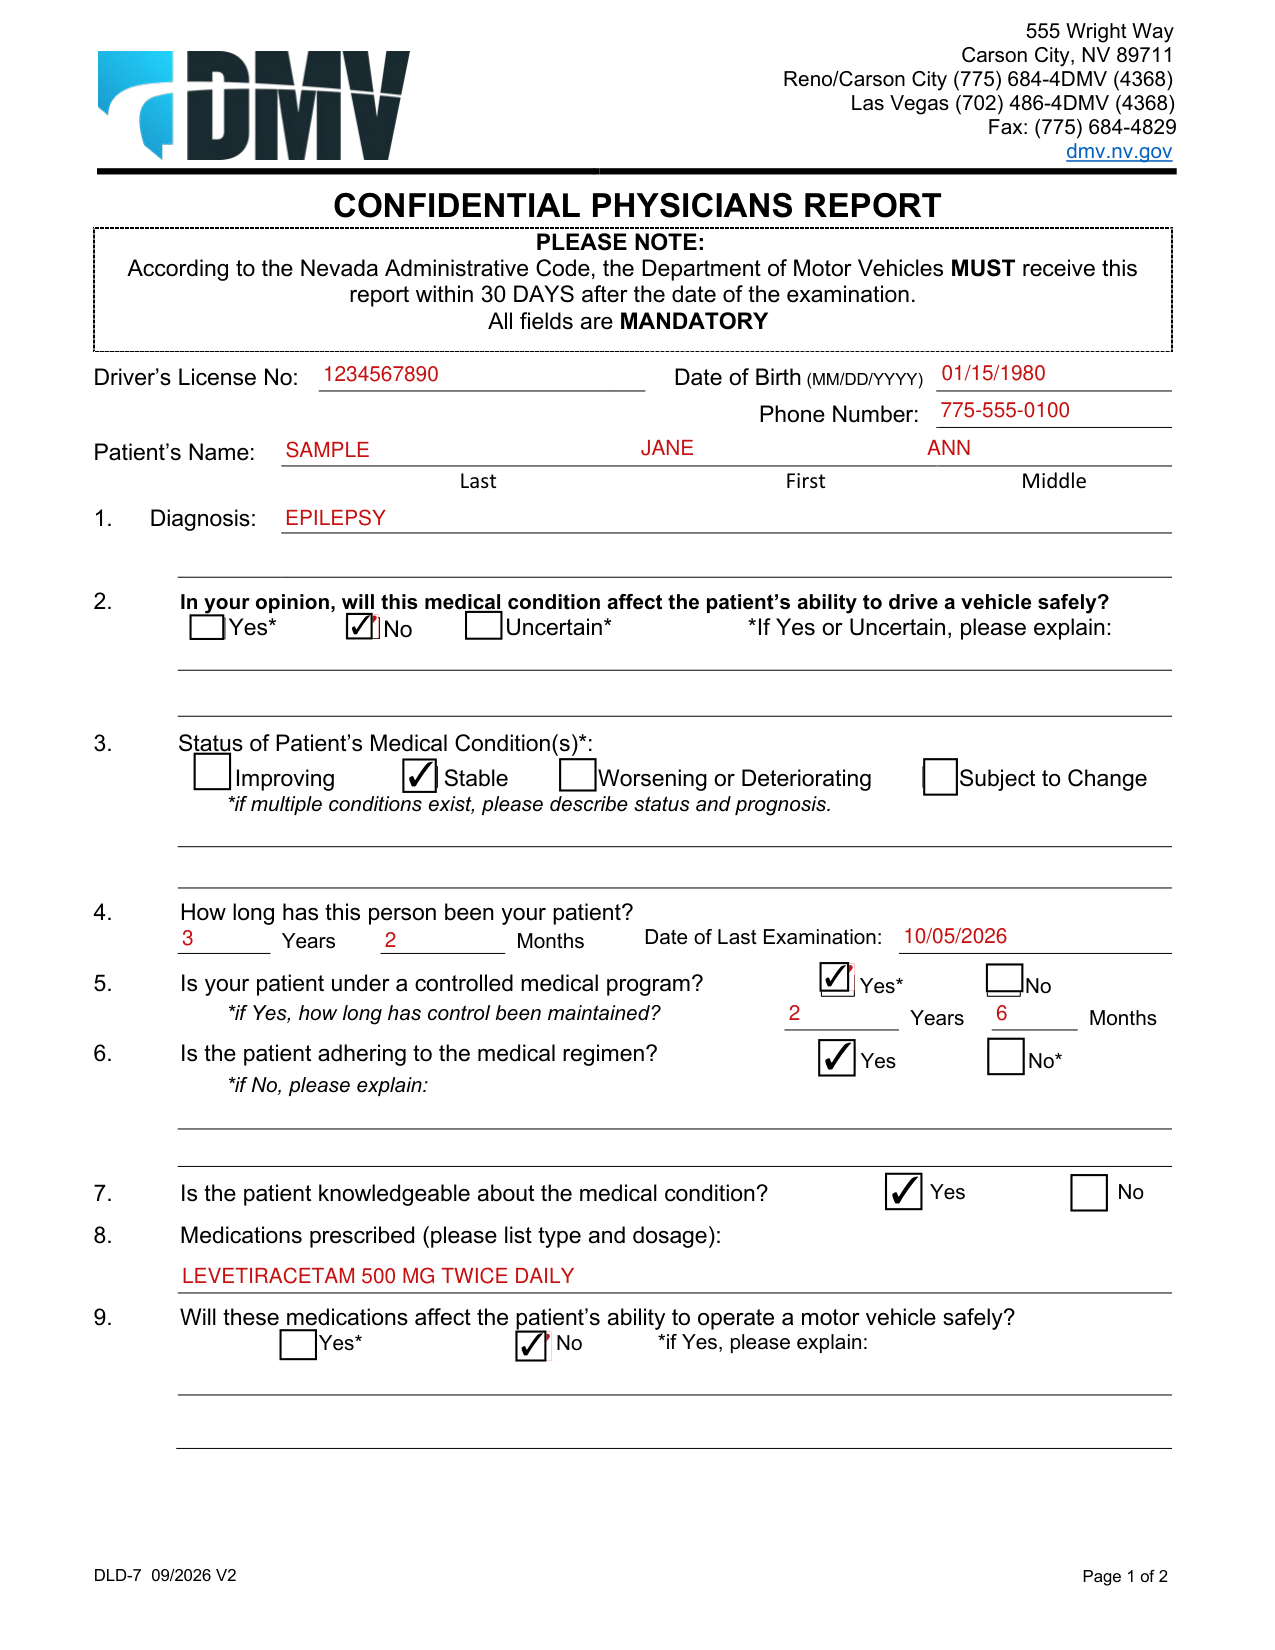
How to fill out Form DLD-7, box by box
Driver's License No, Date of Birth and Patient's Name
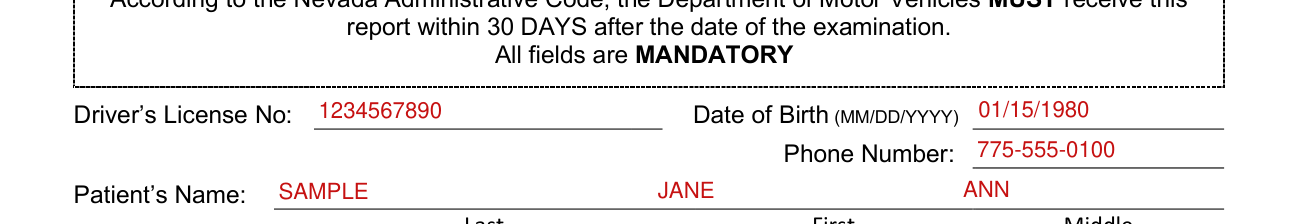
Enter the Driver's License No, Date of Birth (MM/DD/YYYY), Phone Number and the Patient's Name: Last, First, Middle.
1. Diagnosis and 2. ability to drive a vehicle safely

Enter the 1. Diagnosis.
In 2, mark Yes, Uncertain or No: In your opinion, will this medical condition affect the patient's ability to drive a vehicle safely? If Yes or Uncertain, please explain.
3. Status of Patient's Medical Condition(s)

In 3, mark the Status of Patient's Medical Condition(s): Improving, Worsening or Deteriorating, Stable or Subject to Change. If multiple conditions exist, please describe status and prognosis.
4. How long has this person been your patient and 5. controlled medical program

In 4, enter how long this person has been your patient in Years and Months, and the Date of Last Examination.
In 5, mark No or Yes: Is your patient under a controlled medical program? If Yes, enter how long control has been maintained in Years and Months.
6. Adhering to the medical regimen and 7. knowledgeable about the medical condition

In 6, mark Yes or No: Is the patient adhering to the medical regimen? If No, please explain.
In 7, mark Yes or No: Is the patient knowledgeable about the medical condition?
8. Medications prescribed and 9. ability to operate a motor vehicle safely

In 8, list the medications prescribed: please list type and dosage.
In 9, mark Yes or No: Will these medications affect the patient's ability to operate a motor vehicle safely? If Yes, please explain.
10. Loss or lapse of consciousness, seizure activity, fainting or dizzy spells

In 10, mark Yes or No: Does the nature of the condition indicate loss/lapse of consciousness, seizure activity, fainting or dizzy spells? If Yes, please indicate the date (mm/dd/yyyy) of the last occurrence.
In 10a, mark Yes or No: Was the seizure or loss of consciousness and isolated incident? In 10b, mark Yes or No: Are additional seizures likely to occur?
11. Restrictions and 12. Physician's Comments

In 11, recommend any restrictions you feel are necessary for this patient to safely drive a vehicle.
In 12, write the Physician's Comments.
Date of Examination, Signature of Authorized Physician, APRN or PA
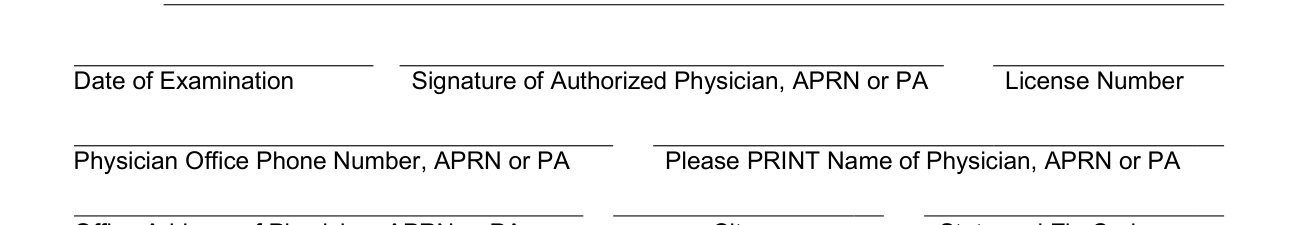
Sign on the Signature of Authorized Physician, APRN or PA line, and fill in the Date of Examination, the License Number, the Physician Office Phone Number, the Please PRINT Name of Physician, APRN or PA, the Office Address of Physician, APRN or PA, City and State and Zip Code.
OPTIONAL: medical condition on your driver's license or identification card
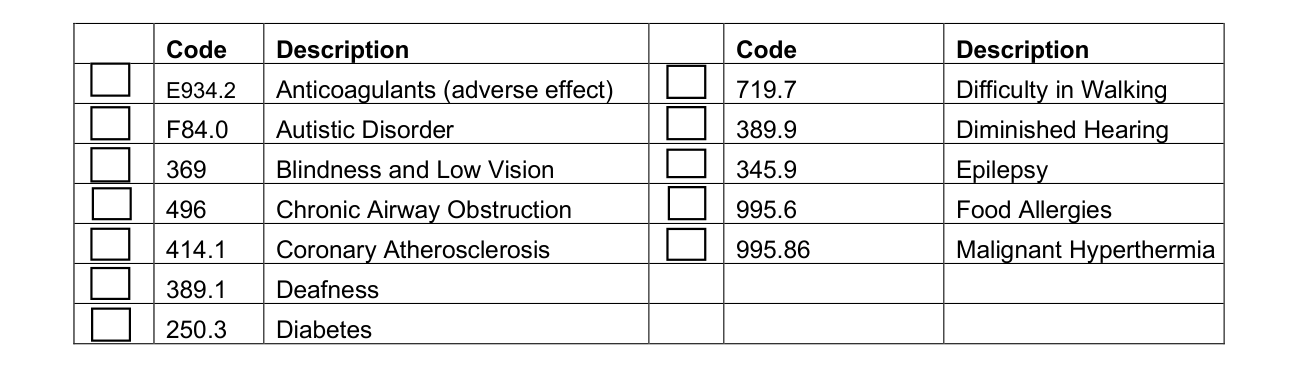
OPTIONAL: You can have an indicator of a medical condition imprinted on your driver's license or identification card to alert police and medical personnel.
Your physician must state on this form that you suffer from any of the medical conditions listed under Code Description.
Check only one to be placed on the back of the license.
The Code and Description list is E934.2 Anticoagulants (adverse effect), 719.7 Difficulty in Walking, F84.0 Autistic Disorder, 389.9 Diminished Hearing, 369 Blindness and Low Vision, 345.9 Epilepsy, 496 Chronic Airway Obstruction, 995.6 Food Allergies, 414.1 Coronary Atherosclerosis, 995.86 Malignant Hyperthermia, 389.1 Deafness and 250.3 Diabetes.
You must present this form in person to the DMV if you wish to have one of these medical conditions imprinted on your driver's license or identification.
There is no charge to have this added to your card, however, there will be a $3.25 fee to produce a new card (checked November 8, 2026).
More rules for Form DLD-7
The patient authorizes any physician, surgeon, advanced practical registered nurse, physician's assistant, or other person, and/or any clinic, or hospital to release any and all acquired medical information that specifically addresses the information on this form. The patient signs with the Date.
Common questions about Form DLD-7
Is there a deadline?
According to the Nevada Administrative Code, the Department of Motor Vehicles MUST receive this report within 30 DAYS after the date of the examination. All fields are MANDATORY.
Sources
[1] Form DLD-7 (09/2026), Confidential Physicians Report, Nevada Department of Motor Vehicles (the Official source link on this page).