


Form MED 3 at a glance
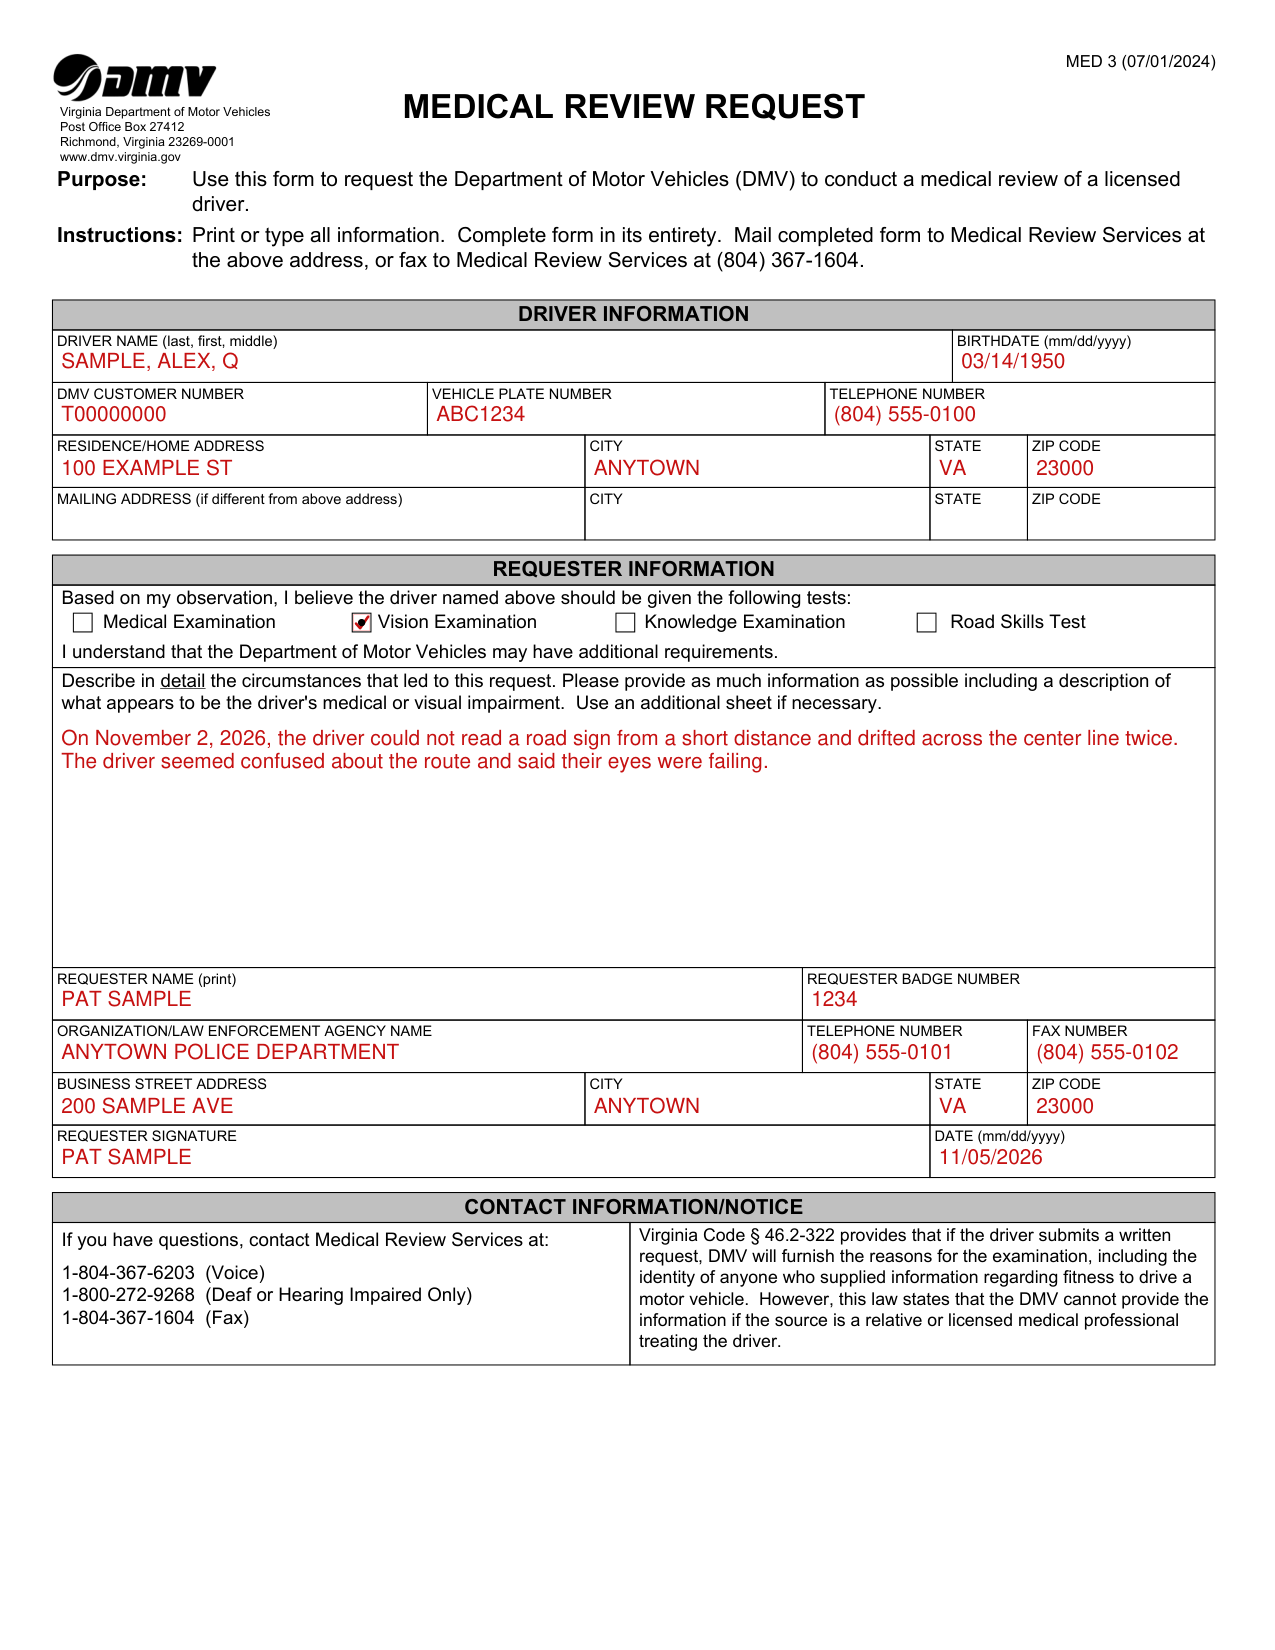
What it is: MED 3, the Medical Review Request. Use this form to request the Department of Motor Vehicles (DMV) to conduct a medical review of a licensed driver. Fax to Medical Review Services is (804) 367-1604.
Where and when to file: Print or type all information and complete the form in its entirety. Mail the completed form to Medical Review Services at Post Office Box 27412, Richmond, Virginia 23269-0001, or fax it to Medical Review Services at (804) 367-1604.
A filled-in Form MED 3 example: an officer asks for a vision examination
How to fill out Form MED 3, box by box
Driver name, birthdate, customer number, plate number and telephone number
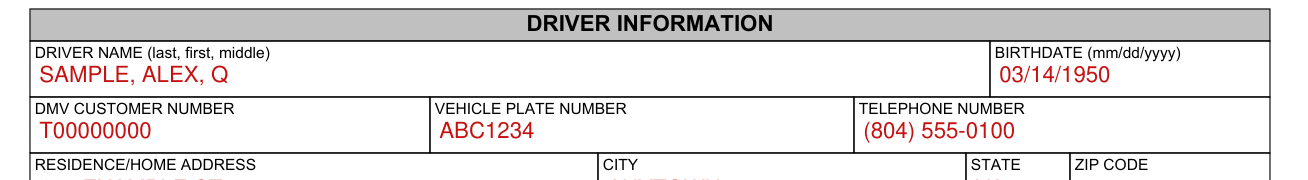
Under DRIVER INFORMATION, enter the DRIVER NAME (last, first, middle) and the BIRTHDATE (mm/dd/yyyy).
Enter the DMV CUSTOMER NUMBER, the VEHICLE PLATE NUMBER and the TELEPHONE NUMBER.
Residence/home address and mailing address
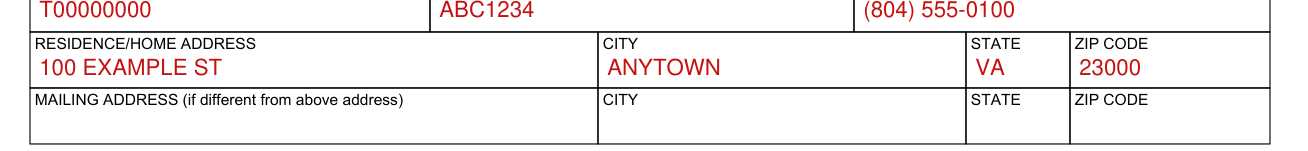
Enter the RESIDENCE/HOME ADDRESS and the MAILING ADDRESS if different from the RESIDENCE/HOME ADDRESS, each with CITY, STATE and ZIP CODE.
Tests and the circumstances that led to the request
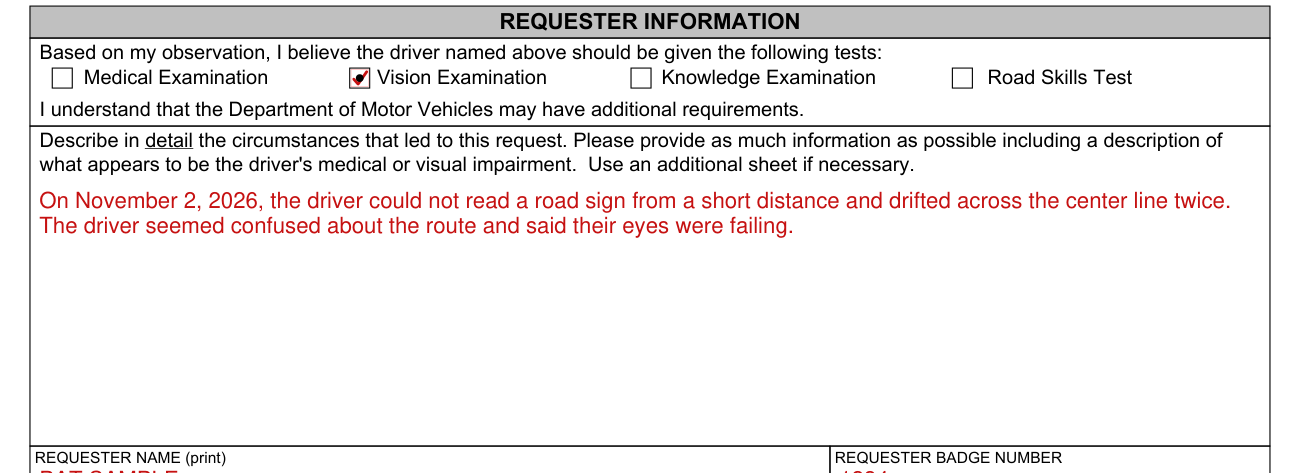
Under REQUESTER INFORMATION, mark the test the driver named in DRIVER INFORMATION should be given, based on your observation: Medical Examination, Vision Examination, Knowledge Examination or Road Skills Test.
The Department of Motor Vehicles may have additional requirements.
Describe in detail the circumstances that led to this request. Provide as much information as possible including a description of what appears to be the driver's medical or visual impairment. Use an additional sheet if necessary.
Requester name, badge number, agency and business street address
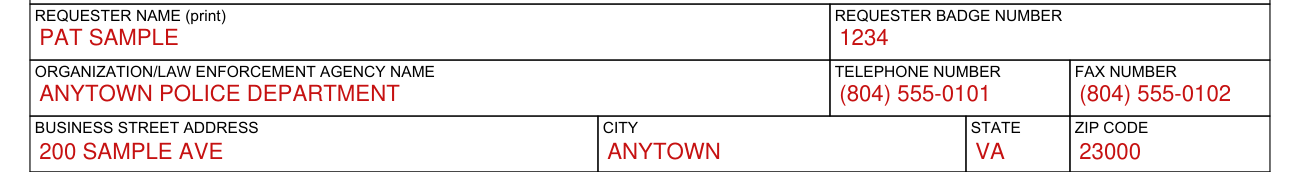
Print the REQUESTER NAME and enter the REQUESTER BADGE NUMBER.
Enter the ORGANIZATION/LAW ENFORCEMENT AGENCY NAME, the TELEPHONE NUMBER and the FAX NUMBER.
Enter the BUSINESS STREET ADDRESS, then the CITY, STATE and ZIP CODE.
Date and requester signature

Enter the DATE (mm/dd/yyyy) and sign on the REQUESTER SIGNATURE line.
More rules for Form MED 3
If you have questions, contact Medical Review Services at 1-804-367-6203 (Voice), 1-800-272-9268 (Deaf or Hearing Impaired Only) or 1-804-367-1604 (Fax).
Virginia Code § 46.2-322 provides that if the driver submits a written request, DMV will furnish the reasons for the examination, including the identity of anyone who supplied information regarding fitness to drive a motor vehicle. However, this law states that the DMV cannot provide the information if the source is a relative or licensed medical professional treating the driver.
Common questions about Form MED 3
Where do I file it?
Virginia Department of Motor Vehicles, Post Office Box 27412, Richmond, Virginia 23269-0001, www.dmv.virginia.gov.
Sources
[1] Form MED 3 (07/01/2024), Medical Review Request, Virginia Department of Motor Vehicles (the Official source link on this page).