

Form P-40 at a glance
What it is: Initial Medical Request P-40 is a form of the State of Connecticut Department of Motor Vehicles Driver Services Division.
Where and when to file: Mail to: DMV, Driver Services Division, 60 State Street, Wethersfield, CT 06161-1013.
The patient named has been referred to the DMV Driver Services Division concerning their ability to safely operate a motor vehicle. This medical report must reflect the results of the medical professional's (licensed physician, PA or APRN) personal examination of the patient performed within 90 days of this report being filed. It must be signed by the patient authorizing the medical professional to release this report and any attachments to DMV.
A filled-in Form P-40 example: a physician completes a medical request

How to fill out Form P-40, box by box
Driver's license number

Enter the Driver's License Number and mark CDL/PS Yes or No.
Patient's name, date of birth, telephone number and address
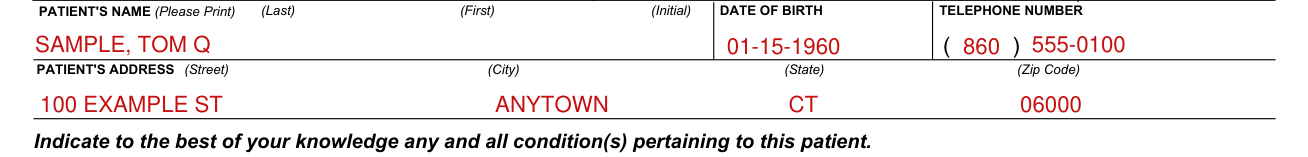
Print the Patient's Name (Last) (First) (Initial), Date of Birth and Telephone Number, then the Patient's Address (Street) (City) (State) (Zip Code).
I hereby authorize the medical professional completing and signing this medical report to release such report to DMV and/or Bureau of Rehabilitative Services (BRS) along with any other medical information necessary to determine my fitness to safely operate a motor vehicle.
Conditions pertaining to this patient

Indicate to the best of your knowledge any and all condition(s) pertaining to this patient.
Alcohol/Substance Abuse, Neurological/Neuromuscular, Alzheimer's/Dementia, Ophthalmologic, Cardiovascular/Hypertension, Orthopedic, Cerebral Palsy, Peripheral Vascular Disease, Cystic Fibrosis, Psychiatric/Emotional Disorder, Endocrine/Glandular, Pulmonary/Sleep Apnea, Liver/Renal Failure, Other and Narcolepsy.
How long have you been treating this person and for what condition(s)

How long have you been treating this person and for what condition(s)? Condition, treatment began and date of last examination.
If treated by another physician

If treated by another physician, please indicate name, address and specialty of physician: Physician's Name (Please Print or Type), Office Address (Include Zip Code) and Physician's Specialty.
This individual has and road test

This individual has NO medical matters which would affect his/her ability to safely operate a motor vehicle.
I do not have sufficient information to determine this person's ability to operate a motor vehicle.
Considering this patient's condition(s), mark Yes or No: do you believe this person should be road tested and/or evaluated for special equipment requirements?
Medical professional certification

Medical Professional Certification: "I certify that I have personally examined the above named person within the 90 days preceding completion of this report. I swear or affirm under penalty of false statement in accordance with Connecticut General Statutes §14-110 and §53a-157b, and subject to penalties for perjury for a deliberate false statement, that the above information and any attachment hereto is true and correct."
Print the Medical Professional's Name (Please Print or Type), Office Address (Include Zip Code), Telephone Number, Medical Professional's License Number and Medical Professional's Specialty.
Medical Professional's Signature and Date Report Completed.
Common questions about Form P-40
Where do I file it?
Mail to: DMV, Driver Services Division, 60 State Street, Wethersfield, CT 06161-1013.
Sources
[1] Form P-40 (REV. 8-2017), Initial Medical Request, State of Connecticut Department of Motor Vehicles (the Official source link on this page).