


Form W-1ER at a glance
What it is: W-1ER, Renewal Of Eligibility, State Of Connecticut Department Of Social Services.
Who signs: This form is only to renew eligibility for the benefits you get now or to add new members of your household. You must fill out the form and sign and date page 6 for it to be complete.
This renewal form is only for current DSS clients who get one or more of Supplemental Nutritional Assistance Program (SNAP), Cash Assistance (including boarding home payments), Medical Insurance (HUSKY) only if you are: (1) 65 years old or older; (2) on Medicare; (3) determined disabled by DSS and are working; or (4) receiving Long-Term Care. If you get HUSKY and you are not in one of these four groups then you cannot renew with this form. You must renew online at www.CONNECT.ct.gov or by phone with Access Health CT at (855) 805-4325. You can also call (855) 805-4325 and ask for a paper form. Renewing online is fastest.
What to bring and attach to Form W-1ER
You must provide proof of your income. Examples of proof are your last 4 weeks of paystubs or, if self-employed, your most recent business records.
A filled-in Form W-1ER example: a mother renews with her son
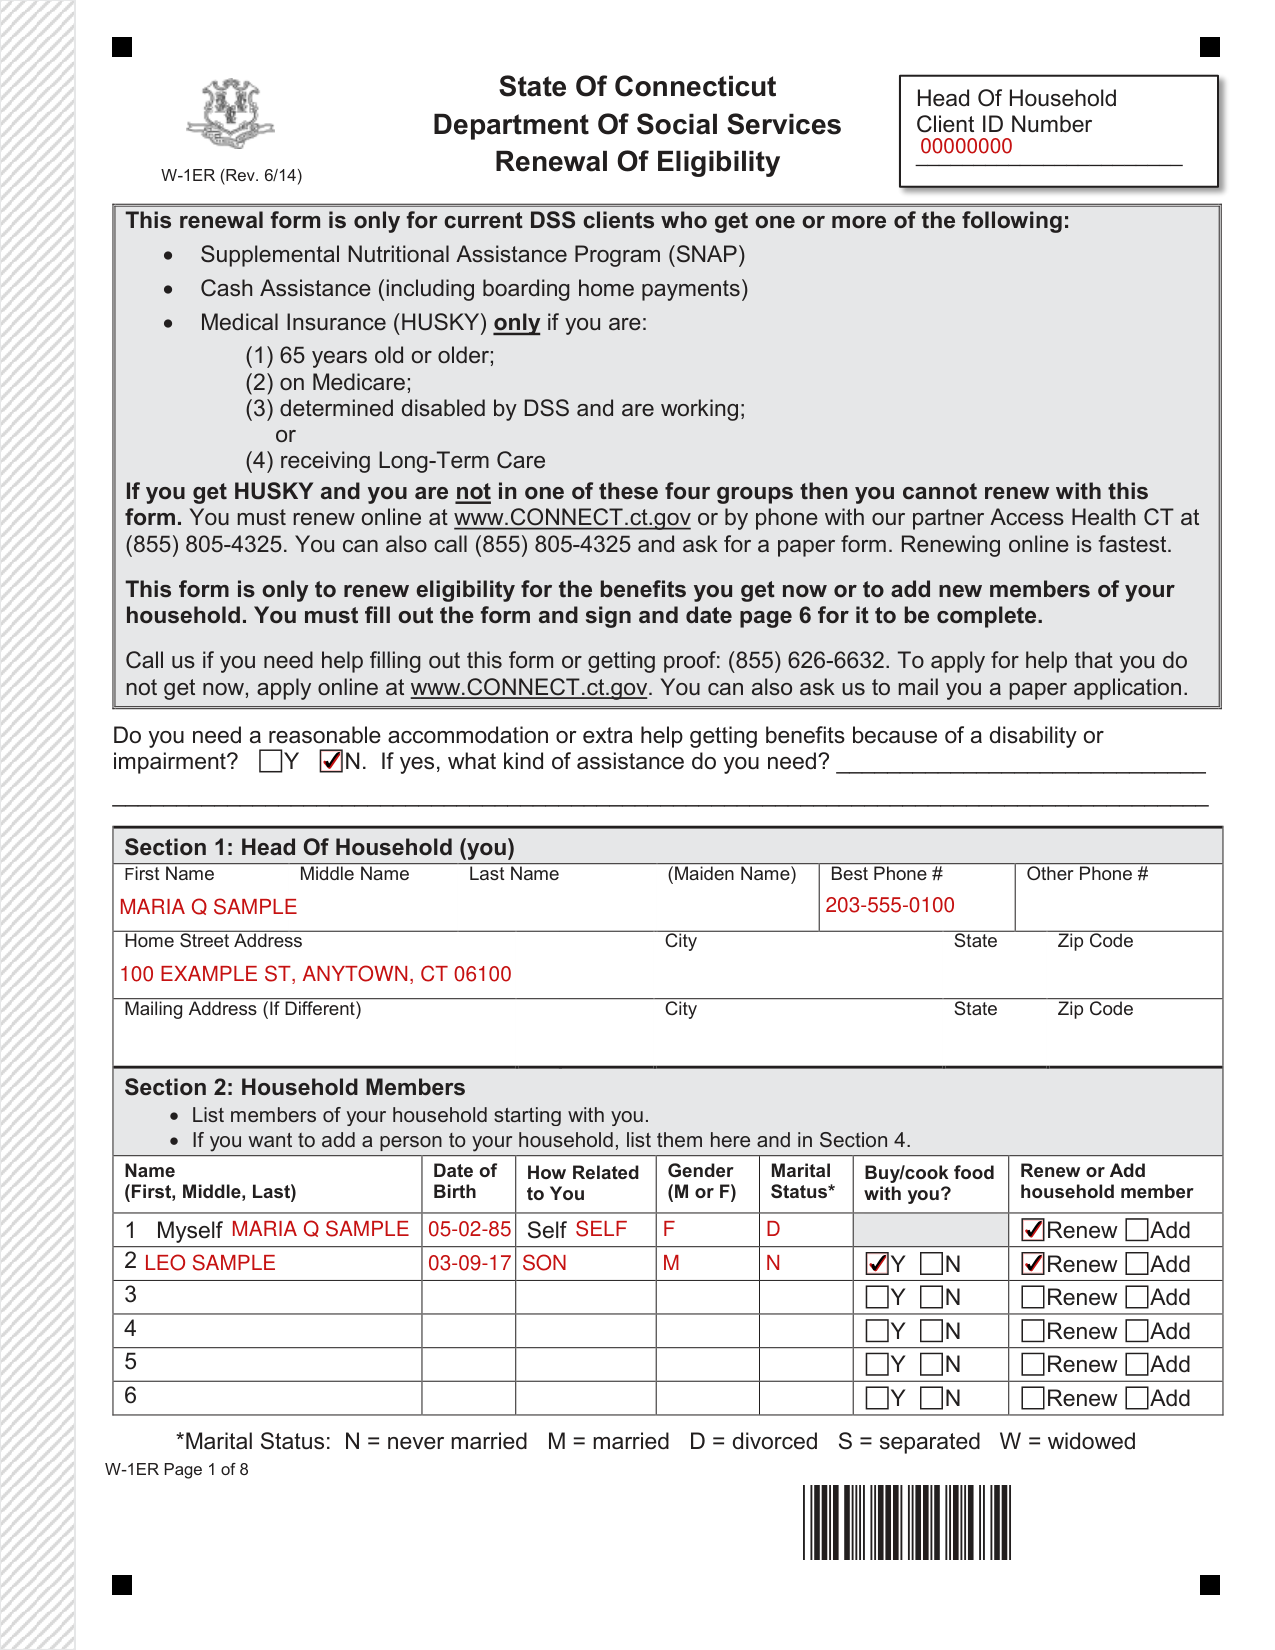
How to fill out Form W-1ER, box by box
Head Of Household Client ID Number

Enter the Head Of Household Client ID Number.
Reasonable accommodation or extra help

Mark Y or N for: Do you need a reasonable accommodation or extra help getting benefits because of a disability or impairment? If yes, write what kind of assistance you need.
Section 1: Head Of Household (you)
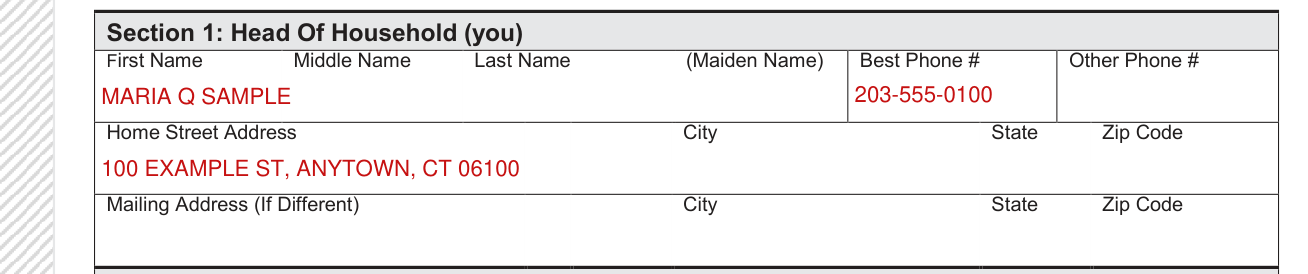
In Section 1: Head Of Household (you), enter First Name, Middle Name, Last Name (Maiden Name), Best Phone # and Other Phone #.
Enter the Home Street Address, City, State and Zip Code. Enter the Mailing Address (If Different), City, State and Zip Code.
Section 2: Household Members
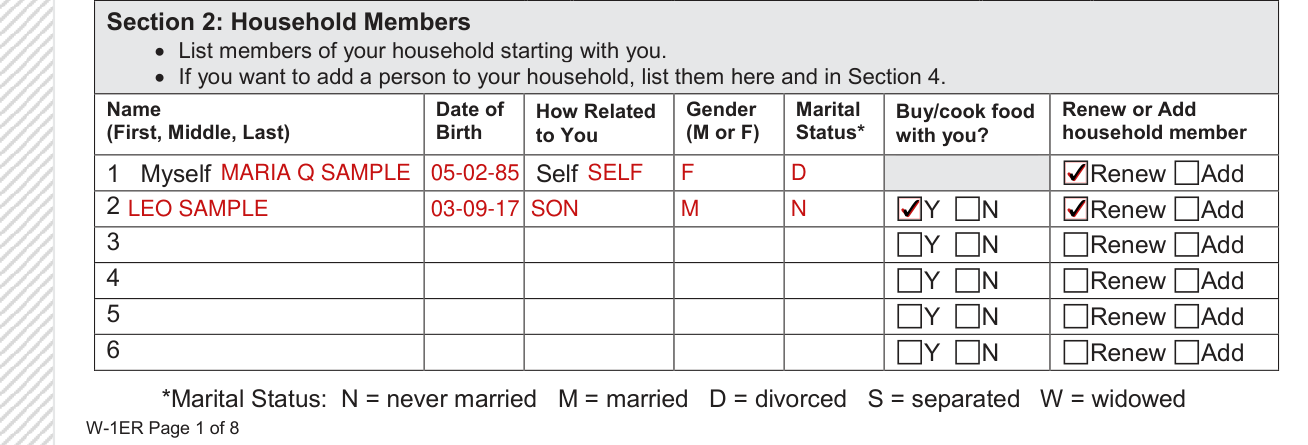
In Section 2: Household Members, list members of your household starting with you. If you want to add a person to your household, list them here and in Section 4.
For each member, enter Name (First, Middle, Last), Date of Birth, How Related to You, Gender (M or F) and Marital Status*, and mark Y or N for Buy/cook food with you? and Renew or Add for household member.
*Marital Status: N = never married, M = married, D = divorced, S = separated, W = widowed.
Section 7: Earned Income (Attach Proof)
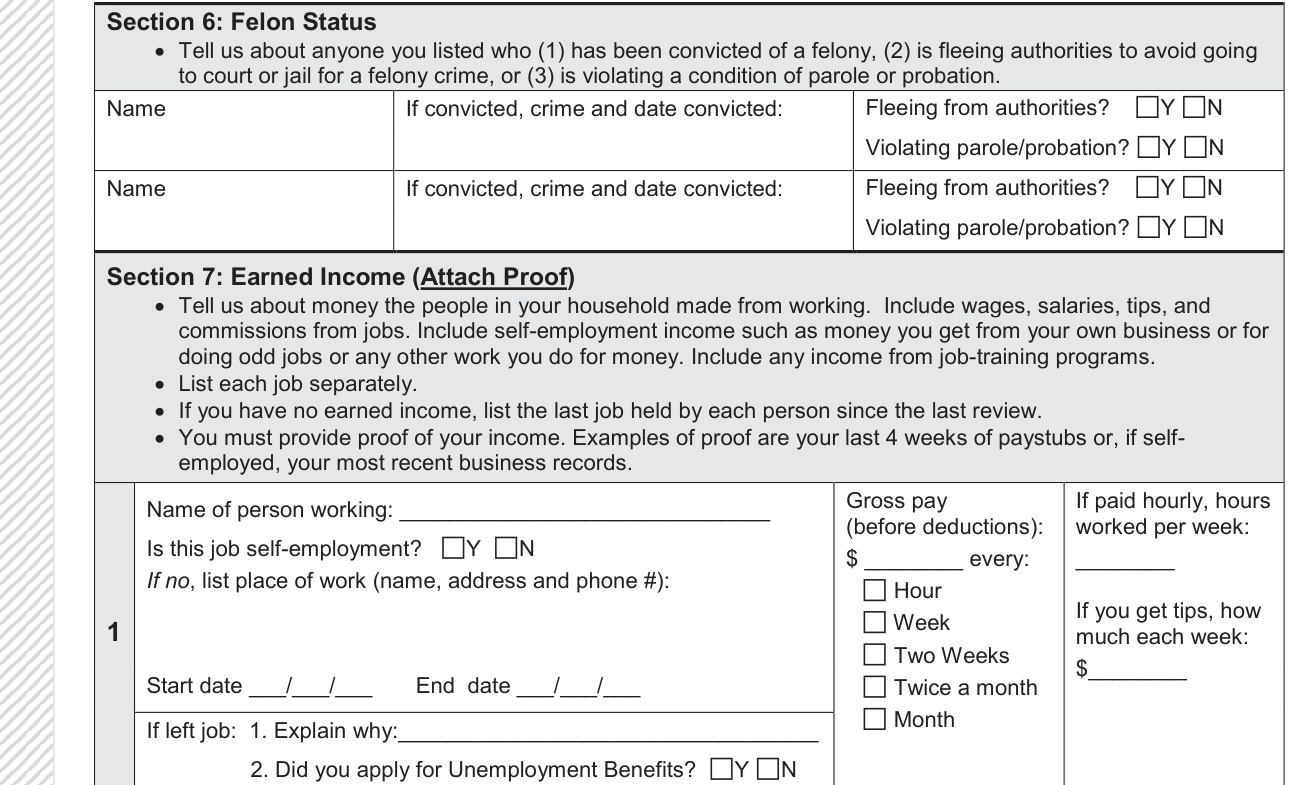
Section 7: Earned Income (Attach Proof): money the people in your household made from working. Include wages, salaries, tips, and commissions from jobs. Include self-employment income such as money you get from your own business or for doing odd jobs or any other work you do for money. Include any income from job-training programs.
List each job separately. If you have no earned income, list the last job held by each person since the last review.
For each job, enter the Name of person working and the Gross pay (before deductions) with every Hour, Week, Two Weeks, Twice a month or Month. If paid hourly, enter hours worked per week. Mark Y or N for Is this job self-employment? If no, list place of work (name, address and phone #). If you get tips, enter how much each week.
If left job, explain why and mark Y or N for Did you apply for Unemployment Benefits?
Section 8: Other Income (Attach Proof)
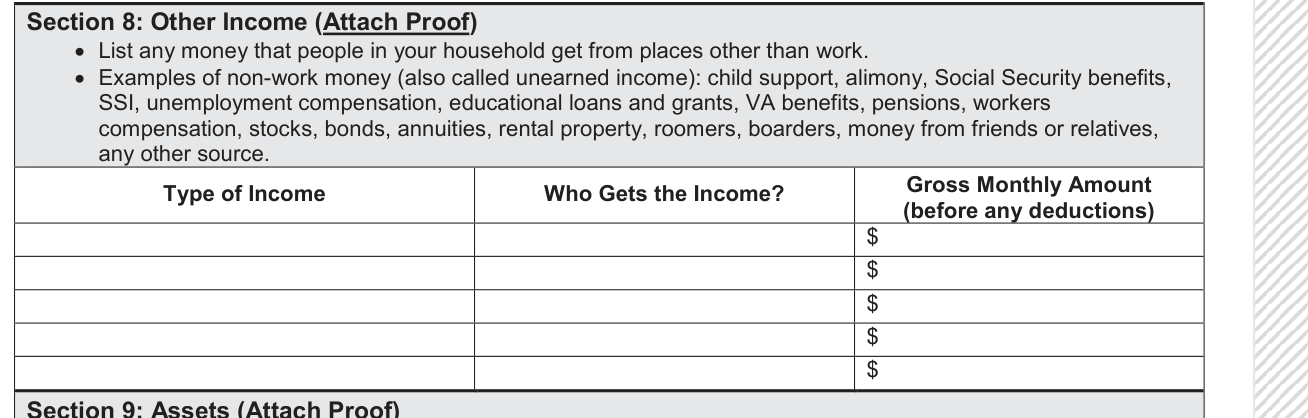
Section 8: Other Income (Attach Proof): list any money that people in your household get from places other than work. Examples of non-work money (also called unearned income): child support, alimony, Social Security benefits, SSI, unemployment compensation, educational loans and grants, VA benefits, pensions, workers compensation, stocks, bonds, annuities, rental property, roomers, boarders, money from friends or relatives, any other source.
Enter the Type of Income, Who Gets the Income? and Gross Monthly Amount (before any deductions).
Section 19: Monthly Expenses
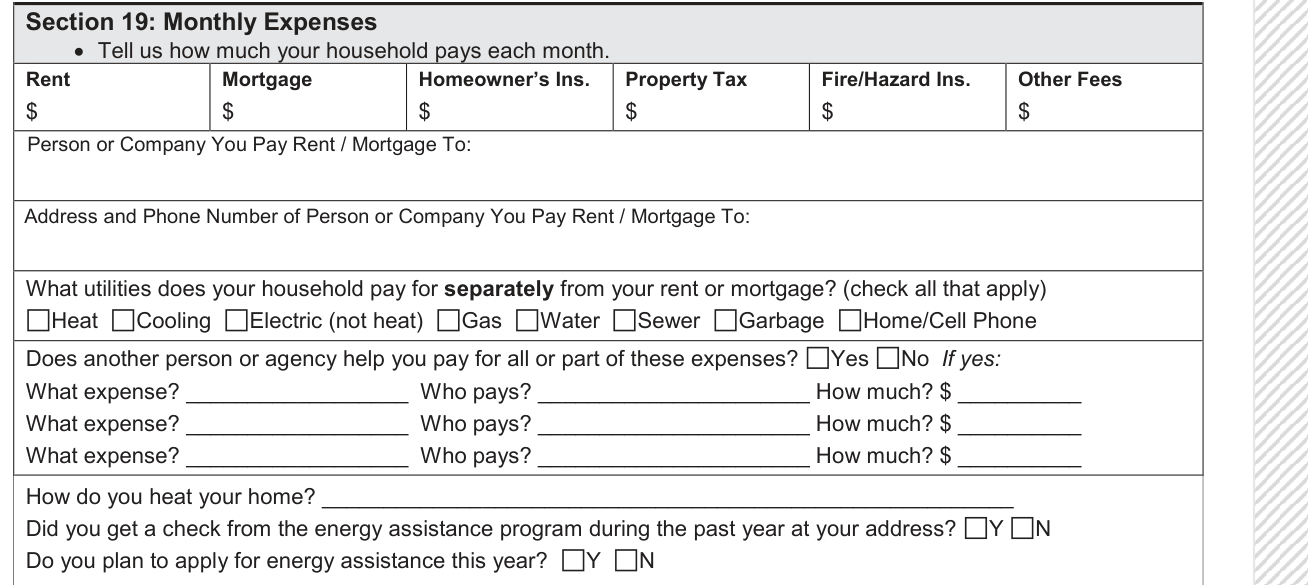
Enter how much your household pays each month.
Enter Rent, Mortgage, Homeowner's Ins., Property Tax, Fire/Hazard Ins. and Other Fees, the Person or Company You Pay Rent / Mortgage To, and the Address and Phone Number of that Person or Company.
What utilities does your household pay for separately from your rent or mortgage? Check all that apply: Heat, Cooling, Electric (not heat), Gas, Water, Sewer, Garbage, Home/Cell Phone.
Mark Yes or No: Does another person or agency help you pay for all or part of these expenses? If yes, enter What expense?, Who pays? and How much?
Enter How do you heat your home? Mark Y or N for Did you get a check from the energy assistance program during the past year at your address? and for Do you plan to apply for energy assistance this year?
CERTIFICATION AND SIGNATURES
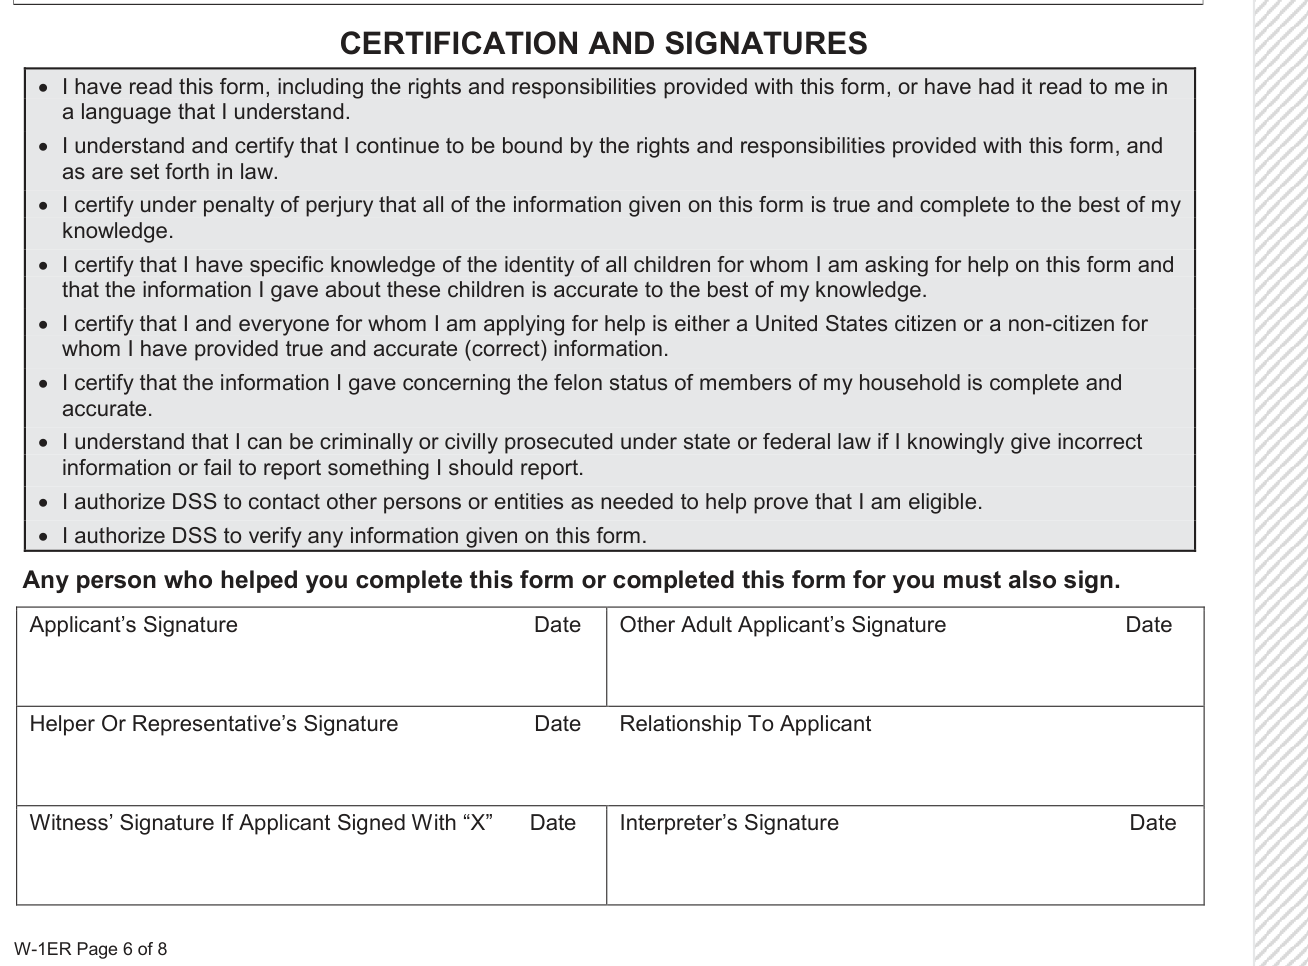
You certify under penalty of perjury that all of the information given on this form is true and complete to the best of your knowledge.
You can be criminally or civilly prosecuted under state or federal law if you knowingly give incorrect information or fail to report something you should report. You authorize DSS to verify any information given on this form.
Any person who helped you complete this form or completed this form for you must also sign. Sign and date at Applicant's Signature Date, Other Adult Applicant's Signature Date, Helper Or Representative's Signature Date, Relationship To Applicant, Witness' Signature If Applicant Signed With “X” Date and Interpreter's Signature Date.
If your situation is different
You are married and get long-term care
Section 12: Community Spouse (Attach proof of income and expenses): complete this section if you are married and (1) you get long-term care at home but your spouse does not, or (2) if you get long-term care in a facility and your spouse lives in the community.
Someone in your household is blind, disabled, or over age 65
Section 13: Special Eating Arrangement: complete this section only if someone in your household is blind, disabled, or over age 65, and renewing State Supplement cash or HUSKY C medical benefits.
Anyone in your household is 60 years old or older, or has an SSI/SSD disability
Section 18: Medical Expenses (Attach proof): complete this section if anyone in your household is 60 years old or older, or is a person with an SSI/SSD disability, and has medical expenses such as medical insurance (premiums, deductibles and co-pays), transportation cost for medical appointments or dental bills.
Sources
[1] Form W-1ER (Rev. 6/14), Renewal Of Eligibility, State of Connecticut Department of Social Services (the Official source link on this page).