
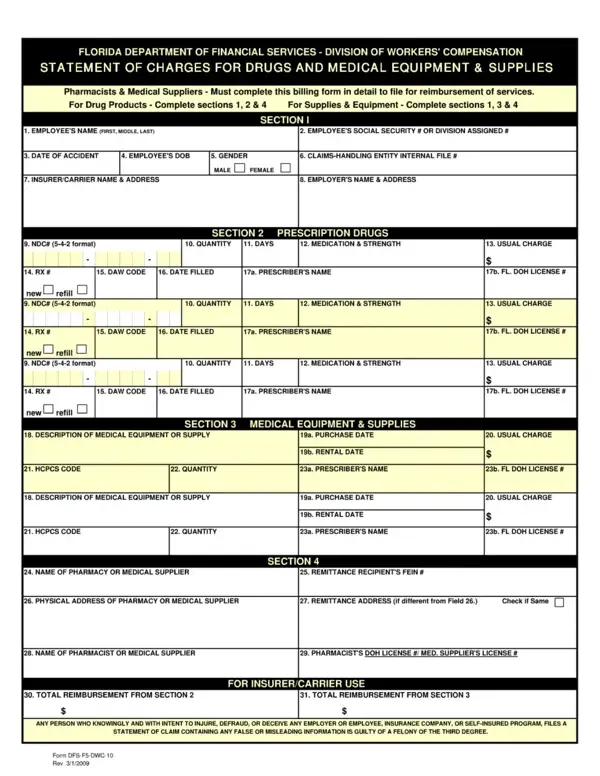

Form DFS-F5-DWC-10 at a glance
What it is: Form DFS-F5-DWC-10 Rev. 1/1/2015 is the Statement of Charges for Drugs and Medical Equipment & Supplies of the Florida Department of Financial Services, Division of Workers' Compensation.
Pharmacists & Medical Suppliers must complete this billing form in detail to file for reimbursement of services.
For Supplies & Equipment, complete Sections 1, 3 and 4. For Drug Products, complete Sections 1, 2 and 4.
A filled-in Form DFS-F5-DWC-10 example: a pharmacist bills one new prescription
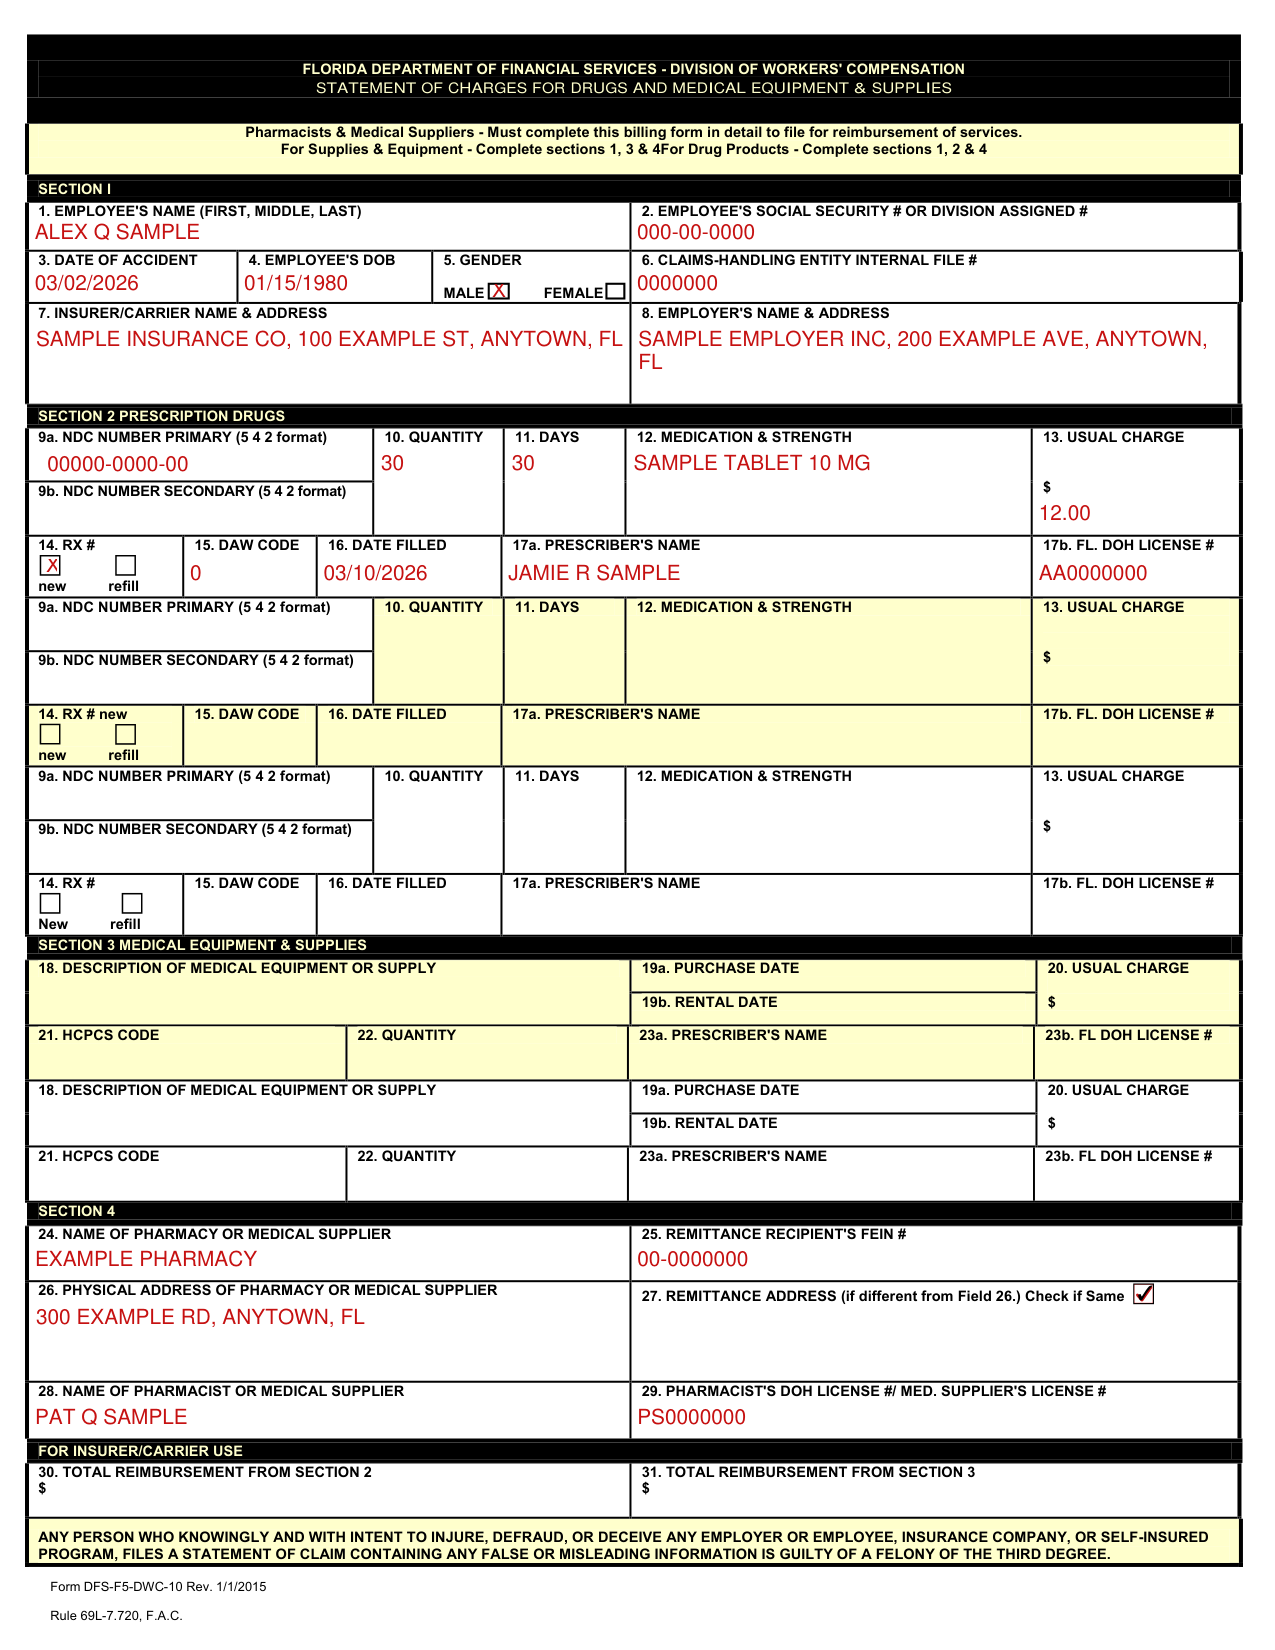
How to fill out Form DFS-F5-DWC-10, box by box
Section I
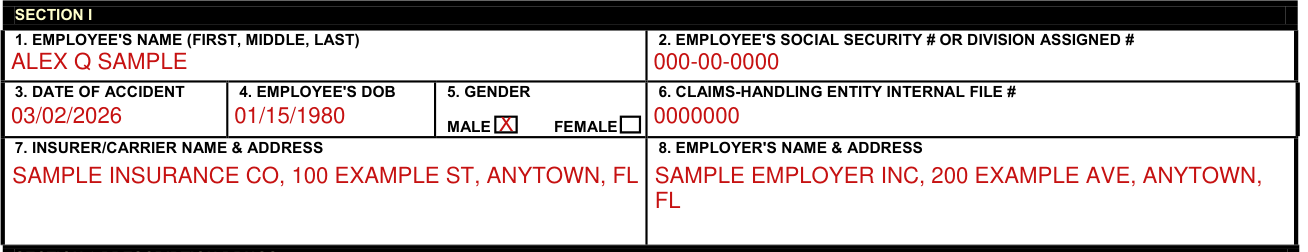
Enter the employee's name (first, middle, last) in Box 1 and the employee's social security number or Division assigned number in Box 2.
Enter the date of accident in Box 3 and the employee's DOB in Box 4. Box 5 is Gender: Male or Female.
Enter the claims-handling entity internal file number in Box 6, the insurer/carrier name and address in Box 7 and the employer's name and address in Box 8.
Section 2 Prescription drugs
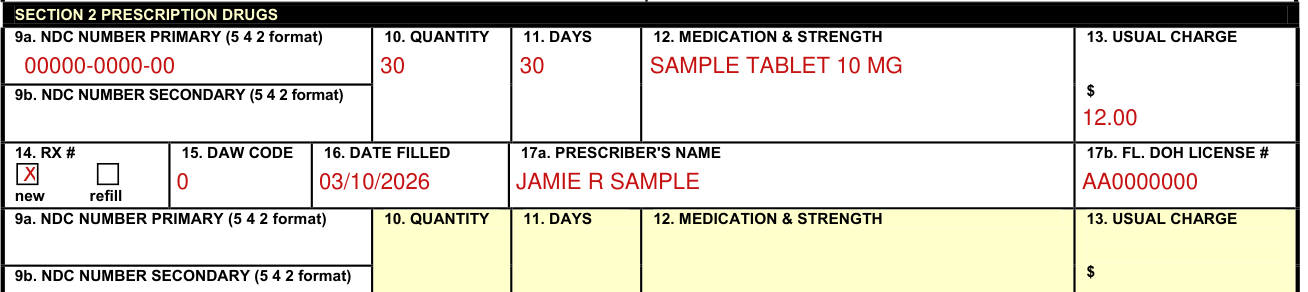
In Section 2 Prescription Drugs, enter the primary NDC number in Box 9a and the secondary NDC number in Box 9b, each in 5 4 2 format. Enter the quantity in Box 10, the days in Box 11, the medication & strength in Box 12 and the usual charge in Box 13.
Enter the RX number in Box 14 and mark new or refill.
Enter the DAW code in Box 15, the date filled in Box 16, the prescriber's name in Box 17a and the FL. DOH license number in Box 17b.
Section 3 Medical equipment & supplies
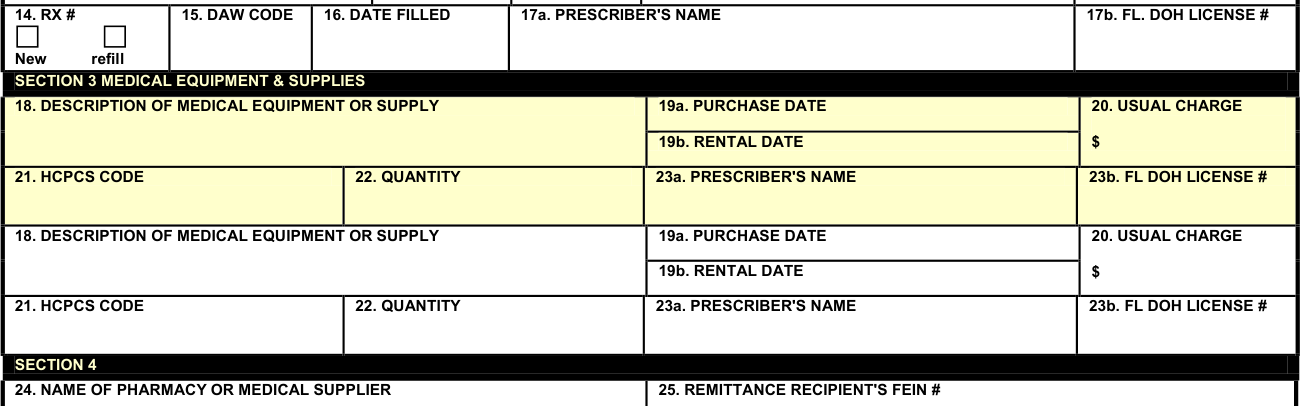
In Section 3 Medical Equipment & Supplies, enter the description of medical equipment or supply in Box 18, the purchase date in Box 19a, the rental date in Box 19b and the usual charge in Box 20.
Enter the HCPCS code in Box 21, the quantity in Box 22, the prescriber's name in Box 23a and the FL DOH license number in Box 23b.
Section 4
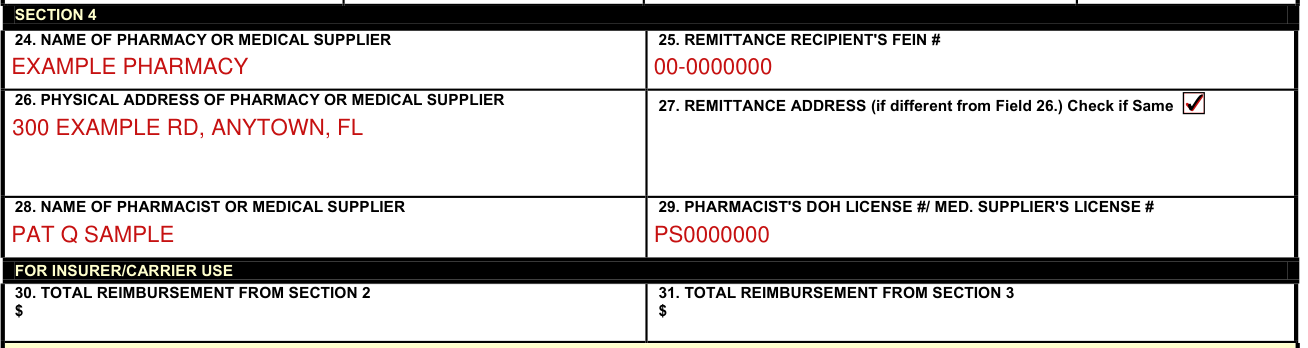
In Section 4, enter the name of pharmacy or medical supplier in Box 24 and the remittance recipient's FEIN number in Box 25.
Enter the physical address of pharmacy or medical supplier in Box 26. Box 27 is the remittance address (if different from Field 26.); Check if Same.
Enter the name of pharmacist or medical supplier in Box 28 and the pharmacist's DOH license number or the medical supplier's license number in Box 29.
Boxes 30 and 31 are under FOR INSURER/CARRIER USE: Box 30 is Total Reimbursement from Section 2 and Box 31 is Total Reimbursement from Section 3.
More rules for Form DFS-F5-DWC-10
Rule 69L-7.720, F.A.C.
Common questions about Form DFS-F5-DWC-10
Is there a penalty?
Any person who knowingly and with intent to injure, defraud, or deceive any employer or employee, insurance company, or self-insured program, files a statement of claim containing any false or misleading information is guilty of a felony of the third degree.
Sources
[1] Form DFS-F5-DWC-10 (Rev. 1/1/2015), Statement of Charges for Drugs and Medical Equipment & Supplies, Florida Department of Financial Services, Division of Workers' Compensation (the Official source link on this page).