


Form ETA-9142B at a glance
What it is: Form ETA-9142B is the H-2B Application for Temporary Employment Certification of the U.S. Department of Labor.
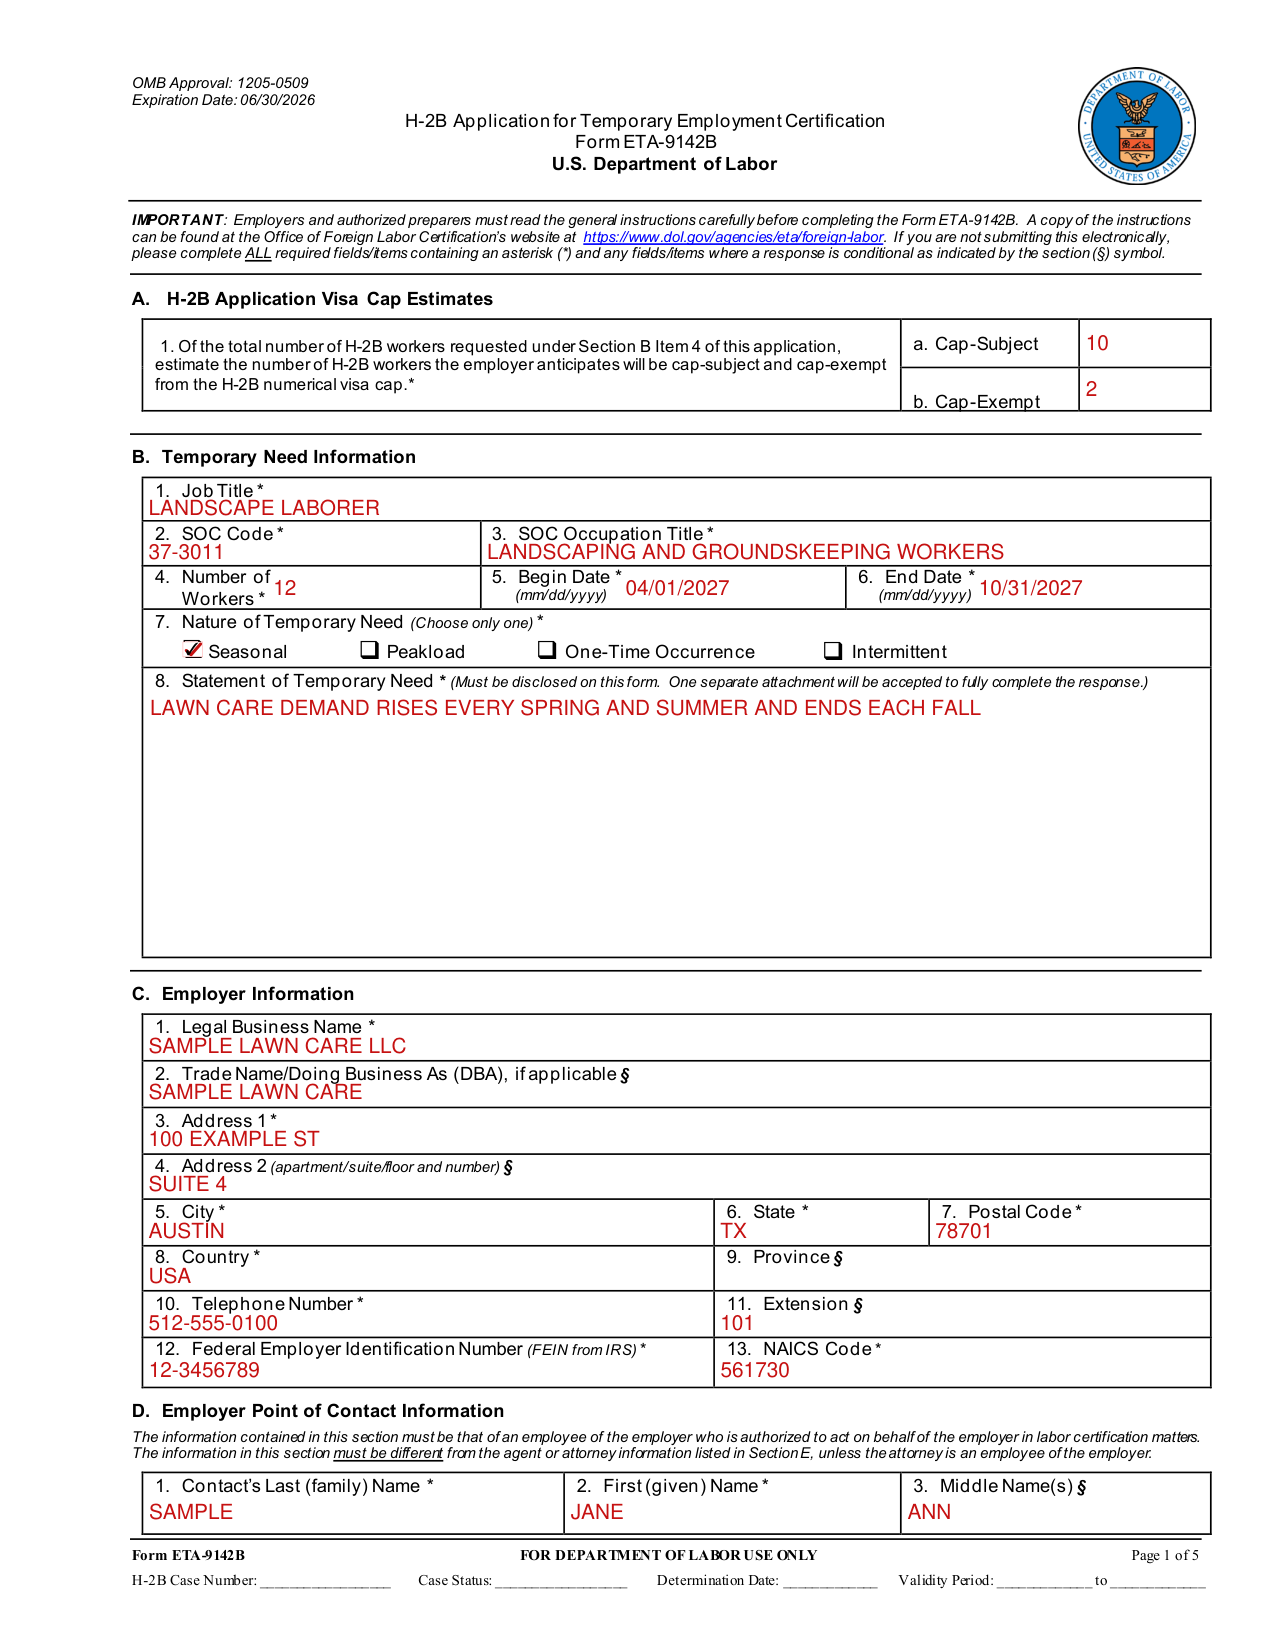
A filled-in Form ETA-9142B example: a landscaping employer requests seasonal workers
How to fill out Form ETA-9142B, box by box
A. H-2B Application Visa Cap Estimates

Estimate the number of H-2B workers the employer anticipates will be cap-subject (a) and cap-exempt (b) from the H-2B numerical visa cap, out of the total number of H-2B workers requested under Section B Item 4.
B. Temporary Need Information
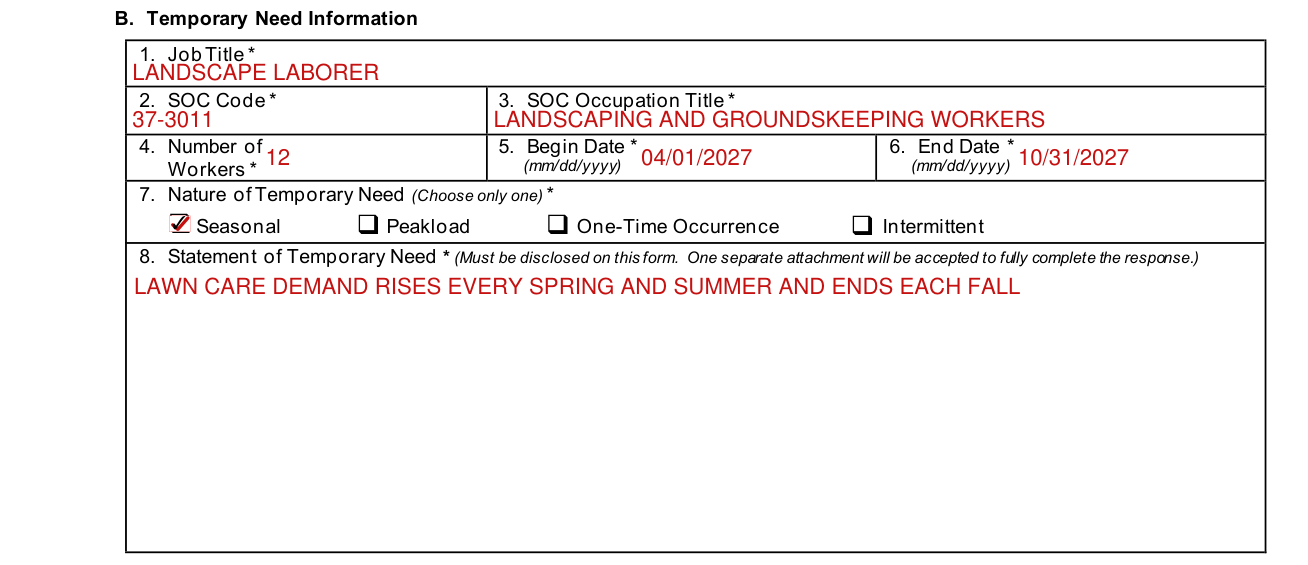
Enter the Job Title, the SOC Code and the SOC Occupation Title.
Enter the Number of Workers, the Begin Date and the End Date as (mm/dd/yyyy).
Choose only one Nature of Temporary Need: Seasonal, Peakload, One-Time Occurrence or Intermittent.
The Statement of Temporary Need must be disclosed on this form. One separate attachment will be accepted to fully complete the response.
C. Employer Information
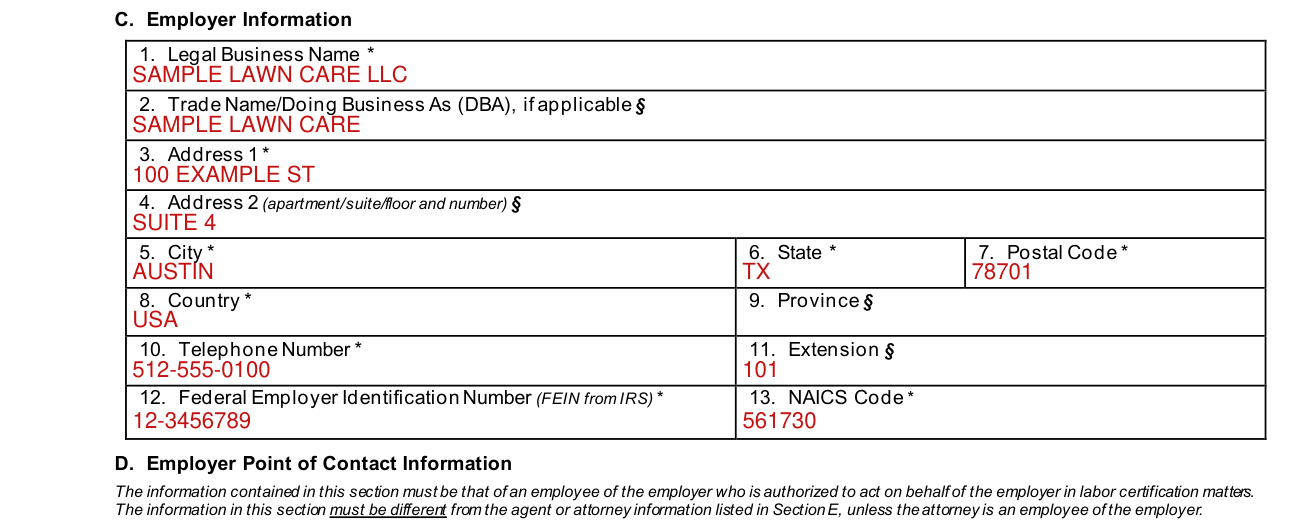
Enter the Legal Business Name, the Trade Name/Doing Business As (DBA), if applicable, Address 1 and Address 2 (apartment/suite/floor and number).
Enter the City, State, Postal Code, Country, Province, Telephone Number, Extension, Federal Employer Identification Number (FEIN from IRS) and NAICS Code.
D. Employer Point of Contact Information
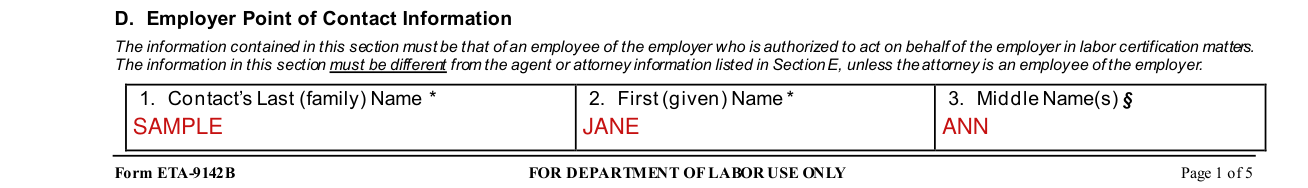
The information in this section must be that of an employee of the employer who is authorized to act on behalf of the employer in labor certification matters. The information in this section must be different from the agent or attorney information listed in Section E, unless the attorney is an employee of the employer.
Enter the Contact's Last (family) Name, First (given) Name and Middle Name(s).
More rules for Form ETA-9142B
Employers and authorized preparers must read the general instructions carefully before completing the Form ETA-9142B. If you are not submitting this electronically, please complete ALL required fields/items containing an asterisk (*) and any fields/items where a response is conditional as indicated by the section (§) symbol.
If your situation is different
Contact's Job Title, Address 1 and Business Email Address
Enter the Contact's Job Title, Address 1, Address 2 (apartment/suite/floor and number), City, State, Postal Code, Country, Province, Telephone Number, Extension and Business Email Address.
Section E, Attorney or Agent Information (If applicable)
Indicate the type of representation for the employer in the filing of this application: Attorney, Agent or None. Complete the remainder of this section if “Attorney” or “Agent” is marked.
Enter the Attorney or Agent's Last (family) Name, First (given) Name, Middle Name(s), Address 1, Address 2 (apartment/suite/floor and number), City, State, Postal Code, Country, Province, Telephone Number, Extension, Law Firm/Business Email Address, Law Firm/Business Name and Law Firm/Business FEIN.
If “Attorney” is marked in question E.1, complete questions 17 to 19: 17. State Bar Number(s), 18. State of highest court where attorney is in good standing and 19. Name of the highest state court where attorney is in good standing.
If “Agent” is marked in question E.1, complete questions 20 and 21. 20. Is a copy of the current agreement or other documentation demonstrating the agent's authority to represent the employer in this application attached? Yes or No. 21. Is a copy of the agent's current Migrant and Seasonal Agricultural Worker Protection Act (MSPA) Certificate of Registration identifying the farm labor contracting activities the agent is authorized to perform attached to this application? Yes, No or N/A.
Section F.a, Job Opportunity and Minimum Requirements
Indicate whether a copy of the job order submitted to the State Workforce Agency (SWA) satisfying the requirements at 20 CFR 655.18 is attached to this application (Yes or No).
Enter the Name of the State and the Date Job Order Submitted.
Describe the specific services or labor to be performed in the Job Duties. All job duties must be disclosed on this form.
An entry is required for each box of the Anticipated days and hours of work per week. Enter the Hourly work schedule.
Education: minimum U.S. diploma/degree required: None, High School/GED, Associate's, Bachelor's, Master's, Doctorate (PhD) or Other degree (JD, MD, etc.).
Enter the number of months required for Training and for Work Experience.
Supervision: does this position supervise the work of other employees? Yes or No. If “Yes” to question 10, enter the number of employees worker will supervise.
List specific skills, licenses/certifications, field(s) of training, and requirements of the job under Special Requirements.
Section F.b, Place of Employment and Wage Information
Enter the Worksite Address, the Worksite Address (apartment/suite/floor and number), City, State and Postal Code.
Enter the County and the Metropolitan Statistical Area (MSA) Name/OES Area Title.
8a. Enter the Basic Wage Rate Paid From and To. 8b. Choose only one Per: Hour, Week, Bi-Weekly, Month, Year or Piece Rate.
8c. Are overtime hours available for this job opportunity at any work locations for the 9142B and Appendix A? Yes or No.
8d. Enter the Wage Rate Range for Overtime Pay From and To.
Enter Additional conditions about the wage rate to be paid at any work locations.
DOL Prevailing Wage Determination (PWD) Information: enter 10. 1st PWD Case Number, 10a. 2nd PWD Case Number and 10b. 3rd PWD Case Number.
If a valid PWD has not been obtained due to an emergency situation under 20 CFR 655.17, indicate whether a completed Form ETA-9141 is attached to this application (Yes, No or N/A).
Section F.c, Additional Place of Employment and Wage Information, and F.d, Other Material Terms and Conditions of the Job Offer
Will work be performed at worksite locations other than the one identified in Section F.b.? Yes or No. 2. If “Yes” is marked in question F.c.1, indicate whether a completed Appendix A is attached to this application.
For Daily Transportation, On-the-Job Training Available, Employer-Provided Tools and Equipment, and Board, Lodging, or Other Facilities, mark Yes or N/A; for tools and equipment, Workers will be provided, without charge or deposit charge, all tools, supplies, and equipment required to perform the duties assigned. State all deduction(s) from pay and, if known, the amount(s).
Section F.e, Recruitment Information
Enter the Telephone Number to Apply, Email Address to Apply and Website address (URL) to Apply.
Section G, Other Supporting Documentation
Type of Employer Application (Choose only one): Individual Employer or Joint Employer (e.g., Job Contractor).
Is a copy of the employer's current MSPA Certificate of Registration identifying the farm labor contracting activities the employer is authorized to perform attached to this application? Yes, No or N/A.
Foreign Labor Recruiter Information
Is the employer, and its attorney or agent, as applicable, engaging or planning to engage any agent(s) or recruiter(s) in the recruitment of prospective H-2B workers, regardless of whether such agent(s) or recruiter(s) is (are) located in the U.S. or abroad? Yes or No.
Indicate whether a copy of all agreements with any agent or recruiter whom you are engaging or planning to engage in the recruitment of H-2B workers is attached to this application (Yes, No or N/A).
Indicate whether a completed Appendix C providing the identity and location of all persons and entities hired by or working for the agent or recruiter subject to the agreement(s), including any of the agents or employees of those persons and entities, is attached to this application (Yes, No or N/A).
Section H, Declaration of Employer and Attorney/Agent
Declaration of Employer and Attorney/Agent: in accordance with Federal regulations, the employer(s) must attest to abide by certain terms, assurances, and obligations as a condition for receiving a temporary labor certification from the U.S. Department of Labor.
Applications that fail to attach Appendix B will not be certified by the Department.
Confirm that you have read and agree to all the applicable terms, assurances, and obligations contained in Appendix B and have attached a signed and dated copy of Appendix B with this application (Yes or No).
Section I, Preparer
Complete this section if the preparer of this application is a person other than the one identified in either Section D (employer point of contact) or Section E (attorney or agent) of this application. Enter the Last (family) Name, First (given) Name, Middle Initial, Law Firm/Business FEIN, Law Firm/Business Name and Law Firm/Business Email Address.
Sources
[1] Form ETA-9142B (OMB 1205-0509), H-2B Application for Temporary Employment Certification, U.S. Department of Labor (the Official source link on this page).