

Form 5021 at a glance
What it is: Form 5021 is the State of California Doctor's First Report of Occupational Injury or Illness.
Who signs: The Physician Signature is an original signature, do not stamp.
A filled-in Form 5021 example: a doctor reports a workplace fall

How to fill out Form 5021, box by box
Insurer Name and Address, Employer Name and Address

Enter the Insurer Name and Address in box 1.
Enter the Employer Name in box 2.
Enter the Address No. and Street, City and Zip Code in box 3.
Patient Name, Sex, Date of Birth, Address and Phone Number
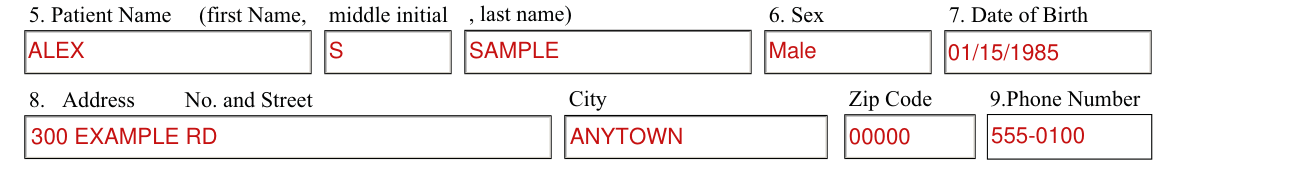
Enter the Patient Name (first Name, middle initial, last name) in box 5, the Sex in box 6 and the Date of Birth in box 7.
Enter the Address No. and Street, City and Zip Code in box 8, and the Phone Number in box 9.
Occupation, Social Security Number and Where Injury Occurred

Enter the Occupation (Specific job title) in box 10, the Social Security Number in box 11, and the Address No.& Street Where Inj. Occurred in box 12, with the City Where Injury Occ. and County.
Providing a social security number is required on this form pursuant to Labor Code § 6409.
If you do not have a social security number, indicate this in the space provided for the injured worker's social security number.
Dates and hours, and previous treatment

Enter the Date and hour of injury or onset of illness in box 13.
Enter the Date last worked in box 14, the Date and hour of 1st exam or treatment in box 15, and in box 16 Have you or your office previously rendered treatment.
How the accident happened, Subjective Complaints and Objective Findings

Patient please complete this portion, if able to do so. Otherwise, doctor please complete immediately, inability or failure of a patient to complete this portion shall not affect his/her rights to workers' compensation under the California Labor Code.
Describe how the accident or exposure happened in box 17: give specific object, machinery or chemical; use reverse side if more space is required.
Enter the SUBJECTIVE COMPLAINTS in box 18.
Under box 19, Objective Findings, enter A. Physical Examination and B. X-ray and laboratory results (State if none or pending.).
Diagnoses
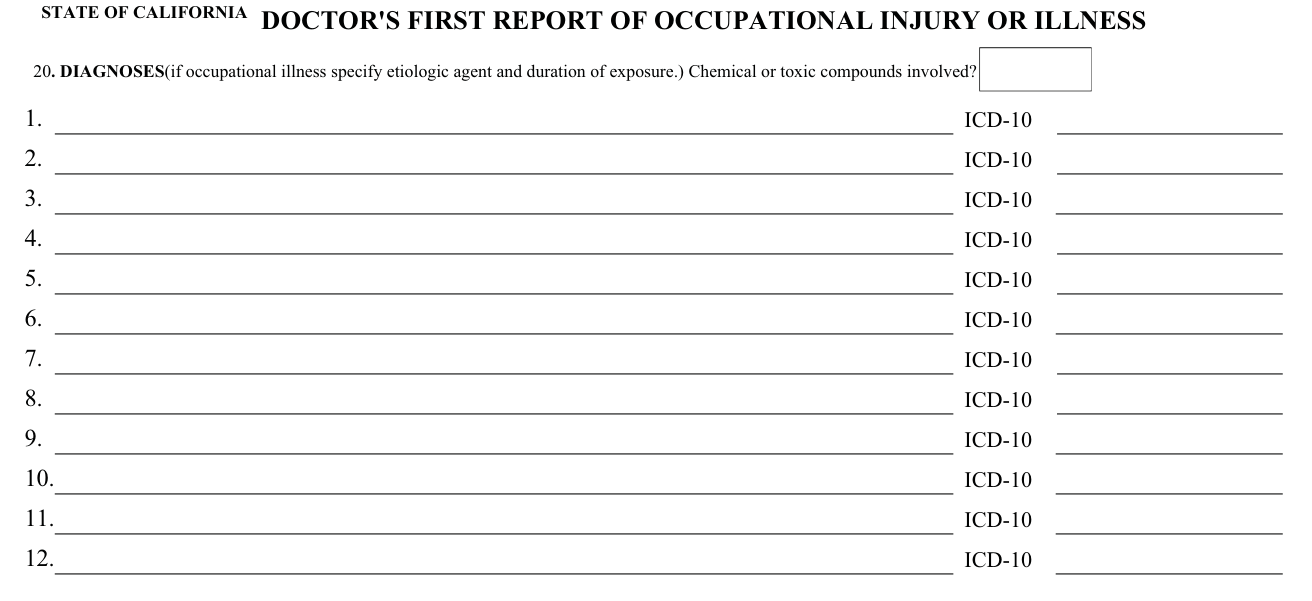
In box 20, DIAGNOSES: if occupational illness specify etiologic agent and duration of exposure. Chemical or toxic compounds involved?
On lines 1 to 12, enter the ICD-10.
Findings consistent and other condition

Box 21: Are your findings and diagnosis consistent with patient's account of injury or onset of illness? If "no," please explain in box 21.
Box 22: Is there any other current condition that will impede or delay patient's recovery? If "yes," please explain in box 22.
Treatment, hospital and work status
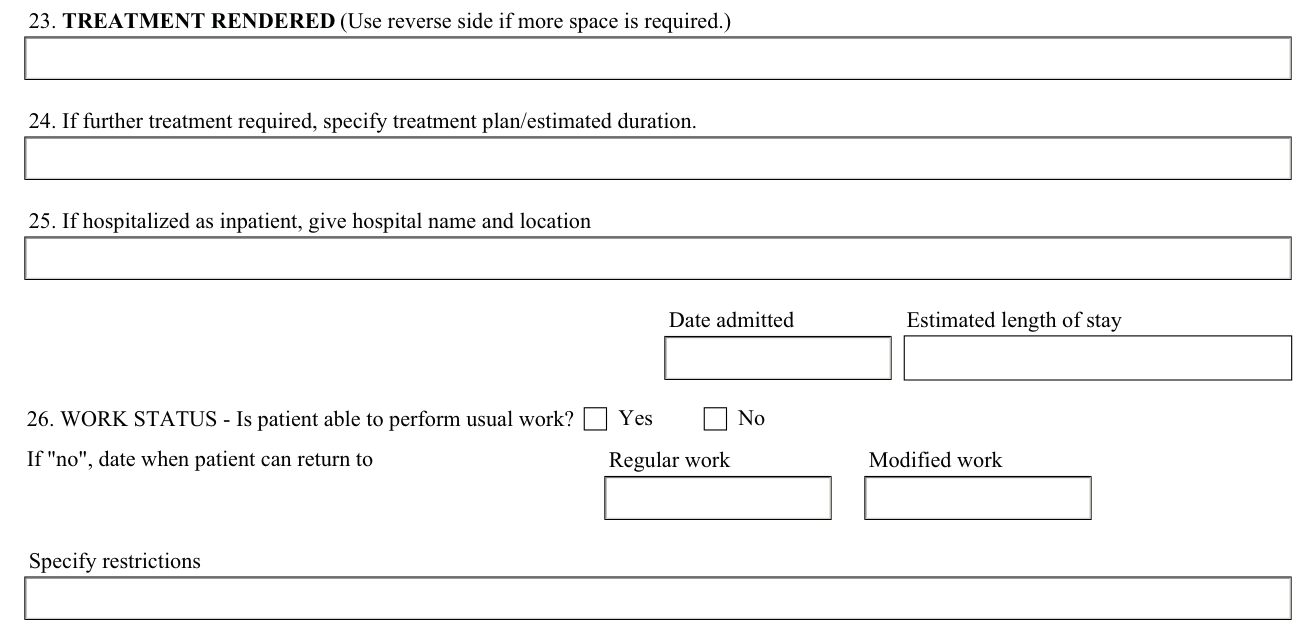
Enter the TREATMENT RENDERED in box 23, and use reverse side if more space is required.
In box 24, if further treatment required, specify treatment plan/estimated duration.
In box 25, if hospitalized as inpatient, give hospital name and location, with the Date admitted and Estimated length of stay.
In box 26, WORK STATUS: Is patient able to perform usual work? Yes No
If "no", date when patient can return to Regular work or Modified work, and Specify restrictions.
Physician signature and declaration

"I declare under penalty of perjury that this report is true and correct to the best of my knowledge and that I have not violated Labor Code section 139.3."
Sign the Physician signature. Enter the Cal. License Number, Executed at, Signature Date (mm/dd/yyyy), Physician Name, Specialty, Physician address and Phone Number.
If your situation is different
Within 5 days, failure to file, or pesticide poisoning
Within 5 days of your initial examination, for every occupational injury or illness, send two copies of this report to the employer's workers' compensation insurance carrier or the insured employer. Failure to file a timely doctor's report may result in assessment of a civil penalty. In the case of diagnosed or suspected pesticide poisoning, send a copy of the report to Department of Industrial Relations, P.O. Box 420603, San Francisco, CA 94142-0603, and notify your local health officer by telephone within 24 hours.
A knowingly fraudulent material statement
Any person who makes or causes to be made any knowingly fraudulent material statement or material representation for the purpose of obtaining or denying workers' compensation benefits or payments is guilty of a felony.
Sources
[1] Form 5021 (Rev. 5) 10/2015, Doctor's First Report of Occupational Injury or Illness, California Department of Industrial Relations (the Official source link on this page).
