

Claim Form at a glance
What it is: The Claim Form for International Healthcare Plans for Qatar is completed in BLOCK CAPITALS.
Who signs: Under 8 DECLARATION, add the Patient's signature and Date; if a minor was treated, a parent or guardian should sign and date this section.
What to bring and attach to Claim Form
It is your responsibility to retain any original supporting documentation (e.g. medical receipts) where copies are submitted, as the original supporting documentation/receipts can be requested up to 12 months after claims settlement for auditing purposes. A proof of payment by you (e.g. bank or credit card statement) can also be requested in respect of your medical receipts.
A filled-in Claim Form example: a paid consultation
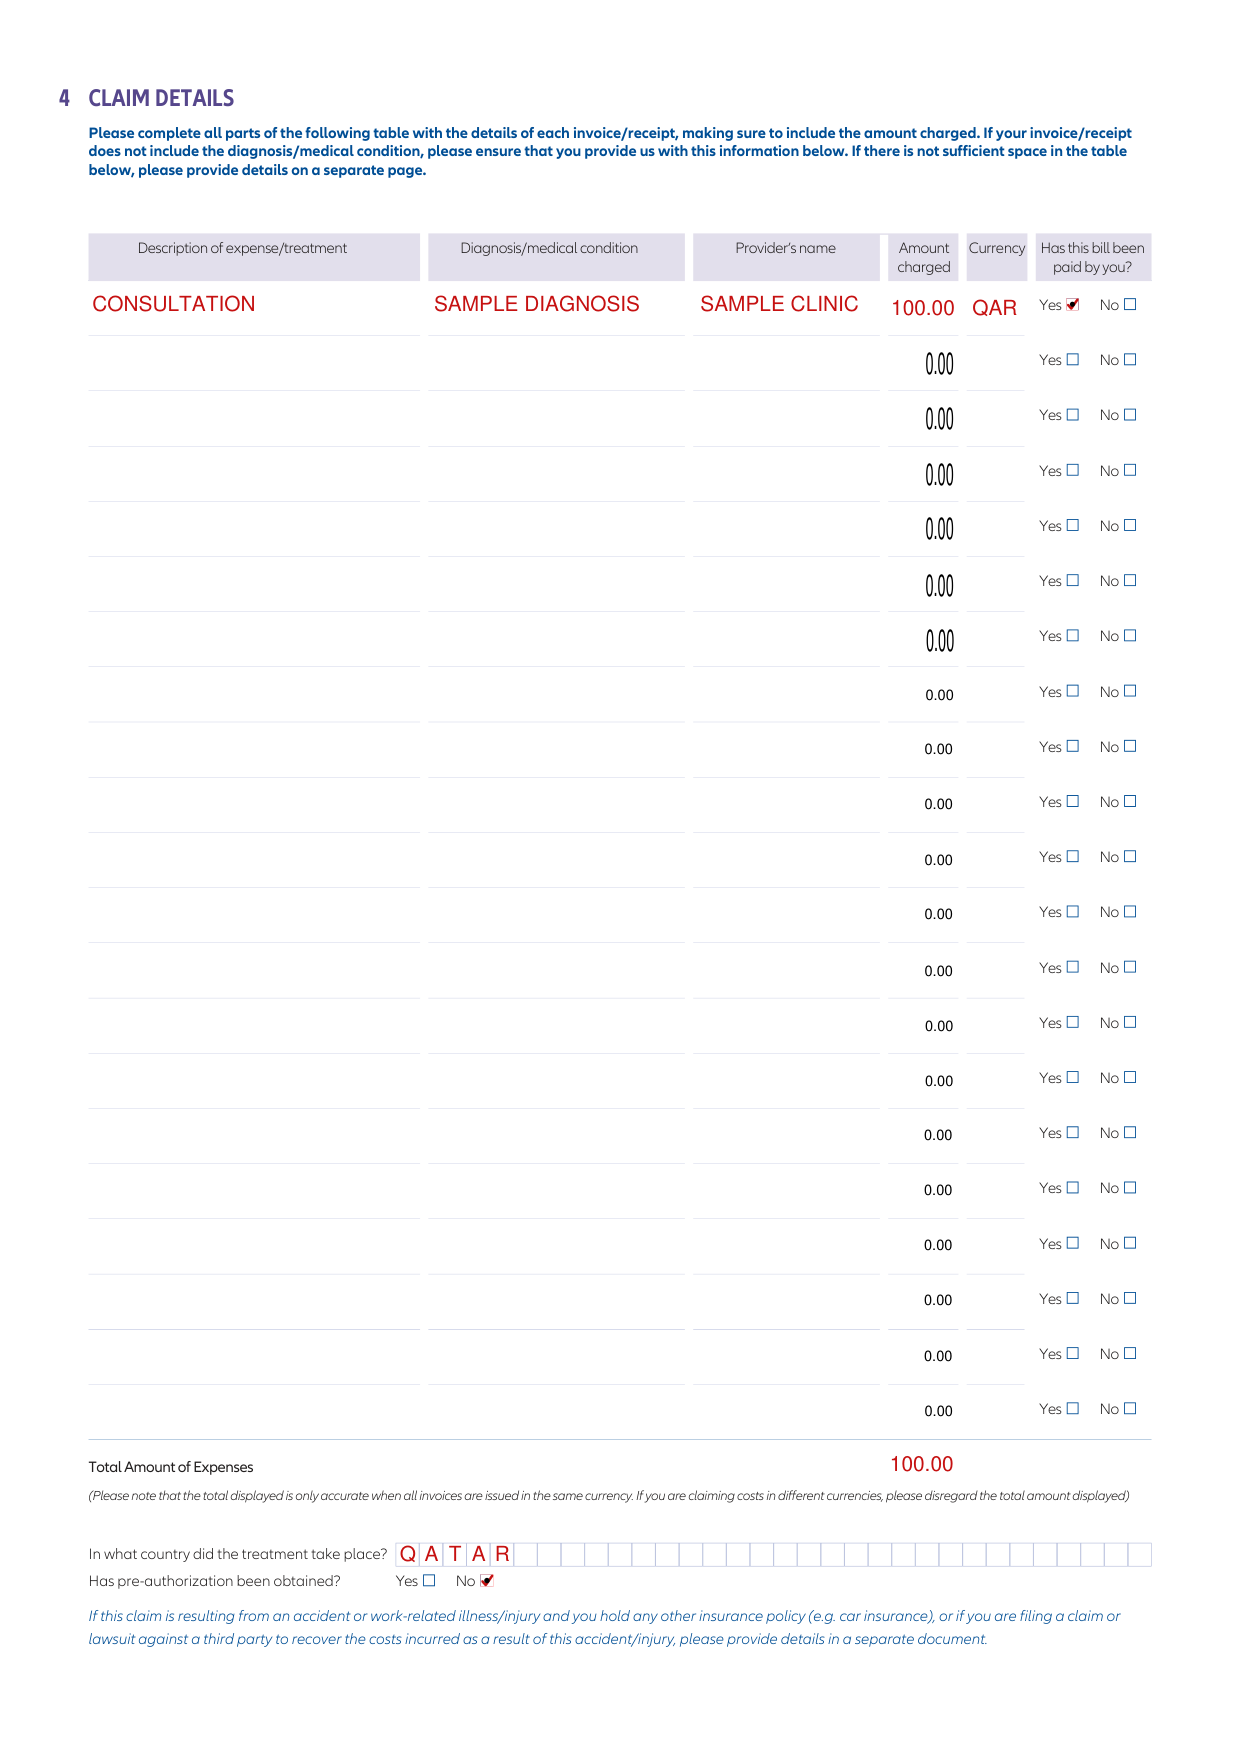
How to fill out Claim Form, box by box
Policyholder's details
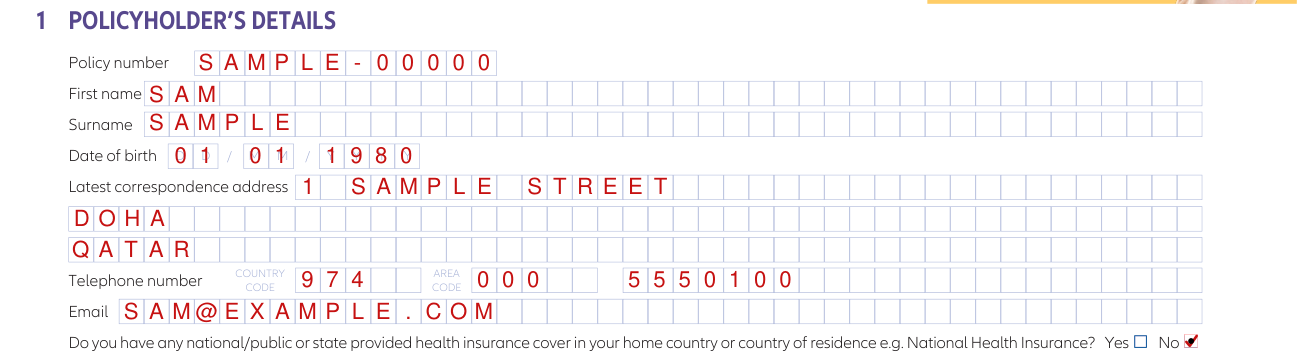
Under 1 POLICYHOLDER'S DETAILS, enter the Policy number, First name, Surname, Date of birth, Latest correspondence address, Telephone number (COUNTRY CODE and AREA CODE) and Email.
National or state provided health insurance cover

Mark Yes or No for any national/public or state provided health insurance cover in your home country or country of residence e.g. National Health Insurance. If Yes, provide a description of the cover provided along with your reference number/identifier with the state.
Patient's details (if different from policyholder)
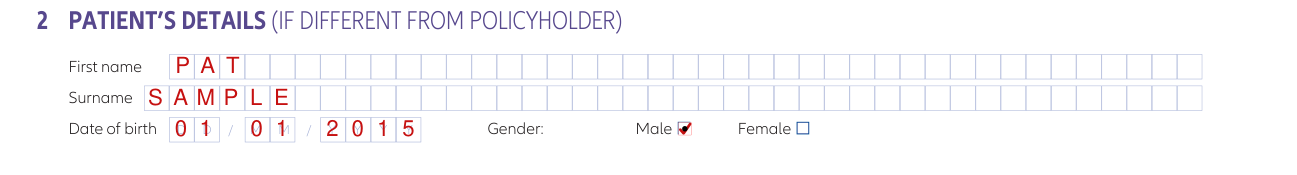
Under 2 PATIENT'S DETAILS (IF DIFFERENT FROM POLICYHOLDER), enter the First name, Surname and Date of birth, and mark the Gender: Male or Female.
Payment details

Under 3 PAYMENT DETAILS, Option 1 is Payment to policyholder: mark the Preferred payment method, Bank transfer (Recommended) or Cheque, and specify the currency you would like to be reimbursed in (and ensure that your bank account supports it).
For bank transfer, please provide bank details: the Name of bank account holder as it appears on your bank statement, Account number, IBAN (where required), Sort/branch code, BIC/Swift code, Name of bank and Bank address. Cheques payable to the policyholder will be sent to the correspondence address provided in section 1. If your bank is within the EU, or if your specific country requires an IBAN (e.g. Qatar, United Arab Emirates, Saudi Arabia, Angola, Tunisia, Turkey), please supply both your IBAN and BIC/Swift code to facilitate the payment of your claim.
If you are aware of any additional information required in order to process international transactions within your country (e.g. Agency Code, Tax ID), please list it, and enter the Swift code of intermediary bank (where applicable).
Option 2: Payment to medical provider (e.g. hospital, specialist), if you have not already paid the medical provider. Tick if direct billing has been previously agreed.
Claim details
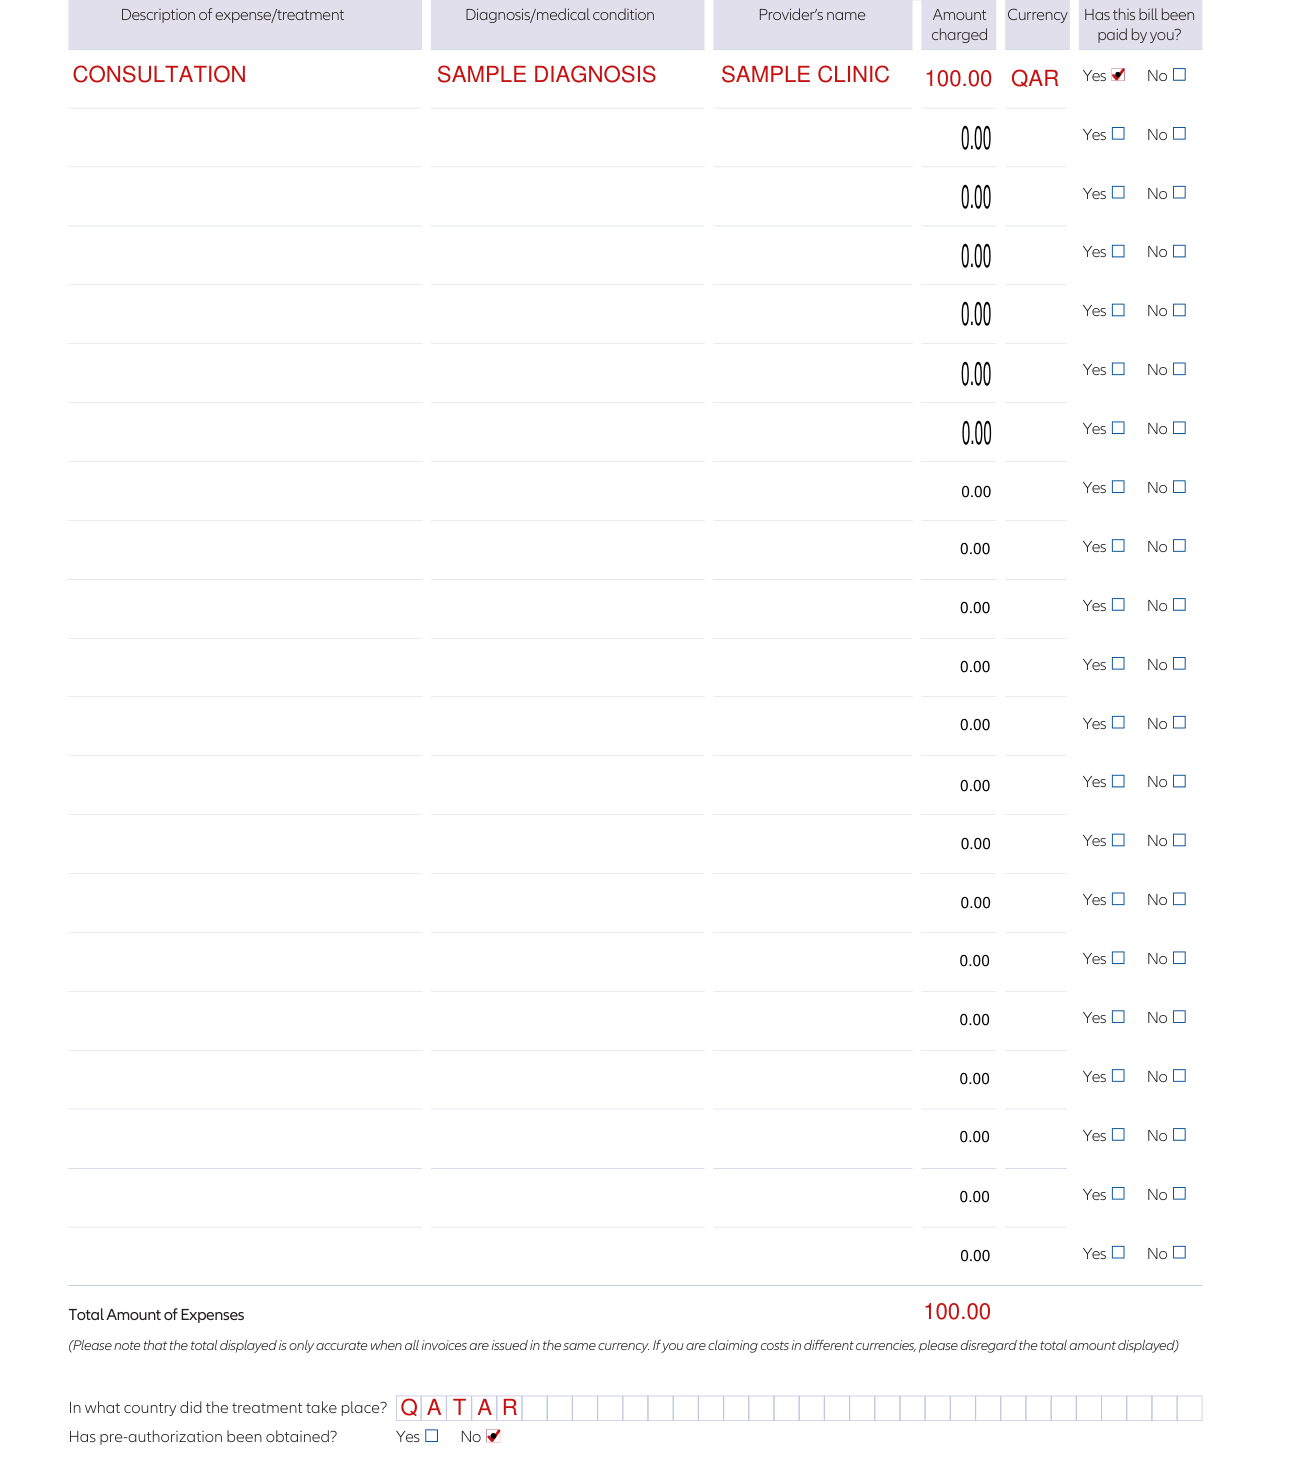
Under 4 CLAIM DETAILS, complete all parts of the table with the details of each invoice/receipt, making sure to include the amount charged: Description of expense/treatment, Diagnosis/medical condition, Provider's name, Amount and Currency, and mark Yes or No to Has this bill been charged paid by you?
If your invoice/receipt does not include the diagnosis/medical condition, please ensure that you provide this information in the Diagnosis/medical condition box.
If there is not sufficient space in the table, please provide details on a separate page.
The Total Amount of Expenses displayed is only accurate when all invoices are issued in the same currency. If you are claiming costs in different currencies, please disregard the total amount displayed.
Enter the country in the box for In what country did the treatment take place? and mark Yes or No to Has pre-authorization been obtained?
If this claim is resulting from an accident or work-related illness/injury and you hold any other insurance policy (e.g. car insurance), or if you are filing a claim or lawsuit against a third party to recover the costs incurred as a result of this accident/injury, please provide details in a separate document.
Medical provider's details
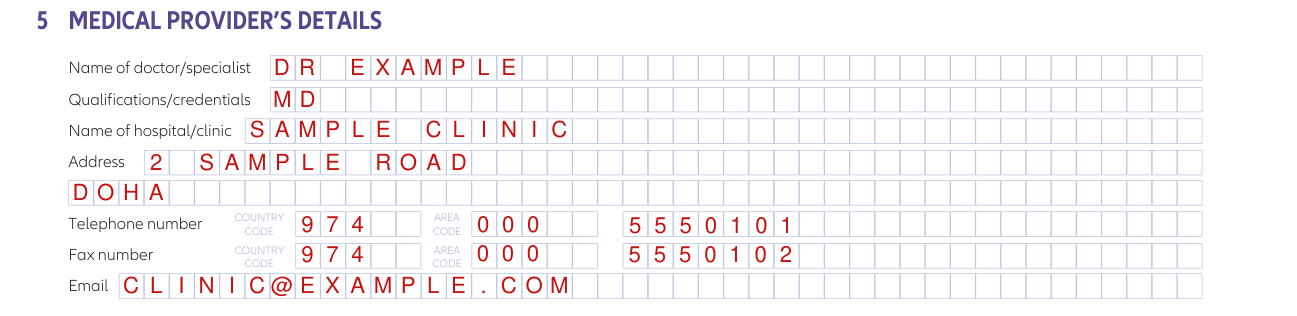
Under 5 MEDICAL PROVIDER'S DETAILS, enter the Name of doctor/specialist, Qualifications/credentials, Name of hospital/clinic, Address, Telephone number (COUNTRY CODE and AREA CODE), Fax number (COUNTRY CODE and AREA CODE) and Email.
The treating doctor completes sections 5 and 6 unless detailed in the supporting documentation (e.g. receipts or invoices), and signs and authenticates with an official stamp.
Physiotherapy or psychotherapy referral

Applicable to physiotherapy/psychotherapy claims only: please provide full referral details: Name of referring physician, Telephone number and Date of referral.
Medical details
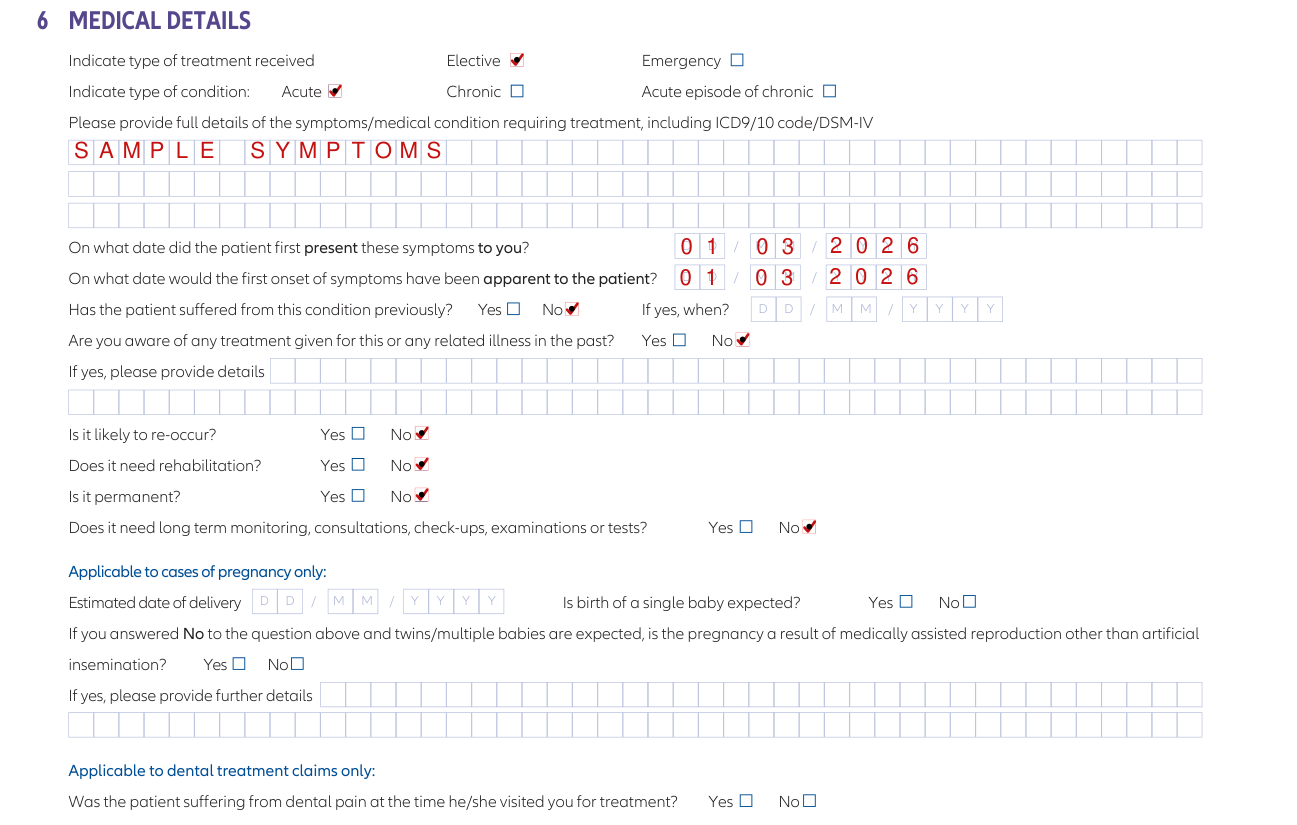
Under 6 MEDICAL DETAILS, indicate type of treatment received, Elective or Emergency, indicate type of condition: Acute, Chronic or Acute episode of chronic, and provide full details of the symptoms/medical condition requiring treatment, including ICD9/10 code/DSM-IV.
Enter the date on which the patient first presented these symptoms to you and the date on which the first onset of symptoms would have been apparent to the patient.
Mark Yes or No to Has the patient suffered from this condition previously? and, if yes, when. Mark Yes or No to Are you aware of any treatment given for this or any related illness in the past? If yes, please provide details.
Mark Yes or No for Is it likely to re-occur?, Does it need rehabilitation?, Is it permanent? and Does it need long term monitoring, consultations, check-ups, examinations or tests?
Applicable to cases of pregnancy only: enter the Estimated date of delivery and mark Yes or No to Is birth of a single baby expected? If you answered No to Is birth of a single baby expected? and twins/multiple babies are expected, is the pregnancy a result of medically assisted reproduction other than artificial insemination? If yes, please provide further details.
Applicable to dental treatment claims only: mark Yes or No to Was the patient suffering from dental pain at the time he/she visited you for treatment?
Declaration

Under 8 DECLARATION, you certify that to the best of your knowledge, this Claim Form does not contain any false, misleading or incomplete information.
If this claim is found to be fraudulent, in whole or in part, the contract will be cancelled from the date of discovery of the fraudulent event and you may be liable to prosecution.
You agree to waive any rights that you may have to medical secrecy/confidentiality in respect of your medical information and you authorize your medical practitioner, health professional or other relevant medical establishment to provide relevant medical information relating to you, if requested by Allianz Partners, its medical advisers, its appointed representatives, or to any third party expert(s) in case of disputes, subject to any legal restrictions which may apply.
Third party authorization

Under 9 THIRD PARTY AUTHORIZATION, insert the name of the third party you authorize, as the claimant, to act for and on your behalf and on behalf of any dependents named on this form (where applicable) in relation to the administration of this claim, which may include the disclosure of sensitive medical information.
Add the Claimant's signature, Date and Claimant's printed name.
Important, please check the following

Please check the following: all receipts, invoices and prescriptions are attached; the Claim Form is completed in full; the declarations are signed and dated; the diagnosis has been confirmed and is either stated on the Claim Form or on the invoice(s).
Common questions about Claim Form
Where do I file it?
Send your fully completed claim form(s) with invoices/receipts by email to: claims@allianzworldwidecare.com, by fax to: + 353 1 645 4033, or by post to: Claims Department, Allianz Partners, 15 Joyce Way, Park West Business Campus, Nangor Road, Dublin 12, Ireland.
Where to get help with Claim Form
Contact the helpline if you have any queries: 8000 155 (calling toll-free from within Qatar) or +974 4031 8444 (calling from within or outside of Qatar).
Sources
[1] Claim Form FRM-CF-Qatar-EN-1217, International Healthcare Plans for Qatar, Allianz Partners (the Official source link on this page).
