

Form C-3 at a glance
What it is: Form C-3, the Employee Claim of the State of New York Workers' Compensation Board: fill out this form to apply for workers' compensation benefits because of a work injury or work-related illness.
Who signs: Sign Form C-3 in the place provided for Employee's Signature on page 2, print your name, and enter the date you signed the form. An individual may sign on behalf of the employee only if they are legally authorized to do so and the employee is a minor, mentally incompetent or incapacitated.
What to bring and attach to Form C-3
If you filed a Department of Motor Vehicles Form MV-104 (Report of Motor Vehicle Accident), please submit a copy along with the C-3. This will expedite the process for you to receive potential benefits.
A filled-in Form C-3 example: a baker reports a fall at work

How to fill out Form C-3, box by box
A. Your information (Employee)
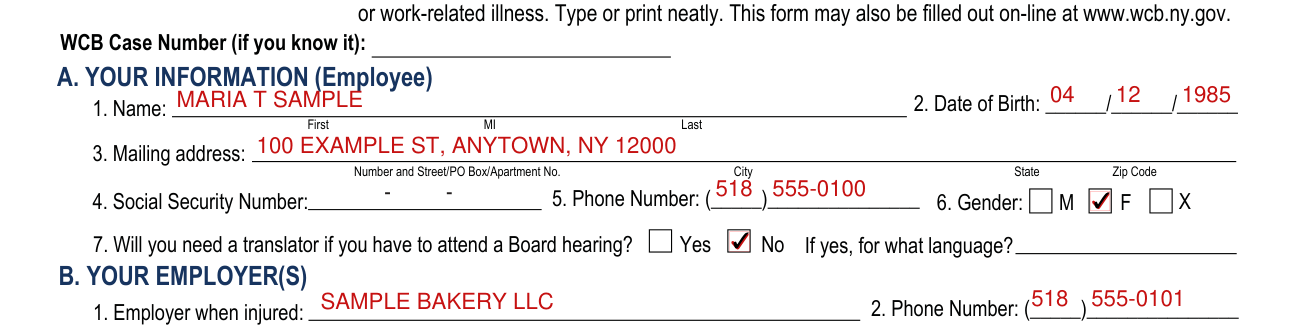
In Section A, enter your name, address and other requested information.
If you do not have or know your Workers' Compensation Board Case Number, please leave the WCB Case Number field blank. It is not required to process your claim.
Providing your social security number to the Board is voluntary. There is no penalty for failure to provide your social security number on this form; it will not result in a denial of your claim or a reduction in benefits.
Note on Item 7: Board hearings are conducted in English. If you need a translator, select Yes and indicate the language needed.
B. Your employer(s)
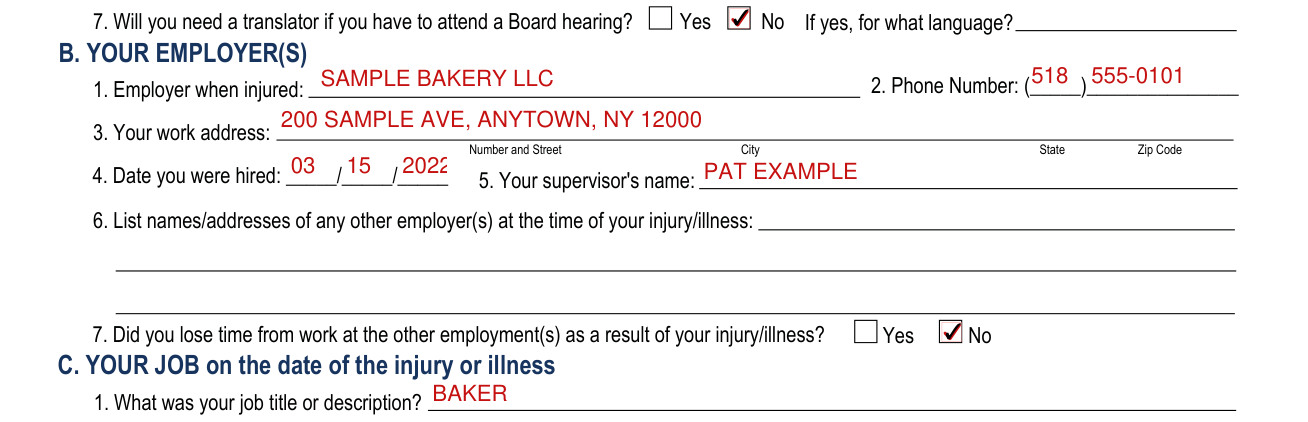
In Section B, enter the name, address, phone number and other information of the employer you were working for at the time of the injury/illness.
Your employer is the company or agency that issues your paycheck. If you are a contractor at a work site or office, the staffing agency or vendor who hired you is your employer, not the work site or office where you report to work.
C. Your job on the date of the injury or illness
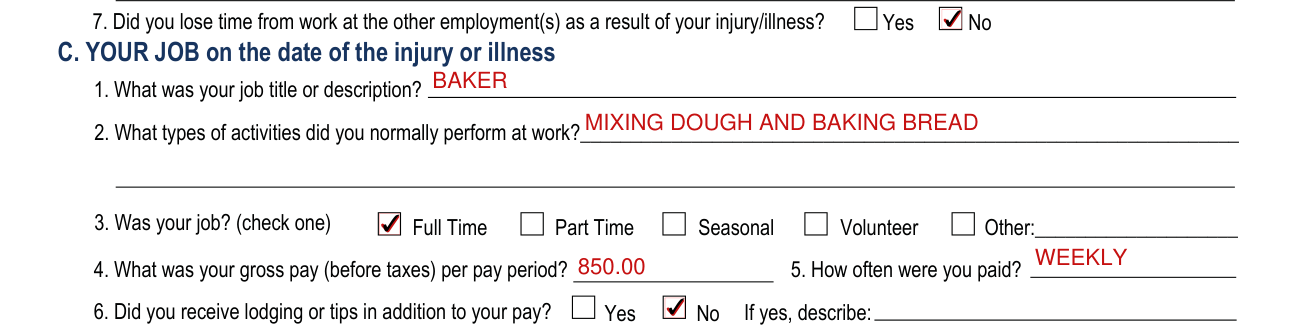
In Section C, enter your job title, work activities and pay information.
For Was your job?, check one: Full Time, Part Time, Seasonal, Volunteer or Other.
D. Your injury or illness
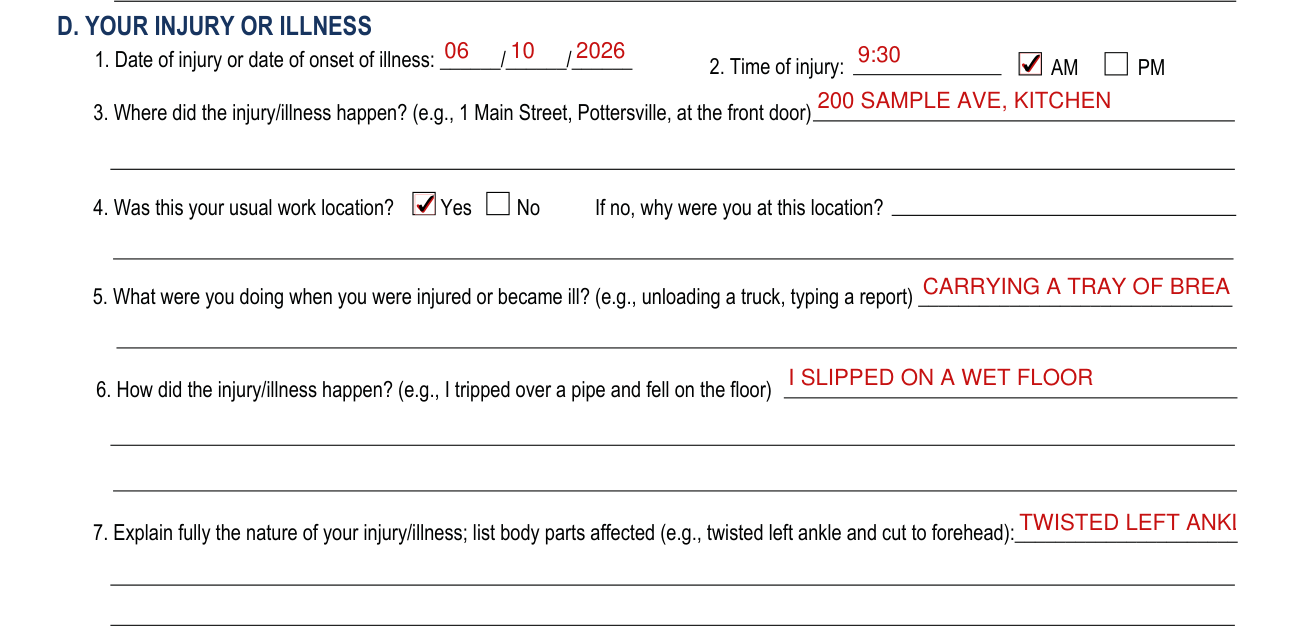
In Section D, enter your injury or illness information.
Item 1: Enter the date you were injured or the first date you noticed you became ill. The date you were injured must be in month/day/year format. The year should be written as four digits, e.g., 2015.
Item 2: Enter the time when the injury occurred. Check whether it was AM or PM. If this is an illness or occupational disease, skip item 2.
Item 3: Indicate the location where the injury/illness occurred, including the address of the building and the physical location in the building where the injury/illness happened.
Item 4: Check whether this was your normal work location. If it was not, explain why you were at this location.
Item 5: Describe in detail what you were doing at the time of the injury/illness (e.g., unloading boxes from a truck by hand). This explains the events leading up to the injury.
Item 6: Describe in detail how the injury/illness occurred (e.g., I was lifting a heavy box off a truck). This should include all people and events involved in the injury/illness.
Item 7: Indicate fully the nature and extent of your injury/illness, including all body parts injured.
More rules for Form C-3
If you need additional help completing this form, contact the Workers' Compensation Board at 1-877-632-4996.
Remember to enter your name and the date of your injury/ illness on the top of page two.
If your situation is different
Object involved in the accident or a licensed motor vehicle
Item 8: Indicate if some object was involved in the accident other than a licensed motor vehicle. Other objects may include a tool (e.g., hammer), a chemical (e.g., acid), machinery (e.g., forklift or drill press), etc. Item 9: Indicate if a licensed motor vehicle was involved in the accident.
Item 9, if a licensed motor vehicle was involved in the accident: check if the motor vehicle involved was yours, your employer's, or a third party's, and include the license plate number (if known). If your vehicle was involved, fill out the name and address of your automobile liability insurance carrier.
Notice of your injury or illness and anyone who saw the injury happen
Item 10: Check if you gave your employer or supervisor notice of your injury or illness. If so, indicate who you gave notice to as well as if it was orally or in writing. Include the date you gave notice.
Item 11: Check if anyone else saw the injury happen. If anyone did see it, include their name(s).
Section E - Return to Work
Section E, Item 1: If you stopped working as a result of your work-related injury/illness, check Yes and indicate the date you stopped working. If you have not stopped working, check No and skip to the next section.
Item 2: If you have since returned to work, check Yes. Also indicate on what date you started working again, as well as if you have returned to your Normal Duties or if you are on Limited or Restricted Duty. (If you have not returned to your full pre-injury or illness work duties, then you are on Limited Duty.)
Item 3: If you have returned to work, indicate who you are working for now.
Item 4: Enter your gross pay (before tax pay) per pay period for the job you are working at now. Indicate how often you are receiving a paycheck (weekly, bi-weekly, etc.).
Section F - Medical Treatment for This Injury or Illness
C-3.0 (6-22) Section F, Item 1: If you did not receive medical treatment for this injury/illness, check None Received and skip to item 5. Otherwise, enter the date you first received treatment for this injury/illness and complete the rest of this section.
Item 2: Check if you were first treated on the job for this injury or illness.
Item 3: Check the location where you first received off site medical treatment for your injury or illness. Include the name and address of the facility as well as the phone number (including area code).
Item 4: If you are still receiving ongoing treatment for the same injury or illness, check Yes and indicate the name and address of the doctor(s) providing treatment as well as the phone number (including area code); otherwise, check No. Item 5: If you already had an injury to the same body part or a similar illness, check Yes and indicate if you were treated by a doctor for this injury or illness. If you were treated by a doctor, indicate the name(s) and address(es) of the doctor(s) whom provided care and complete and file Form C-3.3 together with this form.
Item 6: If you had a previous injury or illness, check if your previous injury or illness was work-related. If Yes, check if the injury or illness happened while working for your current employer.
Signing the form
If a third-party is signing on behalf of the employee, that person should sign on the second signature line.
If you have legal representation, your representative must complete and sign the attorney/representative's certification section on the bottom of page 2.
Common questions about Form C-3
What is a C3 form for workers' comp?
Form C-3, the Employee Claim of the State of New York Workers' Compensation Board: fill out this form to apply for workers' compensation benefits because of a work injury or work-related illness. You may also fill this form out online at wcb.ny.gov.
Is there a deadline?
Failure to file within two years after the date of injury may result in your claim being denied.
Where do I file it?
Please complete this form and send it to the Workers' Compensation Board centralized mailing address: New York State Workers' Compensation Board Centralized Mailing, PO Box 5205, Binghamton, NY 13902-5205.
Is there a penalty?
Any person who knowingly and with INTENT TO DEFRAUD presents, causes to be presented, or prepares with knowledge or belief that it will be presented to, or by an insurer, or self-insurer, any information containing any FALSE MATERIAL STATEMENT or conceals any material fact, SHALL BE GUILTY OF A CRIME and subject to substantial FINES AND IMPRISONMENT.
What am I certifying when I sign?
By signing, you affirm that the information you are providing is true and accurate to the best of your knowledge and belief. If you have an attorney or representative, they sign a certification. They certify, to the best of their knowledge, information and belief, that the allegations and other factual matters asserted on this form have evidentiary support, or are likely to have evidentiary support after a reasonable opportunity for further investigations or discovery. That belief is formed after an inquiry reasonable under the circumstances.
Sources
[1] Form C-3 (6-22), Employee Claim, State of New York Workers' Compensation Board (the Official source link on this page).
