

Form CMS-671 at a glance
What it is: Form CMS-671 (09/2023) is the Long-Term Care Facility Application for Medicare and Medicaid.
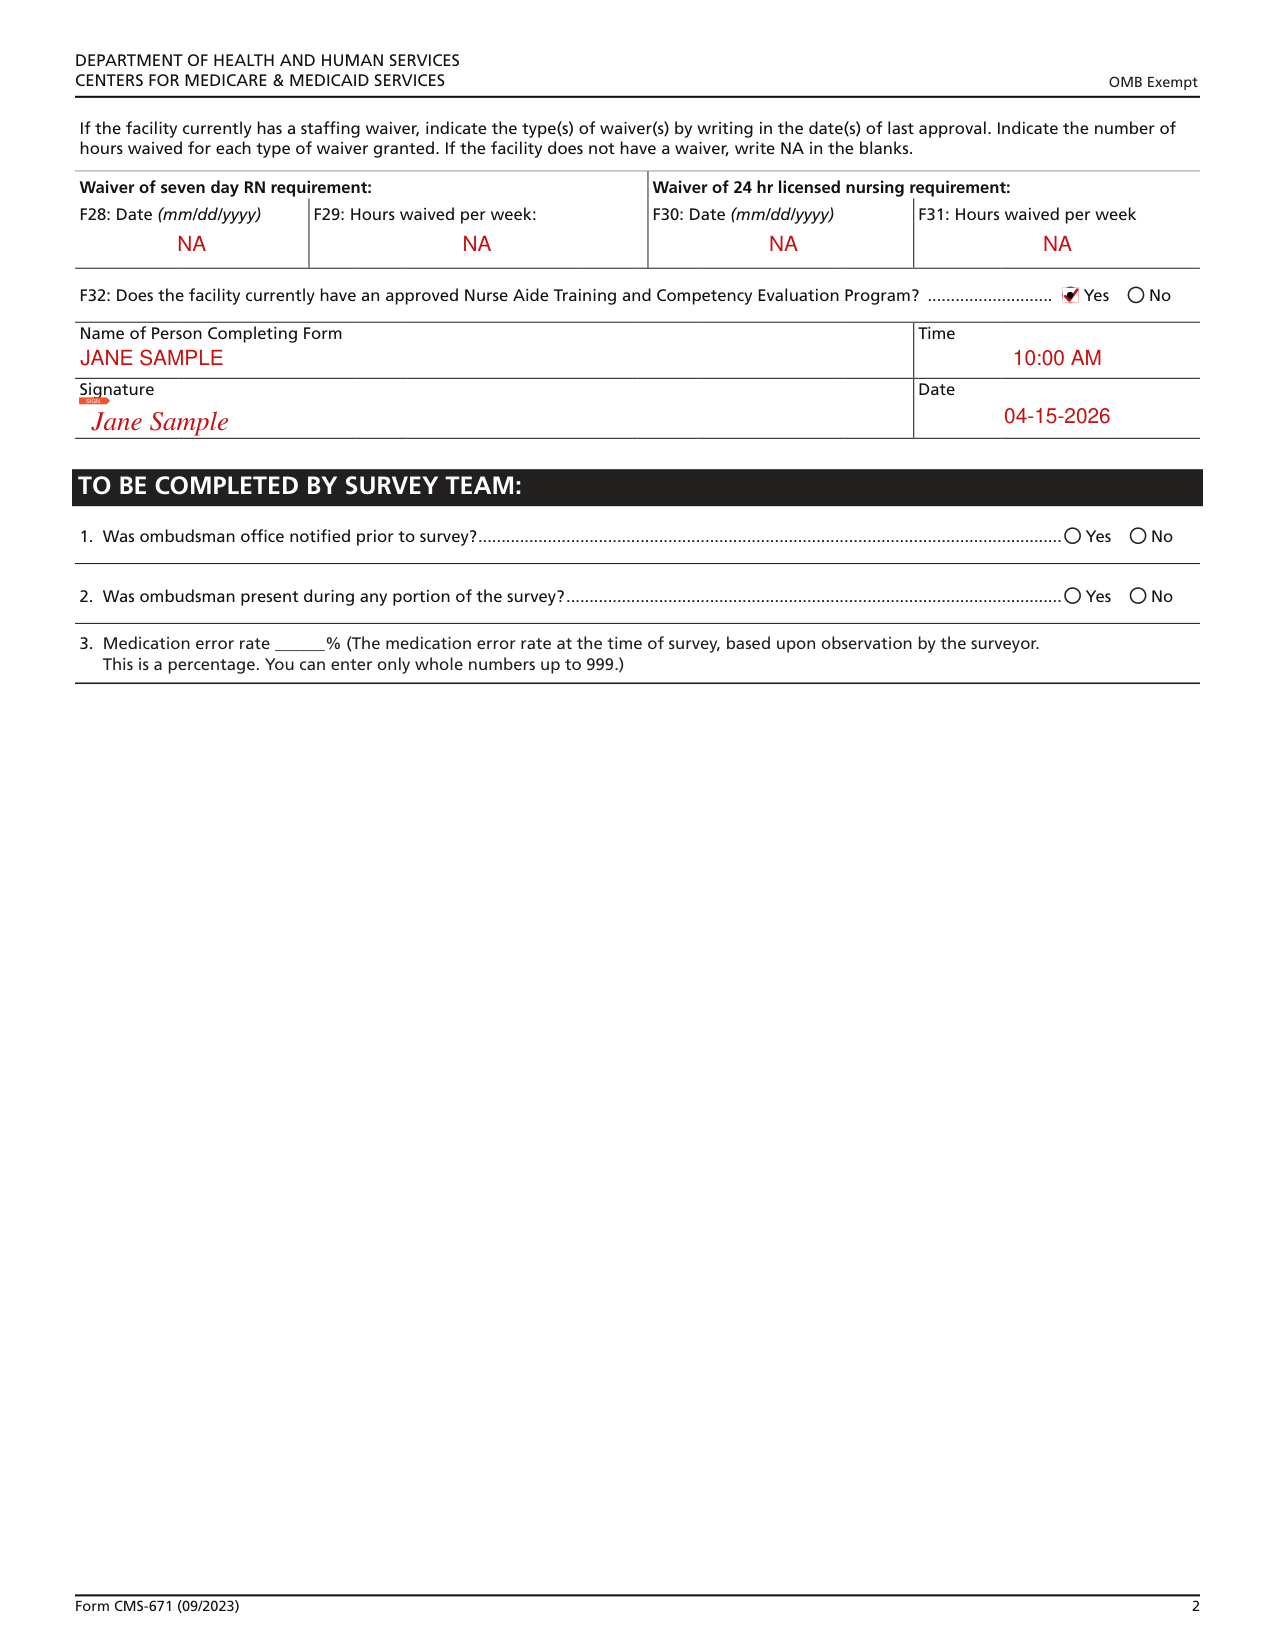
Who signs: SIGN: Sign in Signature and enter the Date.
This form is to be completed by the Facility. For the purpose of this form, “the facility” equals certified beds (i.e., Medicare and/or Medicaid certified beds).
A filled-in Form CMS-671 example: a nursing home's initial application
How to fill out Form CMS-671, box by box
Facility name, provider number and address
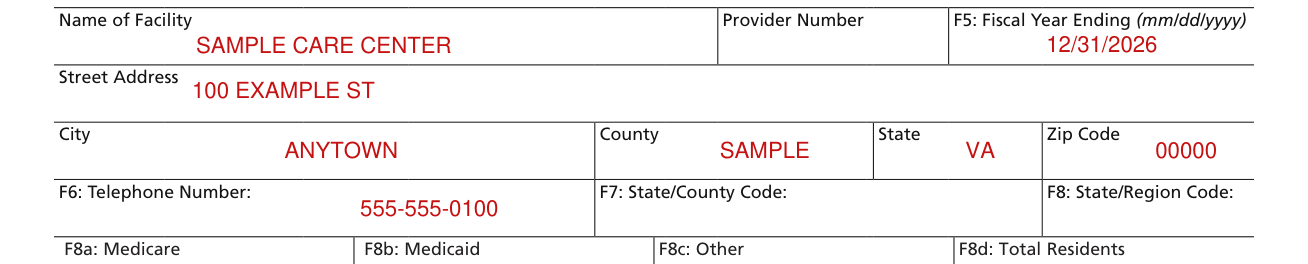
Name of Facility (Form CMS-671 (09/2023), page 3): Use the official name of the facility for business and mailing purposes. This includes components or units of a larger institution.
Provider Number: Leave blank on initial certifications. On all recertifications, insert the facility's assigned six-digit provider code.
F5: Fiscal Year Ending (mm/dd/yyyy).
Common mistake: Street Address: Street name and number refers to physical location, not mailing address, if two addresses differ.
City: Rural addresses should include the city of the nearest post office. County: County refers to parish name in Louisiana and township name where appropriate in the New England States. State: For U.S. possessions and trust territories, name is included in lieu of the State.
Zip Code: Zip Code refers to the “Zip-plus-four” code, if available, otherwise the standard Zip Code. Telephone Number: Include the area code.
State/County Code: LEAVE BLANK. State Survey Office will complete. State/Region Code: LEAVE BLANK. State Survey Office will complete.
Residents by payer

Block F8a: Residents whose stay is covered by their Medicare Part A Skilled Nursing Facility (SNF) benefit (primary payer is Original Medicare or a Medicare Advantage (Part C) plan). Block F8b: Residents whose stay is covered by a state's Nursing Facility (NF) benefit (primary payer is Medicaid or Medicaid Managed Care). Block F8c: Residents for whom a bed is maintained on the day the survey begins, including those temporarily away in a hospital or on leave. This should be representative of residents in the nursing facility or those who have a bed-hold.
Participation and hospital

Block F9: Enter either 01 (SNF), 02 (NF), or 03 (SNF/NF).
Block F10: If the facility is under administrative control of a hospital, check “yes,” otherwise check “no.” If yes, indicate Hospital Provider Number: F11. Block F11: The hospital provider number is the hospital's assigned six-digit Medicare provider number.
Ownership
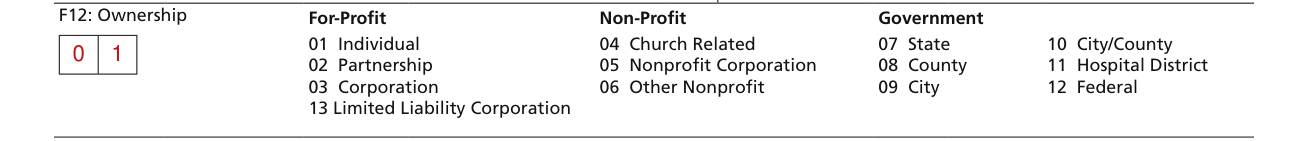
Block F12: Identify the type of organization that controls and operates the facility. Enter the code as identified for that organization (e.g., for a for profit facility owned by an individual, enter 01 in the F12 block; a facility owned by a city government would be entered as 09 in the F12 block).
For-Profit: If operated under commercial ownership, indicate whether owned by individual, partnership, corporation, or limited liability corporation (LLC). Non-Profit: If operated under voluntary or other nonprofit auspices, indicate whether church related, nonprofit corporation or other nonprofit. Government: If operated by a governmental entity, indicate whether State, City, Hospital District, County, City/County, or Federal Government.
F12: Ownership For-Profit: 01 Individual, 02 Partnership, 03 Corporation, 13 Limited Liability Corporation. Non-Profit: 04 Church Related, 05 Nonprofit Corporation, 06 Other Nonprofit. Government: 07 State, 08 County, 09 City, 10 City/County, 11 Hospital District, 12 Federal.
Multi-facility organization
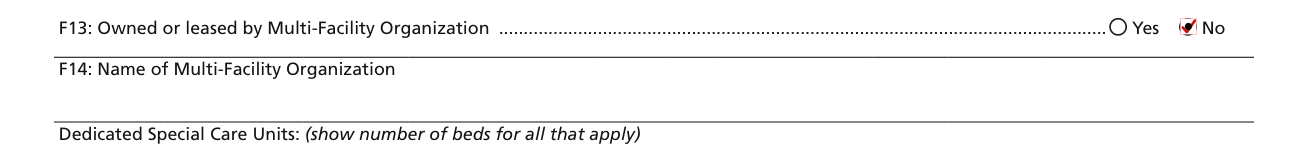
Block F13: Check “yes” if the facility is owned or leased by a multi-facility organization, otherwise check “no.” A Multi-Facility Organization is an organization that owns two or more long term care facilities. The owner may be an individual or a corporation. Leasing of facilities by corporate chains is included in this definition.
Block F14: If applicable, enter the name of the multi-facility organization. Use the name of the corporate ownership of the multi-facility organization (e.g., if the name of the facility is Soft Breezes Home and the name of the multi-facility organization that owns Soft Breezes is XYZ Enterprises, enter XYZ Enterprises).
Dedicated Special Care Units

Block F15 - F23: Enter the number of beds in the facility's Dedicated Special Care Units. These are units with a specific number of beds, identified and dedicated by the facility for residents with specific needs/diagnoses. They need not be certified or recognized by regulatory authorities.
For example, a SNF admits a large number of residents with head injuries. They have set aside 8 beds on the north wing, staffed with specifically trained personnel. Show “8” in F19.
Resident groups, research and retirement community

Block F24: Check “yes” if the facility currently has an organized residents' group, i.e., a group(s) that meets regularly to discuss and offer suggestions about facility policies and procedures affecting residents' care, treatment, and quality of life; to support each other; to plan resident and family activities; to participate in educational activities or for any other purposes; otherwise check “no.”
Block F25 (Form CMS-671 (09/2023), page 4): Check “yes” if the facility currently has an organized group of family members of residents, i.e., a group(s) that meets regularly to discuss and offer suggestions about facility policies and procedures affecting residents' care, treatment, and quality of life; to support each other, to plan resident and family activities; to participate in educational activities or for any other purpose; otherwise check “no.”
Block F26: Check “yes” if the facility conducts experimental research; otherwise check “no.” Experimental research means using residents to develop and test clinical treatments, such as a new drug or therapy, that involves treatment and control groups. For example, a clinical trial of a new drug would be experimental research.
Block F27: Check “yes” if the facility is part of a continuing care retirement community (CCRC); otherwise check “no.” A CCRC is any facility which operates under State regulation as a continuing care retirement community.
Nurse staffing waivers and Nurse Aide program
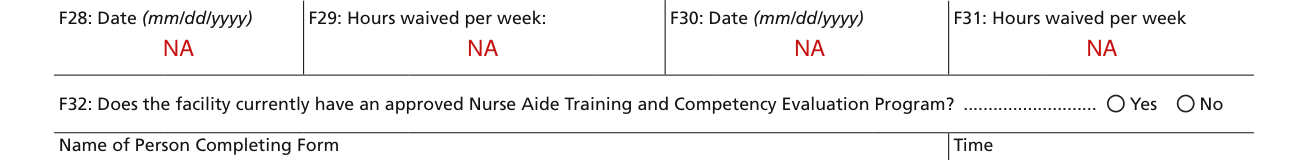
If the facility currently has a staffing waiver, indicate the type(s) of waiver(s) by writing in the date(s) of last approval. Indicate the number of hours waived for each type of waiver granted. If the facility does not have a waiver, write NA in the blanks. Blocks F28 - F31: If the facility has been granted a nurse staffing waiver by CMS or the State Agency in accordance with the provisions at 42CFR 483.35(e) or (f), enter the last approval date of the waiver(s) and report the number of hours being waived for each type of waiver approval.
Waiver of seven day RN requirement: F28: Date (mm/dd/yyyy) F29: Hours waived per week. Waiver of 24 hr licensed nursing requirement: F30: Date (mm/dd/yyyy) F31: Hours waived per week.
Block F32: Check “yes” if the facility has a State approved Nurse Aide Training and Competency Evaluation Program; otherwise check “no.”
Completing and signing

Name of Person Completing Form, Time.
SIGN: Sign in Signature and enter the Date.
More rules for Form CMS-671
TO BE COMPLETED BY SURVEY TEAM: 1. Was ombudsman office notified prior to survey? Yes No 2. Was ombudsman present during any portion of the survey? Yes No
3. Medication error rate ______% (The medication error rate at the time of survey, based upon observation by the surveyor. This is a percentage. You can enter only whole numbers up to 999.)
Common questions about Form CMS-671
What is a CMS 671?
Form CMS-671 (09/2023) is the Long-Term Care Facility Application for Medicare and Medicaid. Survey team will complete: Standard Survey: From F1 (mm/dd/yyyy) To F2 (mm/dd/yyyy); Extended Survey: From F3 (mm/dd/yyyy) To F4 (mm/dd/yyyy).
Sources
[1] Form CMS-671 (09/2023), Long-Term Care Facility Application for Medicare and Medicaid, Centers for Medicare & Medicaid Services (the Official source link on this page).
