
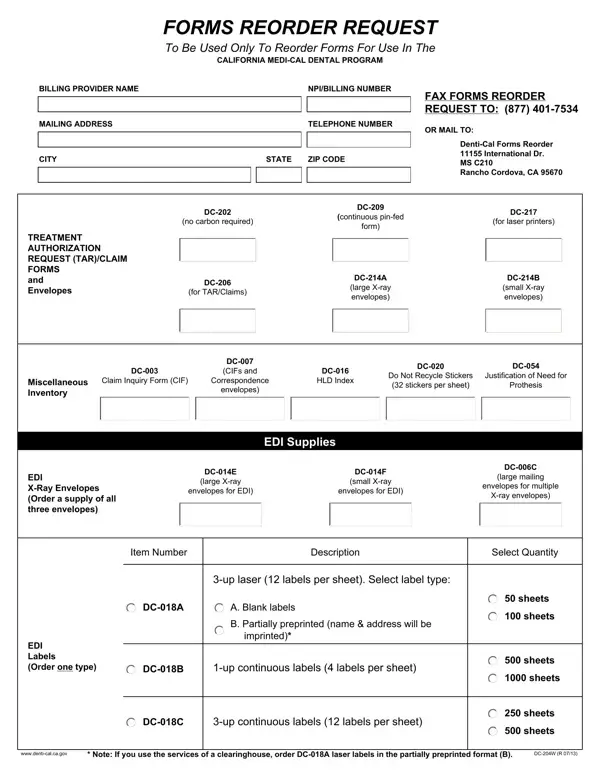
Form DC-204W at a glance
What it is: DC-204W is the Forms Reorder Request For Use with the California Medi-Cal Dental Program.
Where and when to file: Fax this reorder request to (877) 401-7534. Or email to formreorderrequest@gainwelltechnologies.com. Or mail to Medi-Cal Dental Forms P.O. Box 15609 Sacramento, CA 95852-0609.
The blank Form DC-204W: print it and complete it by hand
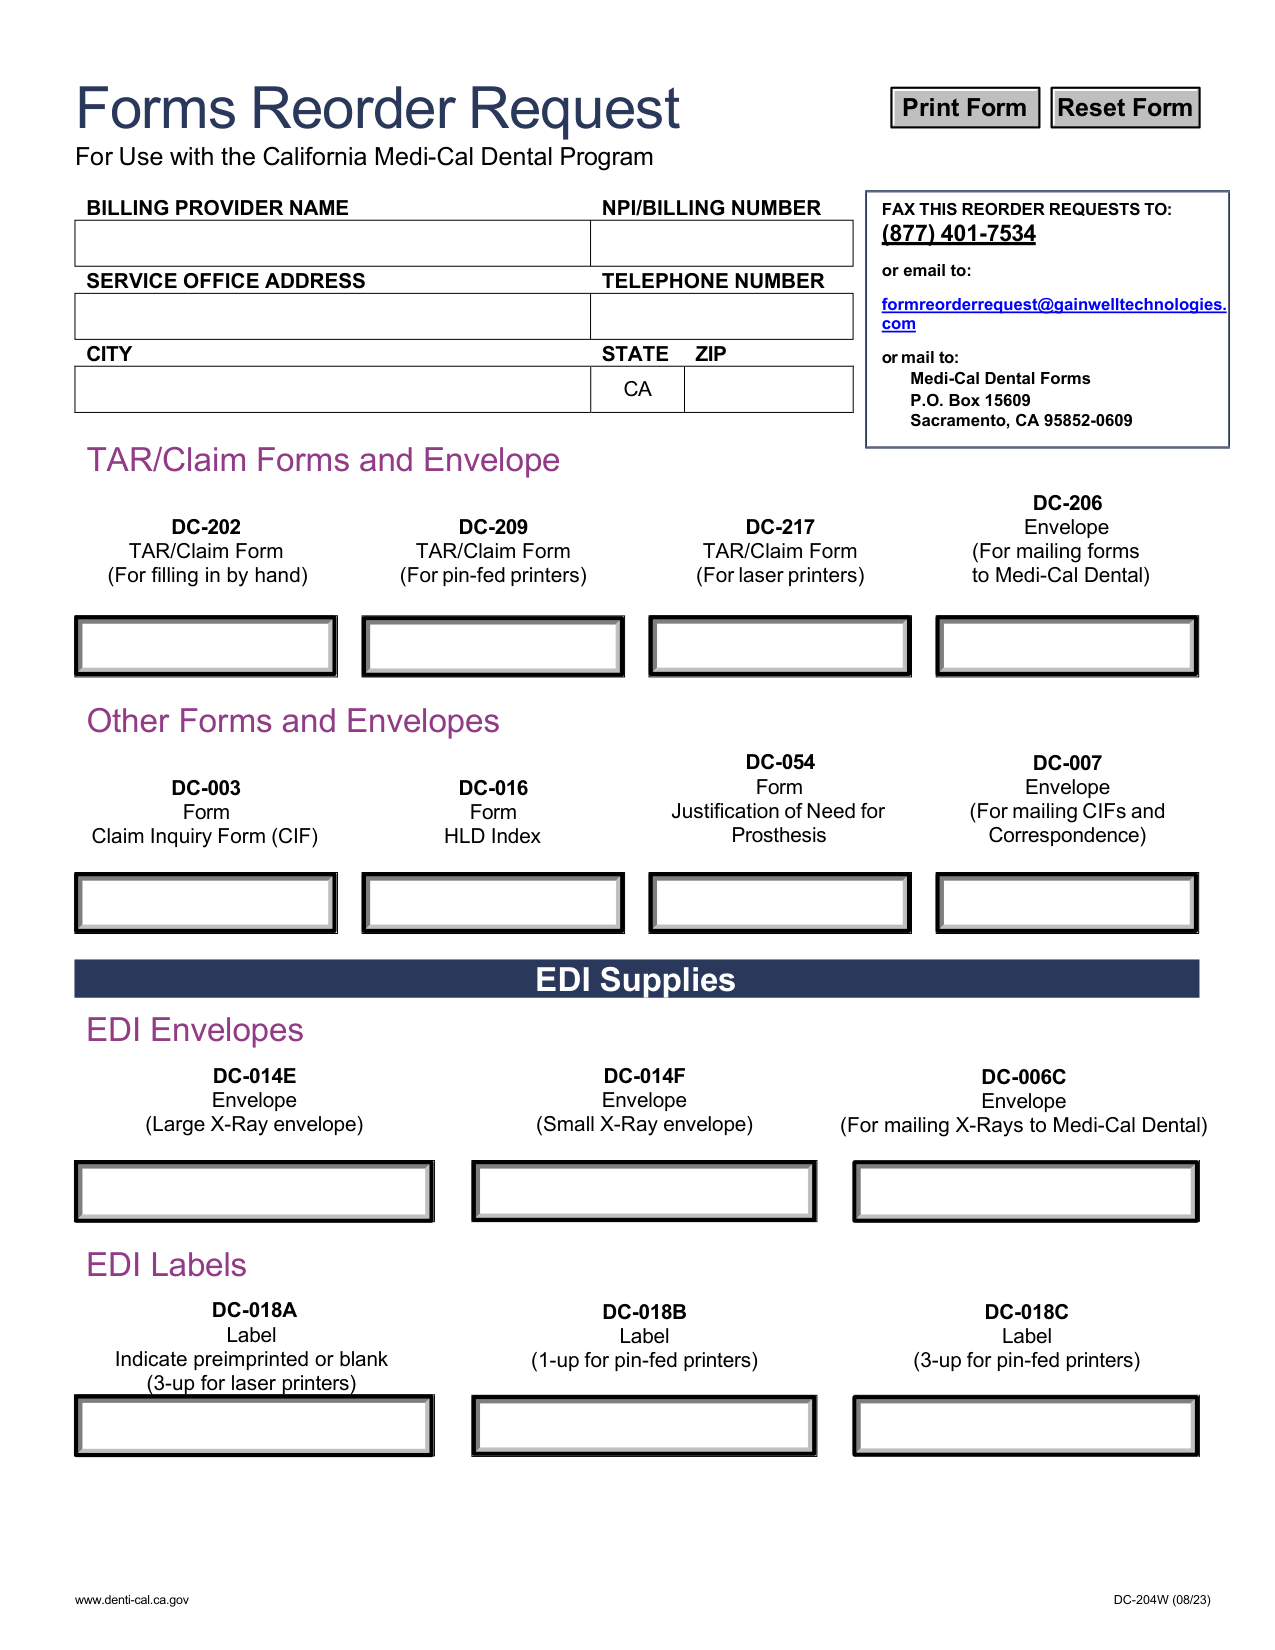
How to fill out Form DC-204W, box by box
More rules for Form DC-204W
Fill in the Billing Provider Name, NPI/Billing Number, Service Office Address, Telephone Number and City State Zip.
Under TAR/Claim Forms and Envelope, DC-206 Envelope is for mailing forms to Medi-Cal Dental.
DC-202 TAR/Claim Form is for filling in by hand; DC-209 TAR/Claim Form is for pin-fed printers.
DC-217 TAR/Claim Form is for laser printers.
Under Other Forms and Envelopes, DC-007 Envelope is for mailing CIFs and Correspondence.
DC-014E Envelope is the Large X-Ray envelope, DC-014F Envelope is the Small X-Ray envelope and DC-006C Envelope is for mailing X-Rays to Medi-Cal Dental.
For a Label, indicate preimprinted or blank.
The labels are Label (1-up for pin-fed printers), Label (3-up for pin-fed printers) and Label (3-up for laser printers).
Common questions about Form DC-204W
Where do I file it?
Fax this reorder request to (877) 401-7534, or email it to formreorderrequest@gainwelltechnologies.com, or mail it to Medi-Cal Dental Forms P.O. Box 15609 Sacramento, CA 95852-0609.
Sources
[1] Form DC-204W (08/23), Forms Reorder Request, California Medi-Cal Dental Program (the Official source link on this page).