

Form DD 2813 at a glance
What it is: This is the Department of Defense Active Duty/Reserve/Guard/Civilian Forces Dental Examination.
Who signs: Enter the dentist's signature in Box 9, the dentist's license number in Box 9 and the date of examination (YYYYMMDD) in Box 10.
A filled-in Form DD 2813 example: a dentist marks Block (3) for one tooth
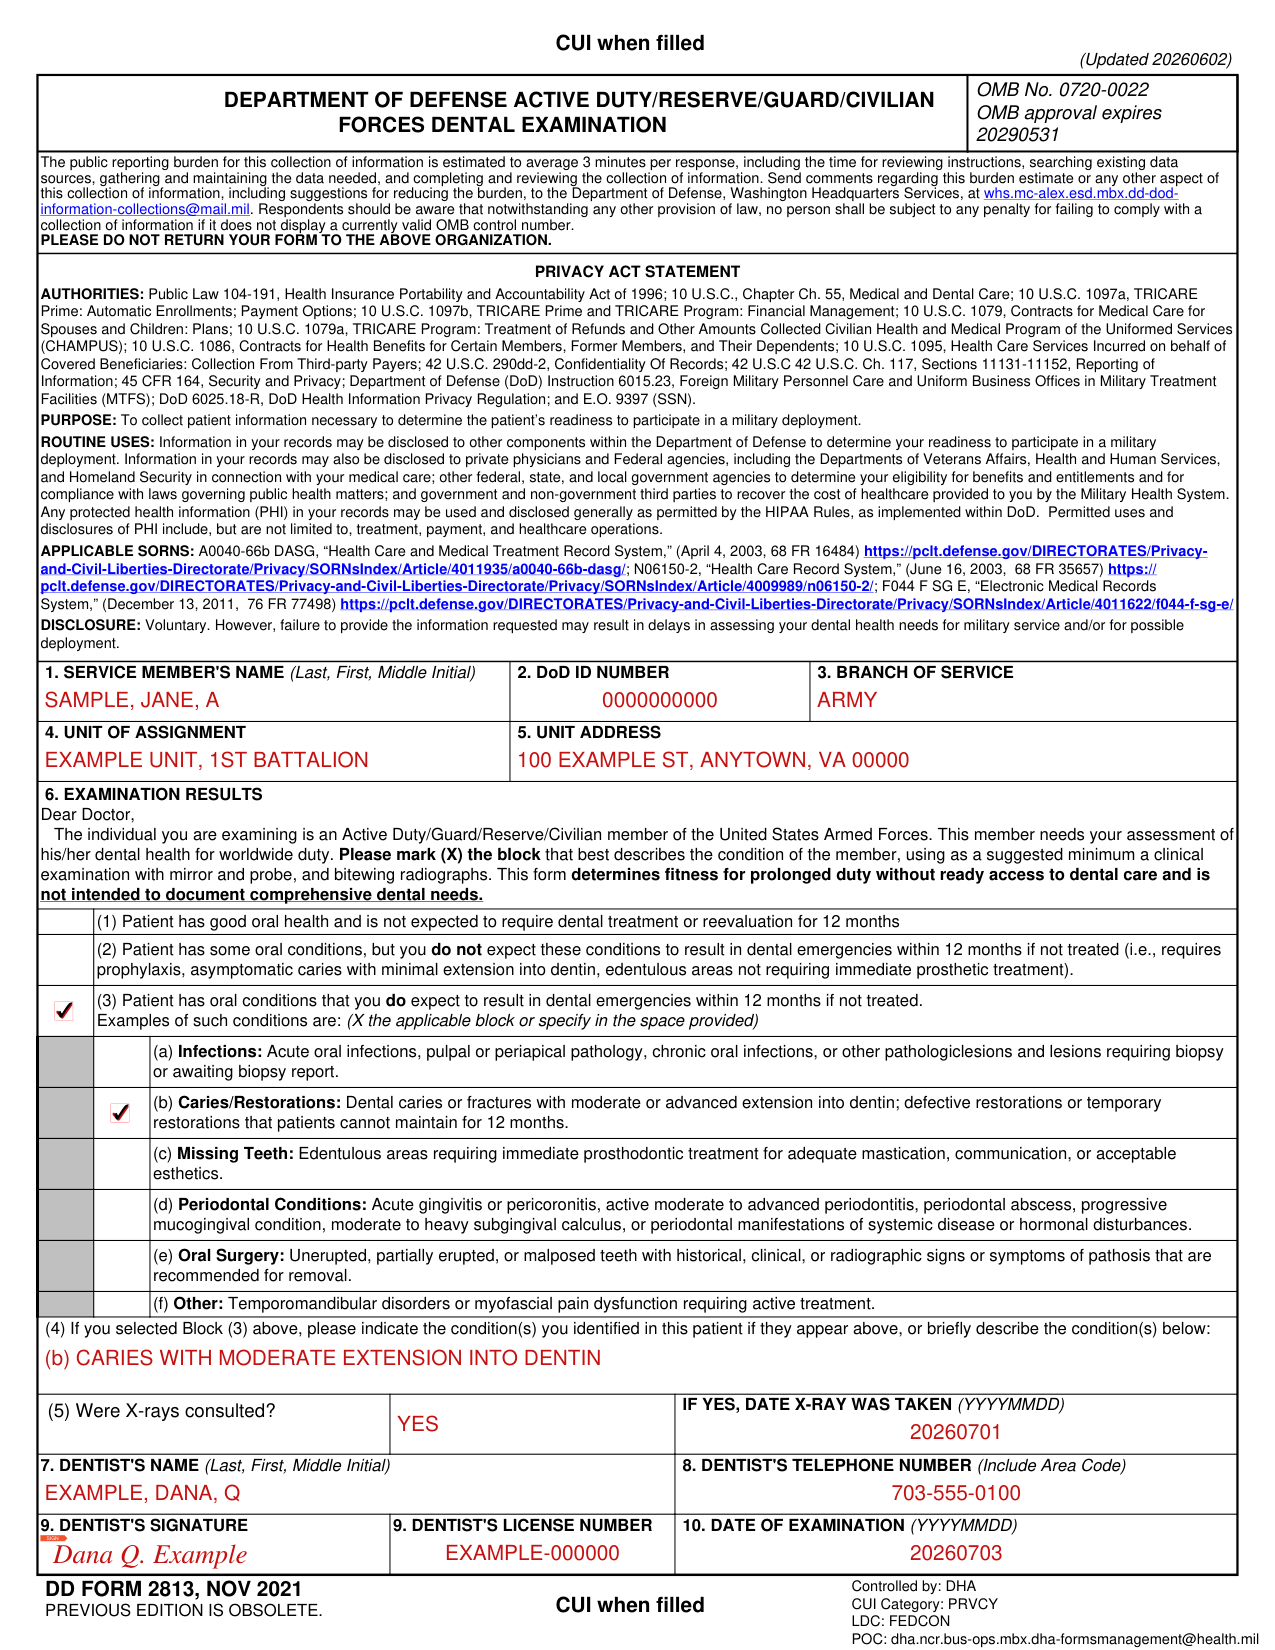
How to fill out Form DD 2813, box by box
Before Box 1: the OMB control number and the time to complete
No person shall be subject to any penalty for failing to comply with a collection of information if it does not display a currently valid OMB control number. The public reporting burden for this collection of information is estimated to average 3 minutes per response.
Boxes 1 to 5: the service member and the unit

Enter the service member's name in Box 1 (Last, First, Middle Initial), the DoD ID number in Box 2 and the branch of service in Box 3.
Enter the unit of assignment in Box 4 and the unit address in Box 5.
Box 6: the dental condition of the patient

(1) Patient has good oral health and is not expected to require dental treatment or reevaluation for 12 months.
(2) Patient has some oral conditions, but you do not expect these conditions to result in dental emergencies within 12 months if not treated (i.e., requires prophylaxis, asymptomatic caries with minimal extension into dentin, edentulous areas not requiring immediate prosthetic treatment).
(3) Patient has oral conditions that you do expect to result in dental emergencies within 12 months if not treated; X the applicable block or specify in the space provided.
(a) Infections: Acute oral infections, pulpal or periapical pathology, chronic oral infections, or other pathologiclesions and lesions requiring biopsy or awaiting biopsy report.
(b) Caries/Restorations: Dental caries or fractures with moderate or advanced extension into dentin; defective restorations or temporary restorations that patients cannot maintain for 12 months.
(c) Missing Teeth: Edentulous areas requiring immediate prosthodontic treatment for adequate mastication, communication, or acceptable esthetics.
(d) Periodontal Conditions: Acute gingivitis or pericoronitis, active moderate to advanced periodontitis, periodontal abscess, progressive mucogingival condition, moderate to heavy subgingival calculus, or periodontal manifestations of systemic disease or hormonal disturbances.
(e) Oral Surgery: Unerupted, partially erupted, or malposed teeth with historical, clinical, or radiographic signs or symptoms of pathosis that are recommended for removal.
(f) Other: Temporomandibular disorders or myofascial pain dysfunction requiring active treatment.
(4) If you selected Block (3), please indicate the condition(s) you identified in this patient if they appear in the list of conditions (a) to (f), or briefly describe the condition(s).
Box 6 (5): were X-rays consulted

(5) Were X-rays consulted? If yes, enter the date the X-ray was taken (YYYYMMDD).
Boxes 7 and 8: the dentist's name and telephone
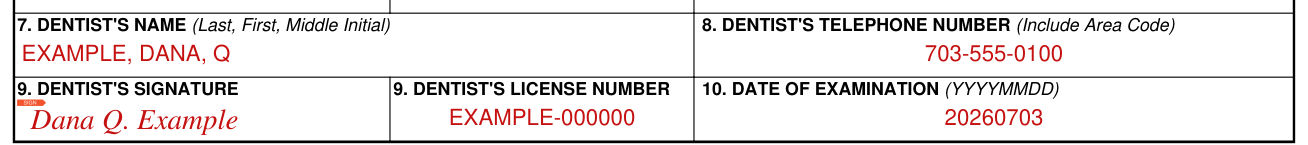
Enter the dentist's name in Box 7 (Last, First, Middle Initial) and the dentist's telephone number in Box 8, including the area code.
More rules for Form DD 2813
Previous edition is obsolete.
Common questions about Form DD 2813
What is DD 2813?
This is the Department of Defense Active Duty/Reserve/Guard/Civilian Forces Dental Examination. The individual you are examining is an Active Duty/Guard/Reserve/Civilian member of the United States Armed Forces. This member needs your assessment of his/her dental health for worldwide duty. Please mark (X) the block that best describes the condition of the member, using as a suggested minimum a clinical examination with mirror and probe, and bitewing radiographs. This form determines fitness for prolonged duty without ready access to dental care and is not intended to document comprehensive dental needs.
Sources
[1] DD Form 2813 (NOV 2021), Active Duty/Reserve/Guard/Civilian Forces Dental Examination, U.S. Department of Defense (the Official source link on this page).
