

Form FR-309 at a glance
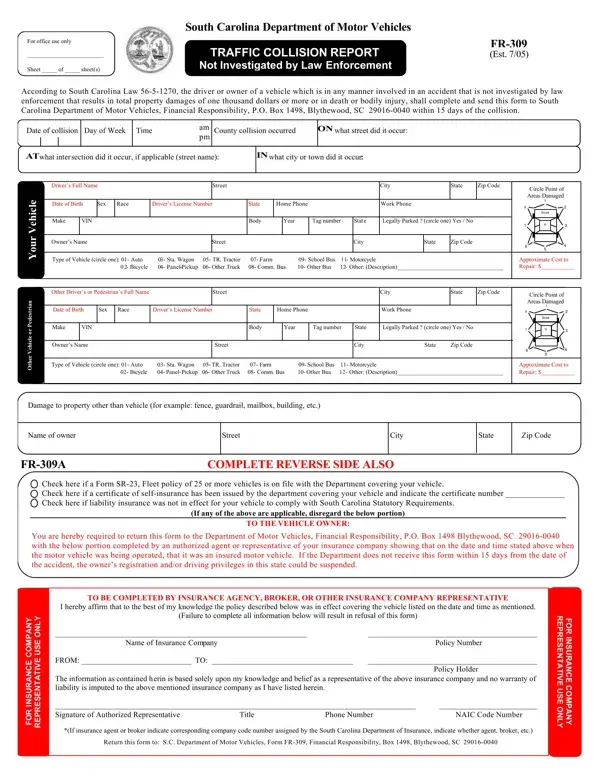
What it is: FR-309 is the South Carolina Department of Motor Vehicles TRAFFIC COLLISION REPORT Not Investigated by Law Enforcement.
Who signs: The person making this report must sign here, with the Signature, Address and Date.
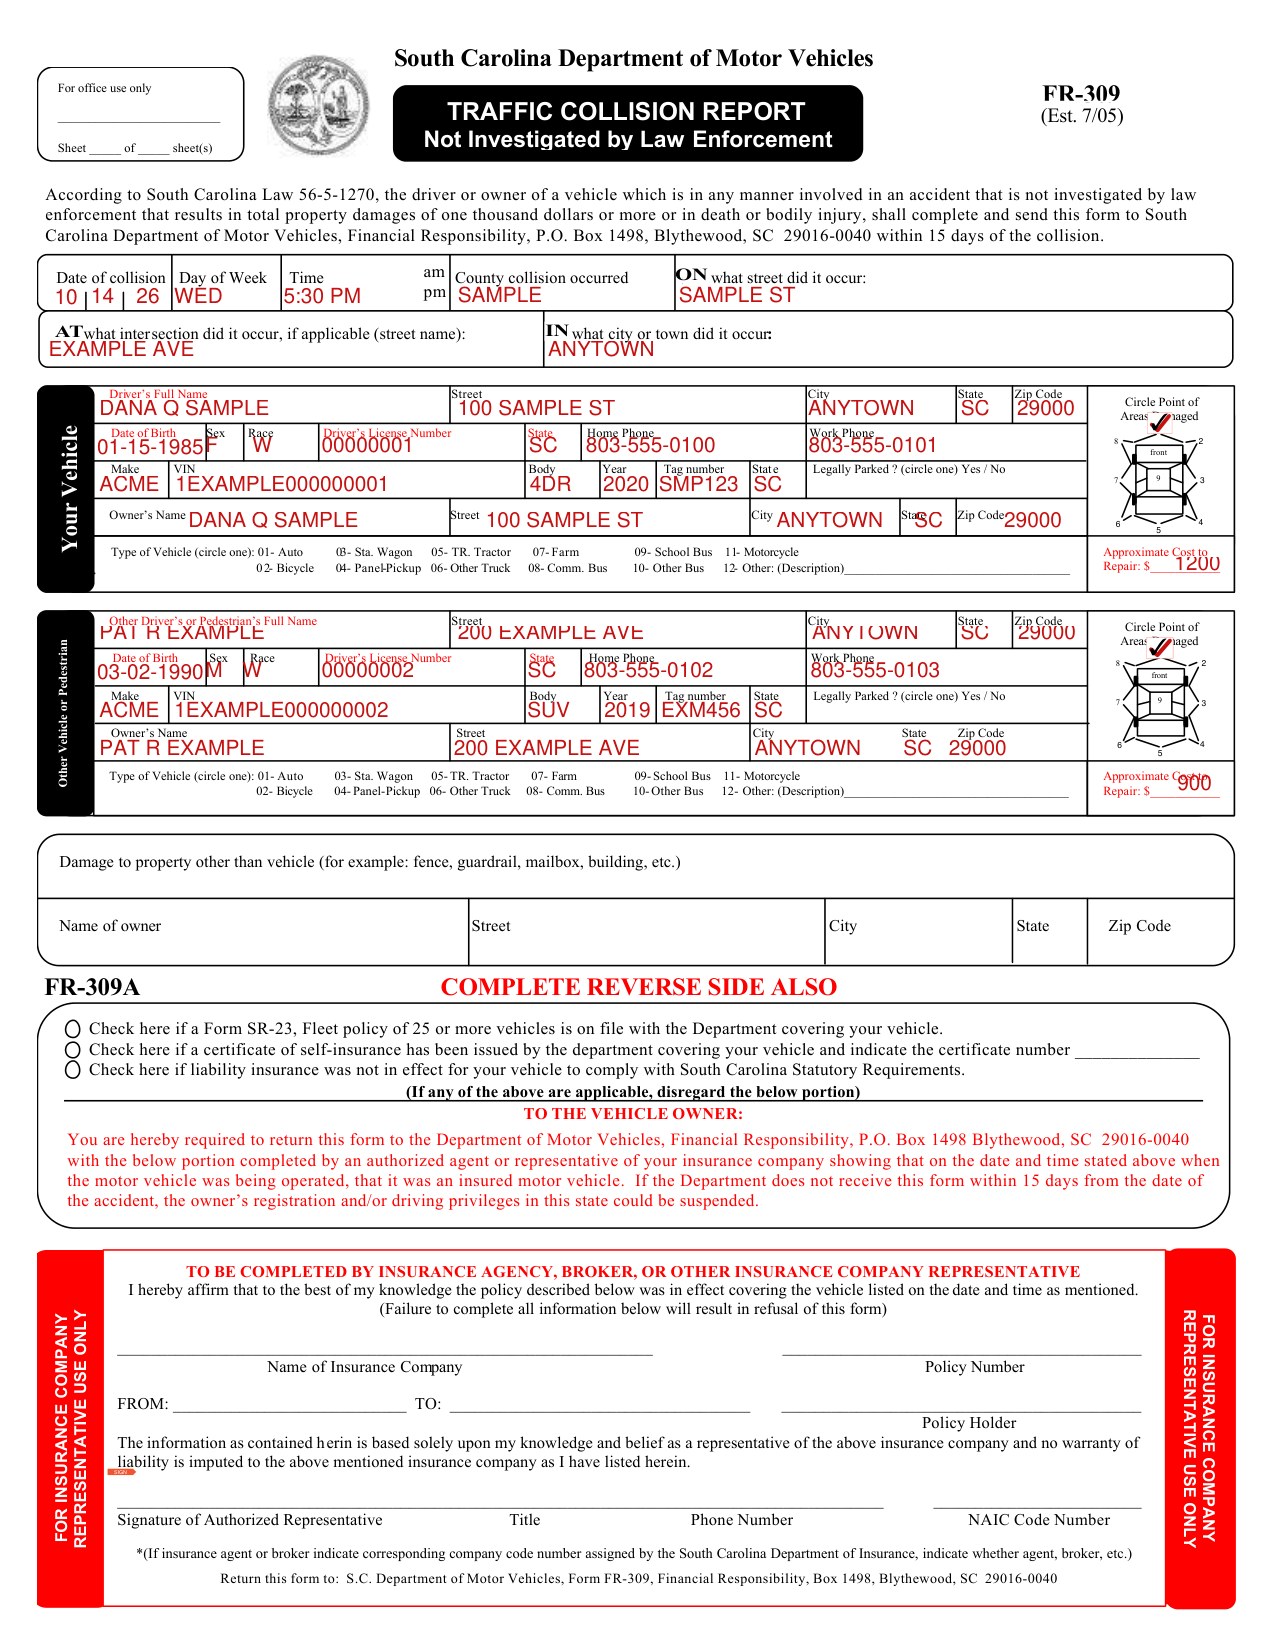
A filled-in Form FR-309 example: a driver reports a crash with another car
How to fill out Form FR-309, box by box
When and where the collision occurred

According to South Carolina Law 56-5-1270, the driver or owner of a vehicle which is in any manner involved in an accident that is not investigated by law enforcement that results in total property damages of one thousand dollars or more or in death or bodily injury, shall complete and send this form to South Carolina Department of Motor Vehicles, Financial Responsibility, P.O. Box 1498, Blythewood, SC 29016-0040 within 15 days of the collision (checked October 31, 2026)
Enter the Date of collision, Day of Week, Time (am or pm), County collision occurred, and ON what street did it occur.
Enter AT what intersection did it occur, if applicable (street name), and IN what city or town did it occur.
Your Vehicle and the Other Vehicle or Pedestrian: the drivers
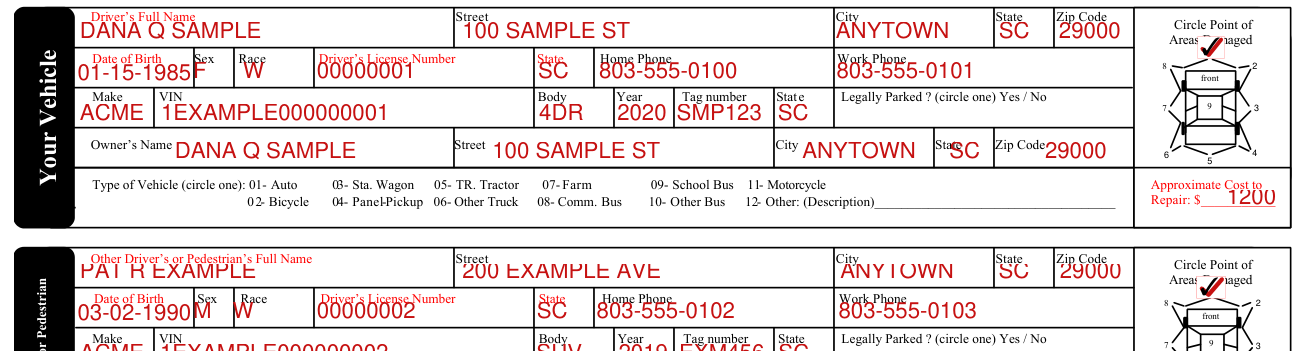
Enter the Driver's Full Name (for the other vehicle, the Other Driver's or Pedestrian's Full Name), Street, City, State and Zip Code, For Your Vehicle and for the Other Vehicle or Pedestrian.
Enter the Date of Birth, Sex, Race, Driver's License Number, State, Home Phone and Work Phone, For Your Vehicle and for the Other Vehicle or Pedestrian.
Your Vehicle and the Other Vehicle or Pedestrian: the vehicles and their owners
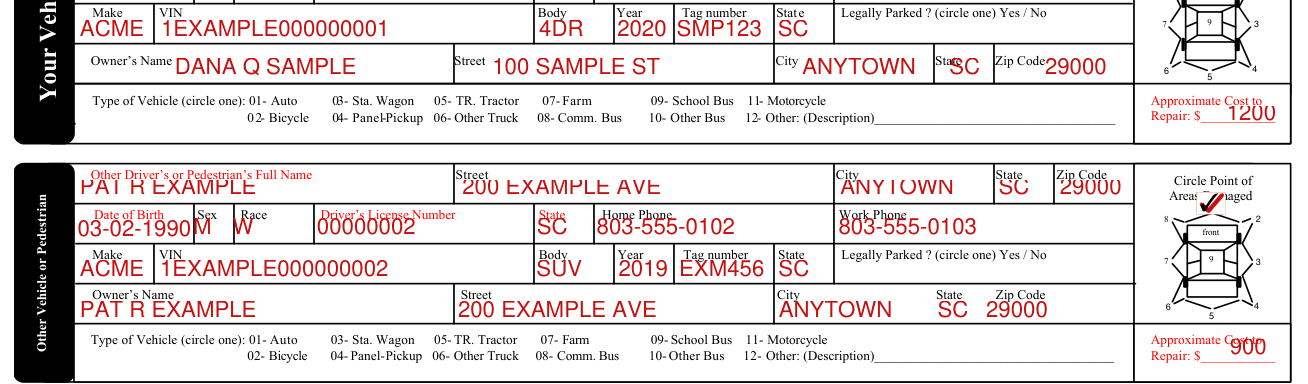
Enter the Make, VIN, Body, Year, Tag number and State, and circle Yes or No for Legally Parked, For Your Vehicle and for the Other Vehicle or Pedestrian.
Enter the Owner's Name, Street, City, State and Zip Code, For Your Vehicle and for the Other Vehicle or Pedestrian.
Circle one Type of Vehicle: 01- Auto, 02- Bicycle, 03- Sta. Wagon, 04- Panel-Pickup, 05- TR. Tractor, 06- Other Truck, 07- Farm, 08- Comm. Bus, 09- School Bus, 10- Other Bus, 11- Motorcycle or 12- Other: (Description), For Your Vehicle and for the Other Vehicle or Pedestrian.
Circle Point of Areas Damaged
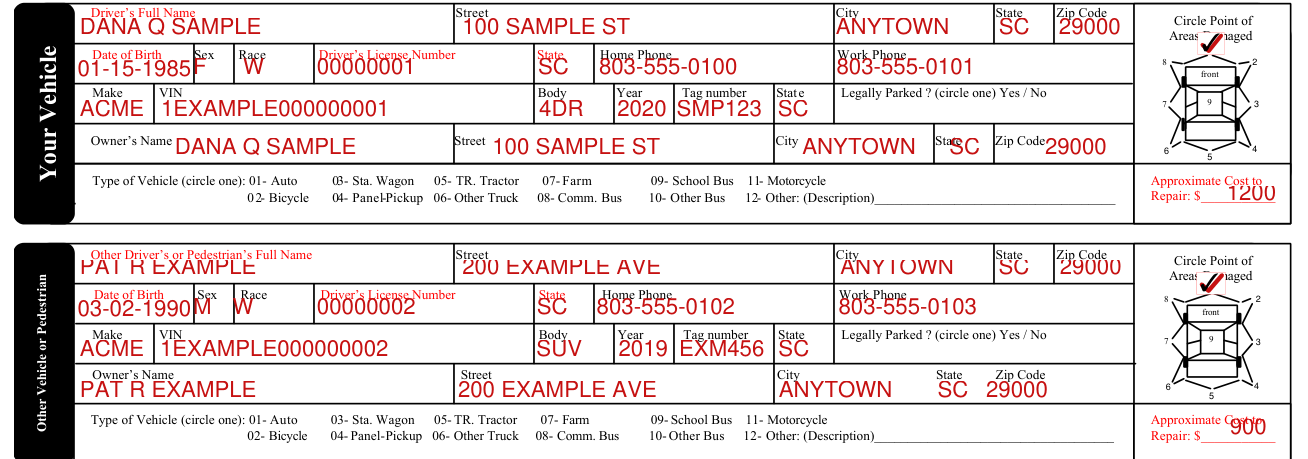
Mark the Circle Point of Areas Damaged and enter the Approximate Cost to Repair, For Your Vehicle and for the Other Vehicle or Pedestrian.
Damage to property other than vehicle

For Damage to property other than vehicle (for example: fence, guardrail, mailbox, building, etc.), enter the Name of owner, Street, City, State and Zip Code.
Insurance on your vehicle

Check here if a Form SR-23, Fleet policy of 25 or more vehicles is on file with the Department covering your vehicle. Check here if a certificate of self-insurance has been issued by the department covering your vehicle and indicate the certificate number. Check here if liability insurance was not in effect for your vehicle to comply with South Carolina Statutory Requirements.
If any of the Check here if boxes are applicable, disregard TO BE COMPLETED BY INSURANCE AGENCY, BROKER, OR OTHER INSURANCE COMPANY REPRESENTATIVE.
To be completed by the insurance representative

You are hereby required to return this form to the Department of Motor Vehicles, Financial Responsibility, P.O. Box 1498 Blythewood, SC 29016-0040 with the below portion completed by an authorized agent or representative of your insurance company showing that on the date and time stated above when the motor vehicle was being operated, that it was an insured motor vehicle. If the Department does not receive this form within 15 days from the date of the accident, the owner's registration and/or driving privileges in this state could be suspended.
An insurance agency, broker, or other insurance company representative completes TO BE COMPLETED BY INSURANCE AGENCY, BROKER, OR OTHER INSURANCE COMPANY REPRESENTATIVE: Name of Insurance Company, Policy Number, FROM, TO and Policy Holder.
Failure to complete all information in TO BE COMPLETED BY INSURANCE AGENCY, BROKER, OR OTHER INSURANCE COMPANY REPRESENTATIVE will result in refusal of this form.
The representative fills in Signature of Authorized Representative, Title, Phone Number and NAIC Code Number.
Victims and codes
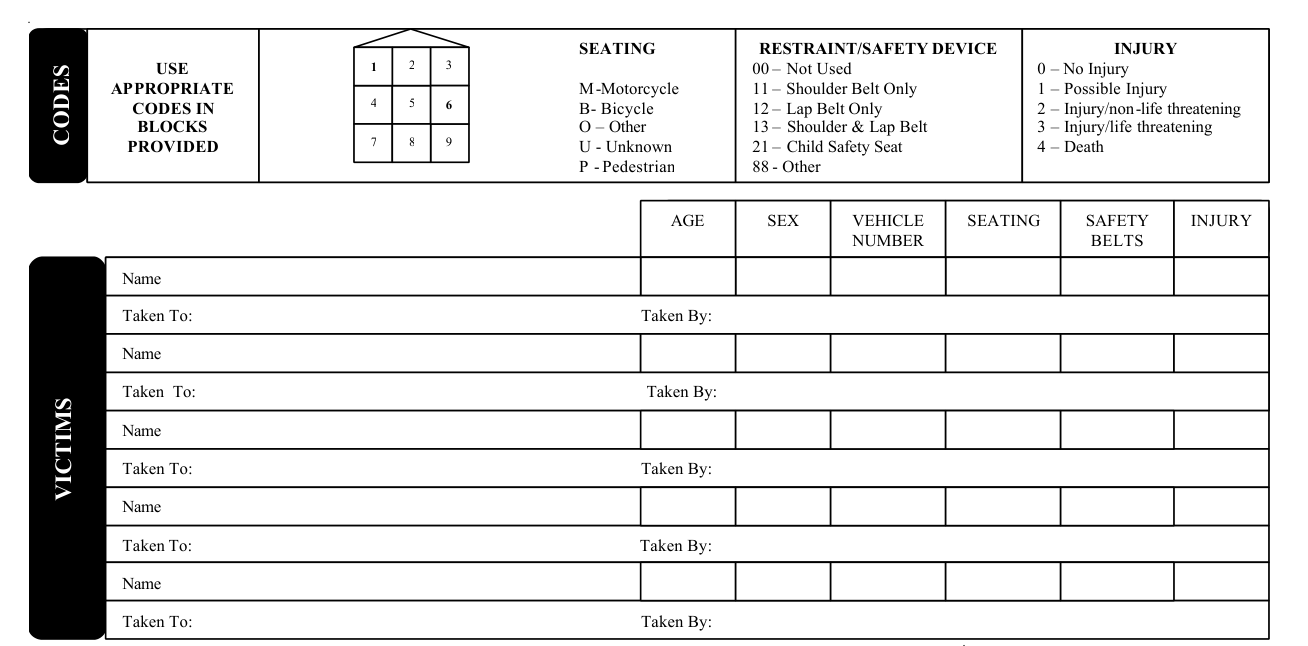
USE APPROPRIATE CODES IN BLOCKS PROVIDED. SEATING codes: M-Motorcycle, B- Bicycle, O - Other, U - Unknown, P - Pedestrian.
RESTRAINT/SAFETY DEVICE codes: 00 - Not Used, 11 - Shoulder Belt Only, 12 - Lap Belt Only, 13 - Shoulder & Lap Belt, 21 - Child Safety Seat, 88 - Other.
INJURY codes: 0 - No Injury, 1 - Possible Injury, 2 - Injury/non-life threatening, 3 - Injury/life threatening, 4 - Death.
Under VICTIMS, enter the Name, Age, Sex, Vehicle Number, Seating, Safety Belts and Injury, and Taken To and Taken By.
Witnesses
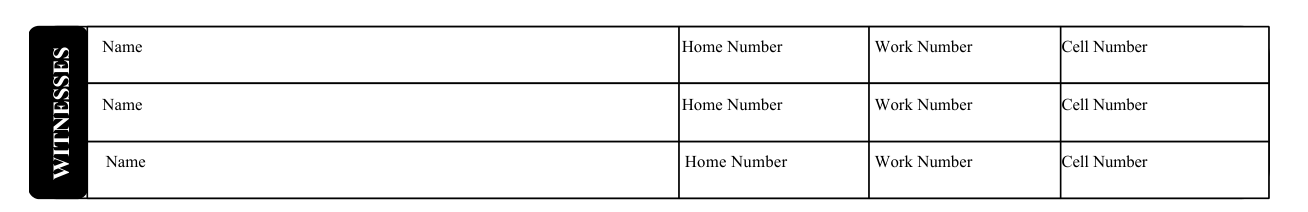
If there are witnesses, enter under WITNESSES the Name, Home Number, Work Number and Cell Number.
Narrative

Under NARRATIVE, describe how the collision happened and include factors that may have contributed to the collision such as road conditions, weather conditions, terrain, etc.
Signing the report

The person making this report must sign here, with the Signature, Address and Date.
More rules for Form FR-309
COMPLETE REVERSE SIDE ALSO.
Sources
[1] Form FR-309 (Est. 7/05), Traffic Collision Report Not Investigated by Law Enforcement, South Carolina Department of Motor Vehicles (the Official source link on this page).