


Form NF-3 at a glance
What it is: NYS Form NF-3 is the New York Motor Vehicle No-Fault Insurance Law Verification of Treatment by Attending Physician or Other Provider of Health Service.
Where and when to file: Submit this completed form to the insurer.
The attending physician or other provider of health service completes and submits this form.
A filled-in Form NF-3 example: a physician verifies treatment

How to fill out Form NF-3, box by box
Where and when to submit the completed form
Submit this completed form to the insurer.
Submit this completed form as soon as reasonably possible but no later than 45 days or 180 days after the treatment date, depending upon the policy endorsement in effect at the time of the accident. If you are unsure of the applicable time requirement, contact the claims representative to determine which deadline is applicable to this claim.
Date, Policyholder, Policy Number, Date of Accident and Claim Number
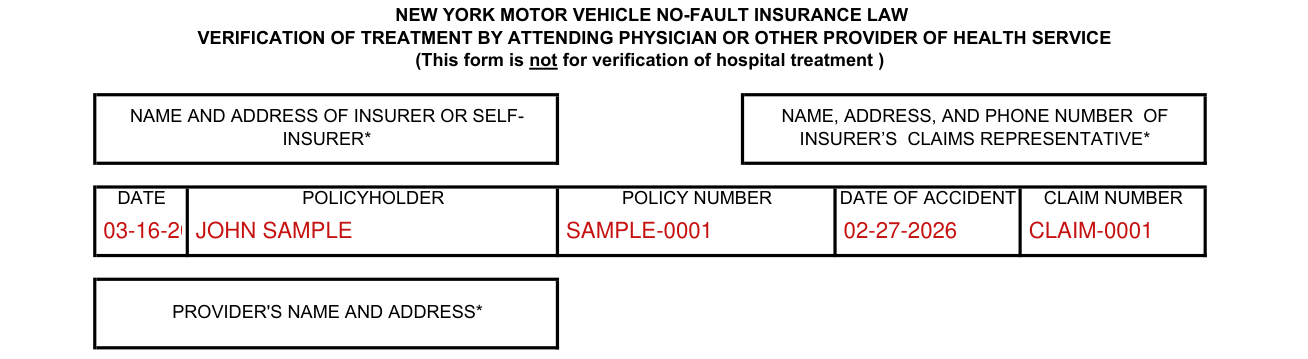
Enter the Date, Policyholder, Policy Number, Date of Accident and Claim Number.
Language marked * is to be filled in by insurer or self-insurer: Name and Address of Insurer or Self-Insurer, Name, Address and Phone Number of Insurer's Claims Representative, and Provider's Name and Address.
Boxes 1 to 4, the patient

Box 1: enter the patient's name and address.
Enter the date of birth in Box 2, the sex in Box 3 and the occupation (if known) in Box 4.
Boxes 5 to 7, the diagnosis and the dates

Box 5: enter the diagnosis and concurrent conditions.
Enter the date symptoms first appeared in Box 6 and the date the patient first consulted you for this condition in Box 7.
Boxes 8 to 11, the condition

Box 8: has the patient ever had the same or similar condition? Mark YES or NO. If YES, state when and describe.
Box 9: is the condition solely a result of this automobile accident? Mark YES or NO. If NO, explain.
Box 10: is the condition due to injury arising out of the patient's employment? Mark YES or NO.
Box 11: will the injury result in significant disfigurement or permanent disability? Mark YES, NO or NOT DETERMINABLE AT THIS TIME. If YES, describe.
Boxes 12 and 13, disabled and return to work

Box 12: enter in FROM and THROUGH the date the patient was disabled (unable to work). Box 13: if still disabled, enter the date the patient should be able to return to work.
Box 14, rehabilitation and occupational therapy
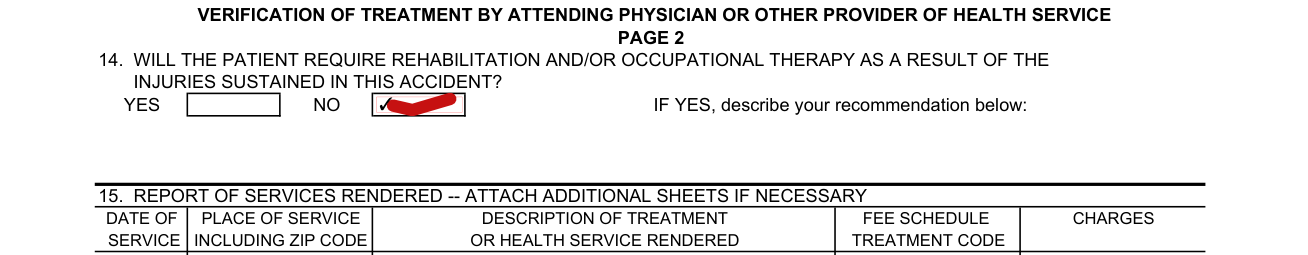
Box 14: will the patient require rehabilitation and/or occupational therapy as a result of the injuries sustained in this accident? Mark YES or NO. If YES, describe your recommendation.
Box 15, report of services rendered

Box 15, report of services rendered: enter the date of service, place of service including zip code, description of treatment or health service rendered, fee schedule treatment code and charges, and attach additional sheets if necessary. Enter the total charges to date.
Boxes 16 and 17, the treating provider and the owners
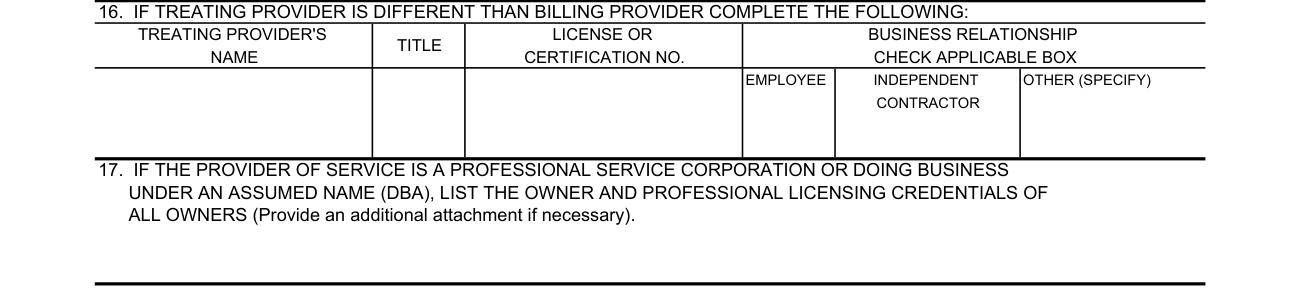
Box 16: if the treating provider is different than the billing provider, complete the following: the treating provider's name, title and license or certification no., and check the applicable box for the business relationship: employee, independent contractor or other (specify).
Box 17: if the provider of service is a professional service corporation or doing business under an assumed name (DBA), list the owner and professional licensing credentials of all owners. Provide an additional attachment if necessary.
Boxes 18 and 19, the care and future treatment

Box 18: is the patient still under your care for this condition? Mark YES or NO.
Box 19: enter the estimated duration of future treatment.
Item 20, authorization to pay benefits

Patient: your health provider may agree to accept payment for health services performed directly from your insurer (Authorization to Pay Benefits) so that you are not required to make payment to the health provider at the time of service. Such agreement is optional on the part of the health provider and must be signed by both patient and health provider.
You may use the optional authorization language by checking off the designated spot in item 20 of this form.
Common mistake: Item 20: if you have chosen to authorize the direct payment of benefits by checking this option, you may not also enter into an assignment of benefits contained in Item 21.
In Item 20, Authorization to Pay Benefits, the patient prints name, signs and dates.
Item 21, assignment of no-fault benefits

Patient: your health provider may agree to have you assign your right to No-Fault benefits from your insurer directly to your health provider (Assignment of Benefits). If you and your health provider agree to an assignment of benefits, you must both sign the agreement contained in # 21 or the prescribed NF-AOB form or its equivalent.
The language contained in the assignment of benefits is mandatory and may not be altered or avoided by any other language added to this agreement or other written agreement.
Common mistake: Item 21: if you have chosen to assign your benefits to the health provider by checking this option, you may not also enter into an authorization to pay benefits contained in Item 20.
In Item 21, Assignment of No-Fault Benefits, the patient (assignor) and the provider of health care service (assignee) each fill in PRINT NAME, SIGNED and DATE.
The original authorization or assignment

Has an original authorization or assignment previously been executed? Mark YES or NO. Is the original signature of the parties on file? Mark YES or NO.
The provider's signature, date, IRS/TIN identification no. and WCB rating code

Enter the date, the provider's signature, the IRS/TIN identification no. and the WCB rating code; if none, enter the specialty.
Common questions about Form NF-3
What is an NF-3 form?
NYS Form NF-3 is the New York Motor Vehicle No-Fault Insurance Law Verification of Treatment by Attending Physician or Other Provider of Health Service. If you have previously submitted an earlier report on this accident, you need only note any changes from the information previously furnished and additional charges.
Is there a penalty?
Any person who knowingly and with intent to defraud any insurance company or other person files an application for commercial insurance or a statement of claim for any commercial or personal insurance benefits containing any materially false information, or conceals for the purpose of misleading, information concerning any fact material thereto, commits a fraudulent insurance act, which is a crime, and shall also be subject to a civil penalty not to exceed five thousand dollars and the value of the subject motor vehicle or stated claim for each violation.
When is this form not the right one?
This form is not for verification of hospital treatment.
Sources
[1] NYS Form NF-3 (Rev 1/2004), Verification of Treatment by Attending Physician or Other Provider of Health Service, New York State Department of Financial Services (the Official source link on this page).