
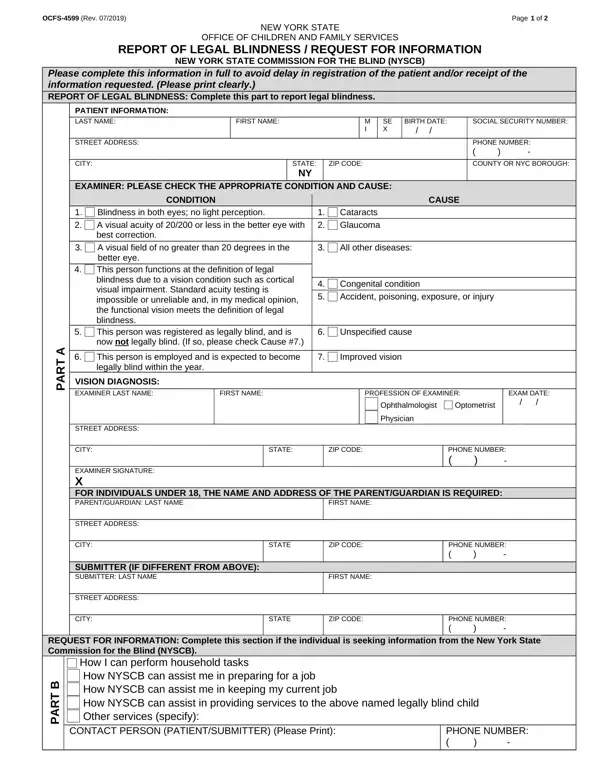
Complete this information in full to avoid delay in registration of the patient and/or receipt of the information requested.
Part A: this section is to be completed for all persons who meet at least one of the conditions (1-6) listed on Page 1.
Part B: in addition to completing Part A, ask your patient if they are experiencing any difficulties performing tasks or activities.
Forwarding: if the patient is experiencing difficulties, assist or have the patient complete Part B and advise them the form will be forwarded to NYSCB.
Where to send: forward the completed form to the NYSCB office listed on the form that serves the county/borough in which this patient resides.
Under 18: for individuals under 18, the name and address of the parent/guardian is required.
| Question | Answer |
|---|---|
| Form Name | Form OCFS-4599 |
| Form Length | 2 pages |
| Fillable? | Yes |
| Fillable fields | 61 |
| Avg. time to fill out | 11 min |
| Edition | Rev 05/2026 |
| Issuing agency | New York State Office of Children and Family Services |
| Other names | OCFS-4599, OCFS 4599, OCFS4599, Report of Legal Blindness, NYSCB legal blindness report, NYSCB request for information |
| Official source | Form OCFS-4599 (Rev 05/2026), New York State Office of Children and Family Services |
Form Ocfs 4599 isn’t the one you’re looking for?