

Form OWCP-5c at a glance
What it is: Form OWCP-5c is the Office of Workers' Compensation Programs Work Capacity Evaluation for Musculoskeletal Conditions.
Who signs: The Physician whose Name is in box 4 signs in box 6 and enters the Date in box 7.
Box 4 is the Physician's Name. Answer the questions concerning your patient. The purpose of this form is to obtain the claimant's specific work tolerance limitation where the accepted condition is musculoskeletal in nature.
A filled-in Form OWCP-5c example: a physician reports a worker's limits
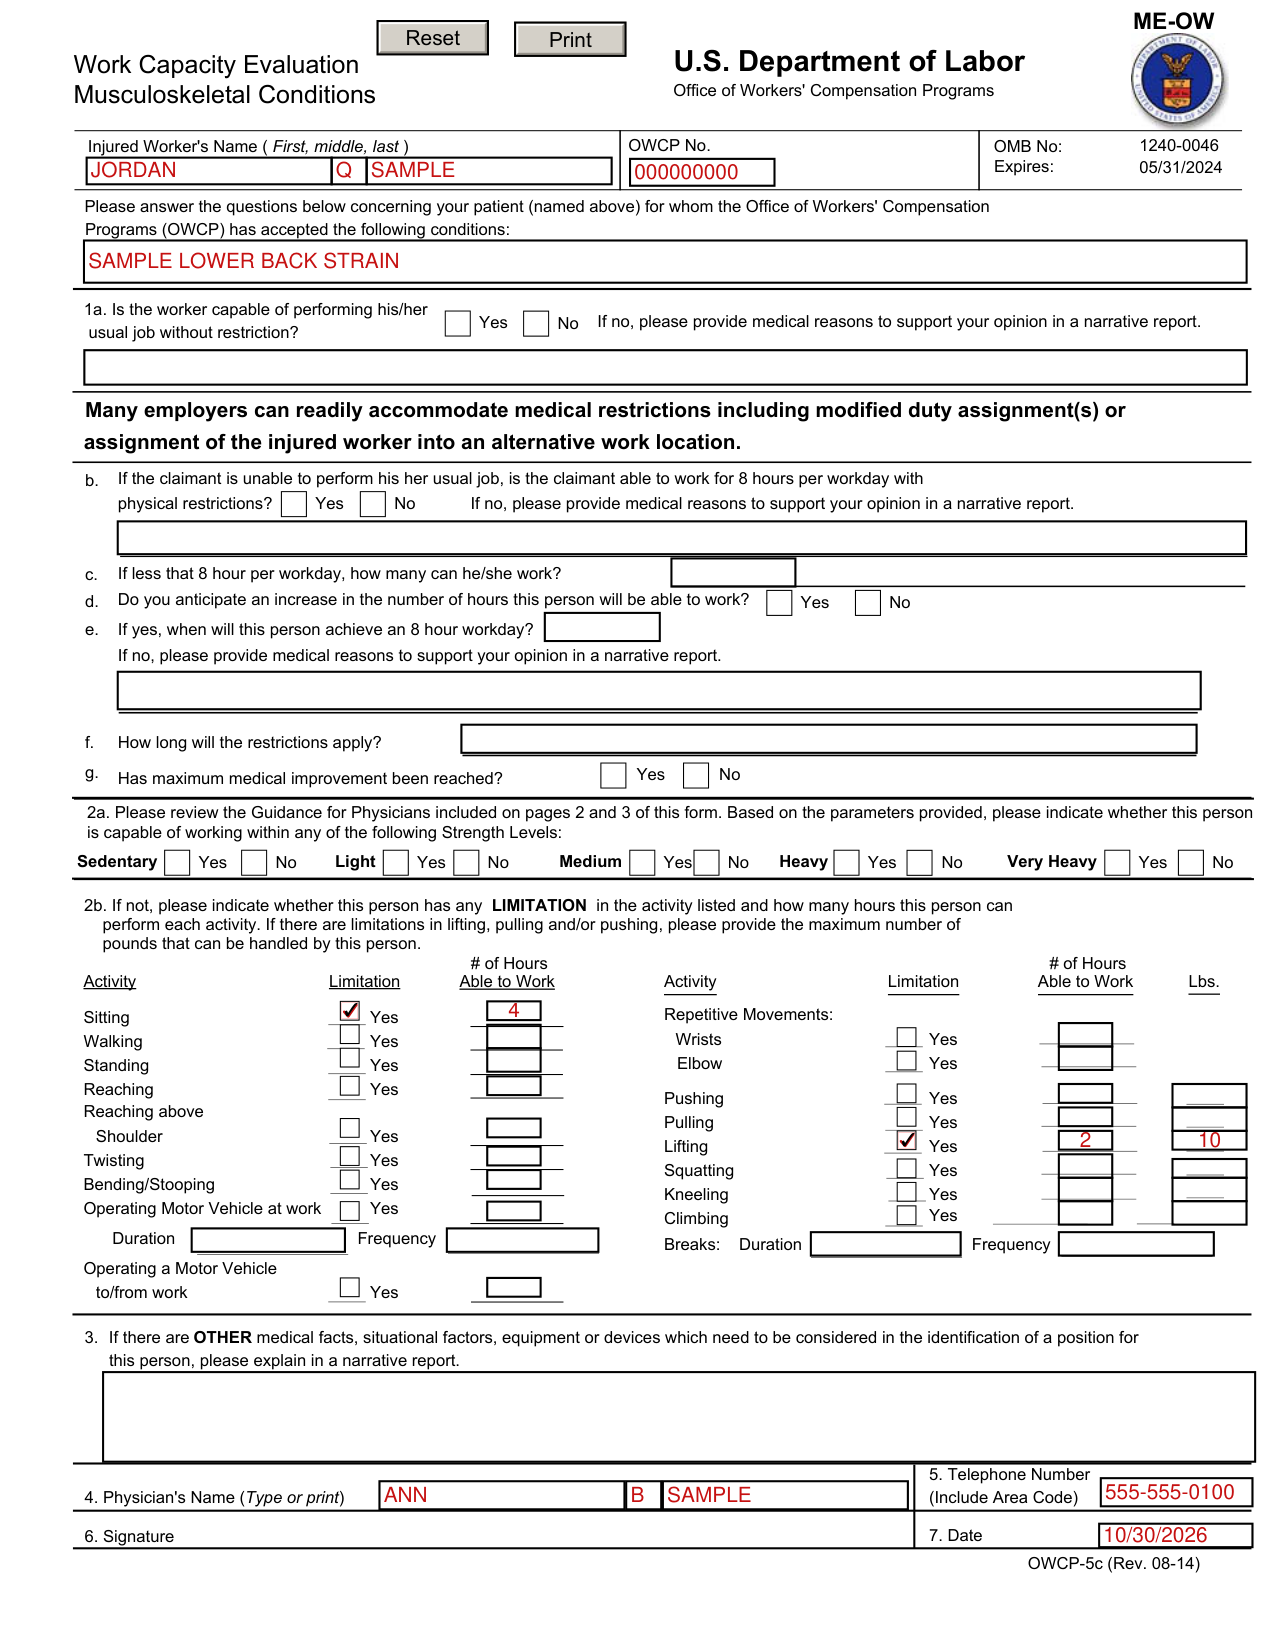
How to fill out Form OWCP-5c, box by box
Injured Worker's Name and OWCP No.
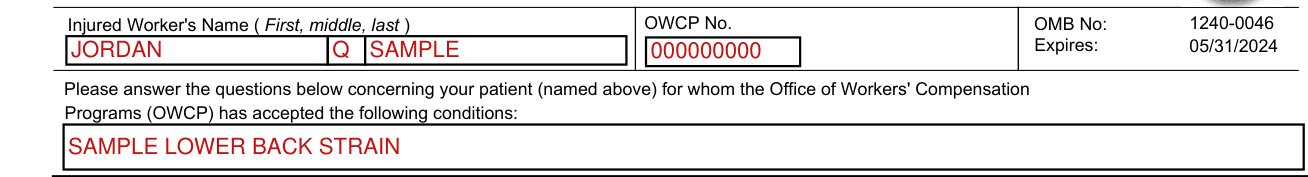
Answer the questions concerning your patient, for whom the Office of Workers' Compensation Programs (OWCP) has accepted the following conditions.
Enter the Injured Worker's Name (First, middle, last) and the OWCP No.
Usual job, 8 hours per workday and maximum medical improvement

1a. Is the worker capable of performing his/her usual job without restriction? If the claimant is unable to perform his her usual job, is the claimant able to work for 8 hours per workday with physical restrictions? If less that 8 hour per workday, how many can he/she work? Do you anticipate an increase in the number of hours this person will be able to work? If yes, when will this person achieve an 8 hour workday? How long will the restrictions apply? Has maximum medical improvement been reached? If no, please provide medical reasons to support your opinion in a narrative report.
Activity limitation and hours
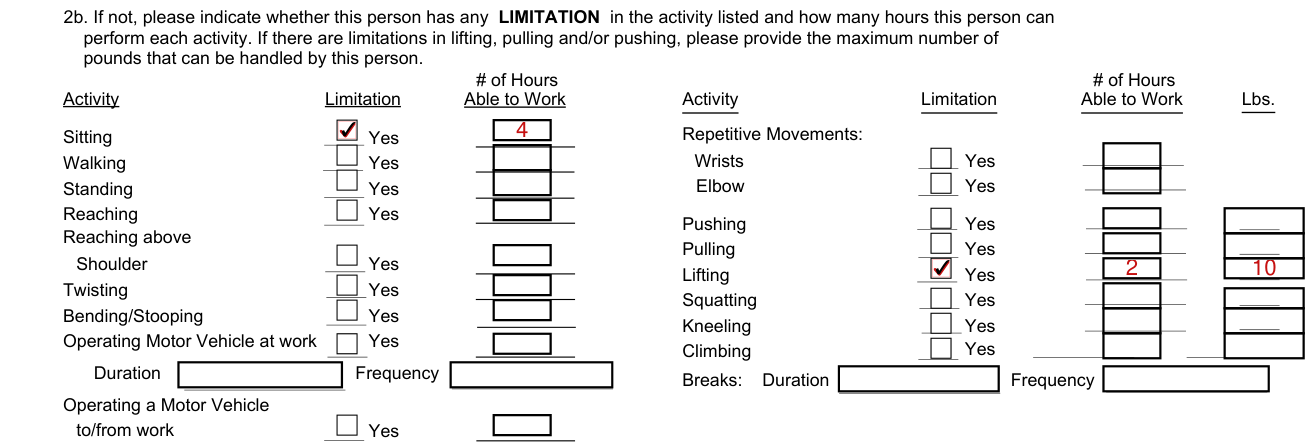
2b. If not, please indicate whether this person has any LIMITATION in the activity listed and how many hours this person can perform each activity. If there are limitations in lifting, pulling and/or pushing, please provide the maximum number of pounds that can be handled by this person.
Breaks and Operating a Motor Vehicle
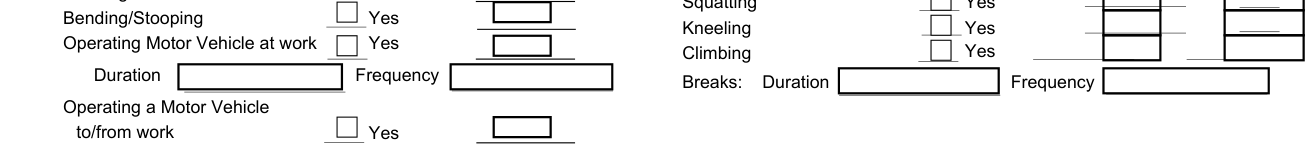
Enter the Duration and Frequency of the breaks.
Other medical facts, situational factors, equipment or devices
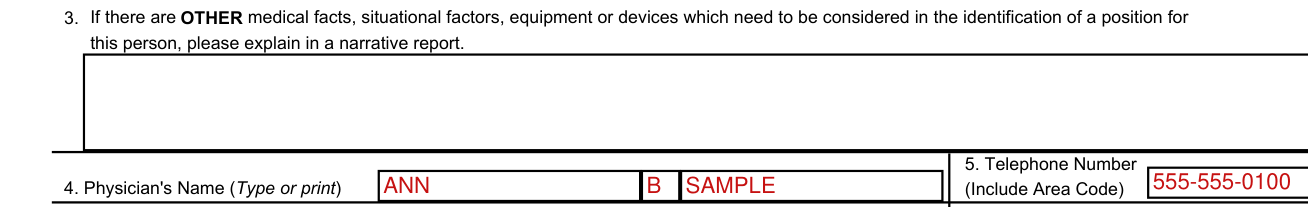
If there are OTHER medical facts, situational factors, equipment or devices which need to be considered in the identification of a position for this person, please explain in a narrative report.
Physician's Name and Telephone Number
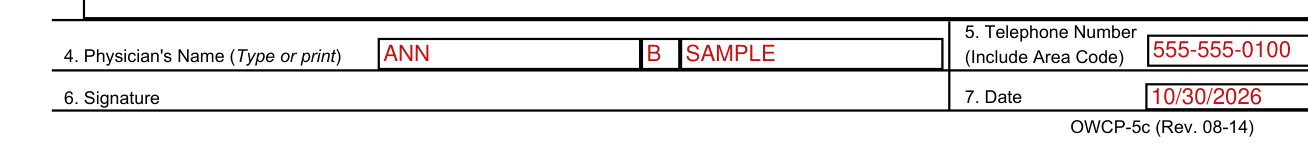
Type or print the Physician's Name in box 4.
In box 5, enter the Telephone Number, including the Area Code.
More rules for Form OWCP-5c
2a. Please review the Guidance for Physicians included on pages 2 and 3 of this form. Based on the parameters provided, please indicate whether this person is capable of working within any of the following Strength Levels: Sedentary Light Medium Heavy Very Heavy Yes No.
Sedentary Work involves exerting up to 10 pounds of force occasionally or a negligible amount of force frequently to lift, carry, push, pull, or otherwise move objects, including the human body.
Light Work involves exerting up to 20 pounds of force occasionally or up to 10 pounds of force frequently, or a negligible amount of force constantly to move objects.
Medium Work involves exerting 20 to 50 pounds of force occasionally or 10 to 25 pounds of force frequently or an amount greater than negligible and up to 10 pounds constantly to move objects.
Heavy Work involves exerting 50 to 100 pounds of force occasionally, or 25 to 50 pounds of force frequently, or 10 to 20 pounds of force constantly to move objects.
Very Heavy work involves exerting in excess of 100 pounds of force occasionally, or in excess of 50 pounds of force frequently or in excess of 20 pounds of force constantly to move objects.
Frequently Activity/condition exists from 1/3 to 2/3 of the time. Constantly Activity/condition exists 2/3 or more of the time.
Common questions about Form OWCP-5c
Where do I file it?
Please do not return the requested information to the Room S-3229 address. Rather, send it to the address shown on the letterhead.
Sources
[1] Form OWCP-5c (Rev. 08-14), Work Capacity Evaluation Musculoskeletal Conditions, U.S. Department of Labor (the Official source link on this page).
