

Form OWCP-915 at a glance
What it is: Form OWCP-915 is the Claim for Medical Reimbursement of the Office of Workers' Compensation Programs.
Who signs: Signature and Date: you certify that the information is correct and authorize any provider named to release information to the Department of Labor, OWCP if necessary for the proper adjudication of this claim.
This form is to be used to seek reimbursement for out of pocket medical expenses pertaining to the treatment of an accepted condition.
Form OWCP-915 can be used to seek reimbursement for expenses in regard to medical treatment, prescription medication and medical supplies.
A filled-in Form OWCP-915 example: a claimant seeks reimbursement for three prescriptions
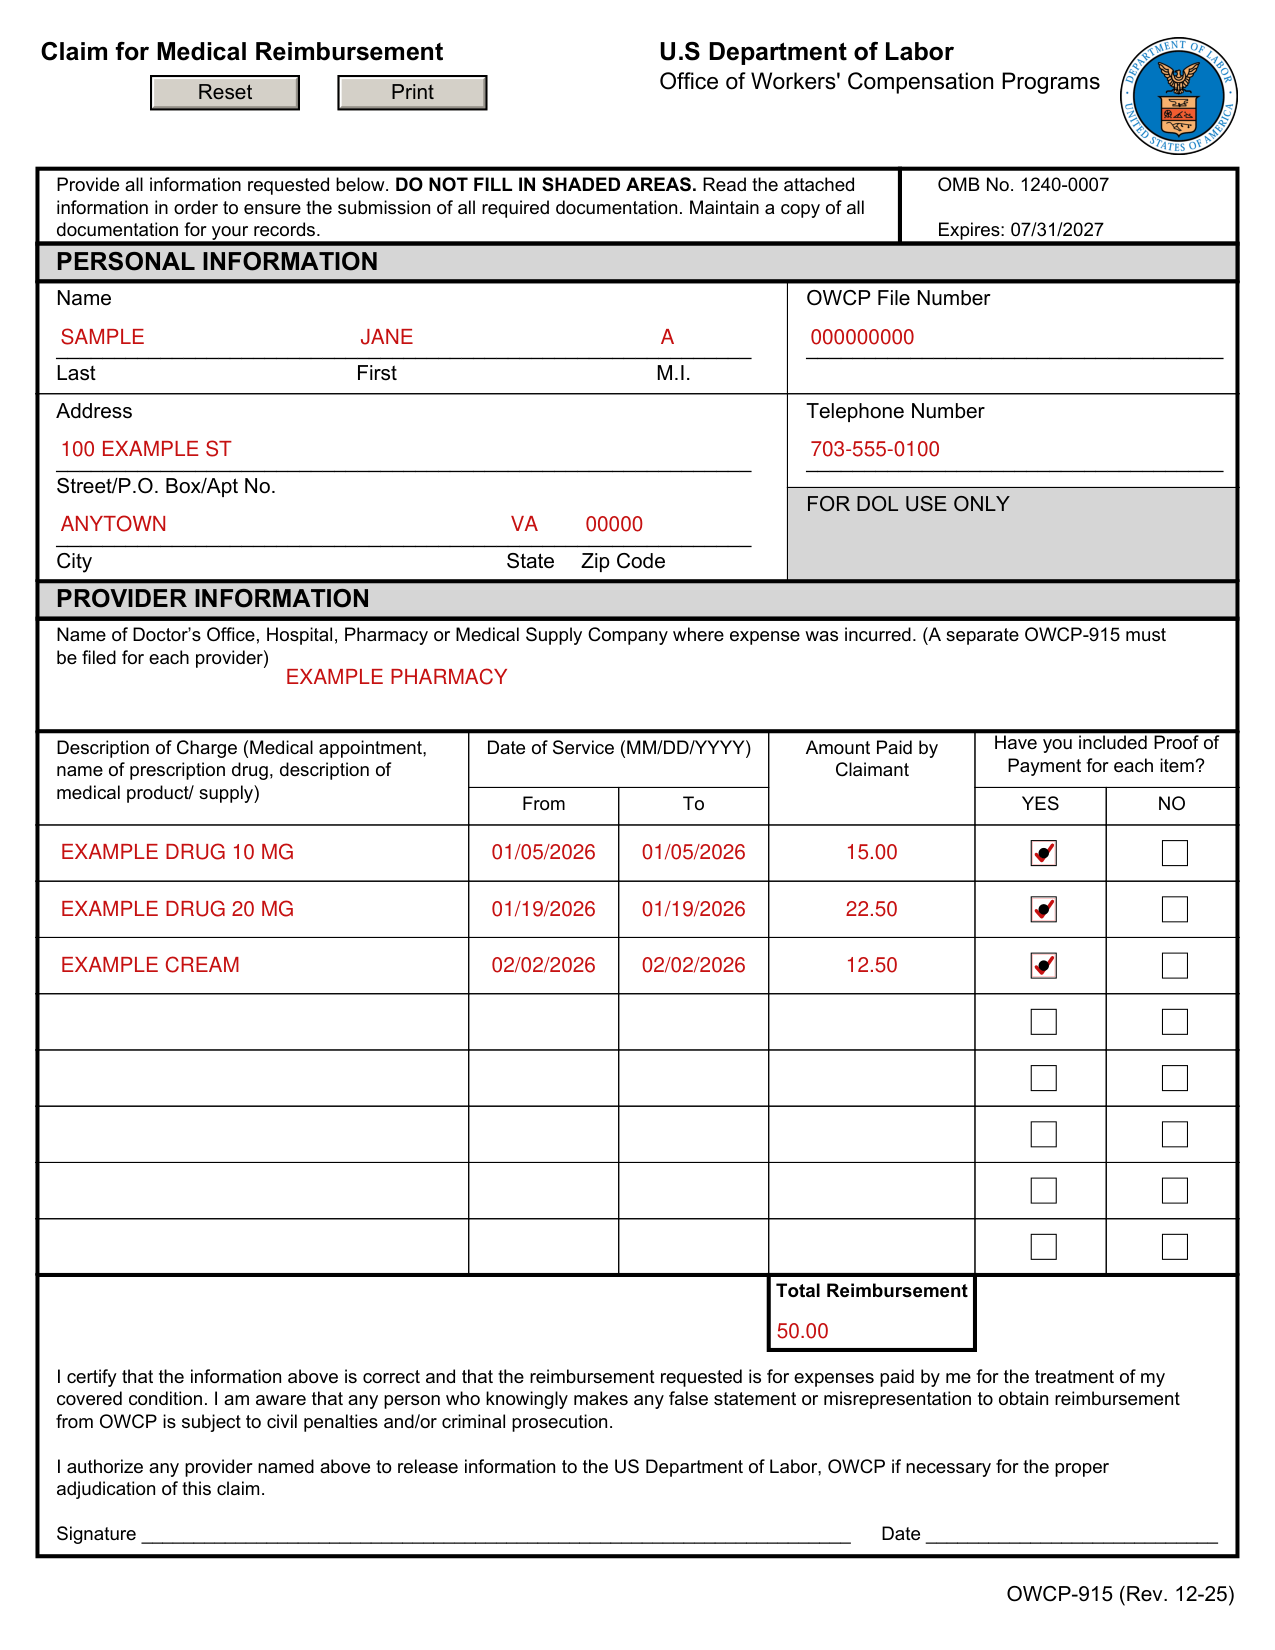
How to fill out Form OWCP-915, box by box
Personal information
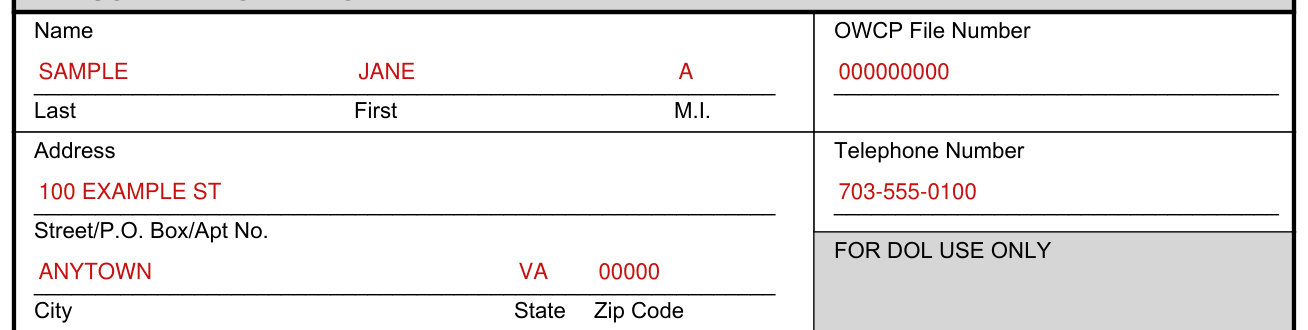
Provide all information requested. DO NOT FILL IN SHADED AREAS.
Under PERSONAL INFORMATION, enter the Name (Last, First, M.I.), OWCP File Number, Address (Street/P.O. Box/Apt No., City, State, Zip Code) and Telephone Number.
Reference your OWCP file number on all documentation.
Provider information

Under PROVIDER INFORMATION, enter the Name of Doctor's Office, Hospital, Pharmacy or Medical Supply Company where expense was incurred. A separate OWCP-915 must be filed for each provider where an out of pocket expense was incurred.
Description of Charge
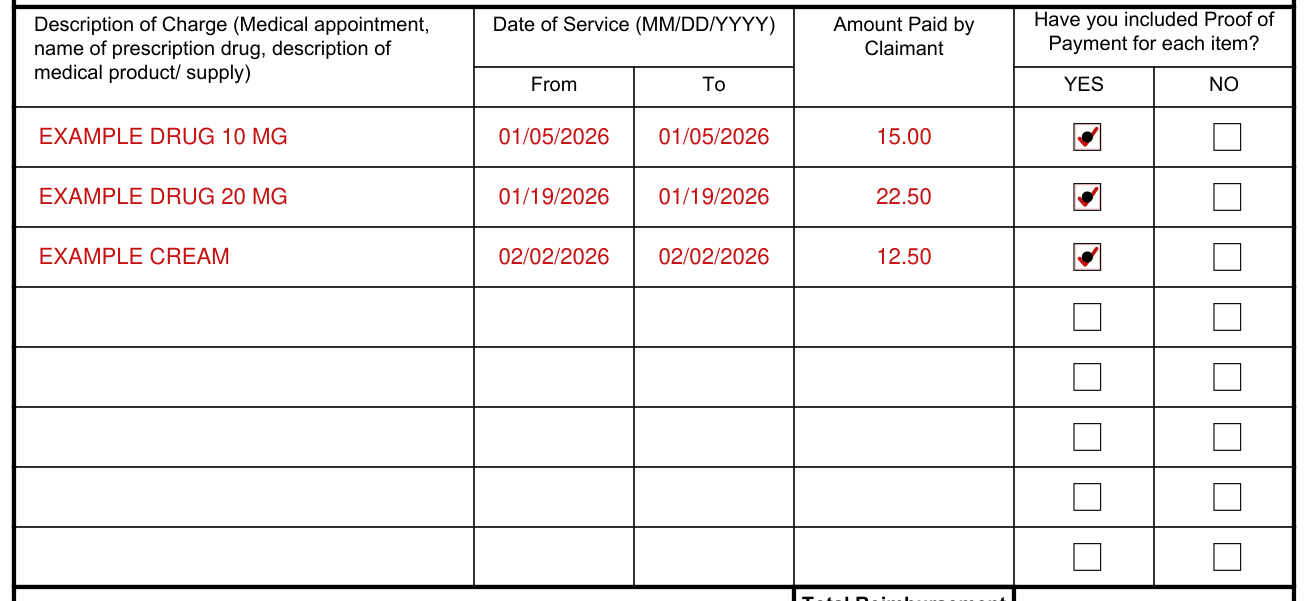
Under Description of Charge, enter Medical appointment, name of prescription drug, description of medical product/ supply.
Enter the Date of Service (MM/DD/YYYY) From and To.
Enter the Amount Paid by Claimant.
Mark YES or NO for Have you included Proof of Payment for each item?
Total Reimbursement, certification and signature

Enter the Total Reimbursement. Under Signature and Date, you certify that the information is correct and that the reimbursement requested is for expenses paid by you for the treatment of your covered condition. You authorize any provider named to release information to the Department of Labor, OWCP if necessary for the proper adjudication of this claim. Any person who knowingly makes any false statement or misrepresentation to obtain reimbursement from OWCP is subject to civil penalties and/or criminal prosecution.
More rules for Form OWCP-915
Please print clearly and legibly.
Maintain a copy of the completed OWCP-915 and supporting documentation for your records.
If your situation is different
Prescription Medication
Prescription Medication: a paper pharmacy billing form must be attached to the OWCP-915. It must include the following information: Name, address and telephone number of pharmacy; Pharmacy provider number; Prescription number; Name of claimant; Date of purchase; Eleven Digit National Drug Code (NDC#); New prescription or refill number; Quantity of medication (e.g. # of pills or ml/cc); Amount paid by employee per medication.
Medical Expense other than prescription medication
Physicians and other health care providers (i.e. physical therapists) must complete Form OWCP-1500. Hospitals and other facilities, such as ambulatory surgical centers, skilled nursing facilities, etc. must submit their bills on Form OWCP-04.
The OWCP-1500 or OWCP-04 must be attached to this form. It is the responsibility of the person submitting a claim for reimbursement to obtain a completed OWCP-1500 or OWCP-04 from the provider rendering service.
Every form must be completed in its entirety in the same manner as bills submitted by the provider directly to OWCP. The amount paid by the claimant must be indicated.
Without a fully completed OWCP-1500 or OWCP-04, the OWCP is not able to process a reimbursement.
Before you go
Proof of payment can include cash receipt, cancelled check or credit card slip.
To receive payment, you must have electronic banking information (Electronic Funds Transfer or EFT) on file with the appropriate program to prevent a delay in the processing of your bills.
Go To https://www.fiscal.treasury.gov/files/forms/form-1199a.pdf to download and complete the EFT form.
Common questions about Form OWCP-915
Where do I file it?
Return this completed claim form to the appropriate program address. Division of Federal Employees' Compensation (DFEC), PO Box 8300, London, KY 40742-8300; Division of Coal Mine Workers' Compensation (DCMWC), PO Box 8302, London, KY 40742-8302; Division of Energy Employees Occupational Illness Compensation (DEEOIC), PO Box 8304, London, KY 40742-8304, or submit electronically via Energy Document Portal (EDP).
When is this form not the right one?
Do not use Form OWCP-915 to submit a claim for travel reimbursement. Claims for travel reimbursement should be submitted on Form OWCP-957.
Sources
[1] Form OWCP-915 (Rev. 12-25), Claim for Medical Reimbursement, U.S. Department of Labor (the Official source link on this page).
