

OWCP-1168 at a glance
What it is: Provider Enrollment Form U.S. Department of Labor Office of Workers' Compensation Programs
Where and when to file: Print, sign and mail or fax form to Provider Enrollment Department of Labor - OWCP P. O. Box 8312 London, KY 40742-8312 Fax: 888-444-5335
Thank you for your interest in providing medical services for injured and ill workers served by the U.S. Department of Labor's Office of Workers' Compensation Programs (OWCP).
Providers can enroll in any one or more of the three OWCP compensation programs.
What to bring and attach to OWCP-1168
Please complete and attach copies of all license/certification required by your State to perform the service under your Provider Type.
If a license or certification is not required by the State, attach letter/ evidence from the State authority.
A filled-in OWCP-1168 example: a medical supply company enrolls as a new facility provider

How to fill out OWCP-1168, box by box
1. Are you applying for a new enrollment or updating your record?

Are you applying for a new enrollment or updating your record? New Enrollment Re-Enrollment Re-Validation Update
For Update, ONLY complete sections you wish to change, then Confirm and Sign on page 8.
If Update, Re-Enrollment or Re-Validation, Enter Provider ID or Federal Employer Identification Number (FEIN)
2. Enrollment Type

Enrollment Type (Refer to Instructions for additional information): Individual; Group Practice (Please see Page 9 - Addendum 1, for completion of group practice enrollment for each professional); Facility/Agency/Organization/Institution
3. Provider Type

Provider Type: If selecting “Other Provider” (96) or Non-Medical Vendor (53), please complete 3a.: Please explain
All fields in this section are required; if "other" is selected, explanation is required.
4. Program

Program (Check the Program(s) in which you want to enroll as a provider.) DFEC DCMWC DEEOIC DLHWC
5. Individual Information

Individual Information (If enrolling using SSN): Last Name, Middle Name, First Name, SSN
6. Organization Information

Organization Information (If enrolling using FEIN): Organization Name (Legal Business Name), Organization Business Name (Doing Business As), FEIN
7. National Provider Identifier (NPI), 8. Entity Type and 9. Email Address

National Provider Identifier (NPI) (Refer to Appendix 3). Entity Type: Select. If Other, please explain. Email Address.
10. I do not wish to be included in an online searchable list of OWCP providers

I do not wish to be included in an online searchable list of OWCP providers. Reason
However, selecting this option will not exclude your information in a FOIA (Freedom Of Information Act) request.
PART B: LOCATION
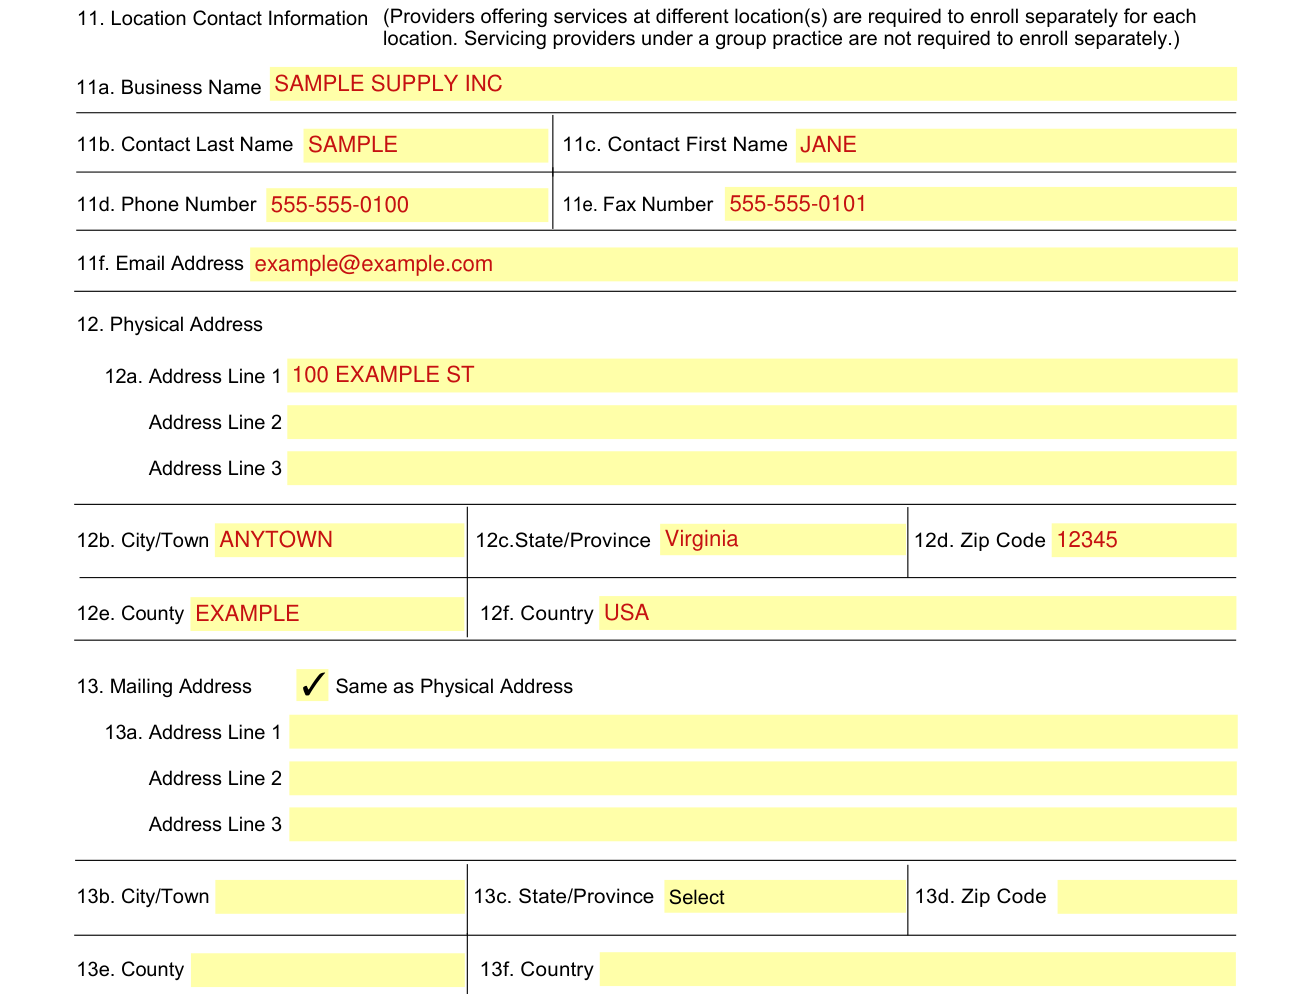
All fields are required. If not applicable specify N/A.
Providers offering services at different location(s) are required to enroll separately for each location. Servicing providers under a group practice are not required to enroll separately.
Mailing Address Same as Physical Address
PART C: TAXONOMY

Taxonomy (Required if applicable.)
Use Addendum 1 for taxonomy for servicing providers Use Addendum 2 for additional taxonomy codes.
PART D: OWNERSHIP DETAILS

OWNERSHIP DETAILS (Optional. Refer to Instructions for additional information.)
For DFEC and DEEOIC providers, list any business with more than a 5% interest in or where involvement is at an officer, director or agent of the company
PART E: LICENSE AND CERTIFICATION
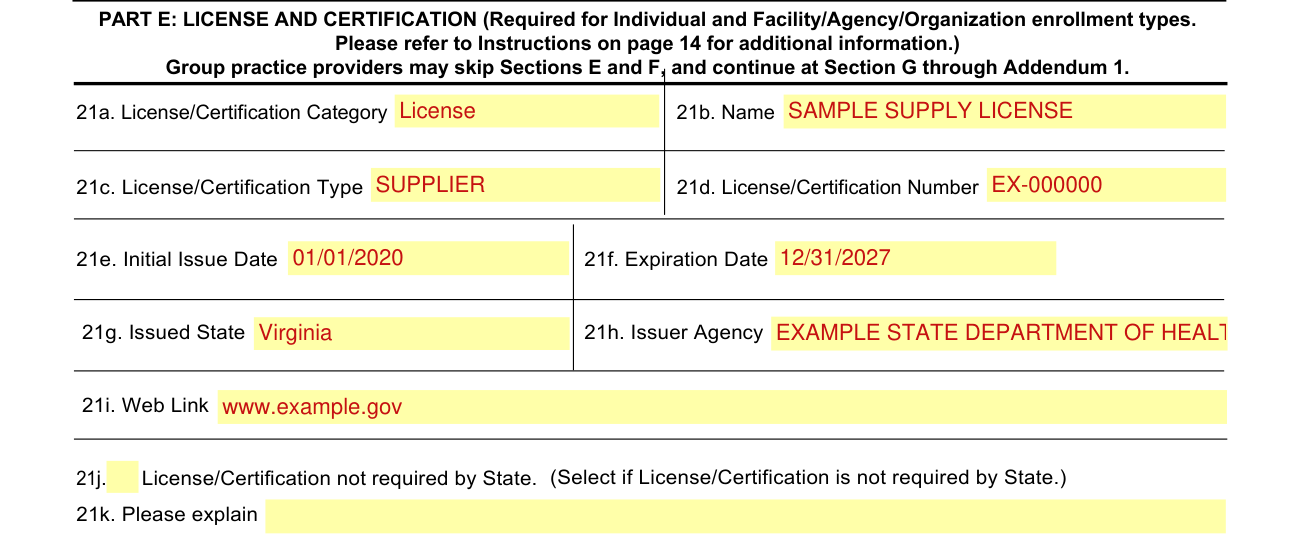
LICENSE AND CERTIFICATION (Required for Individual and Facility/Agency/Organization enrollment types.
Group practice providers may skip Sections E and F, and continue at Section G through Addendum 1.
If you have a renewed license/certification under a different number, please make sure to enter it using the exact same License/Certification Type.
PART F: IDENTIFIERS

IDENTIFIERS: (Medicare number is required for hospitals (Provider type: 01, 02, 03).)
PART G: EDI SUBMISSION METHOD

EDI SUBMISSION METHOD: Mode of Submission. Check all applicable (See Instructions on page 15 for details regarding modes of submission).
Don't select “None” if other submission method is selected.
PART H: EDI SUBMITTER DETAILS

EDI SUBMITTER DETAILS (Required if Billing Agent/Clearinghouse selected in Part G).
Your Billing Agent/Clearinghouse must be enrolled with OWCP first.
PART I: EDI CONTACT DETAILS

EDI CONTACT DETAILS (Required if submitting EDI).
Disclosure Statement

Disclosure Statement Within ten years of the date of this statement have you or any individual listed on this application had an action related to fraud or abuse in a government program taken against him or her resulting in (1) a felony or misdemeanor conviction; (2) a liability finding in civil proceedings; or (3) a settlement entered in lieu of conviction? Yes No If Yes, provide details including type of action, Agency undertaking adverse action and date of action.
Required for DFEC providers

Required for DFEC providers For Provider Type “Medical Supplies/Durable Medical Equipment (DME) / Prosthetics / Orthotics” (75) only: Are you an accredited DMEPOS supplier enrolled with Medicare? Yes No If Yes, provide the phone number that you used in your Medicare DMEPOS enrollment.
Confirm and Sign
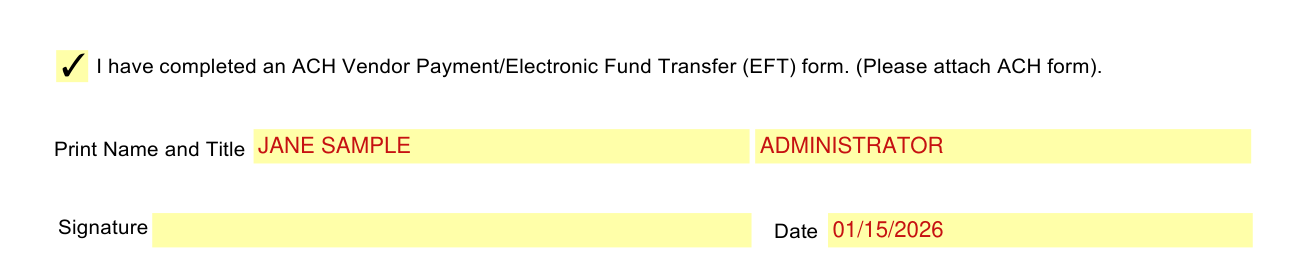
Confirm and Sign I, the undersigned, certify to the following: I have read the contents of this application, and the information contained herein is true, correct, and complete.
“I certify that I and my agents have currently in effect all necessary licenses, certifications, approvals, insurance, etc. required to properly provide the services and/or supplies for the OWCP in the state, county, locality, or jurisdiction where the services and/or supplies are provided. I will provide proof of such licenses, certifications, approvals, insurance, etc. upon the OWCP's request.”
I also certify that I am not currently sanctioned, suspended, debarred or excluded by any Federal or State Health Care Program, (e.g., Medicare, Medicaid, or any other Federal program), or otherwise prohibited from providing services to Medicare, Medicaid, or other Federal program beneficiaries nor are any owners, officers, or managing employees of the practice listed in this application.
Be sure to sign and date the form when you submit it.
I have completed an ACH Vendor Payment/Electronic Fund Transfer (EFT) form. (Please attach ACH form).
Print Name and Title Signature Date
I agree to notify the OWCP of any change in ownership, practice location and/or Final Adverse Action involving fraud or abuse within 30 days of the reportable event.
In addition, I agree to notify the OWCP of any other changes to the information in this form within 90 days of the effective date of change.
Upload completed enrollment form and required documents to the Workers Compensation Medical Bill Processing Portal (WCMBP) for enrollment processing.
Addendum 1: Servicing Providers Information for Group Practice Enrollment
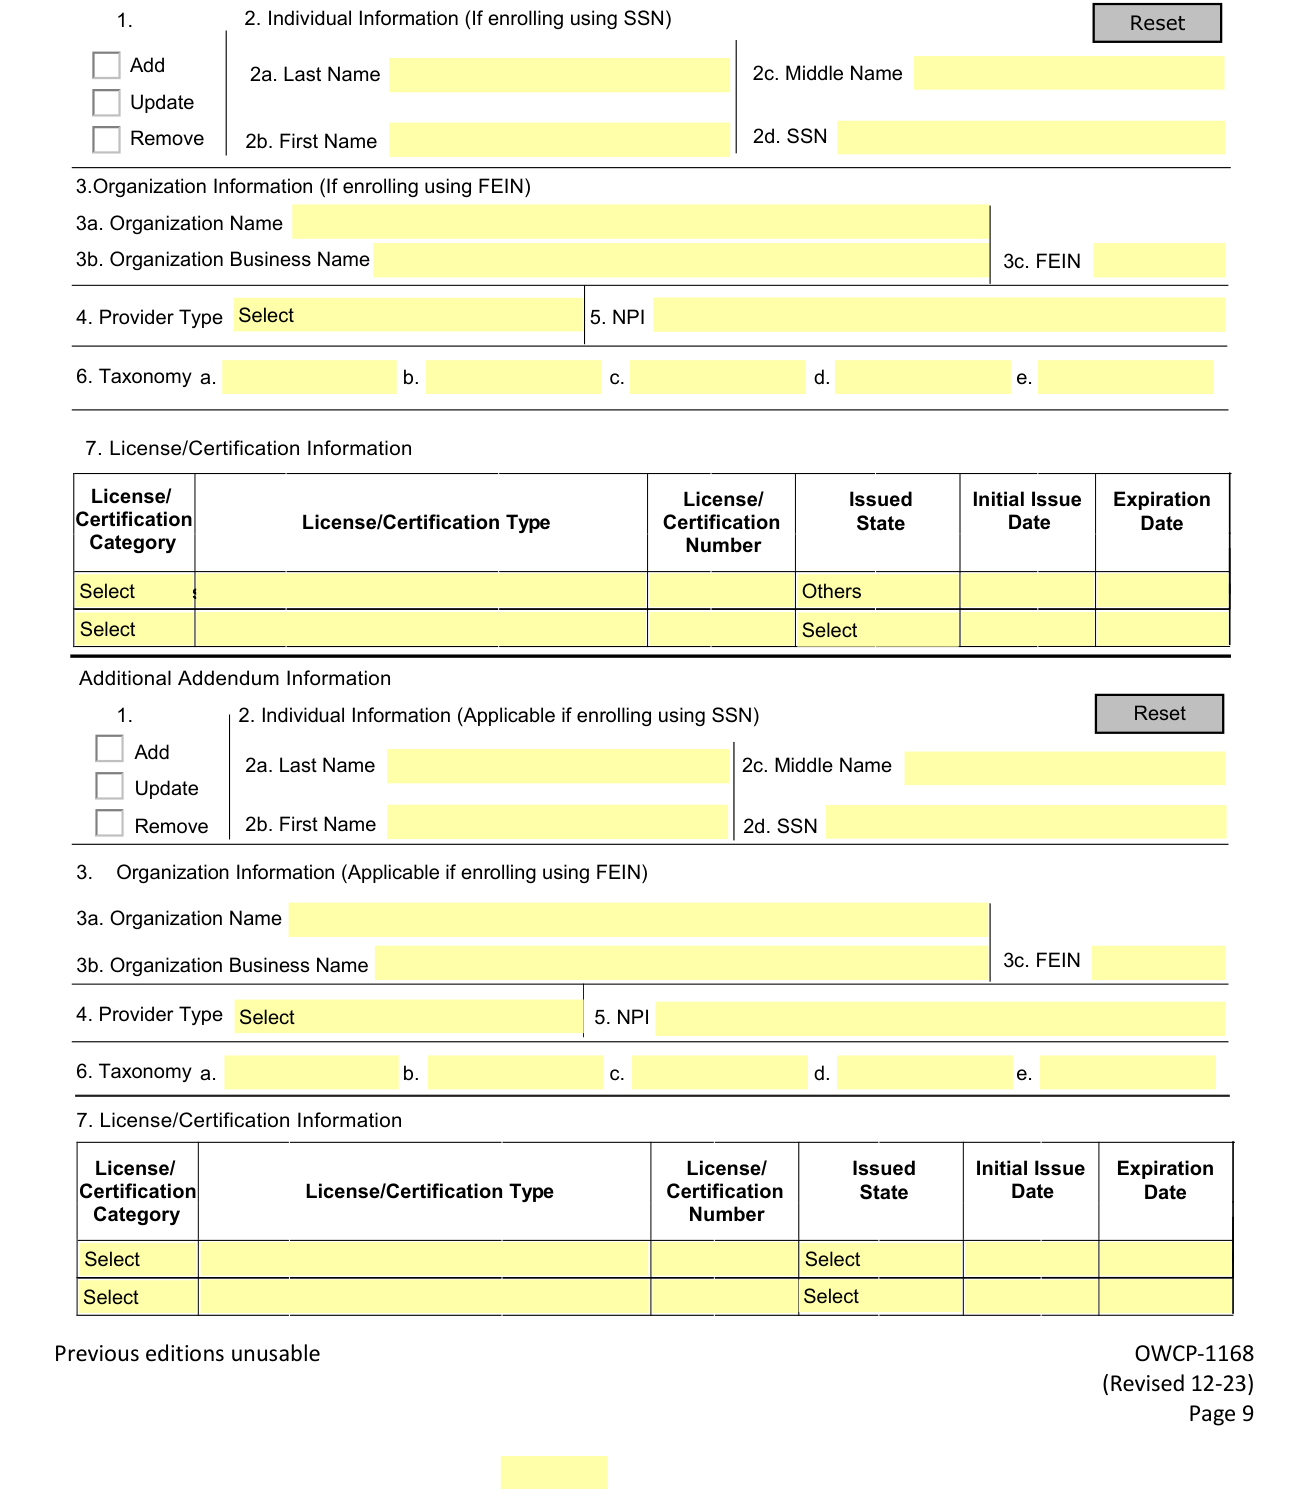
Addendum 1: Servicing Providers Information for Group Practice Enrollment (All fields are required for providers enrolled as Group Practice. Fill in this addendum to add, update or remove servicing providers for Group Practice. Use additional sheet(s) as required.
For New Enrollment, only Add action can be selected.
Common questions about OWCP-1168
Is there a penalty?
I understand that any deliberate omission, misrepresentation, or falsification of any information contained in this application or contained in any communication supplying information to the Department of Labor, Office of Workers' Compensation Program (OWCP), or any deliberate alteration of any text on this application form, may be punished by criminal, civil, or administrative penalties including, but not limited to, the denial or revocation of OWCP billing privileges, civil damages, and/or imprisonment.
Where to get help with OWCP-1168
For questions about completing the enrollment form, please contact OWCP's medical bill processing contractor Enrollment Call Center at 844-493-1966, Monday through Friday from 8:00 a.m. to 8:00 p.m., Eastern Time.
Sources
[1] Provider Enrollment Form OWCP-1168 (Revised 12-23), U.S. Department of Labor, Office of Workers' Compensation Programs (the Official source link on this page).
