
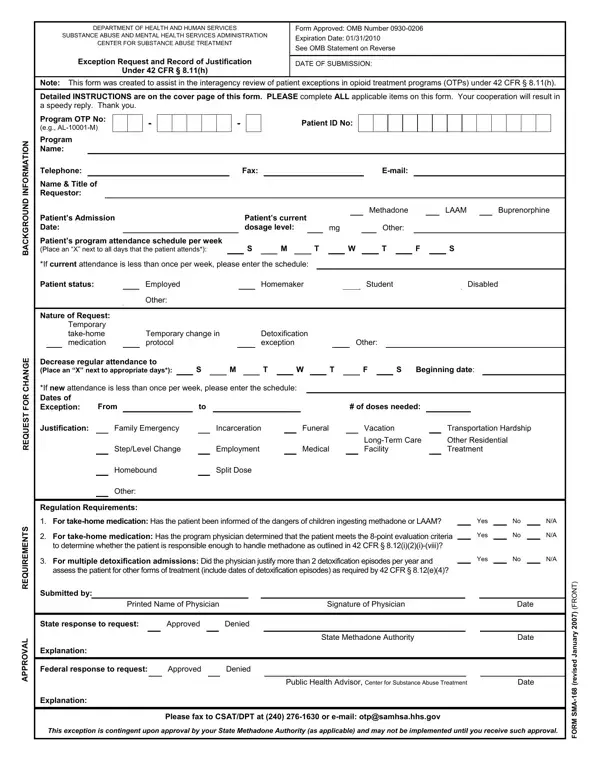

Form SMA-168 at a glance
What it is: The Exception Request and Record of Justification Under 42 CFR § 8.11(h) was created to assist in the interagency review of patient exceptions in opioid treatment programs (OTPs) under 42 CFR § 8.11(h).
Where and when to file: Please fax to CSAT/DPT at (240) 276-1630 or e-mail: otp@samhsa.hhs.gov.
A filled-in Form SMA-168 example: a physician requests a short exception
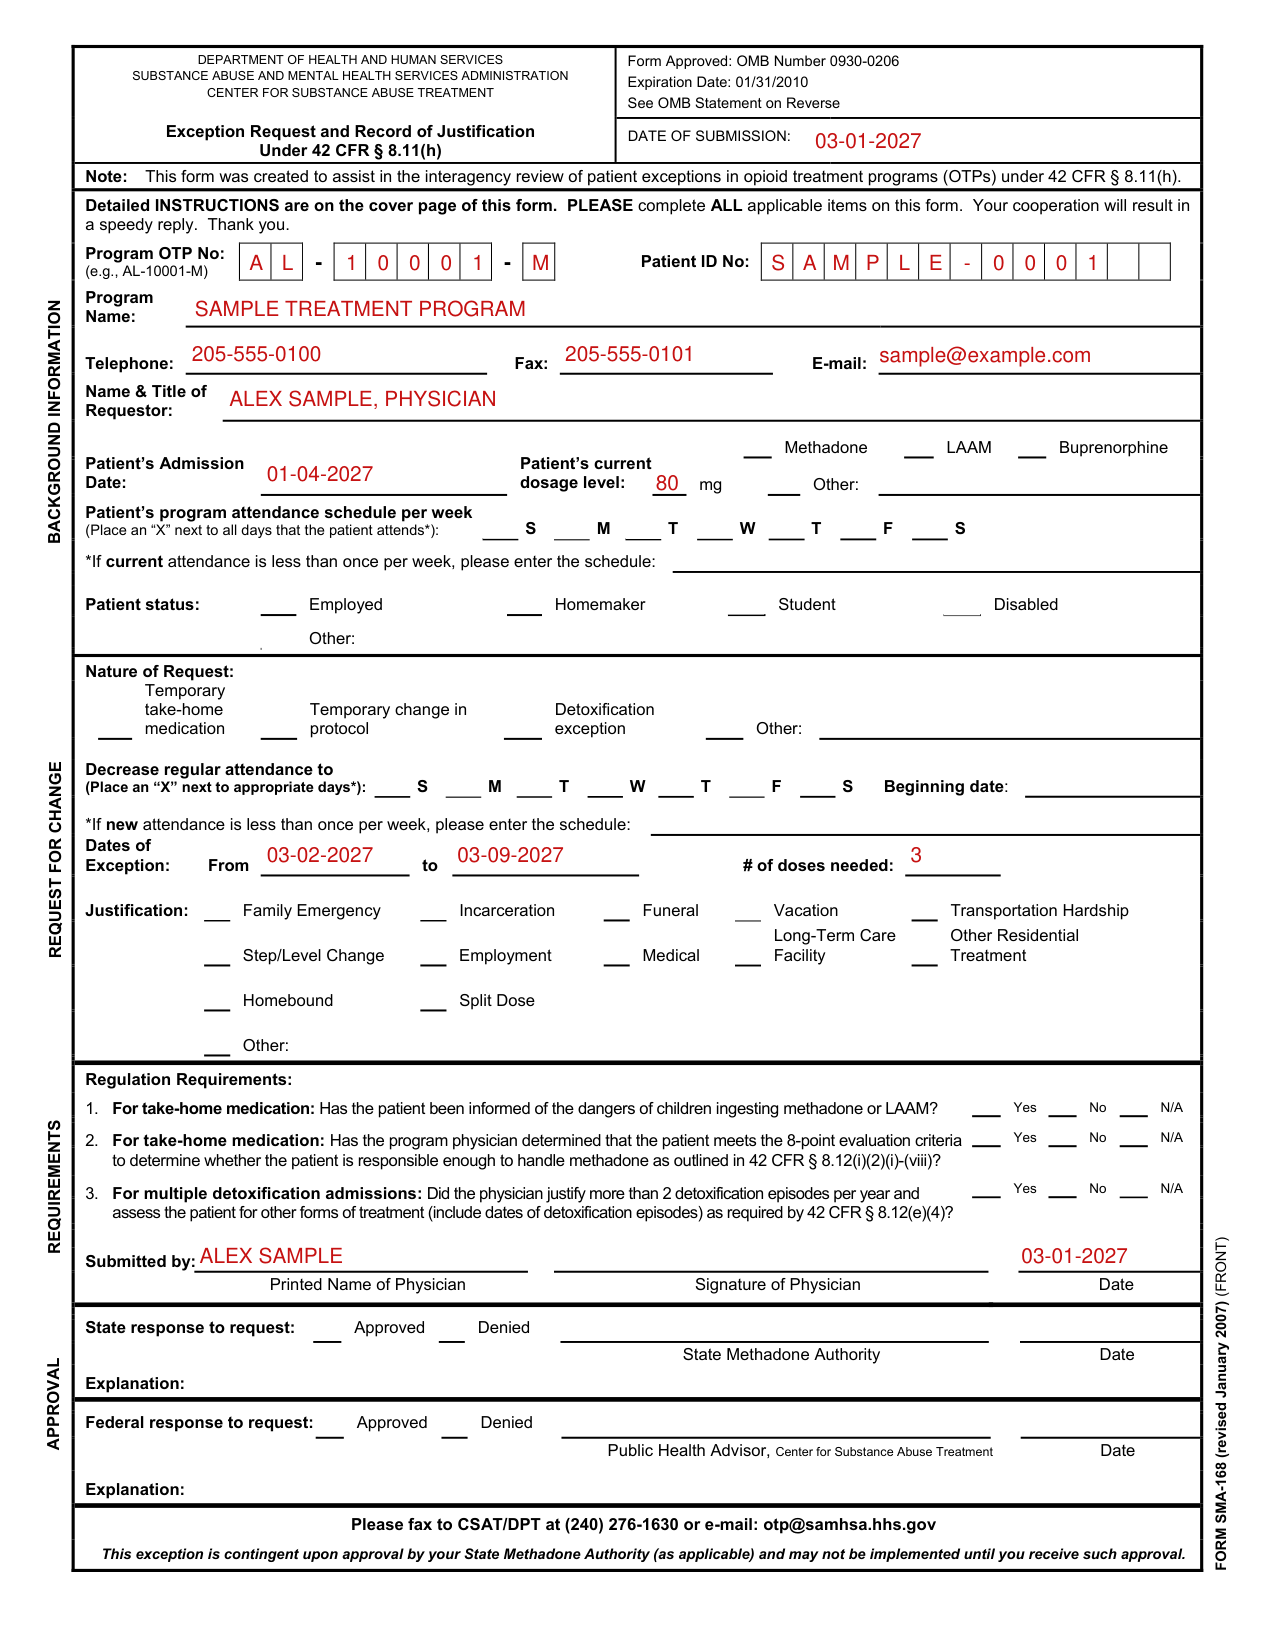
How to fill out Form SMA-168, box by box
Program, patient and requestor
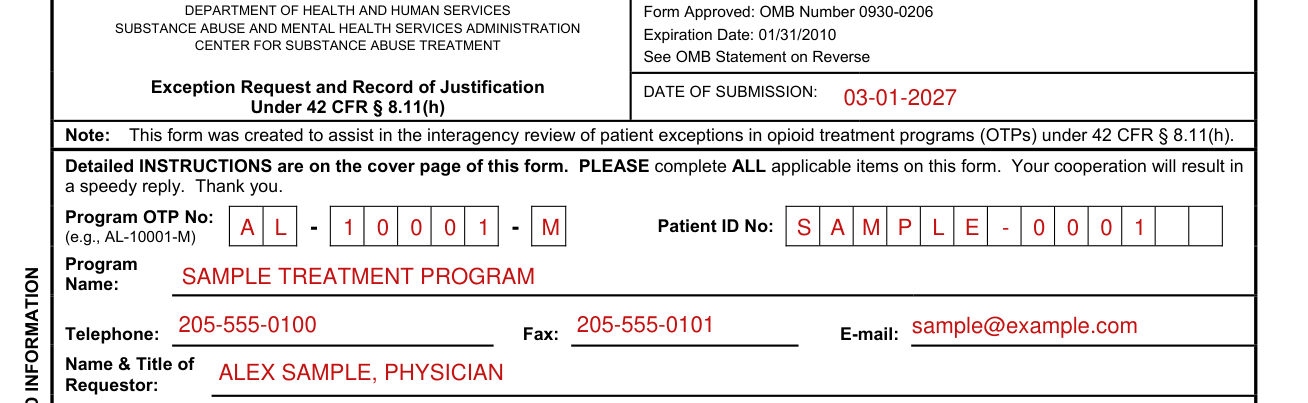
Enter the DATE OF SUBMISSION.
Enter the Program OTP No (e.g., AL-10001-M) and the Patient ID No, then the Program Name.
Enter the Telephone, Fax and E-mail, and the Name & Title of Requestor.
Dosage and attendance
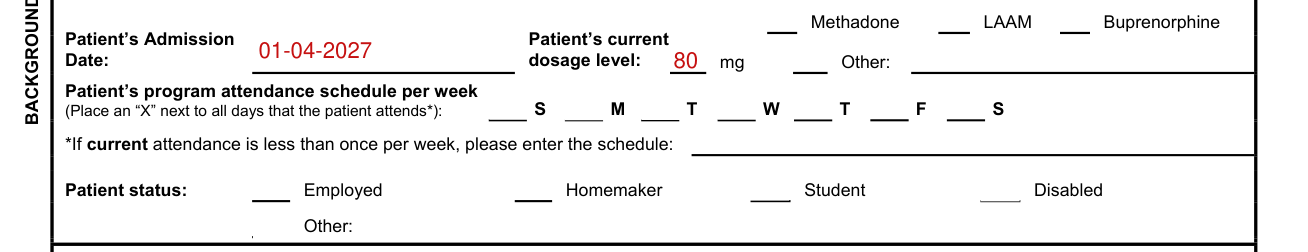
Mark Methadone, LAAM or Buprenorphine, then enter the Patient's Admission Date and the Patient's current dosage level in mg, or Other.
In the Patient's program attendance schedule per week, place an “X” next to all days* that the patient attends. For the * after days: If current attendance is less than once per week, please enter the schedule.
For Patient status, mark Employed, Homemaker, Student, Disabled or Other, and write the status after Other.
Nature of Request and Justification
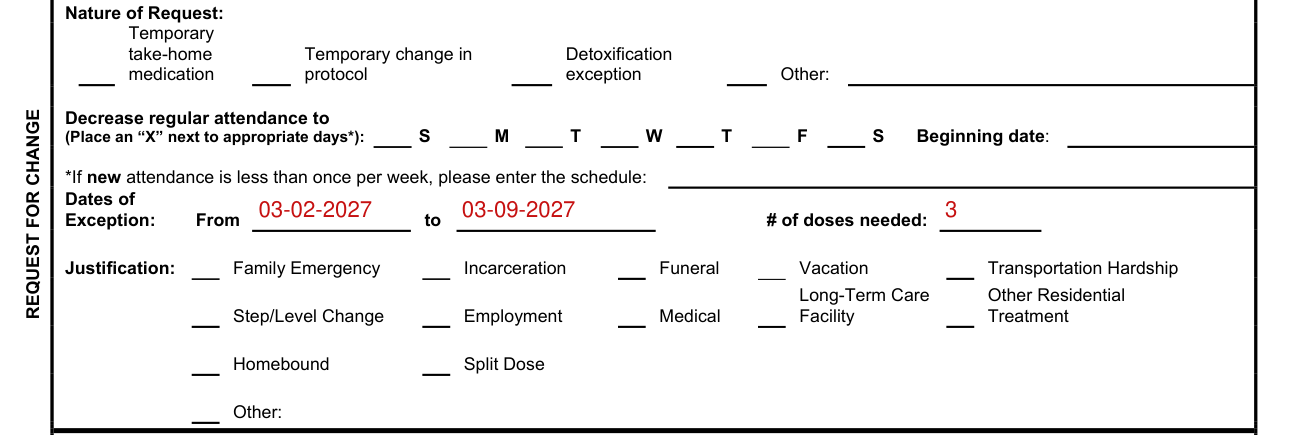
For Nature of Request, mark Temporary take-home medication, Temporary change in protocol, Detoxification exception or Other.
If you decrease regular attendance, place an “X” next to the appropriate days* and enter the Beginning date. For the * after days: If new attendance is less than once per week, please enter the schedule. Enter the Dates of Exception: From and to, and the # of doses needed.
For Justification, mark Family Emergency, Incarceration, Funeral, Vacation, Transportation Hardship, Step/Level Change, Employment, Medical, Long-Term Care Facility, Other Residential Treatment, Homebound, Split Dose or Other.
Regulation Requirements
Under Regulation Requirements, mark Yes, No or N/A for 1. For take-home medication: Has the patient been informed of the dangers of children ingesting methadone or LAAM?
Mark Yes, No or N/A for 2. For take-home medication: Has the program physician determined that the patient meets the 8-point evaluation criteria to determine whether the patient is responsible enough to handle methadone as outlined in 42 CFR § 8.12(i)(2)(i)-(viii)?
Mark Yes, No or N/A for 3. For multiple detoxification admissions: Did the physician justify more than 2 detoxification episodes per year and assess the patient for other forms of treatment (include dates of detoxification episodes) as required by 42 CFR § 8.12(e)(4)?
Submitted by and the responses
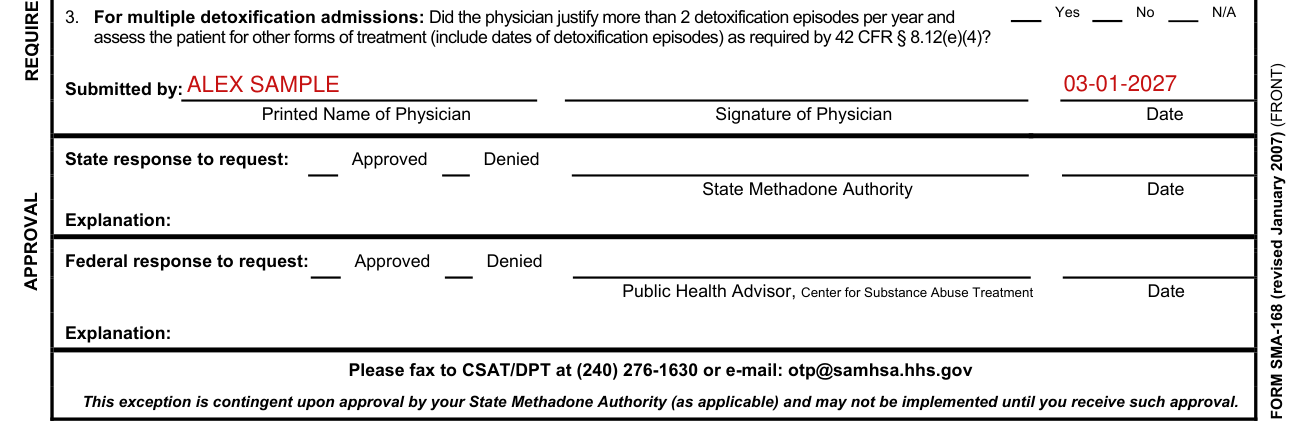
Under Submitted by, enter the Printed Name of Physician, sign on the Signature of Physician line and enter the Date.
The State response to request (Approved or Denied, State Methadone Authority, Date, Explanation) is for your State Methadone Authority.
The Federal response to request (Approved or Denied, Date, Explanation) is for the Public Health Advisor, Center for Substance Abuse Treatment.
More rules for Form SMA-168
The form was created to facilitate the submission and review of patient exceptions under 42 CFR § 8.11(h).
Please complete all applicable items on this form.
This exception is contingent upon approval by your State Methadone Authority (as applicable) and may not be implemented until you receive such approval.
Common questions about Form SMA-168
Where do I file it?
Please fax to CSAT/DPT at (240) 276-1630 or e-mail: otp@samhsa.hhs.gov.
Sources
[1] Form SMA-168 (revised January 2007), Exception Request and Record of Justification Under 42 CFR § 8.11(h), Substance Abuse and Mental Health Services Administration (the Official source link on this page).