

Form SSA-10 at a glance
What it is: Form SSA-10 is the Application for Social Security Benefits.
Who signs: SIGNATURE OF APPLICANT: Signature (First name, middle initial, last name) (Write in ink).
With this application, you are applying for all insurance benefits for which you are eligible under Title II (Federal Old-Age, Survivors, and Disability Insurance) and Part A of Title XVIII (Health Insurance for the Aged and Disabled) of the Social Security Act as presently amended. The information you furnish on this application will ordinarily be sufficient for a determination on the lump-sum death payment. If you were receiving spouse's benefits at the time of your spouse's death, you only need to complete the circled items. All other claimants must complete the entire form. This may also serve as an application for survivors benefits under the Railroad Retirement Act and for Veterans Administration payments under title 38 U.S.C., Veterans Benefits, Chapter 13 (which is, as such, an application for other types of death benefits under title 38).
A filled-in Form SSA-10 example: a widow starts the application
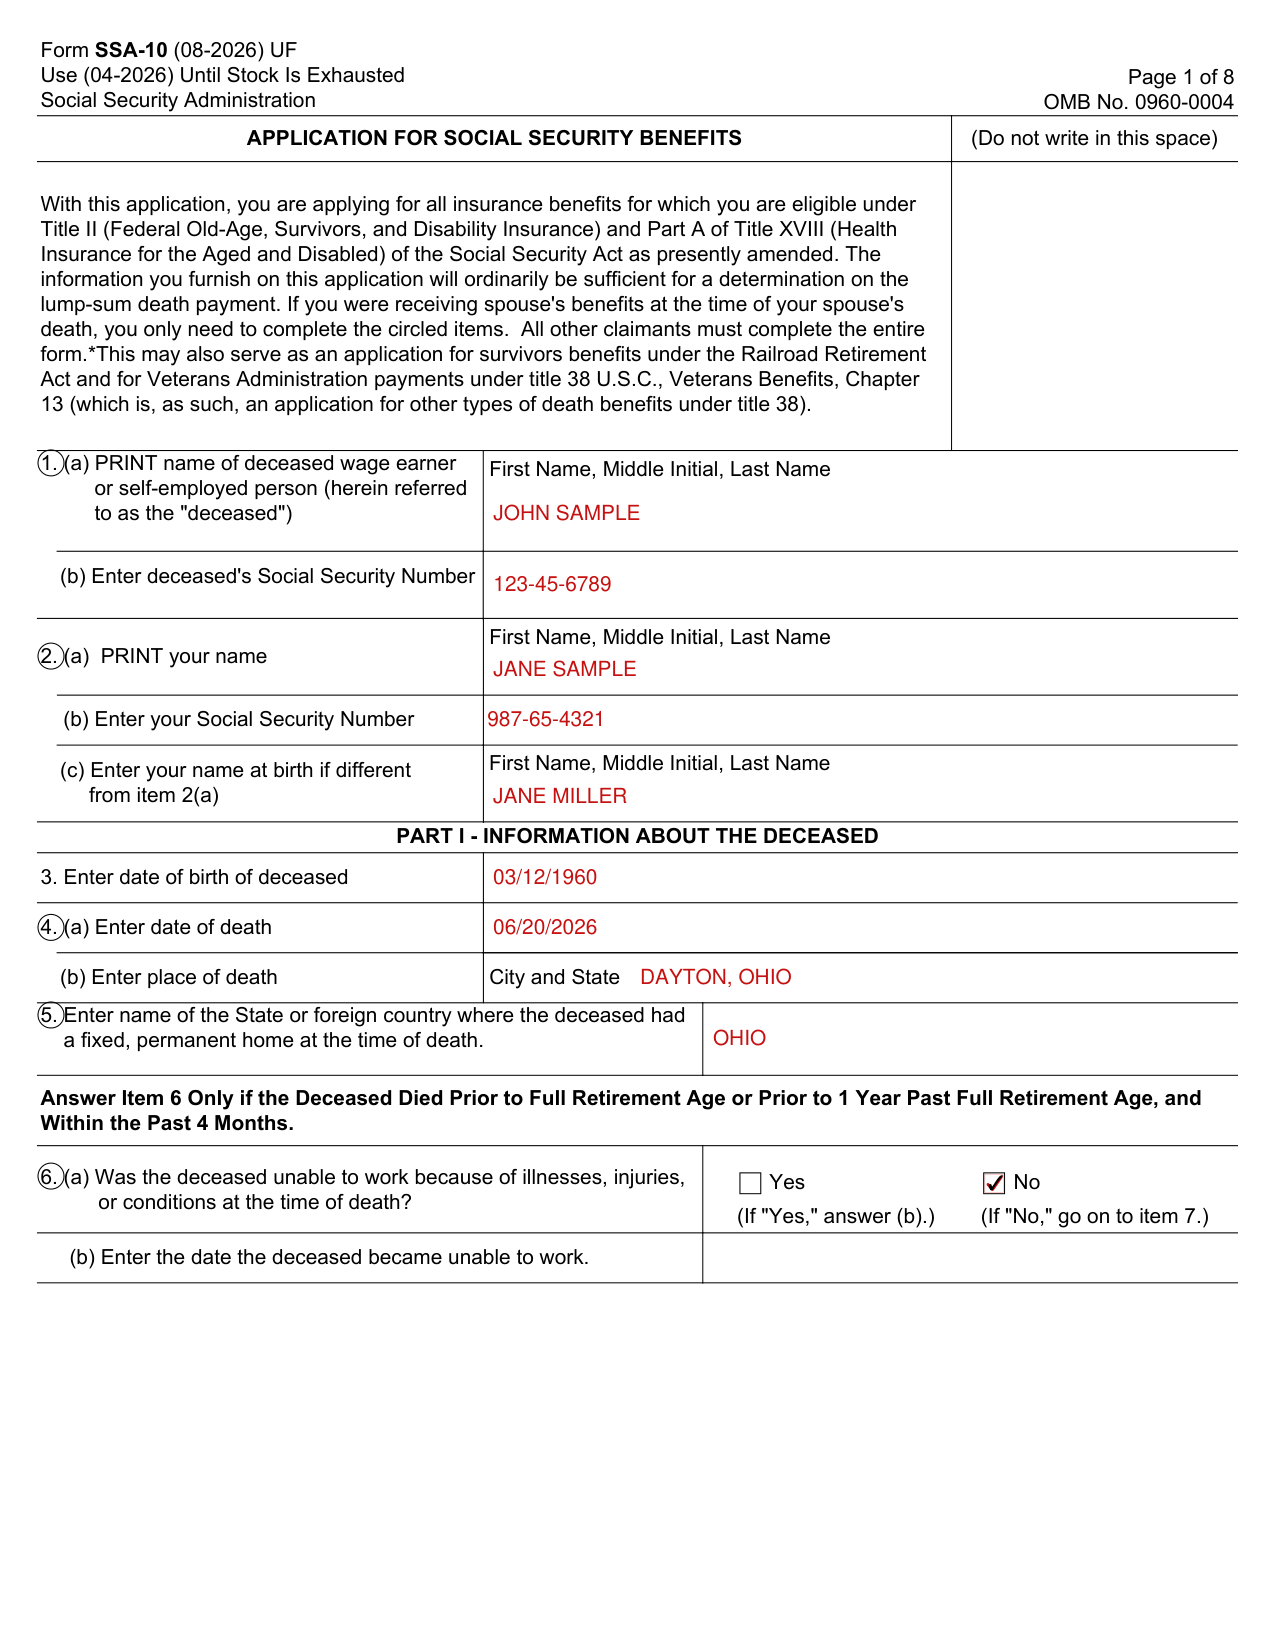
How to fill out Form SSA-10, box by box
1. and 2. Your name and the deceased's name

In 1(a), PRINT name of deceased wage earner or self-employed person (herein referred to as the "deceased"): First Name, Middle Initial, Last Name. In 1(b), enter deceased's Social Security Number.
In 2(a), PRINT your name: First Name, Middle Initial, Last Name. In 2(b), enter your Social Security Number. In 2(c), enter your name at birth if different from item 2(a).
3. to 5. Birth, death and permanent home of the deceased
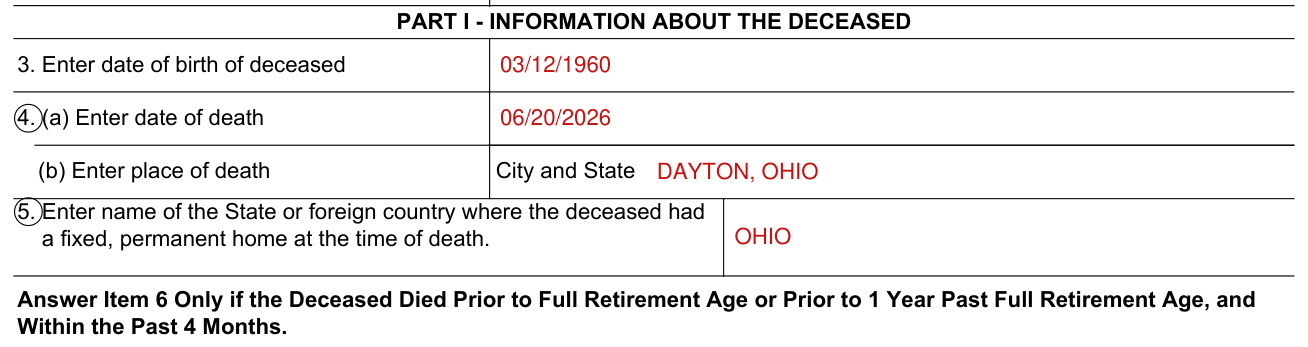
3. Enter date of birth of deceased. 4. (a) Enter date of death. (b) Enter place of death City and State.
5. Enter name of the State or foreign country where the deceased had a fixed, permanent home at the time of death.
6. Was the deceased unable to work

Answer Item 6 Only if the Deceased Died Prior to Full Retirement Age or Prior to 1 Year Past Full Retirement Age, and Within the Past 4 Months. Was the deceased unable to work because of illnesses, injuries, or conditions at the time of death? If "Yes," answer (b): enter the date the deceased became unable to work. If "No," go on to item 7.
More rules for Form SSA-10
Answer item 7 only if death occurred within the last 2 years. In 7(a), enter the Amount: how much the deceased earned from employment and self-employment during the year of death. In 7(b), enter the Amount: how much the deceased earned the year before death.
Did the deceased have wages or self-employment income covered under Social Security in all years from 1978 through last year? If "Yes," skip to item 9. If "No," answer (b): list the years from 1978 through last year in which the deceased did not have wages or self-employment income covered under Social Security.
9. CHECK IF APPLICABLE: I am not submitting evidence of the deceased's earnings that are not yet on his/her earnings record. I understand that these earnings will be included automatically within 24 months, and any increase in my benefits will be paid with full retroactivity.
Is there a surviving parent (or parents) who was receiving support from the deceased at the time of death or at the time the deceased became disabled under Social Security Law? Yes No (If "Yes," enter the name and address in "Remarks.")
Part II - Information about yourself. 12. (a) Enter name of State or foreign country where you were born. Are you a U.S. citizen? Are you an alien lawfully present in the U.S.? If yes, when were you lawfully admitted into the U.S.?
In 14(a), enter information about your marriage to the deceased. If you remarried after the marriage shown in 14.(a), enter information in 14(c). If none, write "NONE".
Complete item 19 only if you are within 3 months of age 65 or older. Do you want to enroll in the Medicare Part B (Medical Insurance)? If this claim is approved and you are still entitled to benefits at age 65, or you are within 3 months of Age 65 or older you could automatically receive Medicare Part A (Hospital Insurance) and Medicare Part B (Medical Insurance) coverage at age 65.
If you live in Puerto Rico or a foreign country, you are not eligible for automatic enrollment in Medicare Part B, and you will need to contact Social Security to request enrollment.
If you are full retirement age or older, go on to item 24. Otherwise, please read carefully the information on page 8 and answer one of the following items. (a) I want benefits beginning with the earliest possible month. (b) I am full retirement age (or will be within 4 months) and I want benefits beginning with the earliest possible month, providing that there is no permanent reduction in my ongoing monthly benefits. (c) I want benefits beginning with the month you enter. I understand that either a higher initial payment or a higher continuing monthly benefit amount may be possible, but I choose not to take it.
Answer question 25 only if you are now at least age 61 years, 8 months. Do you wish this application to be considered an application for retirement benefits on your own earnings record? Yes No
Use Remarks for any explanations. If you need more space, attach a separate sheet. Enter Residence Address in "Remarks," if different.
Enter the Date (MM/DD/YYYY).
Witnesses are required ONLY if this application has been signed by mark (X). If signed by mark (X), two witnesses to the signing who know the applicant must sign: 1. Signature of Witness; 2. Signature of Witness, giving their full addresses. Also, print the applicant's name in the Signature block.
Failure to report may result in overpayments that must be repaid, and in possible monetary penalties. For those under full retirement age, the law requires that a report of earnings be filed with SSA within 3 months and 15 days after the end of any taxable year in which you earn more than the annual exempt amount.
Common questions about Form SSA-10
Who signs it?
SIGNATURE OF APPLICANT: Signature (First name, middle initial, last name) (Write in ink).
Is there a penalty?
Anyone who knowingly gives a false or misleading statement about a material fact in this information, or causes someone else to do so, commits a crime and may be subject to fine or imprisonment, or both.
What am I certifying when I sign?
"I declare under penalty of perjury that I have examined all the information on this form, and on any accompanying statements or forms, and it is true and correct to the best of my knowledge."
Sources
[1] Form SSA-10 (08-2026), Application for Social Security Benefits, Social Security Administration (the Official source link on this page).
