


Form DHS 1128 at a glance
What it is: DHS 1128 is the Disability Report of the State of Hawaii Med-QUEST Division, Department of Human Services.
Who signs: Print or type the Name and sign the Signature of the Licensed Treating Physician/Evaluator. The App./Ben. or Authorized Representative signs the Signature and enters the Date.
A filled-in Form DHS 1128 example: a physician reports a lasting disability

How to fill out Form DHS 1128, box by box
Name, DOB and Sex

Enter the Name (Last, First, MI), the DOB (Mo, Day, Yr) and the Sex.
Licensed treating physician or evaluator: questions must be answered completely and legibly, or the form may be returned.
Illnesses, accidents, deformities, injuries and surgeries

Describe all significant physical and mental illnesses, accidents, deformities, injuries, illnesses and surgeries related to your patients disability. Specify date(s) applicable to condition(s) listed and attach copies of all related reports.
Current diagnoses

Under Current diagnoses, list primary diagnosis first.
Treatment plan and duration of treatment

Indicate your treatment plan and duration of treatment.
Explain in detail

Base your decision on medical evidence and not on subjective judgment. Attach copies of all medical evidence to this report.
Is expected to be

It is expected to be PERMANENT, AT LEAST 12 MONTHS with RE-EVALUATION NEEDED (MO/YR), or TEMPORARY TO (MO/YR).
Licensed Treating Physician/Evaluator
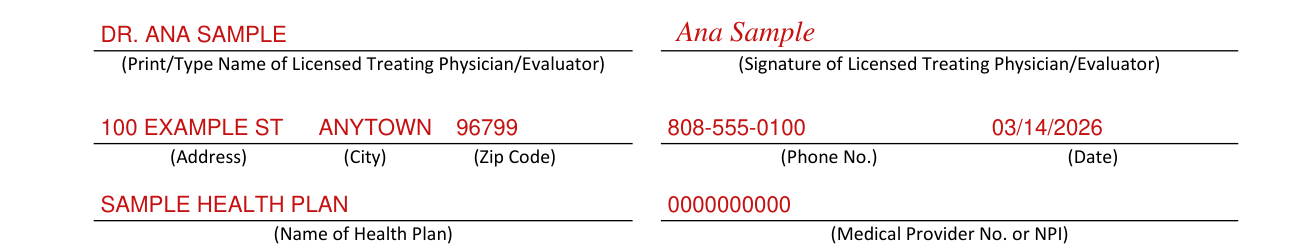
Print or type the Name and sign the Signature of the Licensed Treating Physician/Evaluator.
Under the Licensed Treating Physician/Evaluator, enter the Address, City, Zip Code, Phone No., Date, Name of Health Plan and Medical Provider No. or NPI.
Patient Acknowledgement

Under Patient Acknowledgement, print or type the Name of the Applicant/Beneficiary and the Contact Number.
The App./Ben. or Authorized Representative signs the Signature and enters the Date.
If the Applicant/Beneficiary or Authorized Representative does not sign, indicate the reason under Patient Acknowledgement.
Sources
[1] Form DHS 1128 (Rev. 10/2022), Disability Report, State of Hawaii Med-QUEST Division (the Official source link on this page).