
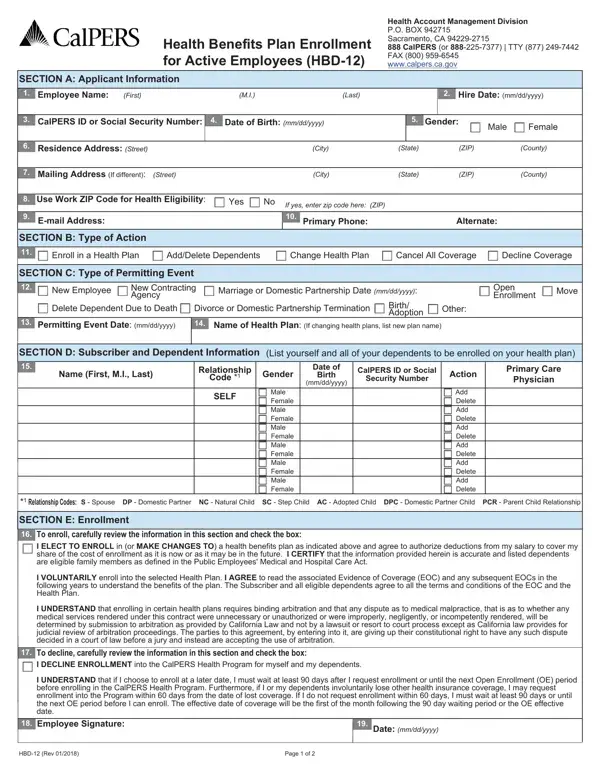
Form HBD-12 at a glance
What it is: HBD-12 is the CalPERS Health Benefits Plan Enrollment for Active Employees.
Who signs: Sign on the Employee Signature line.
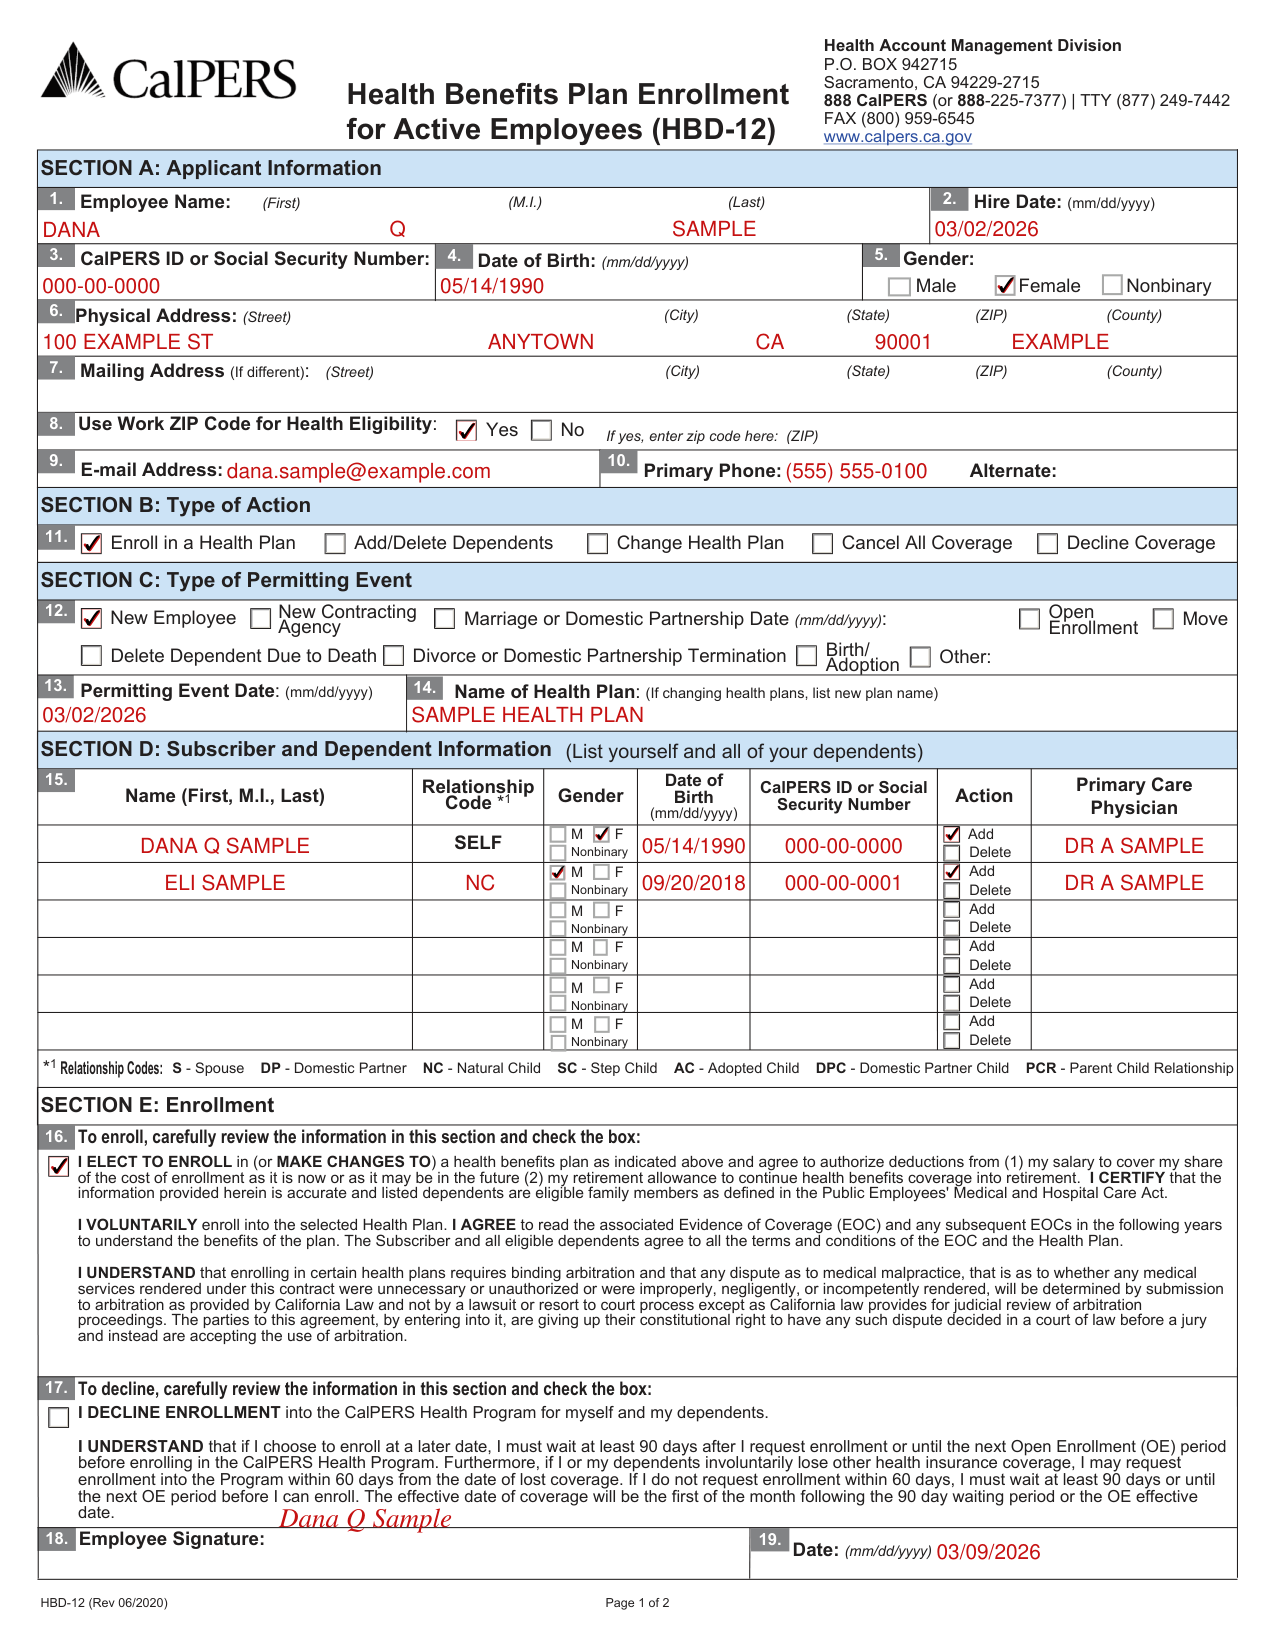
A filled-in Form HBD-12 example: a new employee enrolls with her son
How to fill out Form HBD-12, box by box
Section A: Applicant Information
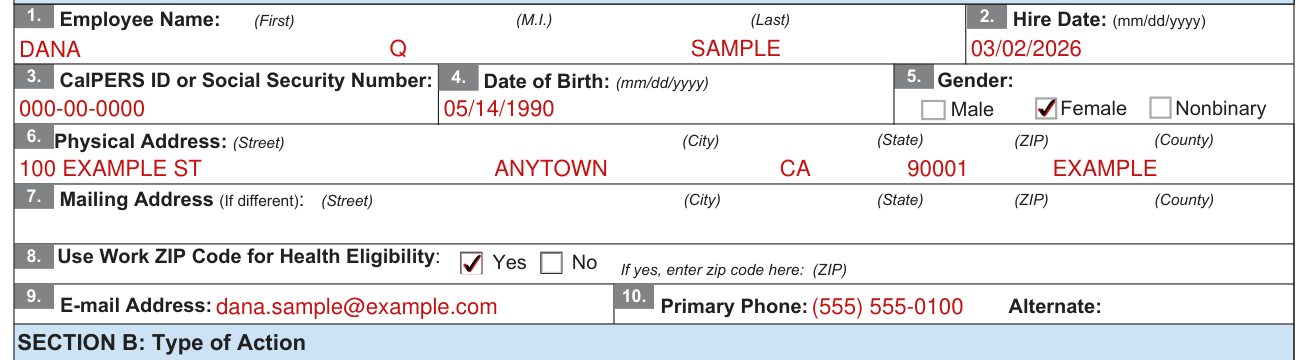
In Section A: Applicant Information, enter the Employee Name: First, M.I. and Last.
Enter the Hire Date as mm/dd/yyyy.
Enter the Date of Birth as mm/dd/yyyy and the CalPERS ID or Social Security Number.
For Gender, check Male, Female or Nonbinary.
For the Physical Address, enter the Street, City, State, ZIP and County.
For the Mailing Address (If different), enter the Street, City, State, ZIP and County.
Check No or Yes for Use Work ZIP Code for Health Eligibility. If yes, enter zip code here.
Enter the E-mail Address, the Primary Phone and the Alternate.
Section B: Type of Action

In Section B: Type of Action, check Decline Coverage, Cancel All Coverage, Change Health Plan, Add/Delete Dependents or Enroll in a Health Plan.
Section C: Type of Permitting Event

In Section C: Type of Permitting Event, check New Contracting Agency, Open Enrollment, New Employee, Marriage or Domestic Partnership with its Date (mm/dd/yyyy), Move, Delete Dependent Due to Death, Divorce or Domestic Partnership Termination, Birth/ Adoption or Other.
Enter the Name of Health Plan: (If changing health plans, list new plan name).
Enter the Permitting Event Date: (mm/dd/yyyy).
Section D: Subscriber and Dependent Information
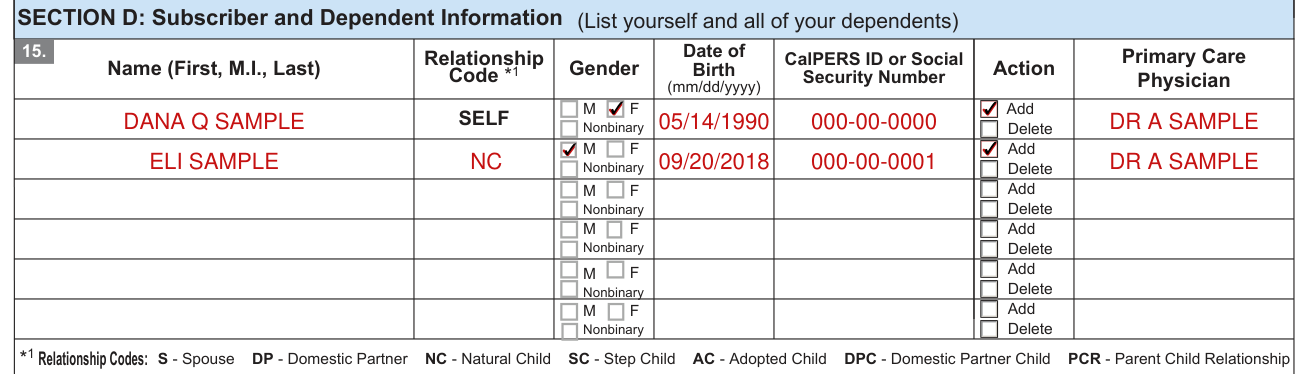
In Section D: Subscriber and Dependent Information, (List yourself and all of your dependents). For each, enter the Name (First, M.I., Last), CalPERS ID or Social Security Number, Date of Birth (mm/dd/yyyy), Gender and Action.
For Action, check Delete or Add. Enter the Primary Care Physician and the Relationship Code.
Relationship Codes: S - Spouse, DP - Domestic Partner, NC - Natural Child, SC - Step Child, AC - Adopted Child, DPC - Domestic Partner Child, PCR - Parent Child Relationship.
Section E: Enrollment
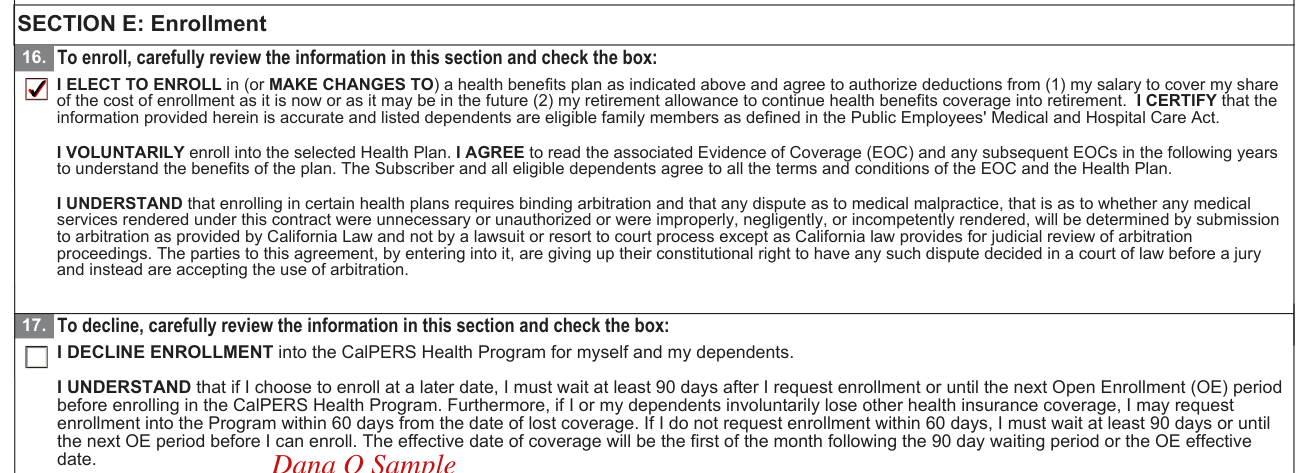
To enroll, carefully review the information in Section E: Enrollment and check the box.
By checking the box you elect to enroll in (or make changes to) a health benefits plan and agree to authorize deductions from (1) your salary to cover your share of the cost of enrollment as it is now or as it may be in the future (2) your retirement allowance to continue health benefits coverage into retirement. You certify that the information provided herein is accurate and listed dependents are eligible family members as defined in the Public Employees' Medical and Hospital Care Act.
You voluntarily enroll into the selected Health Plan and agree to read the associated Evidence of Coverage (EOC) and any subsequent EOCs in the following years to understand the benefits of the plan.
To decline, carefully review the information and check the box for I DECLINE ENROLLMENT into the CalPERS Health Program for myself and my dependents.
If you choose to enroll at a later date, you must wait at least 90 days after you request enrollment or until the next Open Enrollment (OE) period before enrolling in the CalPERS Health Program. If you or your dependents involuntarily lose other health insurance coverage, you may request enrollment into the Program within 60 days from the date of lost coverage. If you do not request enrollment within 60 days, you must wait at least 90 days or until the next OE period before you can enroll. The effective date of coverage will be the first of the month following the 90 day waiting period or the OE effective date.
Date

Enter the Employee Signature Date (mm/dd/yyyy).
More rules for Form HBD-12
It is your responsibility to notify your personnel office when there are any changes in your family situation. Changes include domestic partnership termination, establishment of a parent-child relationship, acquisition of a dependent child, change of address, marriage, divorce, legal separation, and death.
Failure to notify your personnel office may result in adverse consequences.
In Section H: For Employer Use, retain original signed form and all supporting documentation or affidavits in employee file. DO NOT send to CalPERS.
Sources
[1] Form HBD-12 (Rev 06/2020), Health Benefits Plan Enrollment for Active Employees, CalPERS (the Official source link on this page).