

Home Health Medical Records Audit Form at a glance
What it is: Home Health Medical Records Audit Form (Updated for CY2013).
Who signs: The following is applicable for Quarterly Medical Review Report: reviewed and signed by the following Disciplinary Representative: Registered Nurse Occupational Therapist (If Applicable) Physical Therapist (If Applicable) Speech Language Pathologist (If Applicable) Medical Director MSW (If Applicable).
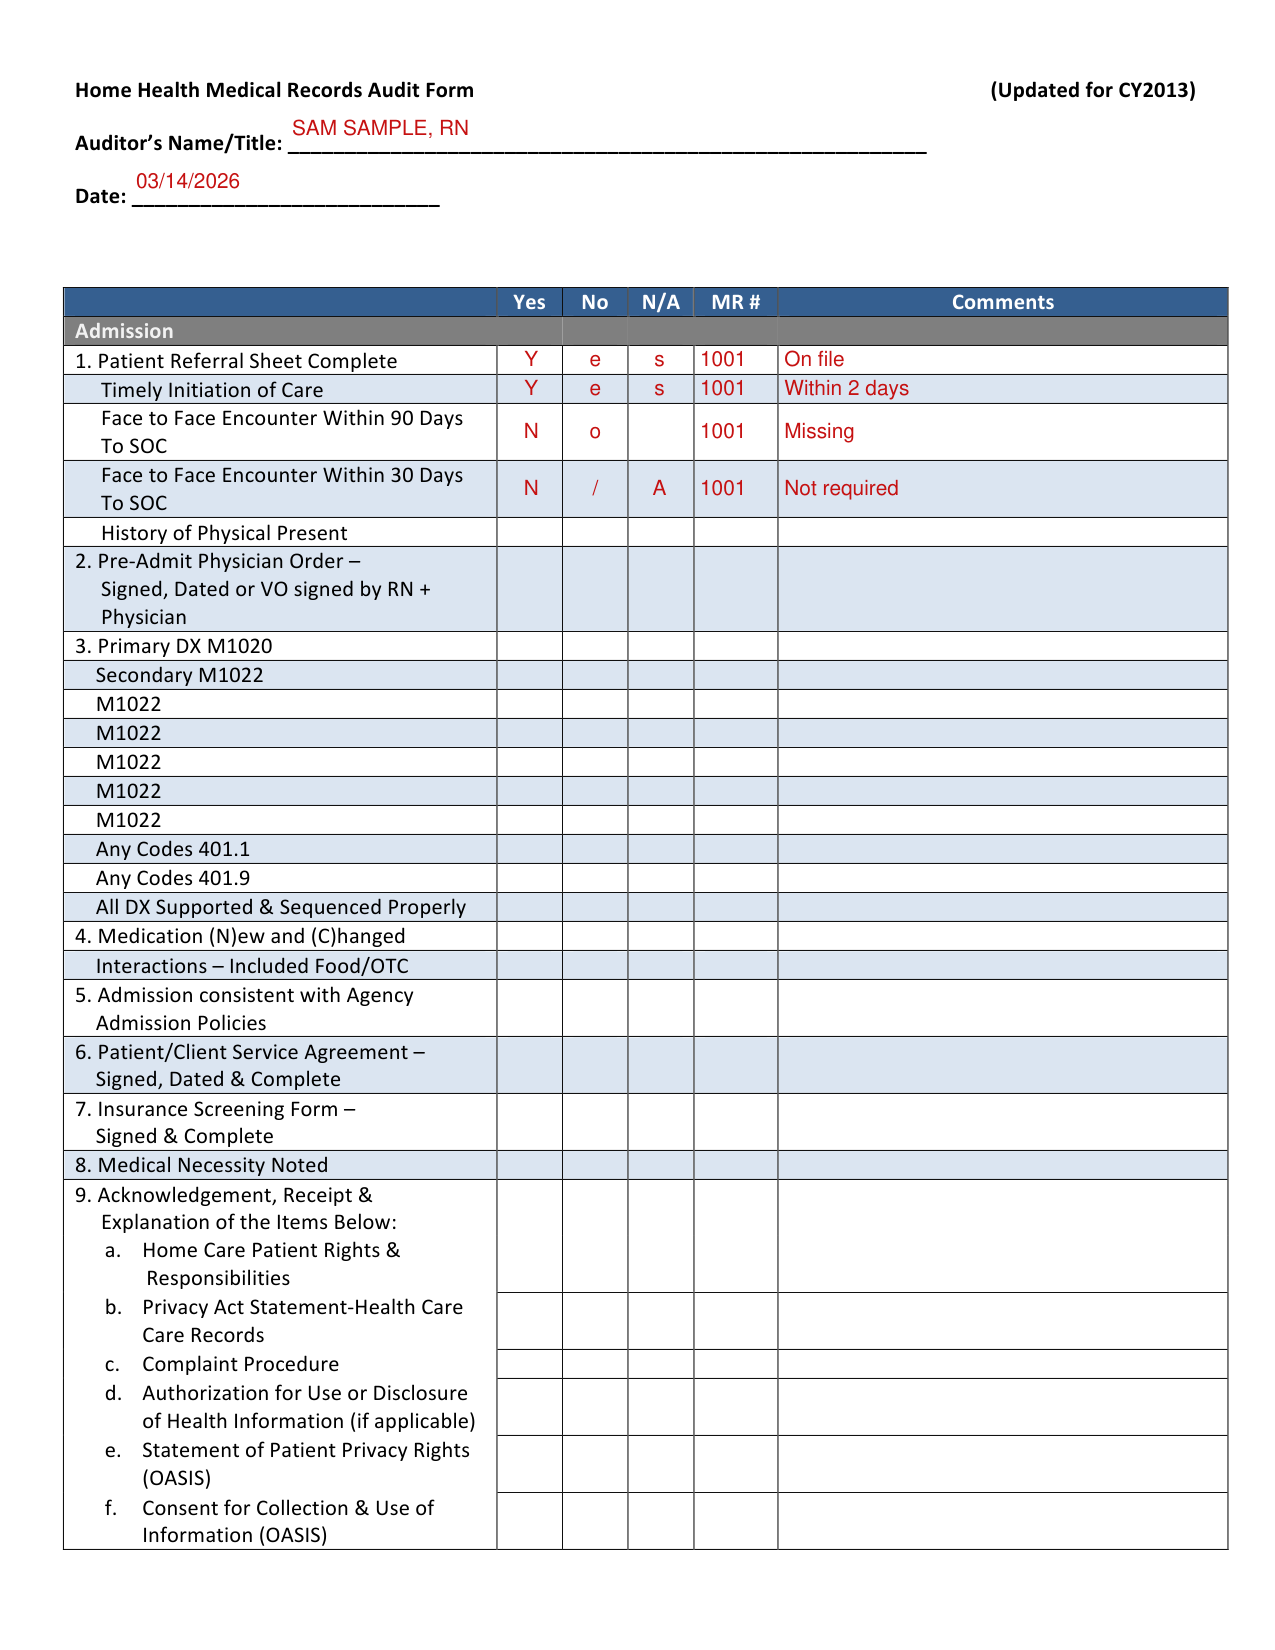
A filled-in Home Health Medical Records Audit Form example: an auditor checks the first admission lines
How to fill out Home Health Medical Records Audit Form, box by box
Auditor's Name/Title and Date

Enter the Auditor's Name/Title and the Date.
Admission
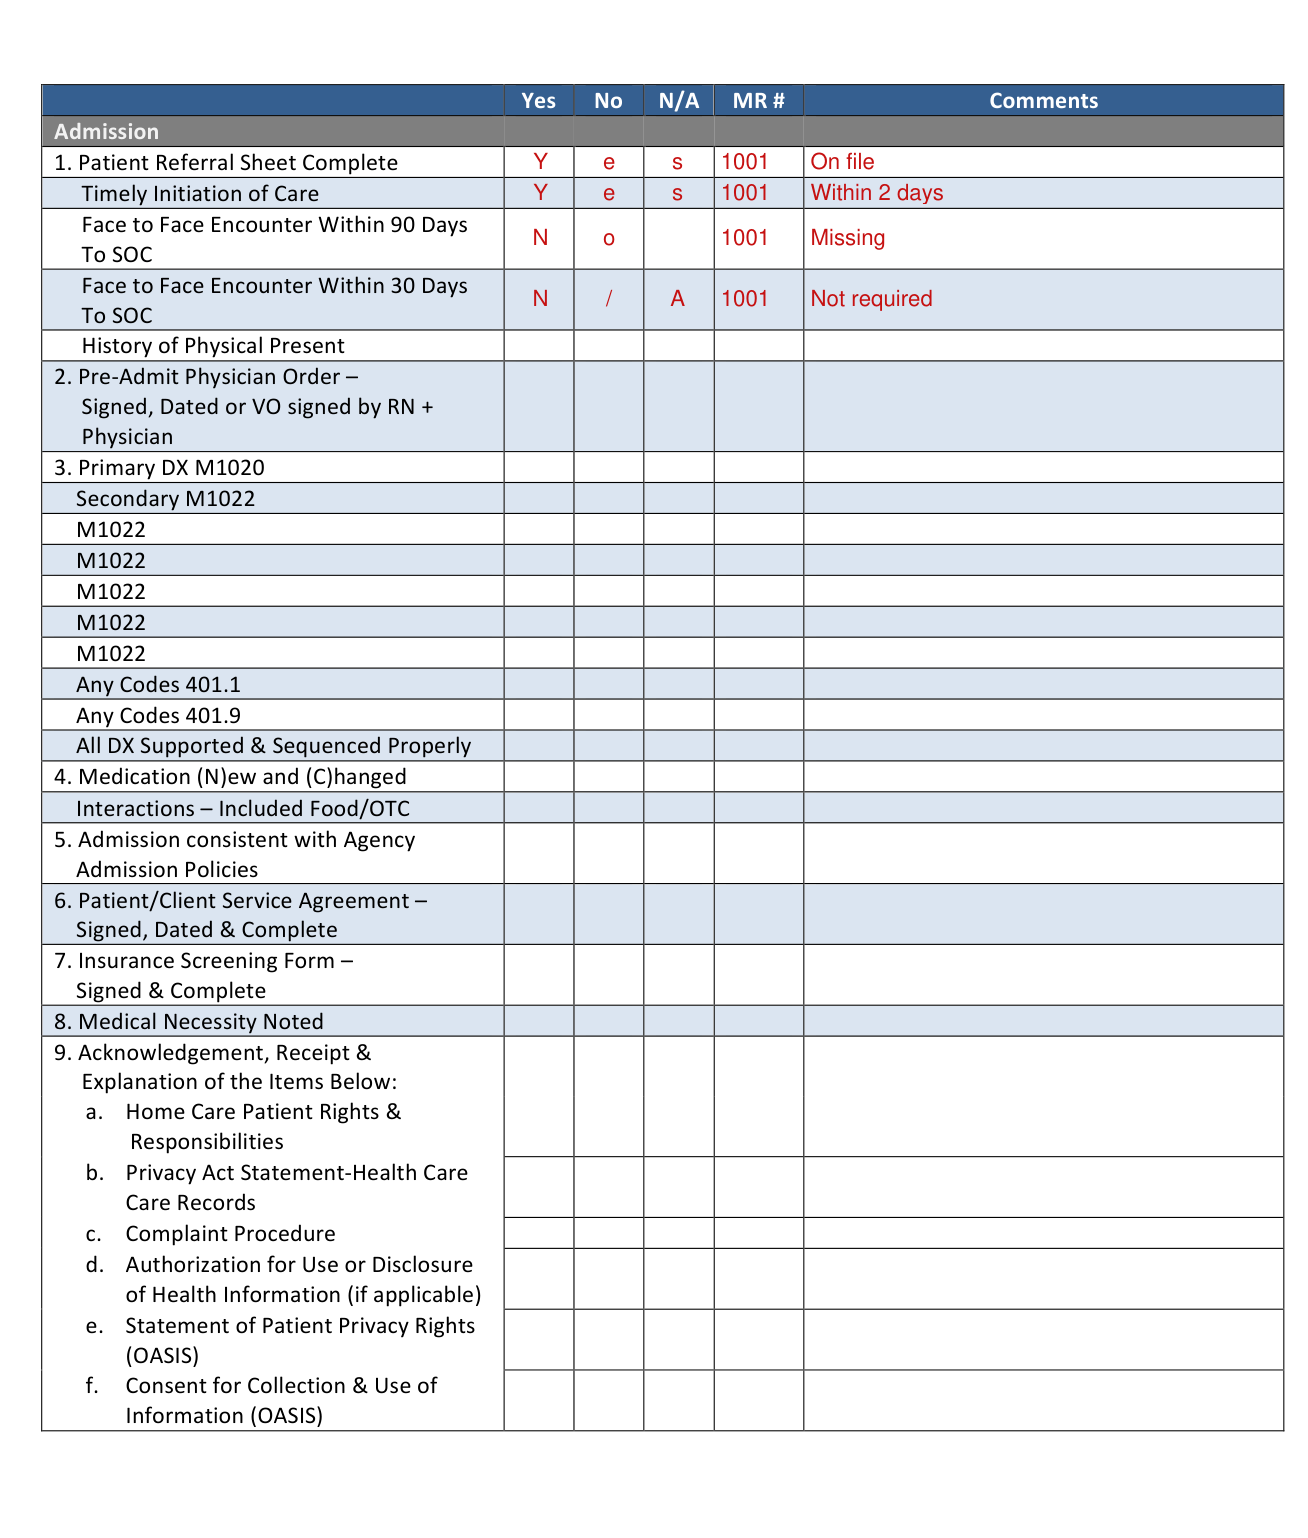
For each of these, fill in Yes, No or N/A, MR # and Comments for: Admission 1. Patient Referral Sheet Complete Timely Initiation of Care Face to Face Encounter Within 90 Days To SOC Face to Face Encounter Within 30 Days To SOC History of Physical Present 2. Pre‐Admit Physician Order - Signed, Dated or VO signed by RN + Physician 3. Primary DX M1020 Secondary M1022 M1022 M1022 M1022 M1022 M1022 Any Codes 401.1 Any Codes 401.9 All DX Supported & Sequenced Properly 4. Medication (N)ew and (C)hanged Interactions - Included Food/OTC 5. Admission consistent with Agency Admission Policies 6. Patient/Client Service Agreement - Signed, Dated & Complete 7. Insurance Screening Form - Signed & Complete 8. Medical Necessity Noted 9. Acknowledgement, Receipt & Explanation of the Items: a. Home Care Patient Rights & Responsibilities b. Privacy Act Statement‐Health Care Care Records c. Complaint Procedured. Authorization for Use or Disclosure of Health Information (if applicable) e. Statement of Patient Privacy Rights (OASIS) f. Consent for Collection & Use of Information (OASIS).
Plan of Care
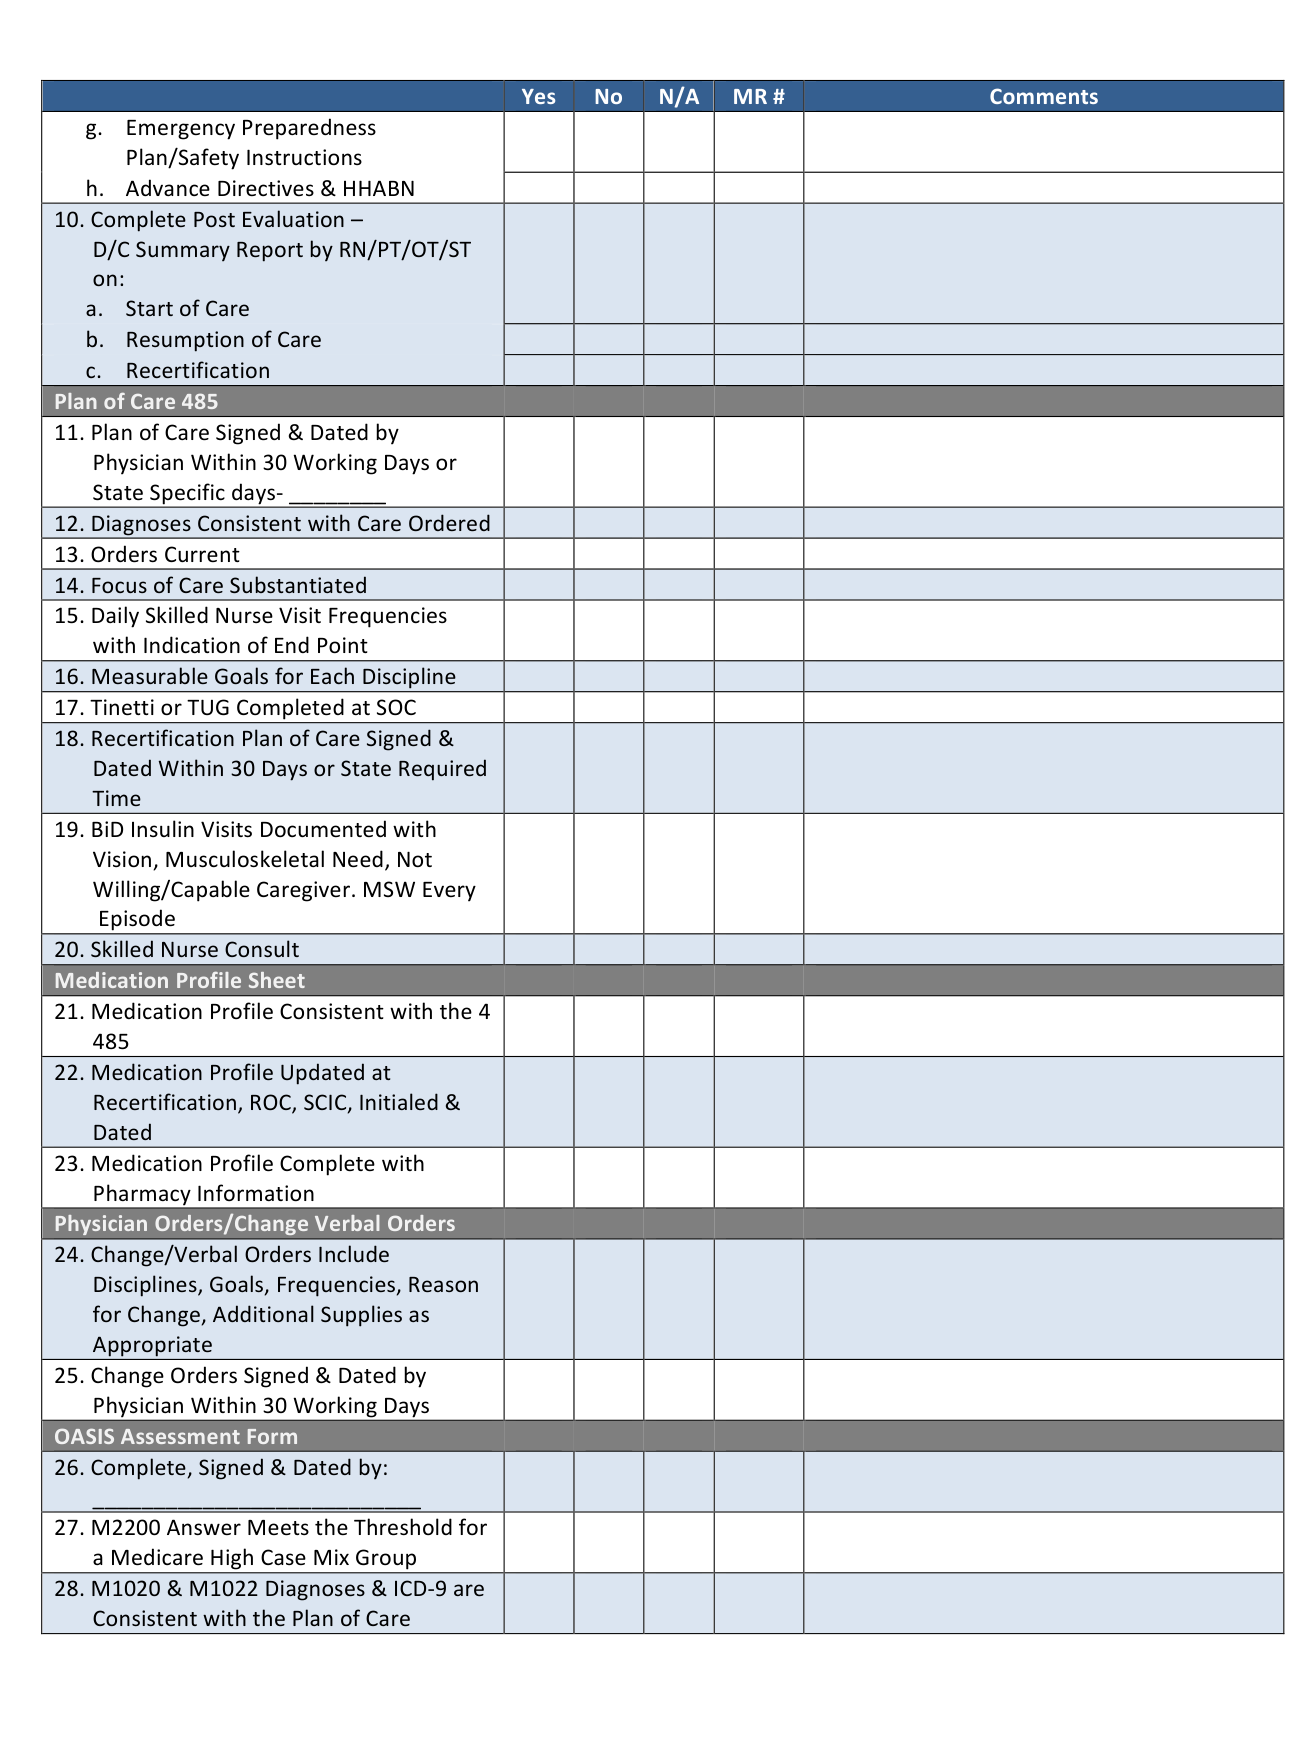
Complete Yes, No or N/A, MR # and Comments for: g. Emergency Preparedness Plan/Safety Instructions h. Advance Directives & HHABN 10. Complete Post Evaluation - D/C Summary Report by RN/PT/OT/ST on: a. Start of Care b. Resumption of Care c. Recertification Plan of Care 485 11. Plan of Care Signed & Dated by Physician Within 30 Working Days or State Specific days‐ 12. Diagnoses Consistent with Care Ordered 13. Orders Current 14. Focus of Care Substantiated 15. Daily Skilled Nurse Visit Frequencies with Indication of End Point 16. Measurable Goals for Each Discipline 17. Tinetti or TUG Completed at SOC 18. Recertification Plan of Care Signed & Dated Within 30 Days or State Required Time 19. BiD Insulin Visits Documented with Vision, Musculoskeletal Need, Not Willing/Capable Caregiver. MSW Every Episode 20. Skilled Nurse Consult Medication Profile Sheet 21. Medication Profile Consistent with the 4 485 22. Medication Profile Updated at Recertification, ROC, SCIC, Initialed & Dated 23. Medication Profile Complete with Pharmacy Information Physician Orders/Change Verbal Orders 24. Change/Verbal Orders Include Disciplines, Goals, Frequencies, Reason for Change, Additional Supplies as Appropriate 25. Change Orders Signed & Dated by Physician Within 30 Working Days OASIS Assessment Form 26. Complete, Signed & Dated by: 27. M2200 Answer Meets the Threshold for a Medicare High Case Mix Group 28. M1020 & M1022 Diagnoses & ICD‐9 are Consistent with the Plan of Care.
Skilled Nursing Clinical Notes

Enter Yes, No or N/A, MR # and Comments for: 29. All OASIS Assessments Were Exported Within 30 Days 30. OASIS Recertifications Were Done Within 5 Days of the End of the Episode 31. All OASIS Were Reviewed for Consistency in Coordination with the Discipline Who Completed the Form Skilled Nursing Clinical Notes 32. Visit Frequencies & Duration are Consistent with Physician Orders 33. Orders Written for Visit Frequencies/ Treatment Change 34. Homebound Status Supported on Each Visit Note 35. Measurable Goals for Each Discipline with Specific Time Frames 36. Frequency of Visits Appropriate for Patient's Needs & Interventions Provided 37. Appropriate Missed Visit (MV) Notes 38. Skilled Care Evident on Each Note 39. Evidence of Coordination of Care 40. Every Note Signed & Dated 41. Follows the Plan of Care (485) 42. Weekly Wound Reports are Completed 43. Missed Visit Reports are Completed 44. Pain Assessment Done Every Visit with Intervention (If Applicable) 45. Abnormal Vital Signs Reported to Physician & Case Managers 46. Evidence of Interventions with Abnormal Parameters/Findings 47. Skilled Nurse Discharge Summary/ Instructions Completed 48. LVN Supervisory Visit Every 30 Days by Registered Nurse Certified Home Health Aide 49. Visit Frequencies & Duration Consistent with Physician Orders 50. Personal Care Instructions Documented, Signed & Dated 51. Personal Care Instructions Modified as Appropriate 52. Notes Consistent with Personal Care Instructions Noted on the CHHA Assignment Sheet Completed by the RN/PT/ST/OT 53. Notes Reflect Supervisor Notification of Patient Complications or Changes 54. Visit Frequencies Appropriate for Patient Needs.
Visit Notes for PT and SLP

Fill in Yes, No or N/A, MR # and Comments for: 55. Each Note Reflects Personal Care Given 56. Supervisory Visits at Least Every 14 Days by RN or PT 57. Every Note Signed & Dated PT 58. Assessment Includes Evaluation, Care Plan & Visit Note 59. Evaluation Done Within 48 Hours of Referral Physician Order or Date Ordered 60. Visit Frequencies/Duration Consistent with Physician Orders 61. Evidence of Need for Therapy/Social Service 62. Appropriate Missed Visit (MV) Notes 63. Notes Consistent with Physician Orders 64. Evidence of Skilled Service(s) Provided in Each Note 65. Treatment/Services Provided Consistent with Physician Orders & Care Plan 66. Notes Reflect Supervisor & Physician Notification of Patient Complications or Changes 67. Specific Evaluation & “Treat” Orders Prior to Care 68. Verbal Orders for “Treat” Orders Prior to Care 69. Homebound Status Validated in Each Visit Note 70. Notes Reflect Progress Toward Goals 71. Evidence of Discharge Planning 72. Evidence of Therapy Home Exercise Program 73. Discharge/Transfer Summary Complete with Goals Met/Unmet 74. Assessment & Evaluation performed by Qualified Therapist Every 30 Days 75. Supervision of PTA/OTA at Least Every 2 Weeks 76. Qualified Therapy Visit 13th Visit (11, 12, 13) 77. Qualified Therapy Visit 19th Visit (17, 18, 19) 78. Every Visit Note Signed & Dated SLP 79. Assessment Includes Evaluation, Care Plan & Visit Note 80. Evaluation Done Within 48 Hours of Referral Physician Order or Date Ordered 81. Visit Frequencies/Duration Consistent with Physician Orders.
Miscellaneous
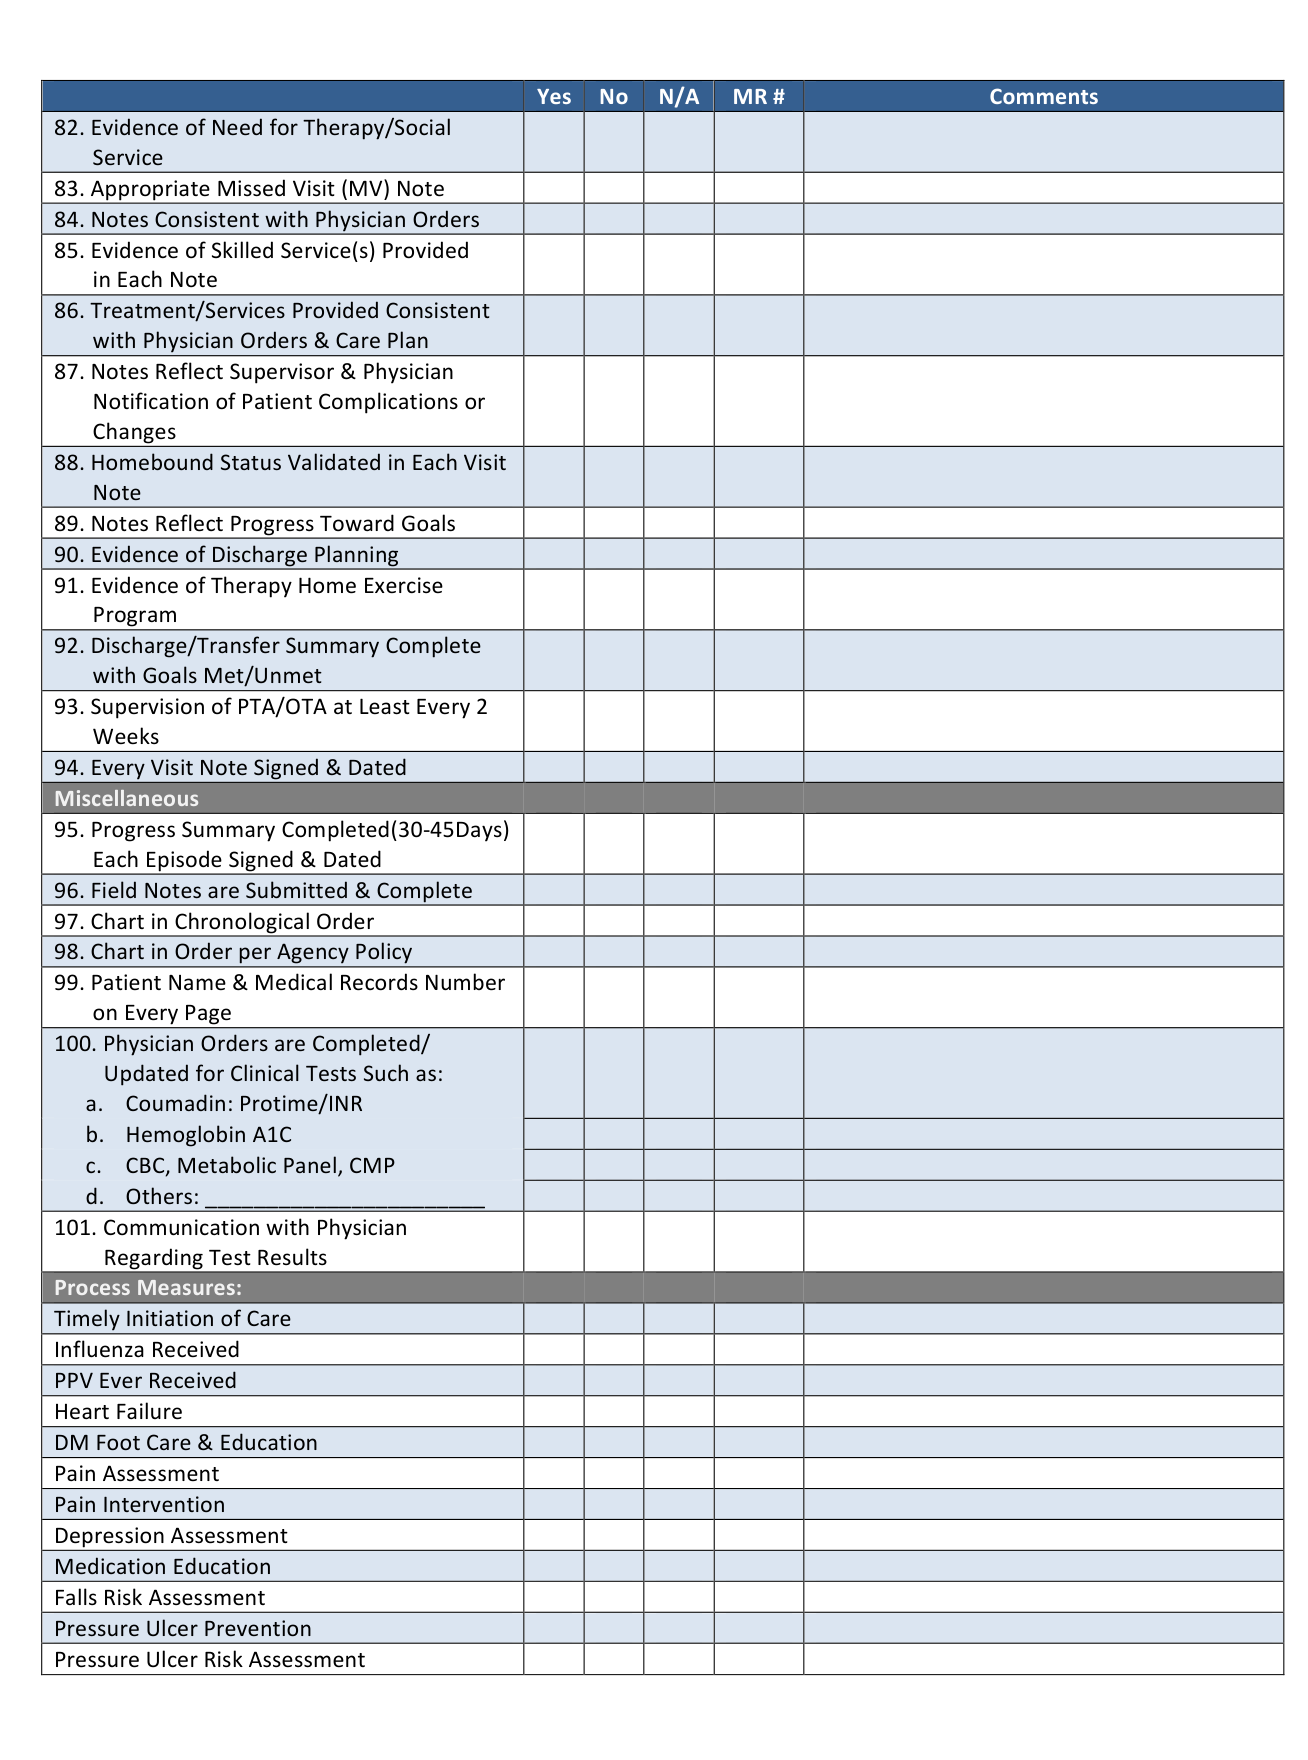
For these, enter Yes, No or N/A, MR # and Comments for: 82. Evidence of Need for Therapy/Social Service 83. Appropriate Missed Visit (MV) Note 84. Notes Consistent with Physician Orders 85. Evidence of Skilled Service(s) Provided in Each Note 86. Treatment/Services Provided Consistent with Physician Orders & Care Plan 87. Notes Reflect Supervisor & Physician Notification of Patient Complications or Changes 88. Homebound Status Validated in Each Visit Note 89. Notes Reflect Progress Toward Goals 90. Evidence of Discharge Planning 91. Evidence of Therapy Home Exercise Program 92. Discharge/Transfer Summary Complete with Goals Met/Unmet 93. Supervision of PTA/OTA at Least Every 2 Weeks 94. Every Visit Note Signed & Dated Miscellaneous 95. Progress Summary Completed(30‐45Days) Each Episode Signed & Dated 96. Field Notes are Submitted & Complete 97. Chart in Chronological Order 98. Chart in Order per Agency Policy 99. Patient Name & Medical Records Number on Every Page 100. Physician Orders are Completed/ Updated for Clinical Tests Such as: a. Coumadin: Protime/INR b. Hemoglobin A1C c. CBC, Metabolic Panel, CMP d. Others: 101. Communication with Physician Regarding Test Results Process Measures: Timely Initiation of Care Influenza Received PPV Ever Received Heart Failure DM Foot Care & Education Pain Assessment Pain Intervention Depression Assessment Medication Education Falls Risk Assessment Pressure Ulcer Prevention Pressure Ulcer Risk Assessment.
Additional Comments/Recommendations

Write Additional Comments/Recommendations only if there are any.
Sources
[1] Home Health Medical Records Audit Form (Updated for CY2013) (the Official source link on this page).
