

Illinois Medicaid Redetermination (Medical Renewal Form) at a glance
What it is: Illinois Medicaid Redetermination is the Medical Renewal Form of the State of Illinois Department of Healthcare and Family Services and Department of Human Services: it is time to renew your medical coverage.
Who signs: Write Your signature and Today's date.
It is time to renew your medical coverage.
What to bring and attach to Illinois Medicaid Redetermination (Medical Renewal Form)
Attach all proofs of income and expenses and other proofs.
A filled-in Illinois Medicaid Redetermination (Medical Renewal Form) example: a renewal with student loan interest

How to fill out Illinois Medicaid Redetermination (Medical Renewal Form), box by box
Do these people still live with you?
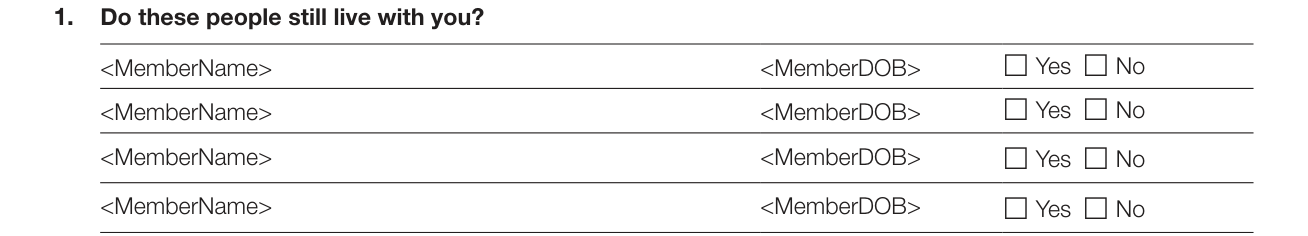
Do these people still live with you? For each one, check Yes or No.
Tell us about anyone else who lives with you
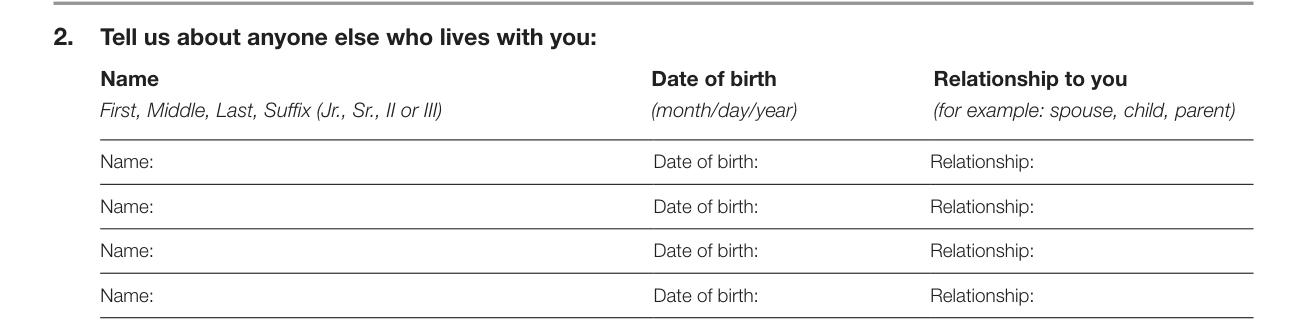
Write about anyone else who lives with you: the Name (First, Middle, Last, Suffix (Jr., Sr., II or III)), the Date of birth (month/day/year) and the Relationship to you (for example: spouse, child, parent).
Is anyone who lives with you pregnant?

Is anyone who lives with you pregnant? If yes, write the name, the Due date and the Expected number of babies.
Did you or anyone living with you get new health insurance in the last year?

Did you or anyone living with you get new health insurance in the last year? Check Yes or No. If yes, write the name of the insurance plan, the Policy number and who is covered by this health insurance.
Will you or anyone who lives with you file a federal income tax return next year
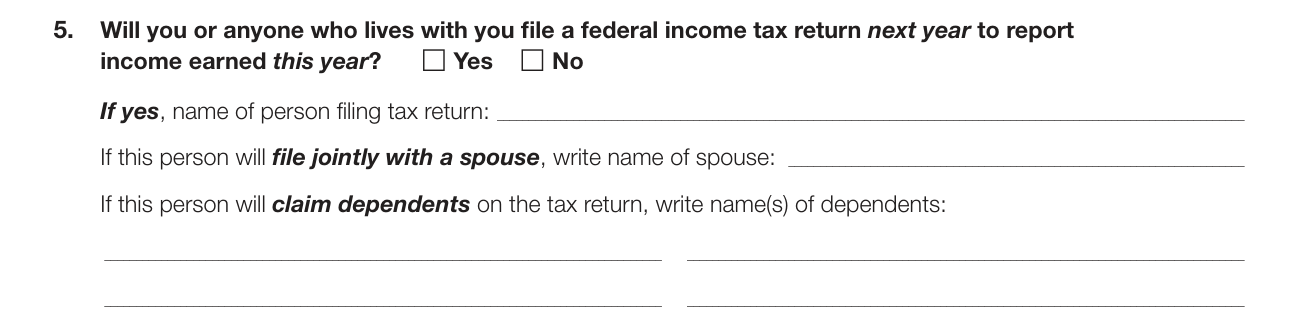
Will you or anyone who lives with you file a federal income tax return next year to report income earned this year? Check Yes or No. If yes, write the name of the person filing tax return.
If this person will file jointly with a spouse, write name of spouse.
If this person will claim dependents on the tax return, write name(s) of dependents.
Can you be claimed as a dependent on anyone's tax return?

Can you be claimed as a dependent on anyone's tax return? Check Yes or No. If yes, write the name of the person and the Relationship to you.
Do you and everyone living with you still get this income from these sources?

Do you and everyone living with you still get this income from these sources? Each one has Total per month and Is this correct? Check Yes or No.
This income is Salary, wages, and tips for everyone (total before taxes are taken out), Self-employment income for everyone (profit once business expenses are paid), Unemployment for everyone, Social Security for everyone, Pension or retirement income for everyone, Spousal support received by everyone, Interest or investment income for everyone, and Rental fees or royalties for everyone. Check Yes or No.
If you checked no for any income, write the correct amount in the next section.
Do you or anyone living with you get other income?
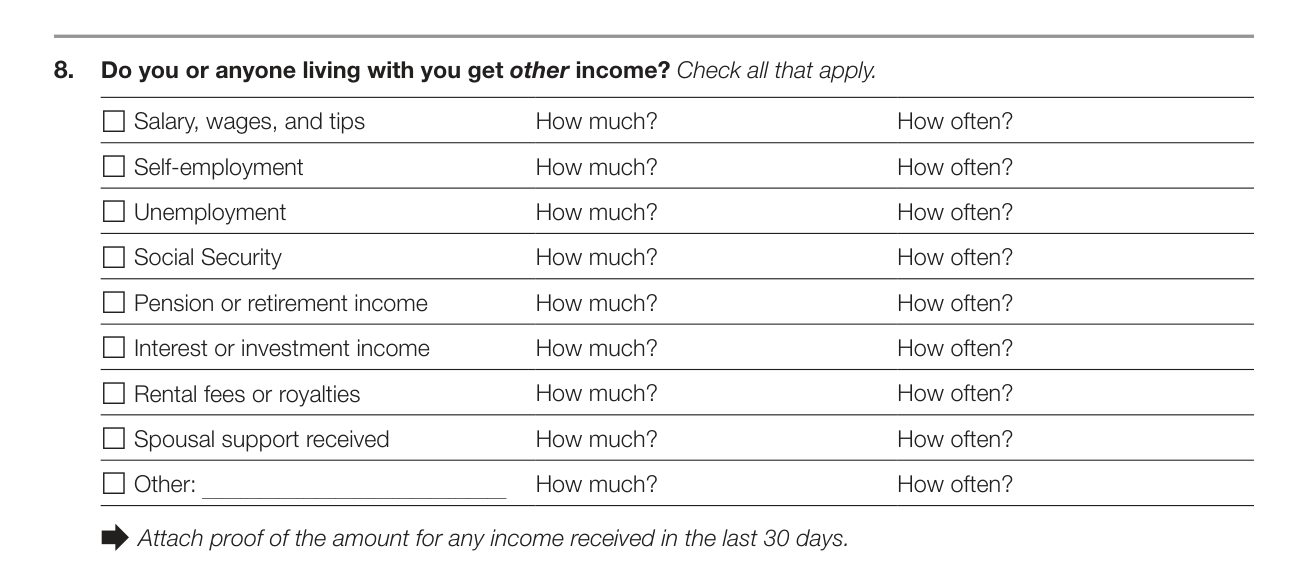
Do you or anyone living with you get other income? Check all that apply.
Salary, wages, and tips, Self-employment, Unemployment, Social Security, Pension or retirement income, Interest or investment income, Rental fees or royalties, Spousal support received, and Other. For each one you check, write How much? and How often?
Attach proof of the amount for any income received in the last 30 days.
Do you or anyone living with you pay any of these expenses?

Do you or anyone living with you pay any of these expenses? Check all that apply.
Spousal support paid to someone else, Student loan interest paid, and Other. For each one you check, write How much? and How often?
Attach proof of all expenses paid in the last 30 days.
We also need these proofs from you

These proofs are also needed from you: Copy of a Social Security card, and Other.
Read and sign below

Read and sign. Officials in charge of your health benefits may check all information on this form, and they may check your information electronically. If they ask for your help checking information, you must cooperate.
Anyone who knowingly lies or provides untrue information, or arranges for someone to knowingly lie or provide untrue information, or intentionally misuses the health benefits card issued by the State of Illinois, may be committing a crime which can be prosecuted or punished under federal law, state law, or both.
If the Illinois Department of Healthcare and Family Services pays medical bills for you, the State of Illinois may collect your medical support payments instead of you.
You are signing this form under the penalty of perjury. That means the information you have provided on this renewal form is true to the best of your knowledge, and you may be punished under law if you provide false or untrue information.
More rules for Illinois Medicaid Redetermination (Medical Renewal Form)
Answer all questions on this form.
Call 1-855-458-4945 (TTY: 1-855-694-5458) if you cannot send everything on time or if you have questions. You may be able to get help with the proofs you need.
The call is free! Monday to Friday from 7 a.m. to 9 p.m. and Saturday from 8 a.m. to 1 p.m. E-mail HFS.medredes@illinois.gov or send a fax to 1-855-394-8066.
Common questions about Illinois Medicaid Redetermination (Medical Renewal Form)
Is there a deadline?
Send your signed form and all proofs by the Due Date. Your medical benefits may end if you do not send your proofs by the Due Date.
Where do I file it?
Send your form and proofs one of these ways: fax to 1-855-394-8066, mail in the envelope sent to you, or e-mail to HFS.medredes@illinois.gov.
Sources
[1] Illinois Medicaid Redetermination, Medical Renewal Form, State of Illinois Department of Healthcare and Family Services and Department of Human Services (the Official source link on this page).