

MAP 351 at a glance
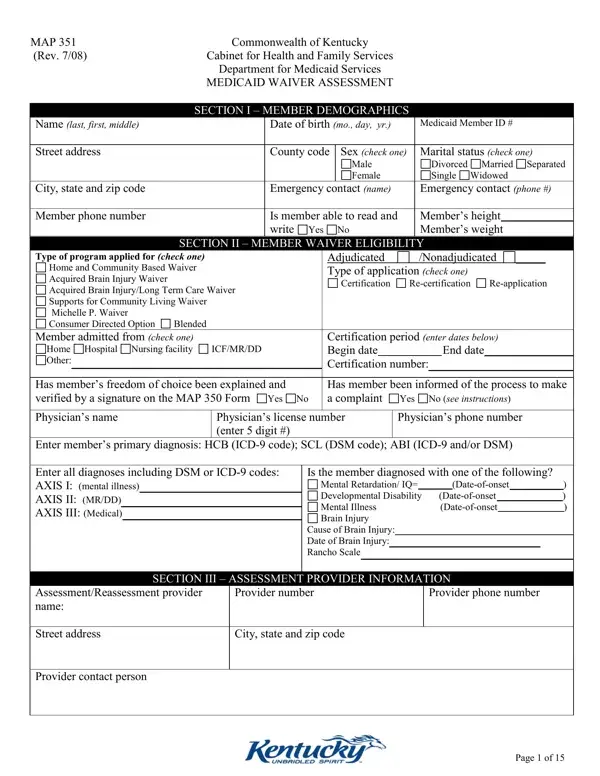
What it is: MAP 351 is the Medicaid Waiver Assessment of the Commonwealth of Kentucky, Cabinet for Health and Family Services, Department for Medicaid Services.
Who signs: Under Signatures, each person performing assessment or reassessment enters Signature, Title and Date.
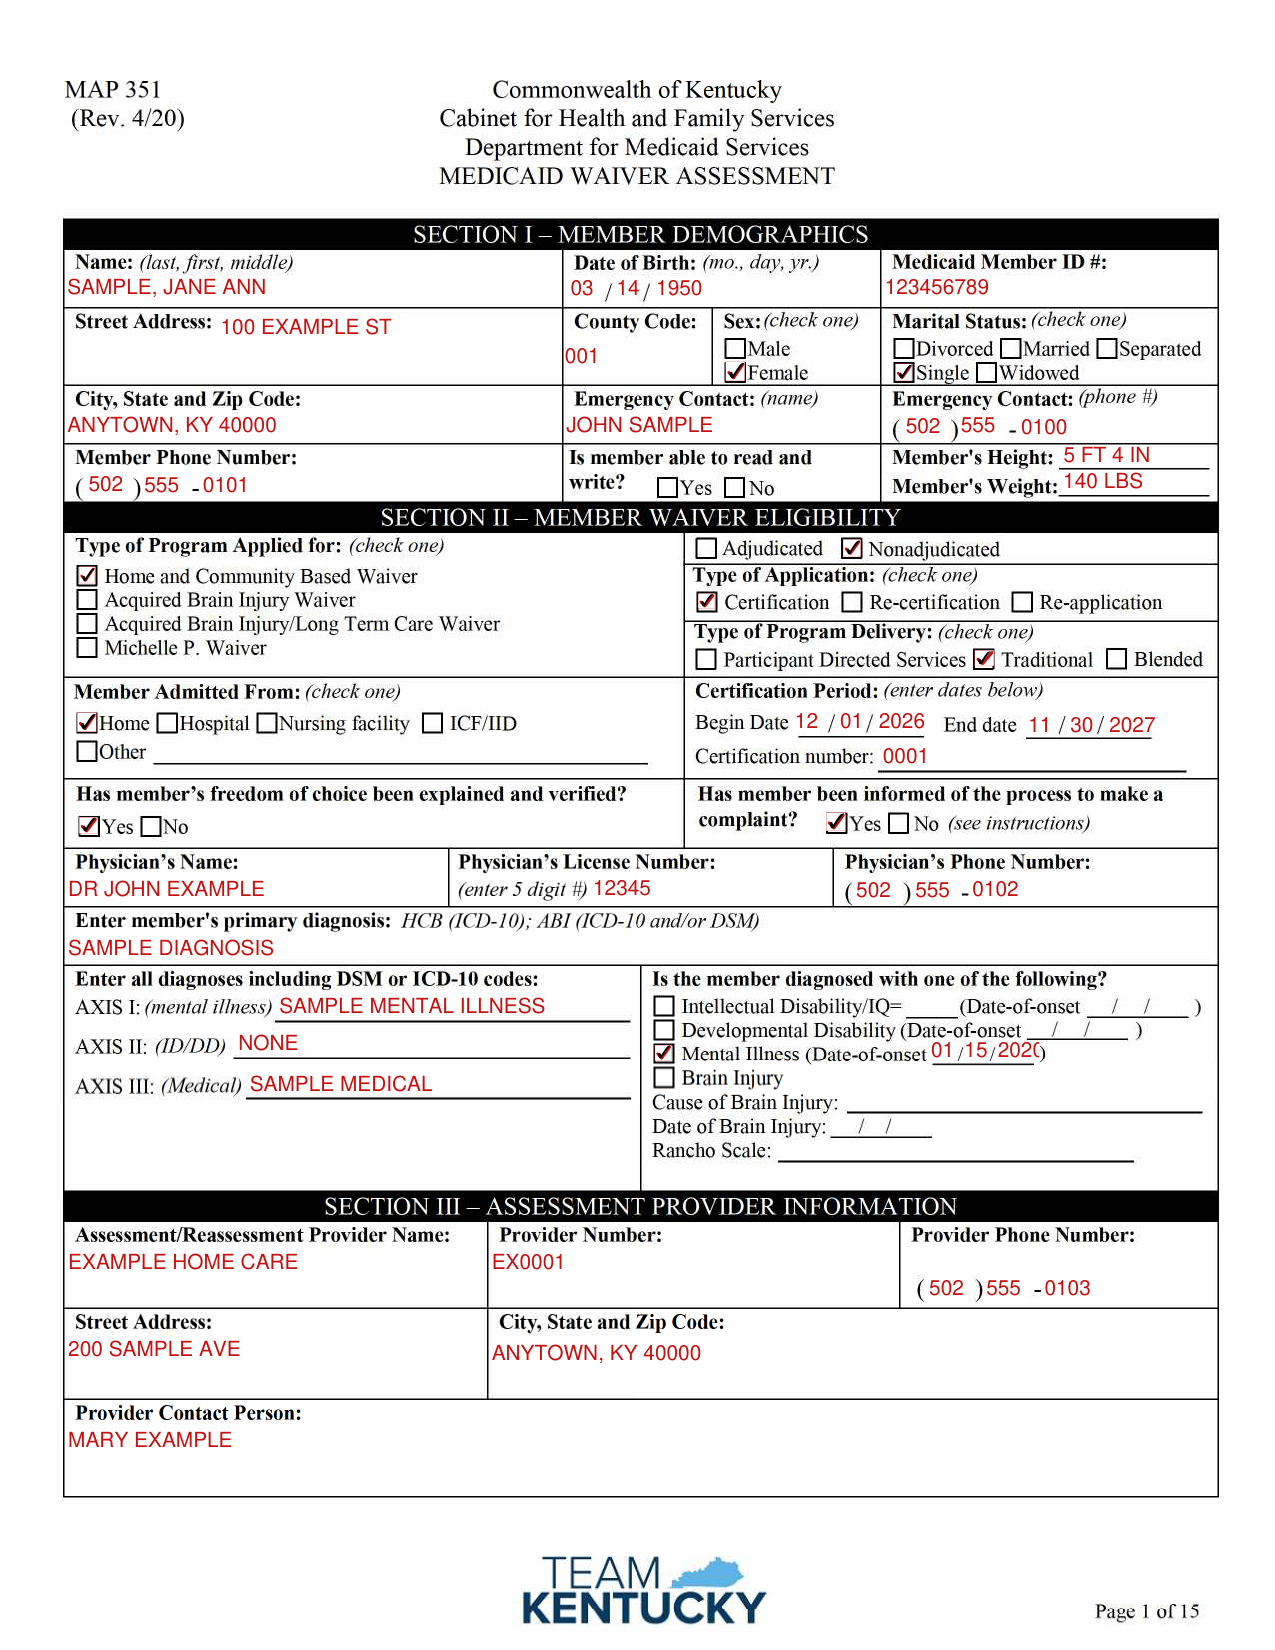
A filled-in MAP 351 example: a first waiver certification
How to fill out MAP 351, box by box
Section I Member demographics
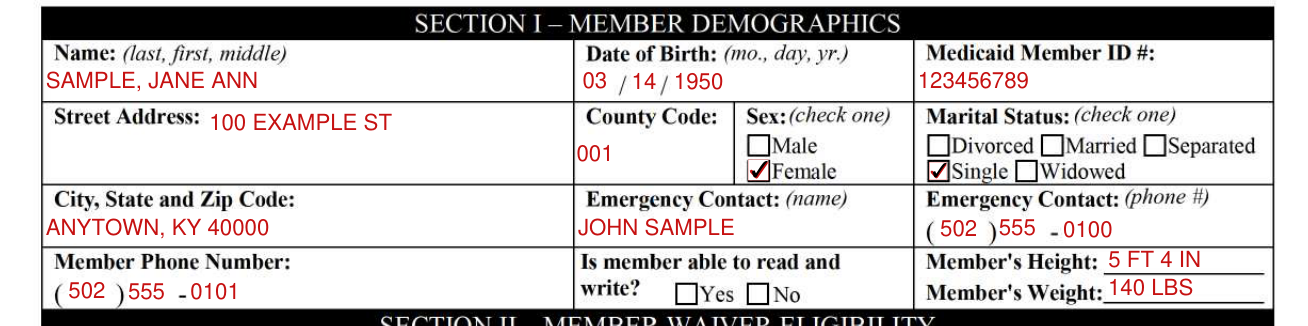
In Section I, Member Demographics, enter the member's Name (last, first, middle), Date of Birth, Medicaid Member ID #, Street Address, County Code, and City, State and Zip Code.
Check one for Sex and check one for Marital Status.
Enter the Emergency Contact name and phone #, the Member Phone Number, and the Member's Height and Weight. Is member able to read and write? Check Yes or No.
Type of Program Applied for
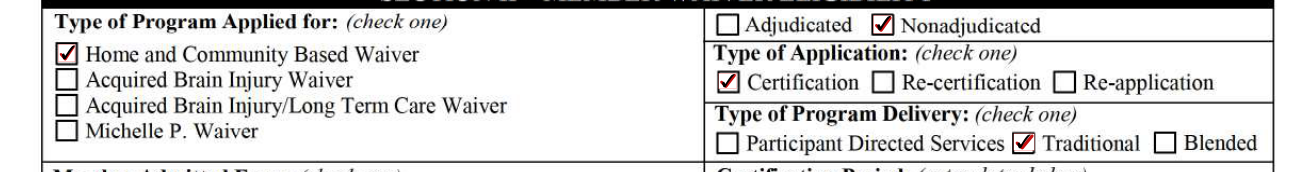
Under Type of Program Applied for, check one: Home and Community Based Waiver, Acquired Brain Injury Waiver, Acquired Brain Injury/Long Term Care Waiver or Michelle P. Waiver.
Check Adjudicated or Nonadjudicated. Under Type of Application, check one: Certification, Re-certification or Re-application. Under Type of Program Delivery, check one: Participant Directed Services, Traditional or Blended.
Member Admitted From and Certification Period

Under Member Admitted From, check one, or check Other.
Under Certification Begin Period, enter dates: the Begin Date and the End date, and the Certification number.
Has member's freedom of choice been explained and verified? Check Yes or No. Has member been informed of the process to make a complaint? Check Yes or No.
Physician and diagnoses
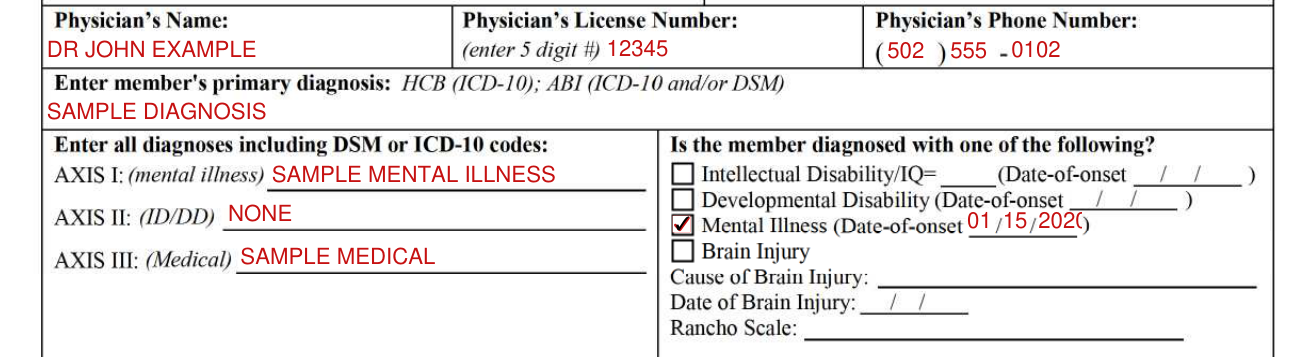
Enter the Physician's Name, Physician's License Number (enter 5 digit #) and Physician's Phone Number.
Enter the member's primary diagnosis: HCB (ICD-10); ABI (ICD-10 and/or DSM). Enter all diagnoses including DSM or ICD-10 codes under AXIS I: (mental illness), AXIS II: (IDIDD) and AXIS III: (Medical).
Check Intellectual Disability/IQ=, Developmental Disability, Mental Illness or Brain Injury for the one the member is diagnosed with, and enter its Date-of-onset; for Brain Injury, enter the Cause of Brain Injury, Date of Brain Injury and Rancho Scale.
Assessment/Reassessment Provider Name
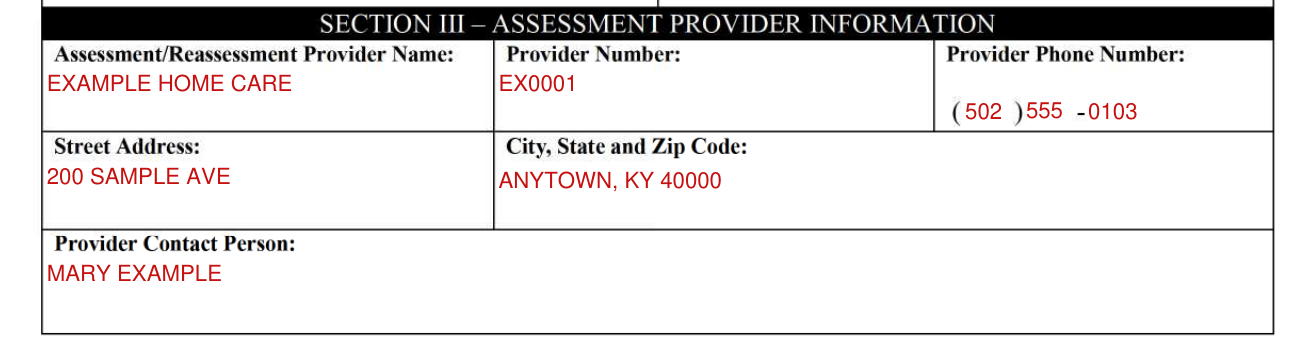
Under Section III, Assessment/Reassessment Provider Name, enter the Provider Number, Provider Phone Number, Street Address, City, State and Zip Code, and Provider Contact Person.
Section IV Self Assessment
Section IV, Self Assessment, is for MP and ABI waivers only; add additional pages as needed.
Enter Community Inclusion, Relationships, Rights, Dignity and Respect, Health and Lifestyle.
Section V Activities of Daily Living
In Section V, Activities of Daily Living, check Yes or No: Is member independent with dressing/undressing, grooming, bed mobility, bathing, toileting and eating. If no, check all that apply and comment.
Ambulation, Transferring and Section VI Instrumental Activities of Daily Living
Is member independent with ambulation and transferring? Check Yes or No; if no, comment and check all that apply.
In Section VI, Instrumental Activities of Daily Living, check Yes or No: Is member able to prepare meals, shop independently, perform light housekeeping and perform heavy housework. If no, check all that apply and explain in the comments.
Laundry, medication, finances and telephone
Check Yes or No: Is member able to perform laundry tasks, take medication independently, handle finances independently and use the telephone independently. If no, explain in the comments and check all that apply. For the telephone: Requires adaptive device to use telephone, Requires supervision or verbal cues, Requires assistance when using telephone, Unable to use telephone.
Section VII Neuro/Emotional/Behavioral behavior problems
In Section VII, Neuro/Emotional/Behavioral, mark Yes or No for: Does member exhibit behavior problems. If yes, check all that apply and explain the frequency in comments, and enter the Date of functional analysis and the Date of behavior support plan.
Oriented to person, place, time and major change or crisis
Is member oriented to person, place, time? Check Yes or No; if no, check all that apply and comment. Has member experienced a major change or crisis within the past twelve months, and is the member actively participating in social and/or community activities? Check Yes or No; if yes, describe.
In 5) Is the member experiencing, for each checked, explain the frequency and details in the comments section.
Cognitive functioning, When Confused, When Anxious and Depressive Feelings
6) Cognitive functioning: Alert/oriented, able to focus and shift attention, comprehends and recalls task directions independently. Requires prompting only under stressful or unfamiliar conditions. Requires assistance and some direction in specific situations, or consistently requires low stimulus environment due to distractibility. Required considerable assistance in routine situations. Is not alert and oriented or is unable to shift attention and recall directions more than half the time. Totally dependent due to disturbances such as constant disorientation, coma, persistent vegetative state, or delirium. 7) When Confused, 8) When Anxious and 9) Depressive Feelings (Reported or Observed) each have Comments. "None of the above feelings reported or observed."
Member Behaviors, Behaviors Demonstrated at Least Once a Week and Frequency of Behavior Problems
10) Member Behaviors (Reported or Observed) and 12) Frequency of Behavior Problems each have Comments. 11) Behaviors Demonstrated at Least Once a Week: Memory deficit: failure to recognize familiar persons/places, inability to recall events of past 24-hours, significant memory loss so that supervision is required. Impaired decision-making: failure to perform usual ADL's, inability to inappropriately stop activities, jeopardizes safety through actions. Verbal disruption: yelling, threatening, excessive profanity, sexual references, etc. Physical aggression: aggressive or combative to self and others. Disruptive, infantile, or socially inappropriate behavior (excludes verbal actions). Delusional, hallucinatory, or paranoid behavior. "None of the above behaviors demonstrated."
Mental Status, Psychiatric Nursing Services, vision, hearing, communicate needs and diet
13) Mental Status and 14) Psychiatric Nursing Services each have Comments. Is member's vision adequate (with or without glasses) and is member's hearing adequate (with or without hearing aid)? Is member able to communicate needs and does member maintain an adequate diet? Check Yes or No; if no, check all that apply, then comment.
Respiratory care, stroke, lab work, genital and/or urinary care and paralysis
Does member require respiratory care and/or equipment, have history of a stroke(s), require routine lab work, require specialized genital and/or urinary care, or have total or partial paralysis? Check Yes or No; if yes, check all that apply and comment.
Body position, 24 hour caregiver, respite services, intravenous, allergies and medications
Does member require assistance with changes in body position, 24 hour caregiver or respite services? Check Yes or No; if yes, comment and check all that apply.
If the member requires intravenous fluids, intravenous medications or intravenous alimentation, check Peripheral IV or Central line and list solution, location, amount, rate, frequency and prescribing physician.
List drug allergies and other allergies. Does the member use any medications? Check Yes or No; if yes, list name of medication, dosage/frequency/route and administered by; add additional pages if needed.
Adaptive equipment and health, safety and welfare/crisis issues
For each adaptive equipment, check Has, Needs or N/A; if needs, explain in the comments. Please describe in detail any information regarding health, safety and welfare/crisis issues.
Section IX Environment Information and Section X Household
In Section IX, Environment Information, check Yes or No for each physical environment item; comment if necessary. 2) Provide an inventory of home adaptations already present in the member's dwelling (Such as wheelchair ramp, tub rails, etc.). In Section X, Does the member live alone? Check Yes or No; if yes, does the member receive any assistance from others? Check Yes or No.
Household Members and Section XI Additional Services
Fill in household member info: Name, Relationship, Age, Are they functionally able to provide care (if no, explain in the comments section), Comments and Care provided/frequency.
In Section XI, Additional Services, has the member had any admissions in the past 12 months? Check Yes or No; if yes, please list the facility name, facility address, reason for admission, admission date and discharge date.
Services from other agencies and Section XII Participant Directed Services
Does the member receive services from other agencies? Check Yes or No; if yes, list service(s) received, agency/worker name, phone number, agency address, frequency and number of units.
In Section XII, has the member been provided information on Participant Directed Services (PDS)? Check Yes or No; if no, give reason. If the member has chosen Participant Directed Services, include form MAP 2000.
More rules for MAP 351
Enter the Date Forwarded, Time Forwarded, Name of Person Forwarding and Title of Person Forwarding, then the Date Received, Time Received, Name of Person Logging Receipt and Title of Person Logging Receipt.
Common questions about MAP 351
Who signs it?
Under Signatures, each person performing assessment or reassessment enters Signature, Title and Date.
Sources
[1] Form MAP 351 (Rev. 4/20), Medicaid Waiver Assessment, Kentucky Cabinet for Health and Family Services, Department for Medicaid Services (the Official source link on this page).