

MAP-751k at a glance
What it is: MAP-751k is the CONSUMER/PROVIDER REQUEST TO CHANGE INFORMATION ON FILE (No Documentation Required) and replaces MAP-751, MAP-751a, and MAP-3069b.
Where and when to file: Fax the MAP-751K form to 917-639-0837 to make this change.[2]
A filled-in MAP-751k example: correcting a date of birth

How to fill out MAP-751k, box by box
Case Name, Case Number, CIN and Change is for
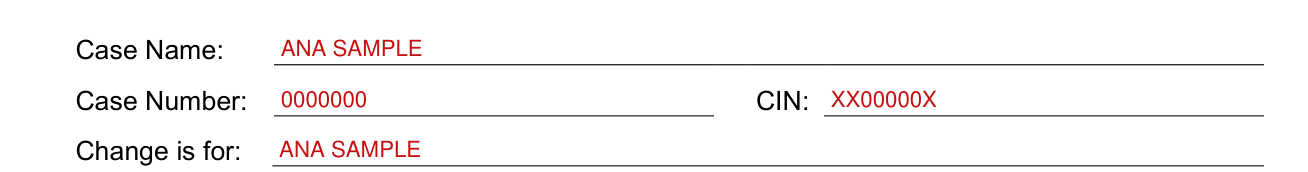
Fill in Case Name, Case Number, CIN and Change is for.
Change Name, Social Security Number, Date of Birth and Phone Number
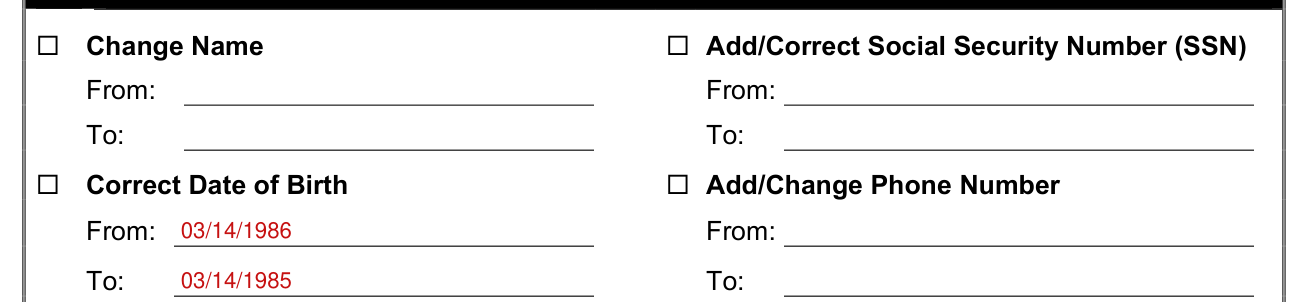
In A. CORRECT/ADD THE FOLLOWING INFORMATION, check all that apply.
To change a name, check Change Name and fill in From and To.
To add or correct a Social Security Number, check Add/Correct Social Security Number (SSN) and fill in From and To.
To correct a date of birth, check Correct Date of Birth and fill in From and To.
To add or change a phone number, check Add/Change Phone Number and fill in From and To.
Correct Gender Information

To correct gender information, check Correct Gender Information. Gender Identity is how you perceive yourself and what you call yourself. Your gender identity can be the same as or different from your sex assigned at birth.
Under From: and To: check Male, Female, Non-Binary or Non-Conforming, X, Transgender or Different Identity: (Describe).
Correct Sex
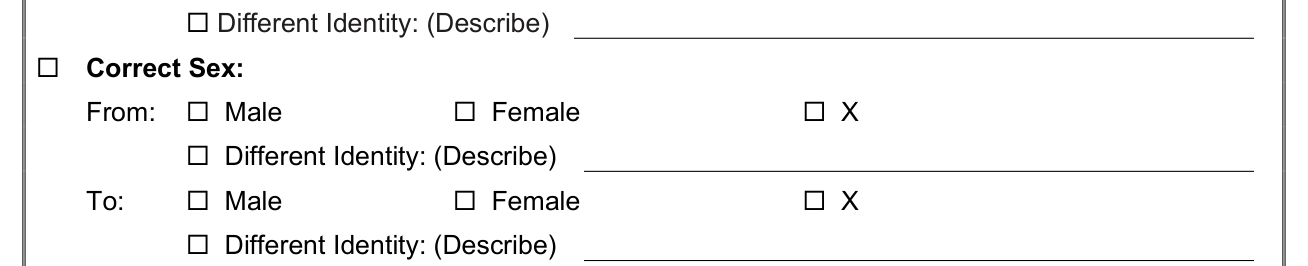
To correct sex, check Correct Sex.
Under From: and To: check Male, Female, X or Different Identity: (Describe).
Residency Address, Mailing Address and Secondary Mailing Address

To change a residency address, check Change Residency Address and fill in From and To.
To change a mailing address, check Change Mailing Address and fill in From and To.
To add or change a secondary mailing address, check Add/Change Secondary Mailing Address and fill in From and To.
Language Spoken and Language Read
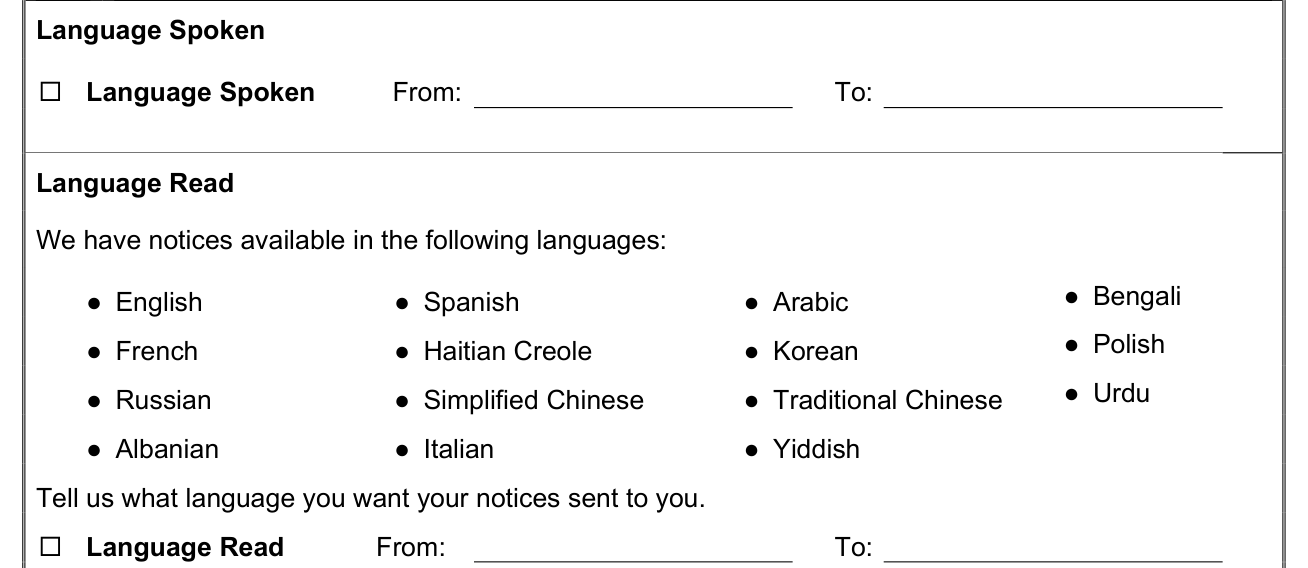
In CORRECT/ADD THE FOLLOWING INFORMATION (CHECK ALL THAT APPLY), check Language Spoken and fill in From and To.
To correct or add the language you want your notices sent to you in, check Language Read and fill in From and To.
Notices are available in English, Spanish, Arabic, Bengali, French, Haitian Creole, Korean, Polish, Russian, Simplified Chinese, Traditional Chinese, Urdu, Albanian, Italian, Yiddish.
Alternative Format/Visual Impairment

Do you have a visual disability that makes reading notices difficult? The formats for notices are Large Print, Audio CD, Data CD, Braille. Tell how you want your notices sent to you.
Provider Information (to be completed by providers only)

B. PROVIDER INFORMATION (TO BE COMPLETED BY PROVIDERS ONLY). Note: This section is not to be used for Home Care Services Program Providers submissions.
Fill in Provider Name, Provider Address, Provider Code, Original Determination Date, Admission Date, Admission Number, Discharge Date, Phone Number and Fax Number.
Name, signature and date

Enter NAME (PRINT), sign in SIGNATURE and enter DATE.
More rules for MAP-751k
Do you have a medical or mental health condition or disability? Does this condition make it hard for you to understand this notice or to do what this notice is asking? Does this condition make it hard for you to get other services at HRA? HRA can help you. Call 888-692-6116. You can also ask for help when you visit an HRA office. You have a right to ask for this kind of help under the law.
Common questions about MAP-751k
Where do I file it?
Fax the MAP-751K form to 917-639-0837 to make this change.[2]
Sources
[1] Form MAP-751k (E) 11/27/2024, Consumer/Provider Request to Change Information on File, NYC Human Resources Administration (the Official source link on this page).
[2] nyc.gov, submission_method (nyc.gov). Accessed October 31, 2026.