


Form DOH-5139 at a glance
What it is: Form DOH-5139 is the Disability Questionnaire of the New York State Department of Health State Disability Review Unit: current medical evidence is needed to evaluate your physical and/or mental impairments.
Who signs: Enter the Name of Person Completing Form (Please Print), the Date and the Telephone Number.
A filled-in Form DOH-5139 example: a first-time applicant with back pain

How to fill out Form DOH-5139, box by box
Name, Social Security Number, Date of Birth and Telephone No
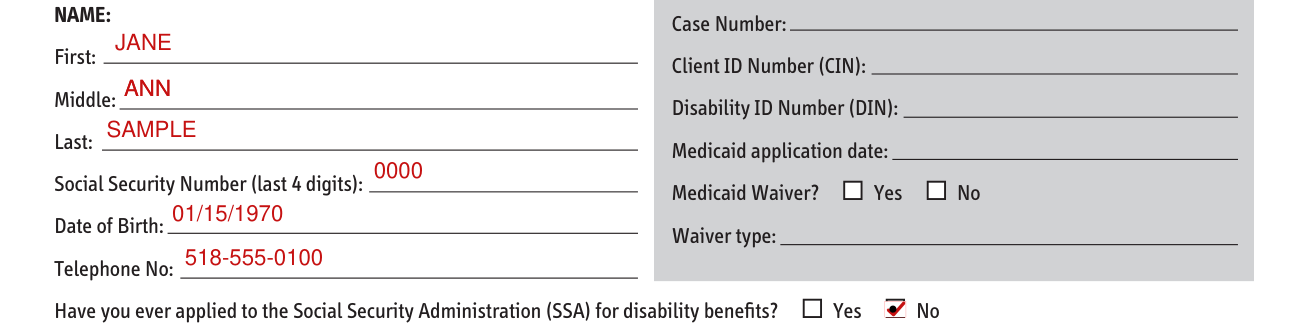
Under NAME, enter First, Middle and Last.
Enter the Social Security Number (last 4 digits), the Date of Birth and the Telephone No.
Completed by the State Disability Review Unit
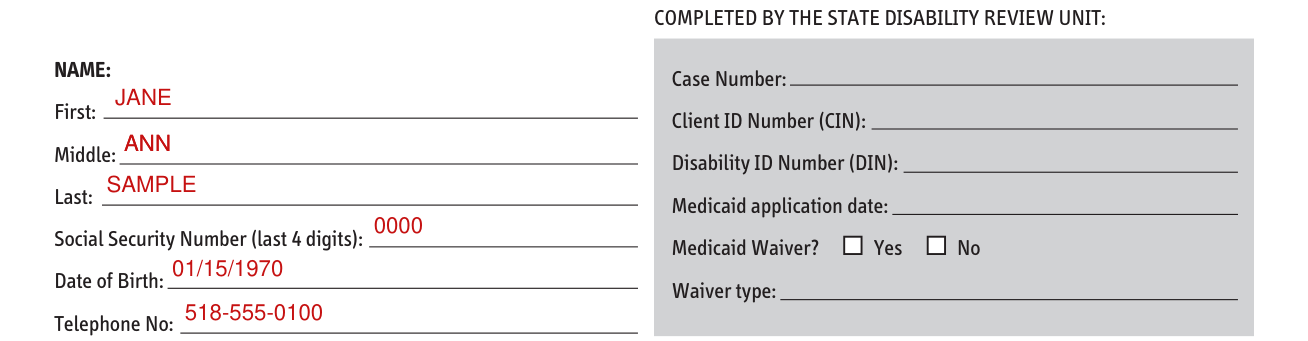
The State Disability Review Unit completes the section with Case Number, Client ID Number (CIN), Disability ID Number (DIN), Medicaid application date, Medicaid Waiver (Yes or No) and Waiver type.
Applied to the Social Security Administration (SSA) for disability benefits
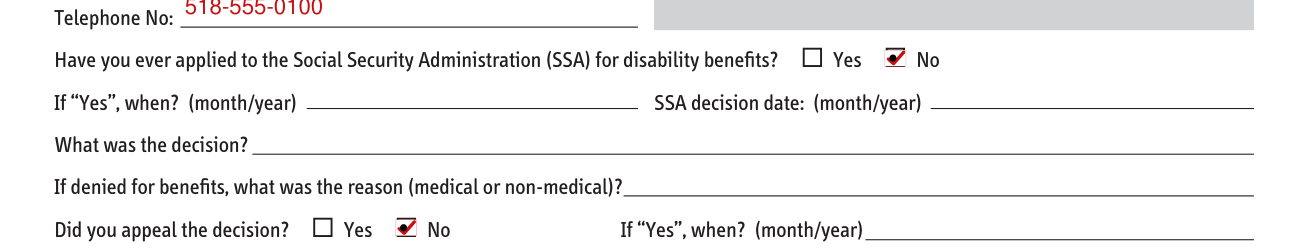
Have you ever applied to the Social Security Administration (SSA) for disability benefits? Yes or No.
If "Yes", enter when (month/year) and the SSA decision date (month/year).
Enter what the decision was, and if denied for benefits, the reason (medical or non-medical).
Did you appeal the decision
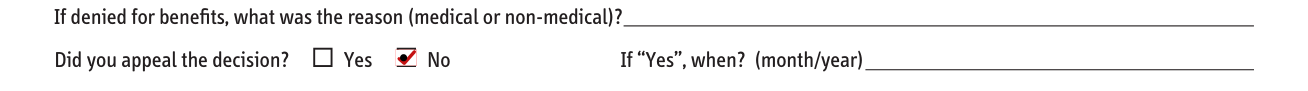
Did you appeal the decision? Yes or No. If "Yes", enter when (month/year).
PART I - INFORMATION ABOUT YOUR MEDICAL CONDITIONS

Under PART I - INFORMATION ABOUT YOUR MEDICAL CONDITIONS, A. Please list all of your medical conditions (diagnoses).
Under B, enter how your medical conditions affect your ability to function. Please include any limitations in your ability to perform activities of daily living and work-related activities.
C. Please list your medications (or attach a list).
A. Do you have a primary care provider

A. Do you have a primary care provider? Yes or No. (If "Yes", please provide name, address, phone number.)
Enter the Date of last visit (month/year).
B. Have you seen any other medical provider(s) within the past 12 months
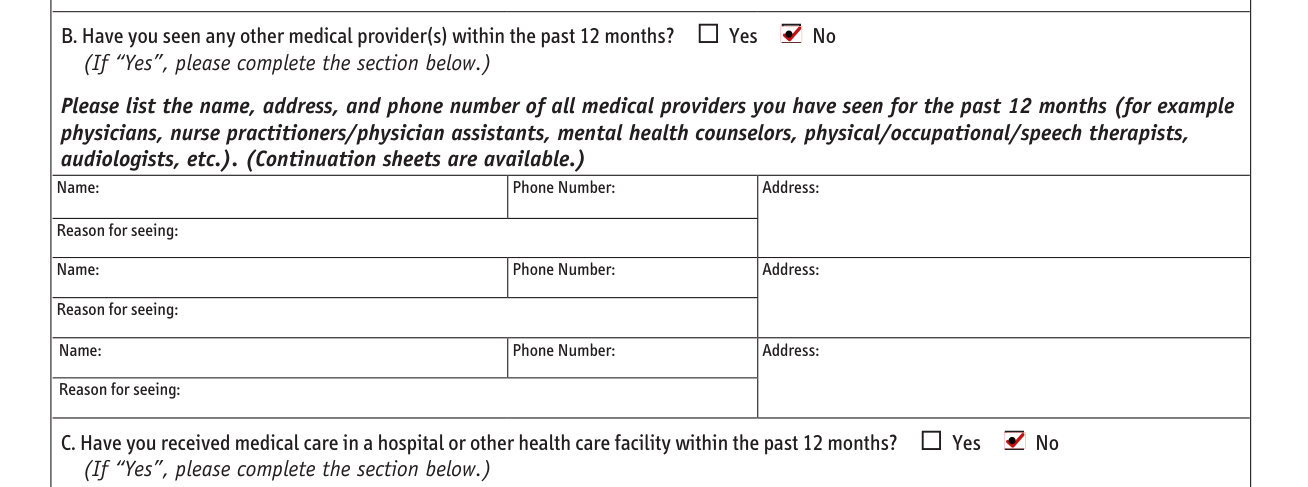
B. Have you seen any other medical provider(s) within the past 12 months? Yes or No. If "Yes", list the name, address, and phone number of all medical providers you have seen for the past 12 months (for example physicians, nurse practitioners/physician assistants, mental health counselors, physical/occupational/speech therapists, audiologists, etc.): enter Name, Phone Number, Address and Reason for seeing.
C. Have you received medical care in a hospital or other health care facility within the past 12 months

C. Have you received medical care in a hospital or other health care facility within the past 12 months? Yes or No. If "Yes", list the name and address of all hospitals and other medical facilities at which you have sought treatment in the past 12 months: enter Name, Address and Reason.
D. Have you received services from any agencies to assist you with your impairment(s) within the past 12 months

D. Have you received services from any agencies to assist you with your impairment(s) within the past 12 months? Yes or No. If "Yes", list the name and address of any other agencies that you have seen for assistance with your medical conditions in the past 12 months (for example, vocational rehabilitation agencies, supported employment or housing agencies, case management agencies, etc.): enter Name, Address and Reason.
PART III - Highest grade level and your child's school or program

A. What is the highest grade level of schooling that you have completed?
B. If you have a child up to the age of 21 attending school or a vocational program, enter the School/Program Name and Address, and complete the DOH-5173, Authorization for Release of Medical Information Pursuant to HIPAA form for this school/program.
Special Education classes, special help or accommodations in school and vocational training
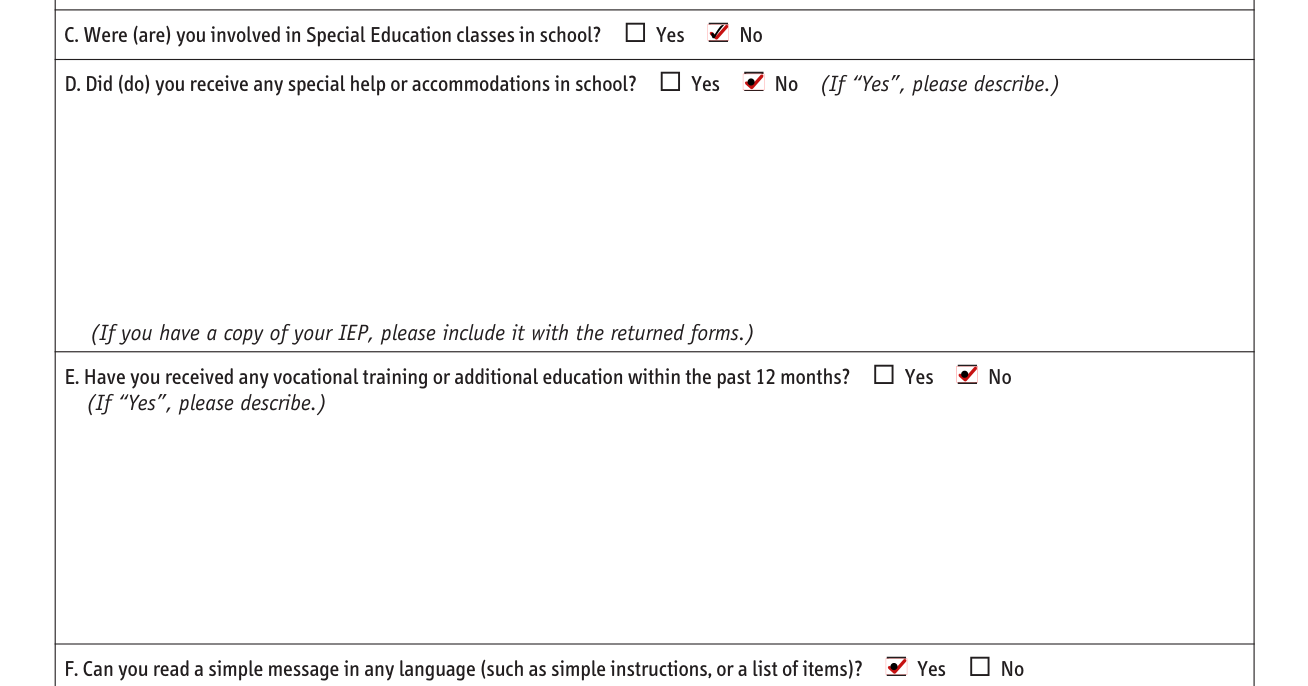
C. Were (are) you involved in Special Education classes in school? Yes or No.
D. Did (do) you receive any special help or accommodations in school? Yes or No. If "Yes", please describe.
If you have a copy of your IEP, please include it with the returned forms.
E. Have you received any vocational training or additional education within the past 12 months? Yes or No. If "Yes", please describe.
Read, write and assistance or an interpreter
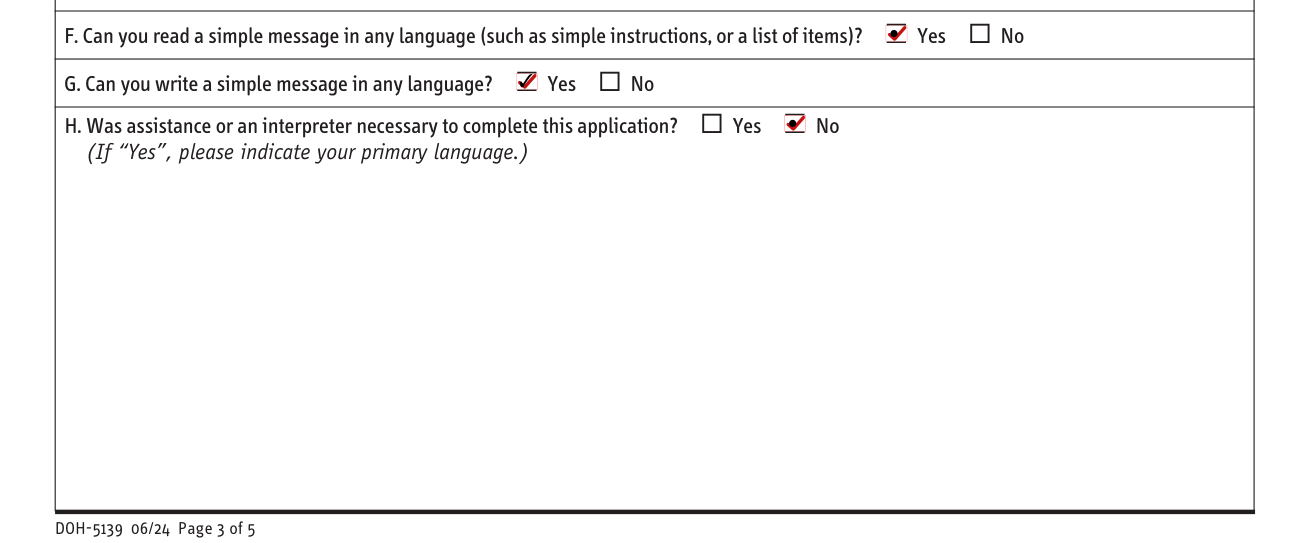
F. Can you read a simple message in any language (such as simple instructions, or a list of items)? Yes or No.
G. Can you write a simple message in any language? Yes or No.
H. Was assistance or an interpreter necessary to complete this application? Yes or No. If "Yes", please indicate your primary language.
PART IV - INFORMATION ABOUT WORK YOU DID IN THE PAST 5 YEARS
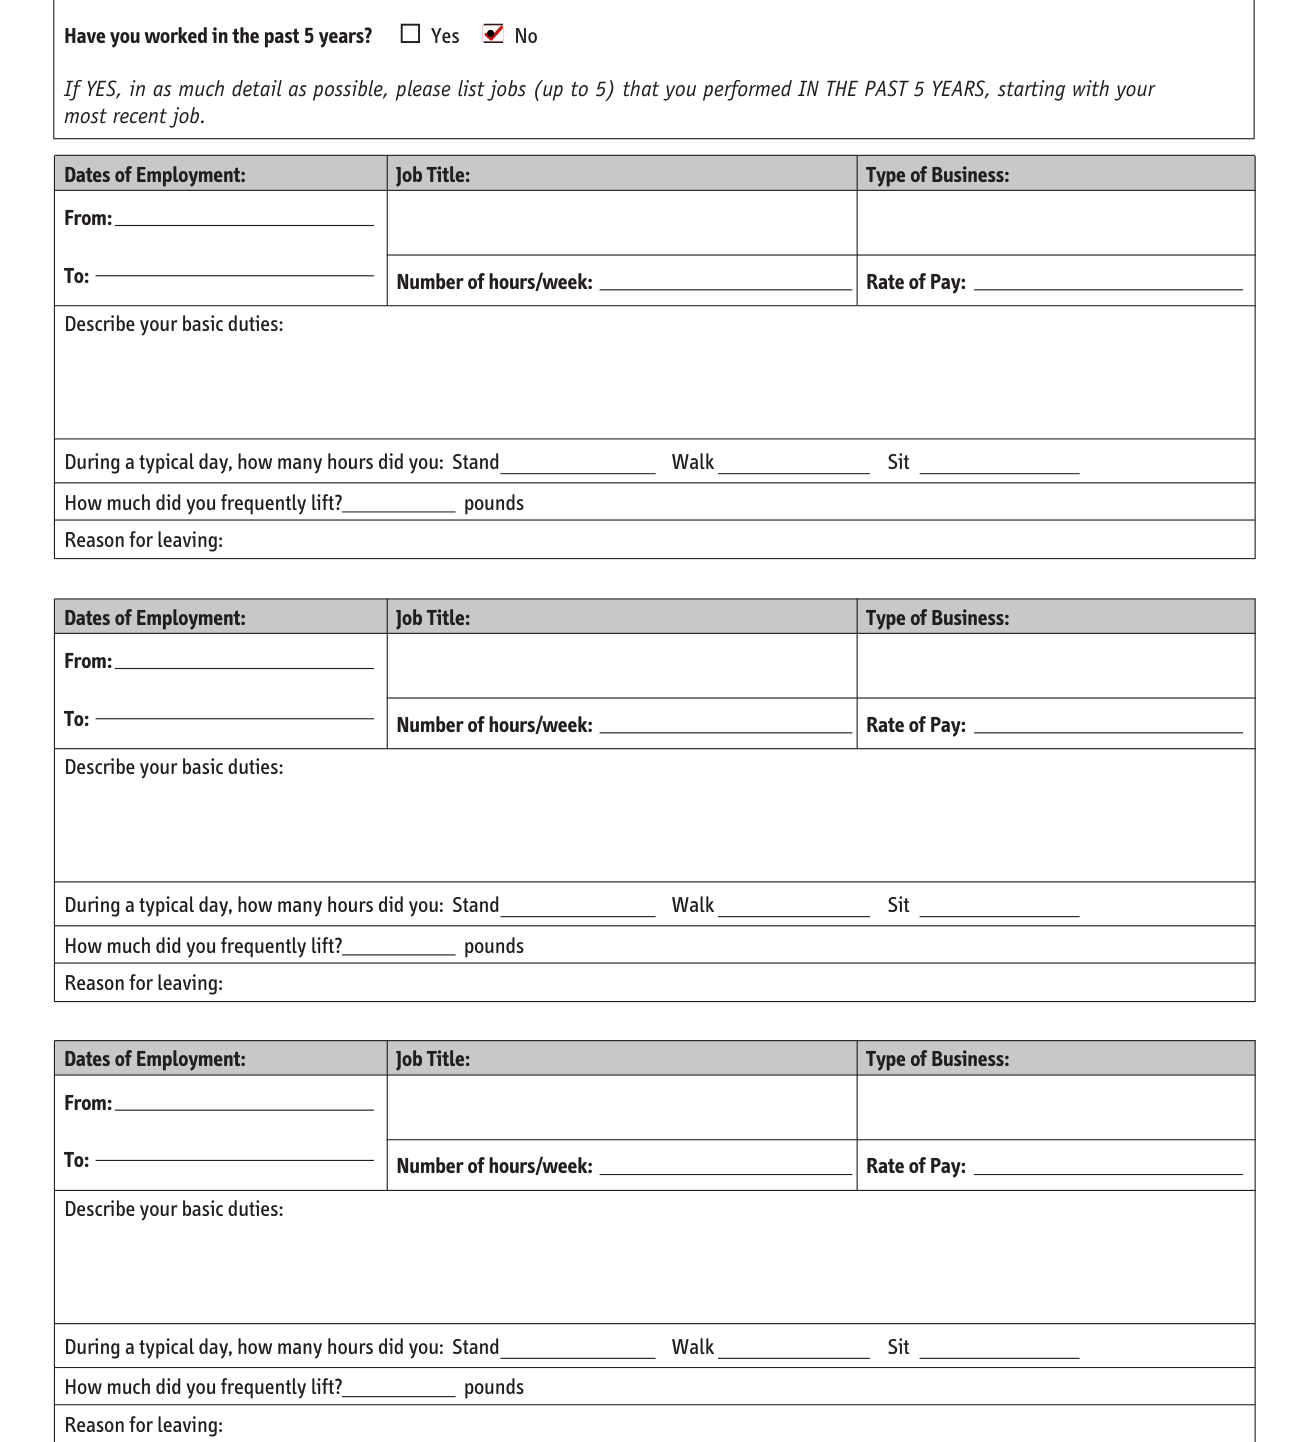
Under PART IV - INFORMATION ABOUT WORK YOU DID IN THE PAST 5 YEARS: Have you worked in the past 5 years? Yes or No. If YES, in as much detail as possible, list jobs (up to 5) that you performed IN THE PAST 5 YEARS, starting with your most recent job.
For each job, enter Dates of Employment (From and To), Job Title, Type of Business, Number of hours/week and Rate of Pay.
Describe your basic duties.
Enter how many hours you stand, walk and sit during a typical day, and how much you frequently lift, in pounds.
Enter the Reason for leaving.
More rules for Form DOH-5139
If you have not seen a medical provider for your impairment(s) within the past 12 months, a consultative exam may be arranged for you by the local agency.
Continuation sheets are available.
If a disability determination cannot be made based on your medical conditions alone, the factors of education, literacy, and work history will be used to determine disability.
Sources
[1] Form DOH-5139 (06/24), Disability Questionnaire, New York State Department of Health (the Official source link on this page).