

Form MC 371 at a glance
What it is: Form MC 371_07/09, from the State of California Health and Human Services Agency, Department of Health Care Services, is for Additional Family Members Requesting Medi-Cal.
Who signs: Sign on the Signature line and enter the Date.
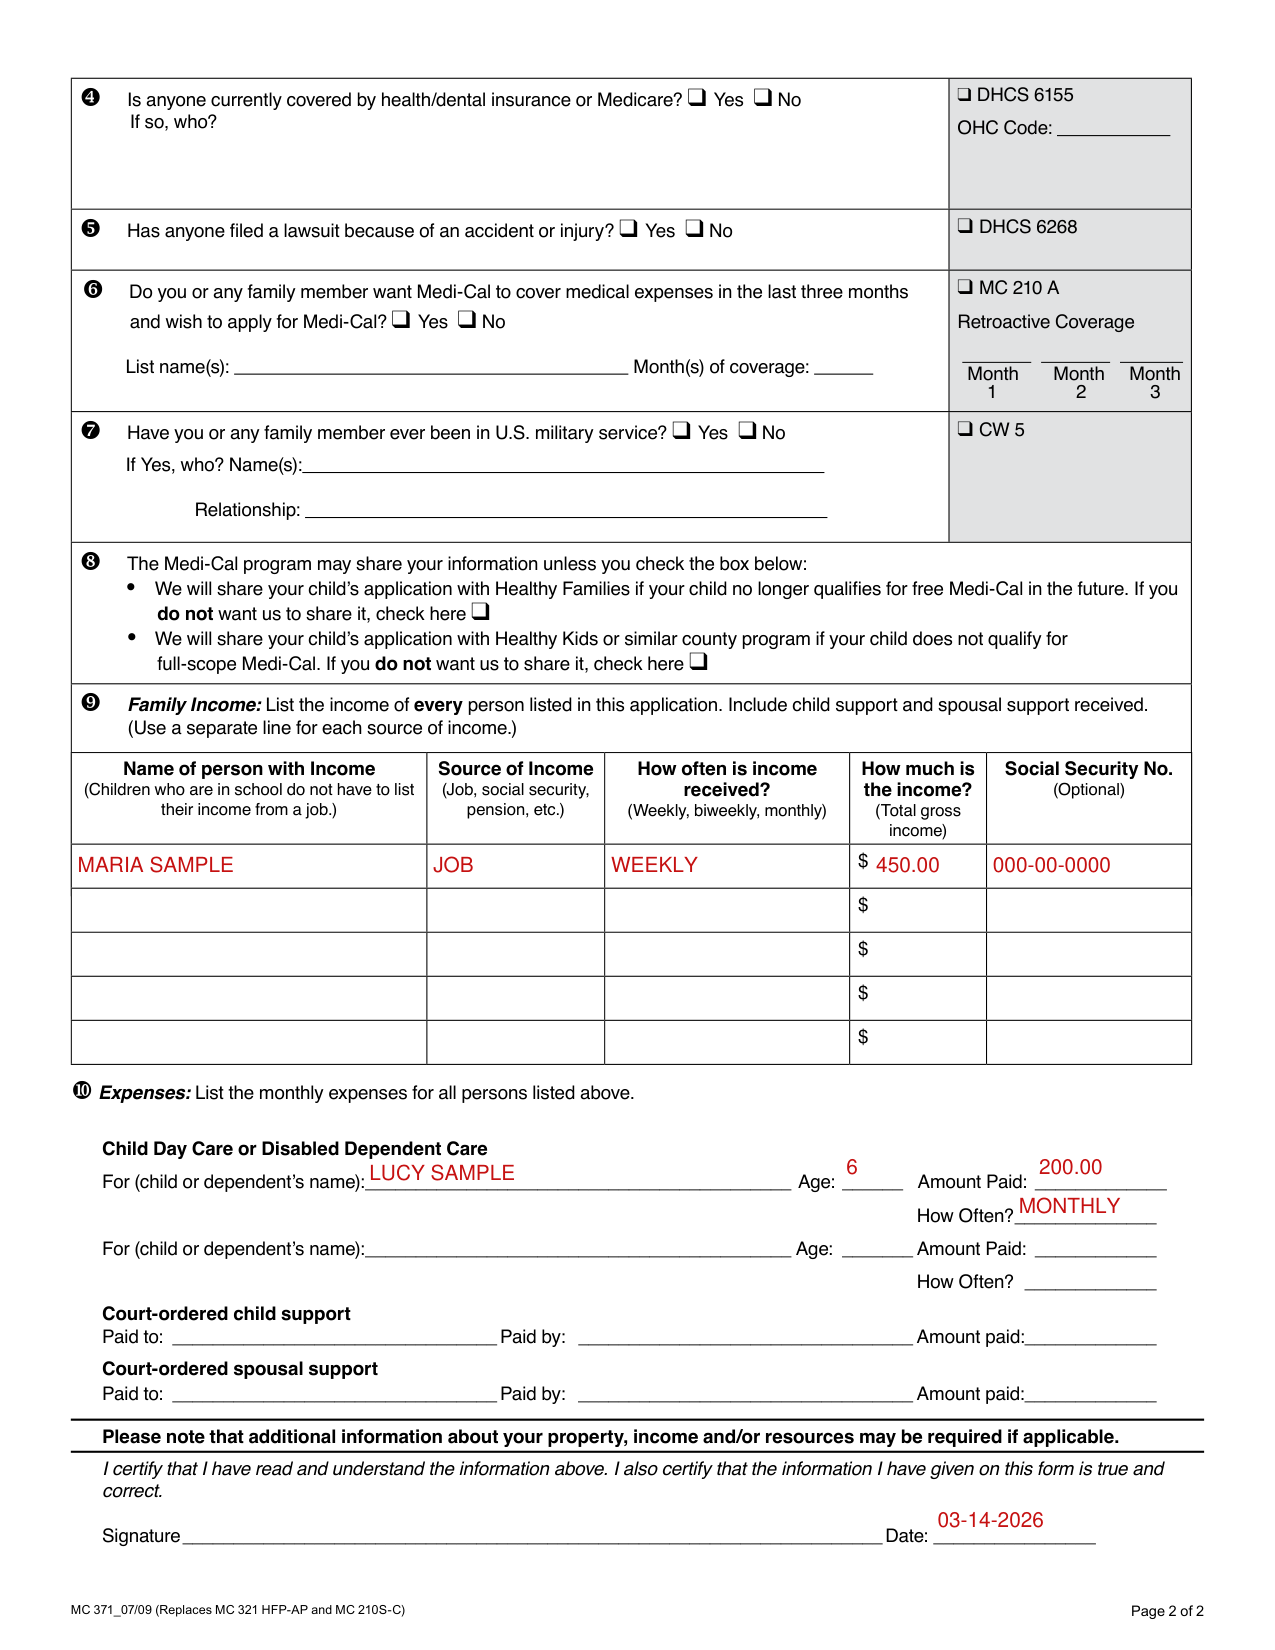
A filled-in Form MC 371 example: a mother reports income and day care costs
How to fill out Form MC 371, box by box
Name and Relationship on the u, v and w lines

On the u line, enter the Applicant/Caretaker's Name (First, Middle, Last) and the Applicant/Caretaker's Relationship to Child(ren).
On the v line, enter the Spouse/Other Parent's Name (First, Middle, Last) and the Relationship to Applicant/Caretaker.
On the w line, enter the Child's Name: (First, Middle, Last) or "Unborn" and the Relationship to Applicant/Caretaker.
Gender and Pregnant?
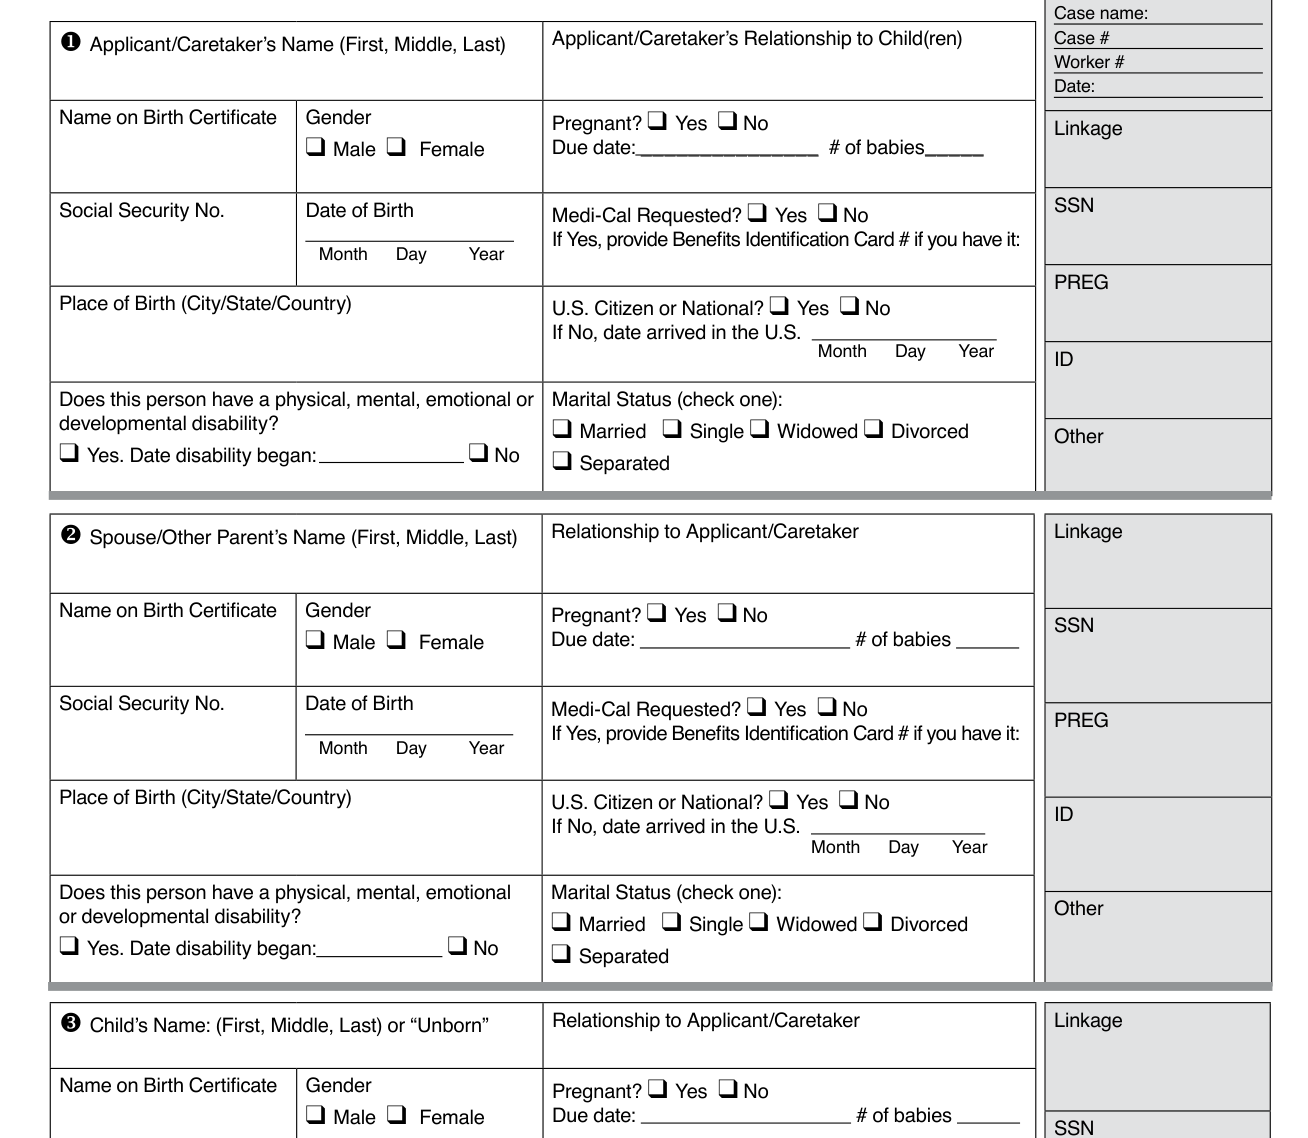
On each of the u, v and w lines, check q Male or q Female under Gender.
On each of the u, v and w lines, check Pregnant? q Yes or q No, and enter the Due date and the # of babies.
Social Security No. and Place of Birth
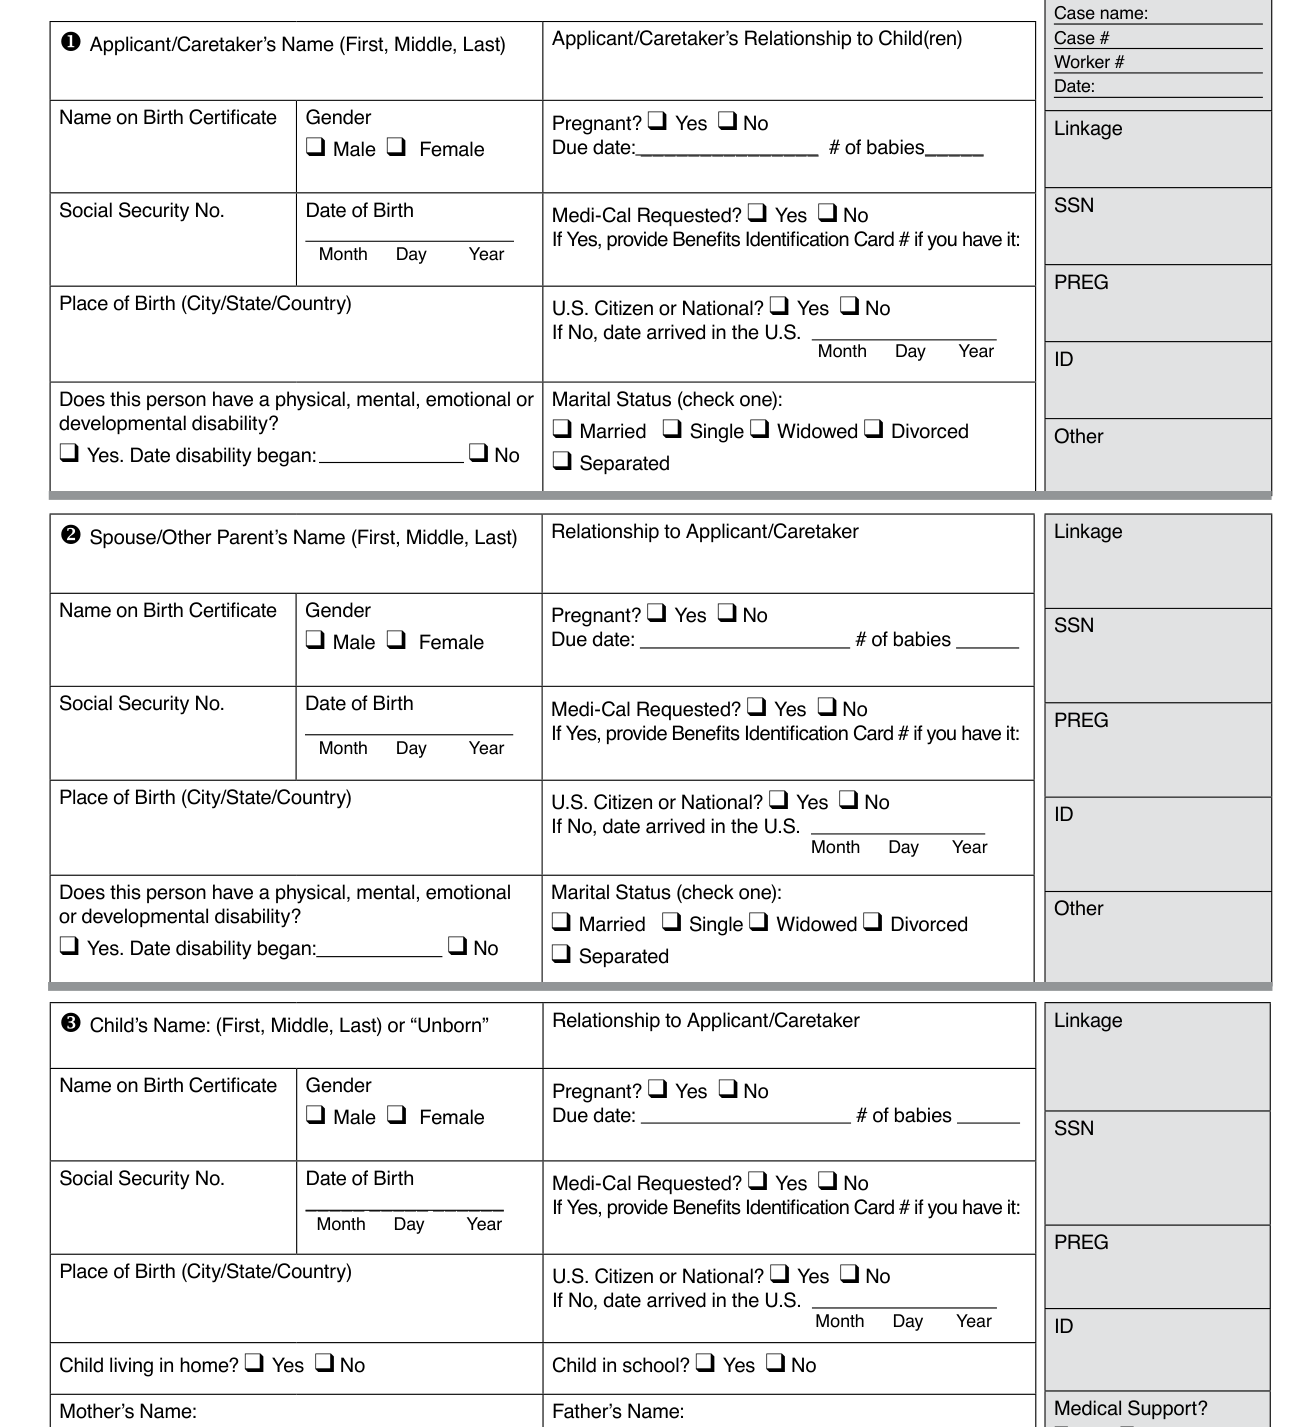
On each of the u, v and w lines, enter the Social Security No. and the Date of Birth. Under Medi-Cal Requested?, check q Yes or q No. If Yes, provide the Identification Card # if you have it.
On each of the u, v and w lines, enter the Place of Birth (City/State/Country). Under U.S. Citizen or National?, check q Yes or q No. If No, enter the date arrived in the U.S.
Disability and Marital Status
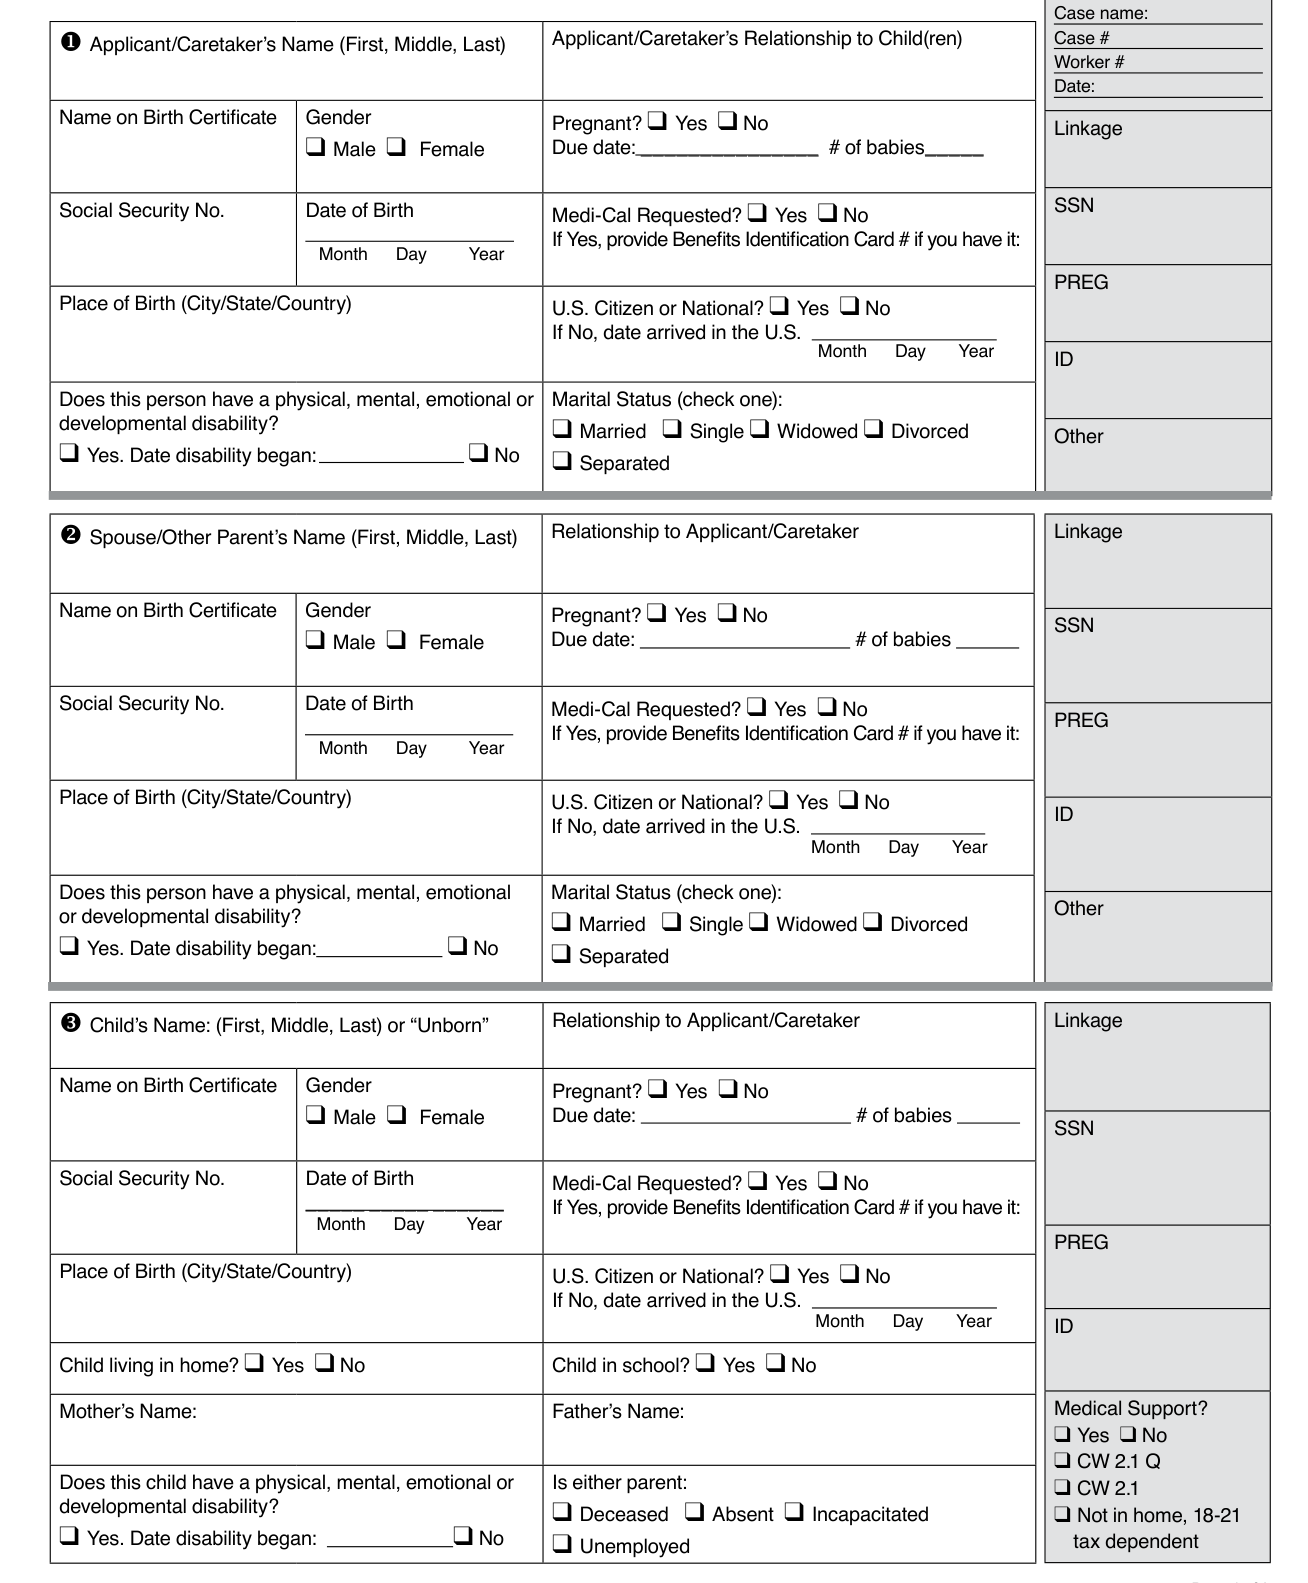
On the u and v lines, check q Yes or q No if this person has a physical, mental, emotional or developmental disability. If q Yes, enter the date the disability began.
On the u and v lines, check one of Married, Single, Widowed, Divorced or Separated under Marital Status (check one).
On the w line, check q Yes or q No for Child living in home? and for Child in school?
On the w line, enter the Mother's Name and the Father's Name.
On the w line, check q Yes or q No if this child has a physical, mental, emotional or developmental disability, and enter the Date disability began after q Yes.
On the w line, under Is either parent:, check q Deceased, q Absent, q Incapacitated or q Unemployed.
Insurance, lawsuit, Retroactive Coverage and military service

On line x, check q Yes or q No to: Is anyone currently covered by health/dental insurance or Medicare? If so, enter who.
On line y, check q Yes or q No for a lawsuit because of an accident or injury.
On line z, check q Yes or q No to: Do you or any family member want Medi-Cal to cover medical expenses in the last three months and wish to apply for Medi-Cal? Under Retroactive Coverage, list name(s) and the Month(s) of coverage.
Check q Yes or q No to: Have you or any family member ever been in U.S. military service? If Yes, enter who: the Name(s) and the Relationship.
Family Income
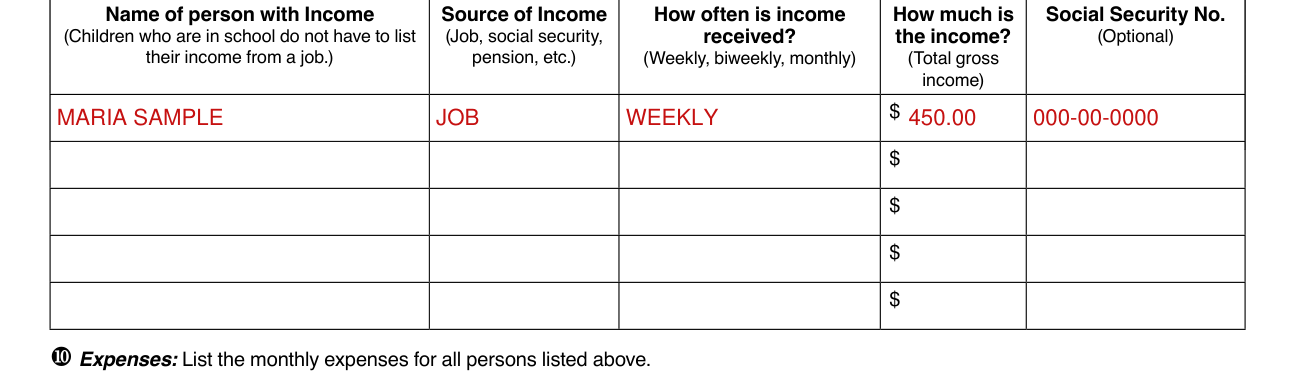
List the income of every person listed in this application. Include child support and spousal support received. Use a separate line for each source of income.
Under Name of person with Income, children who are in school do not have to list their income from a job.
On each line, enter the Source of Income (Job, social security, pension, etc.), How often is income received? (Weekly, biweekly, monthly), How much is the income? (Total gross income) and the Social Security No. (Optional).
Expenses
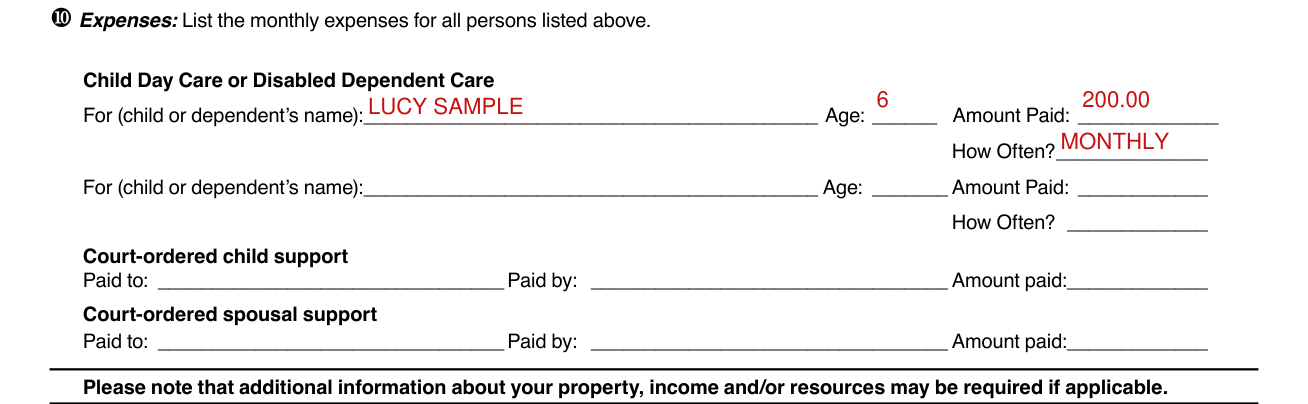
List the monthly expenses for all persons. Under Child Day Care or Disabled Dependent Care, enter For (child or dependent's name), Age, Amount Paid and How Often?
Under Court-ordered child support and Court-ordered spousal support, enter Paid to, Paid by and Amount paid.
Certification

By signing, you certify that the information you have given on this form is true and correct.
More rules for Form MC 371
Additional information about your property, income and/or resources may be required if applicable.
Sources
[1] Form MC 371 (07/09), Additional Family Members Requesting Medi-Cal, California Department of Health Care Services (the Official source link on this page).
