

Mileage Reimbursement Form at a glance
What it is: Mileage reimbursement form for the round-trip mileage to and from residence and the name of the medical facility.
A filled-in Mileage Reimbursement Form example: a claimant lists two medical visits
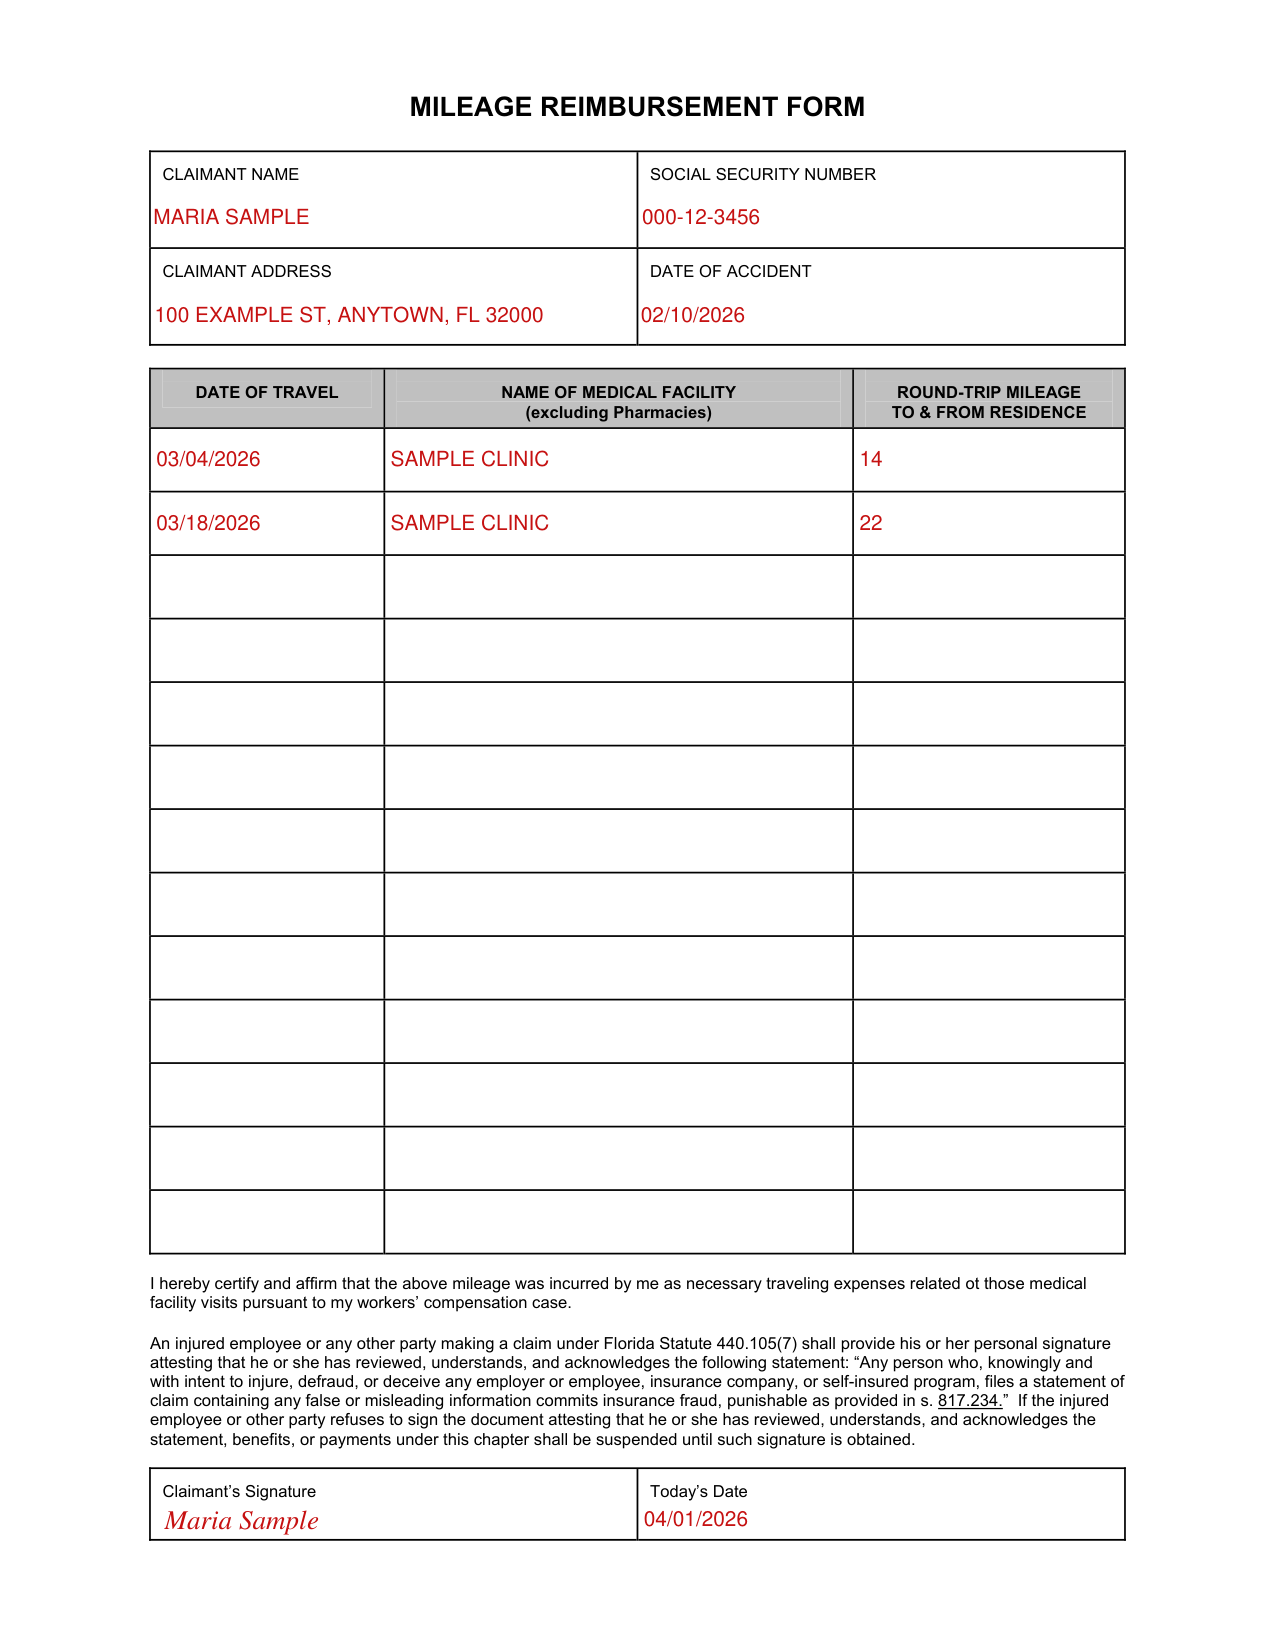
How to fill out Mileage Reimbursement Form, box by box
Claimant name, social security number, address and date of accident
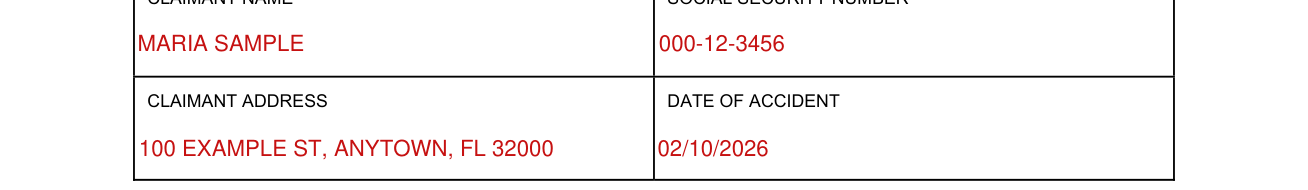
Write the claimant name on the Mileage Reimbursement Form.
Enter the social security number.
Enter the claimant address.
Enter the date of accident.
Date of travel, name of medical facility and round-trip mileage
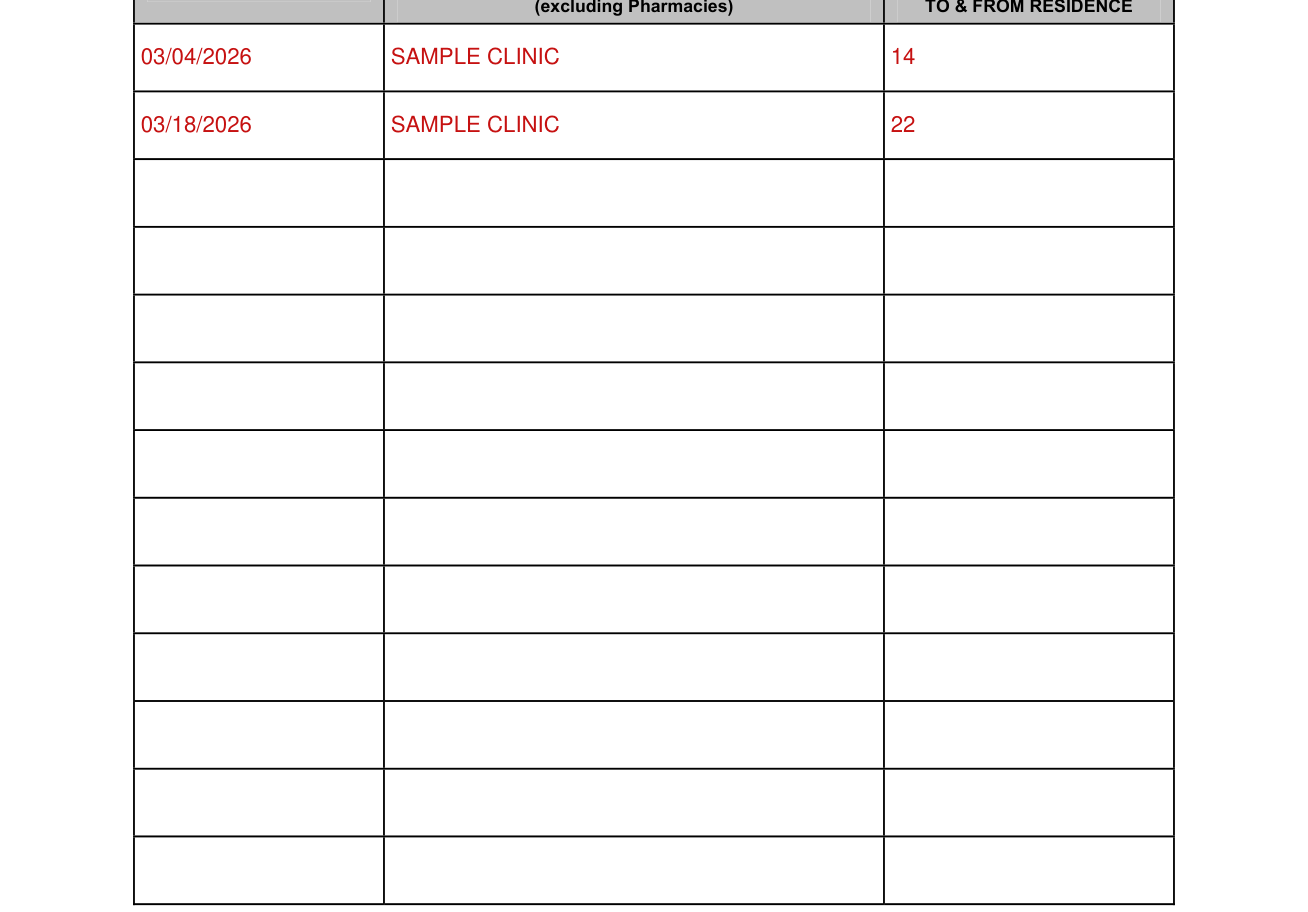
Enter the date of travel.
Enter the name of the medical facility, excluding pharmacies.
Enter the round-trip mileage to and from residence.
Claimant's Signature and Today's Date

You certify and affirm that the mileage in ROUND-TRIP MILEAGE TO & FROM RESIDENCE was incurred by you as necessary traveling expenses related to those medical facility visits pursuant to your workers' compensation case. An injured employee or any other party making a claim under Florida Statute 440.105(7) shall provide his or her personal signature attesting that he or she has reviewed, understands, and acknowledges the following statement: “Any person who, knowingly and with intent to injure, defraud, or deceive any employer or employee, insurance company, or self-insured program, files a statement of claim containing any false or misleading information commits insurance fraud, punishable as provided in s. 817.234.” If the injured employee or other party refuses to sign the document attesting that he or she has reviewed, understands, and acknowledges the statement, benefits, or payments under this chapter shall be suspended until such signature is obtained. Sign at Claimant's Signature.
Enter Today's Date.
Sources
[1] Mileage Reimbursement Form, Florida workers' compensation (no issuer file found) (the Official source link on this page).
