


University of Mississippi Medical Center/University Sports Medicine Athletic Participation Form at a glance
What it is: The University of Mississippi Medical Center/University Sports Medicine Athletic Participation Form has the athlete's Family Medical History, Orthopaedic History and Medical History, a WAIVER FORM and physician-only information. Do not fold the form.
Who signs: Sign the Signature of Patient line and enter the Typed or Printed Name of Physician. Signature of Parent/Guardian is not required if the patient is over 18 yrs old.
A filled-in University of Mississippi Medical Center/University Sports Medicine Athletic Participation Form example: an athlete and a physician complete page 1

How to fill out University of Mississippi Medical Center/University Sports Medicine Athletic Participation Form, box by box
Name, Date, School, Grade, Sport(s), Date of Birth and Parent/Guardian Name
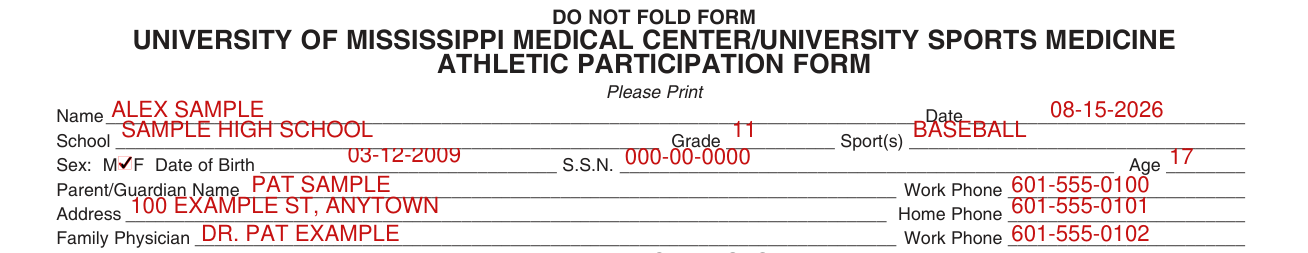
Please Print the Name, Date, School, Grade, Sport(s), Sex (M or F), Date of Birth, S.S.N., Age, Parent/Guardian Name and Work Phone, Address and Home Phone, Family Physician and Work Phone.
Waiver Form

Enter the day, the blank after "day of", the 20 blank, the M.D. and the patient when this waiver is executed. It is executed in compliance with Mississippi law, with the full understanding that if a physician voluntarily provides needed medical or health services to any program at an accredited school in the state without expectation of payment, the physician will be immune from liability for any civil action arising out of the provision of those medical and/or health care services which were provided in good faith on a charitable basis. Such immunity does not extend to willful acts or gross negligence.
Signature of Patient and Signature of Physician

Sign the Signature of Patient line and enter the Typed or Printed Name of Physician.
Signature of Parent/Guardian is not required if the patient is over 18 yrs old.
Signature of Physician.
Information below to be filled out by physician only

To be filled out by physician only: Height, Weight, Blood Pressure and Pulse.
Check one box: From this limited screening I see no reason why this student cannot participate in athletics, or Student needs further evaluation as described.
More rules for University of Mississippi Medical Center/University Sports Medicine Athletic Participation Form
Family Medical History: Has any member of your family under age 50 had these conditions? Check Yes or No for Heart Attack, Sudden Death, Stroke, Heart Disease / High Blood Pressure, Diabetes, Sickle Cell Anemia, Arthritis, Epilepsy and Kidney Disease, and enter Whom for each Condition.
Athlete's Orthopaedic History: Has the athlete had any of the following injuries? Check Yes or No and enter the Date for Shoulder L / R, Elbow L / R, Hip, Knee L / R, Chronic Shin Splints L / R, Foot L / R, Pinched Nerve, Neck Injury / Stinger, Arm / Wrist / Hand L / R, Back, Thigh L / R, Lower Leg L / R, Ankle L / R, Severe Muscle Strain and Chest. Enter Previous Surgeries.
Athlete's Medical History: Has the athlete had any of these conditions? Check Yes or No for Heart Murmur, Organ Loss, Overnight in hospital, Seizures, Shortness of breath / coughing during exercise, Hernia, Kidney Disease, Rapid weight loss / gain, Irregular Pulse, Chest Pain/Tightness, Take supplements / vitamins, Single Testicle, Loss of consciousness/"Knocked out", Heat related problems, High Blood Pressure, Heart Disease, Menstrual irregularities, Dizzy / Fainting, Diabetes, Recent Mononucleosis / Enlarged Spleen, Head Injury / Concussion, Liver Disease, Asthma and Tuberculosis.
Have you had any serious medical illness/injury since your last sports physical? Are you currently taking any prescription or non prescription (over the counter) medications? Enter Surgery - What Type?, Allergies (Food, Drugs) and the Date of last Tetanus Immunization.
Knowledge: true and accurate information is given and permission is granted for the physical screening evaluation. The evaluation involves a limited examination, and the screening is not intended to nor will it prevent injury or sudden death. The examination will be provided without expectation of payment, and the physician and many other medical professionals providing services may be immune from liability under Mississippi Law.
To be filled out by physician only: ORTHOPAEDIC EXAM and GENERAL MEDICAL EXAM: enter Norm or Abnl for I. Spine / Neck (Cervical, Thoracic, Lumbar), II. Upper Extremity (Shoulder, Elbow, Wrist, Hand / Fingers), III. Lower Extremity (Hip, Knee, Ankle, Feet), ENT, Lungs, Heart, Abdomen, Skin and Hernia (if Needed), then General Health Comments. FLEXIBILITY LEFT RIGHT for Neck, Shoulders, Hips, Quadriceps, Hamstrings, Achilles and Back Ext / Flex, then Comments and Other Comments.
To be filled out by physician only: OPTIONAL EXAMS: DENTAL and VISION L and R, each with Comments.
Sources
[1] University of Mississippi Medical Center/University Sports Medicine Athletic Participation Form (the served file; no issuer file found) (the Official source link on this page).