How to Fill Out Initial Self Evaluation Form

Initial Self Evaluation Form at a glance

What it is: Initial Self Evaluation Form: please tell about yourself, so that you can be served better.

A filled-in Initial Self Evaluation Form example: a first visit for knee pain

Initial Self Evaluation Form example filled out, example: a first visit for knee pain
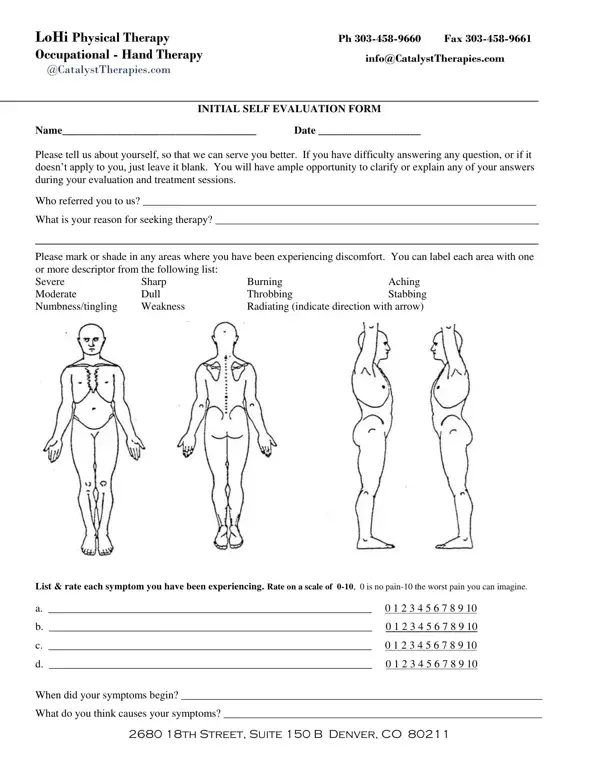
Sam Sample completes the initial self evaluation form. Sam rates a sore right knee 6 out of 10 and ticks Standing and Walking. The picture shows page 1, and all its values are invented.

How to fill out Initial Self Evaluation Form, box by box

Your name, the date and who referred you

Initial Self Evaluation Form example filled out, your name, the date and who referred you

Write your Name, the Date and Who referred you.

Your reason for seeking therapy

Initial Self Evaluation Form example filled out, your reason for seeking therapy

What is your reason for seeking therapy?

Please mark or shade in any areas where you have been experiencing discomfort.

Label each area with one or more descriptor: Severe, Sharp, Burning, Aching, Moderate, Dull, Throbbing, Stabbing, Numbness/tingling, Weakness, Radiating (indicate direction with arrow).

List and rate each symptom

Initial Self Evaluation Form example filled out, list and rate each symptom

List & rate each symptom you have been experiencing. Rate on a scale of 0-10, 0 is no pain-10 the worst pain you can imagine.

When did your symptoms begin and what do you think causes them

Initial Self Evaluation Form example filled out, when did your symptoms begin and what do you think causes them

When did your symptoms begin?

What do you think causes your symptoms?

What makes your symptoms worse and what eases them

Initial Self Evaluation Form example filled out, what makes your symptoms worse and what eases them

What makes your symptoms worse? Sitting, Standing, Bending, Lifting, Walking, Running, or Other, describe.

What eases your symptoms?

The daily pattern of your symptoms and your sleep

Initial Self Evaluation Form example filled out, the daily pattern of your symptoms and your sleep

Please describe the daily pattern of your symptoms. Type and severity of discomfort.

First thing in the morning? Later morning? Late afternoon? Evening?

Is your sleep pattern disturbed? How many hours of sleep do you typically have per night?

Seen by a physician, diagnostic tests and previous treatment

Initial Self Evaluation Form example filled out, seen by a physician, diagnostic tests and previous treatment

Have you been seen by a physician for these symptoms? If so, what was the diagnosis?

Have you had any diagnostic tests done? (X-rays, MRI, EMG/NCV, etc.) If so what were the results?

(If you have access to any reports or films, it would be helpful to bring them in.)

Have you had any previous treatment for this condition? (Previous Physical Therapy, chiropractic, massage, etc.) What were the results?

Medications, work, activities and exercise
Initial Self Evaluation Form example filled out, medications, work, activities and exercise

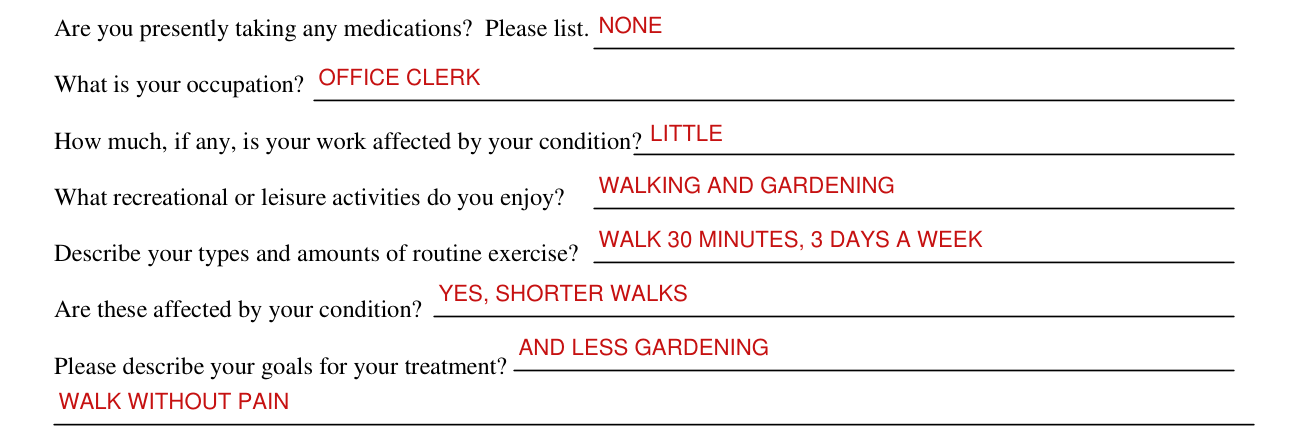
Are you presently taking any medications? Please list.

What is your occupation? How much, if any, is your work affected by your condition?

What recreational or leisure activities do you enjoy? Describe your types and amounts of routine exercise? Are these affected by your condition?

Goals, time and other comments

Initial Self Evaluation Form example filled out, goals, time and other comments

Please describe your goals for your treatment? How much time (per day or per week) are you willing to commit to improve your symptoms? Other Comments.

More rules for Initial Self Evaluation Form

If you have difficulty answering any question, or if it doesn't apply to you, just leave it blank.

You will have ample opportunity to clarify or explain any of your answers during your evaluation and treatment sessions.

Sources

[1] Initial Self Evaluation Form, LoHi Physical Therapy (the served file; no issuer file found) (the Official source link on this page).

Pictures Of A Physical Therapist Evaluation Form PDF Details

The Pictures Of A Physical Therapist Evaluation form, utilized by LoHi Physical Therapy, is a comprehensive document designed to gather essential information from patients seeking therapy services. This form, accessible at both 2680 18th Street, Suite 150 B in Denver, Colorado, and through contact methods like phone (303-458-9660) and email (info@CatalystTherapies.com), serves as a preliminary self-assessment tool. It encourages patients to provide detailed accounts of their symptoms, their severity, and their impact on daily life. The form prompts patients to indicate the location and nature of their discomfort using descriptors such as severe, sharp, or aching, and to rate their symptoms on a scale from zero to ten. Furthermore, it probes into the onset of these symptoms, potential causes, aggravating and alleviating factors, and any disturbance to sleep patterns. Patients are also asked about their medical history concerning the condition, including physician consultations, diagnostic tests, and prior treatments. Additionally, it seeks information on medication use, occupational impacts, exercise routines, and recreational activities affected by the condition. Importantly, it asks the patient to outline their treatment goals and the time they are willing to commit to therapy. Through its comprehensive approach, the form not only assists therapists in tailoring treatment plans but also fosters an open line of communication between the therapist and patient right from the start.

QuestionAnswer
Form NamePictures Of A Physical Therapist Evaluation Form
Form Length2 pages
Fillable?Yes
Fillable fields39
Avg. time to fill out8 min 22 sec
Other namesshoulder evaluation physical therapy format, therapy initial self evaluation, initial self evaluation form, pedcicatric phsyical threapy evaluation template