


Certificate of Death VS 300 (MO 580-2211) at a glance
What it is: The Missouri Department of Health and Senior Services Certificate of Death, VS 300 MO 580-2211 (1-10).
A filled-in Certificate of Death VS 300 (MO 580-2211) example: a funeral director completes the certificate
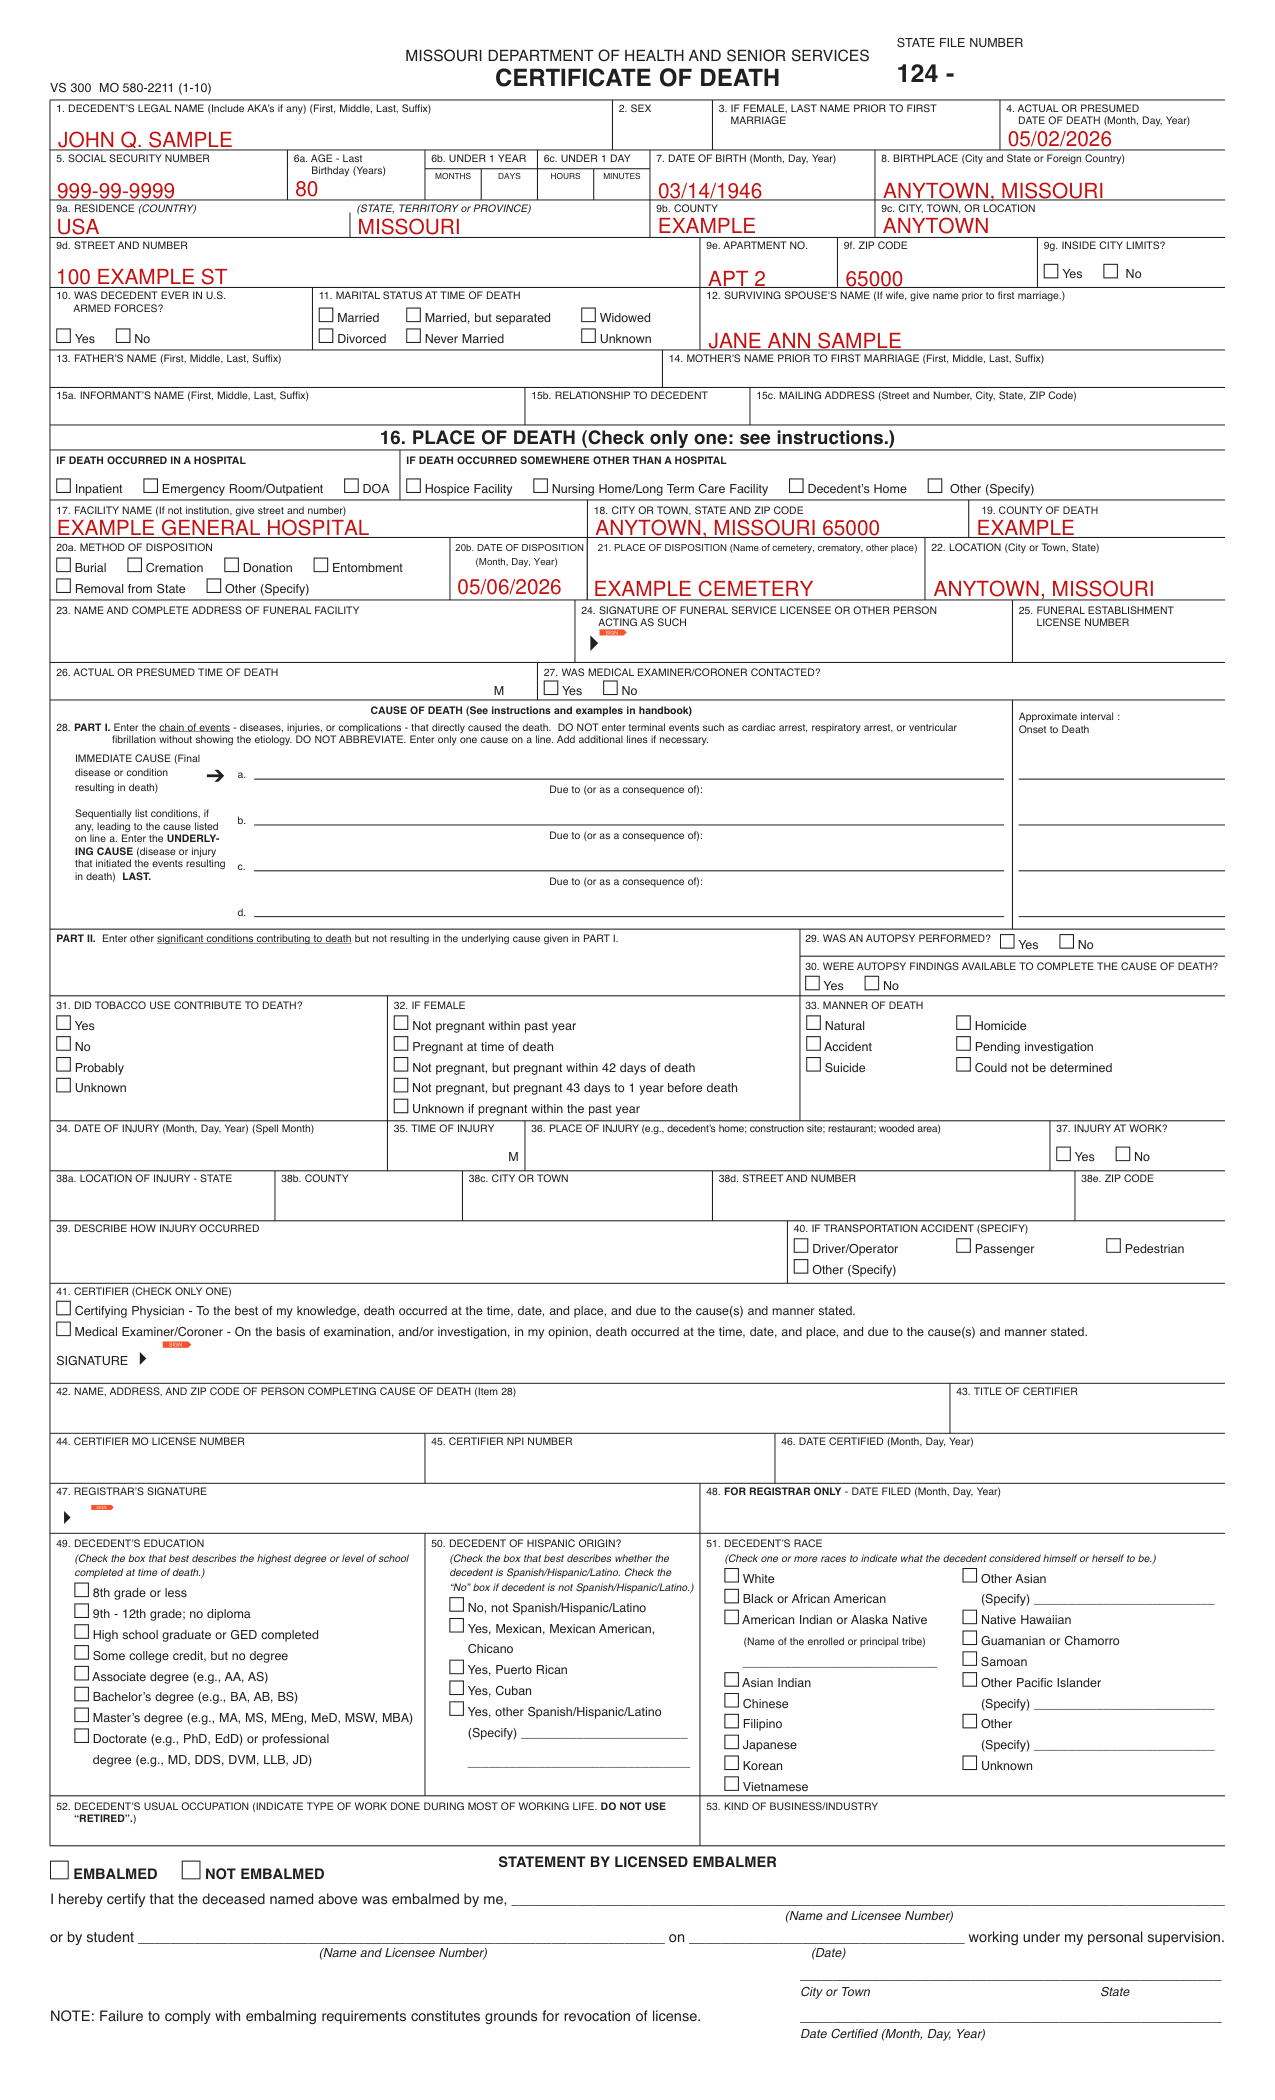
How to fill out Certificate of Death VS 300 (MO 580-2211), box by box
1. DECEDENTʼS LEGAL NAME and 4. ACTUAL OR PRESUMED DATE OF DEATH
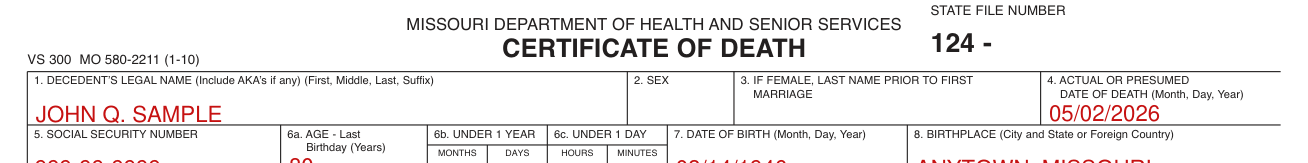
In box 1, enter the decedentʼs legal name (include AKAʼs if any) as First, Middle, Last, Suffix. Box 2 is sex. In box 3, if female, enter the last name prior to first marriage.
In box 4, enter the actual or presumed date of death (Month, Day, Year).
5. SOCIAL SECURITY NUMBER, 6a. AGE, 7. DATE OF BIRTH and 8. BIRTHPLACE

Enter the social security number in box 5 and the age at last birthday (years) in box 6a. For box 6b, under 1 year, or box 6c, under 1 day, enter months, days, hours, minutes. Enter the date of birth (Month, Day, Year) in box 7 and the birthplace (City and State or Foreign Country) in box 8.
9a. RESIDENCE to 9g. INSIDE CITY LIMITS?
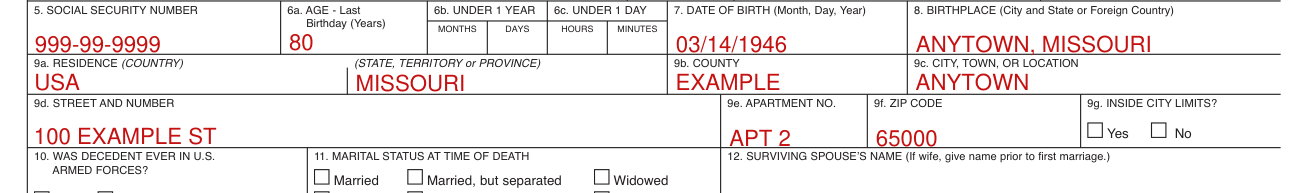
In boxes 9a to 9c, enter the residence (country), the state, territory or province, the county, and the city, town, or location.
In boxes 9d to 9f, enter the street and number, the apartment no. and the ZIP code; for box 9g, inside city limits, mark Yes or No.
10. WAS DECEDENT EVER IN U.S. ARMED FORCES? and 11. MARITAL STATUS AT TIME OF DEATH

For box 10, was decedent ever in U.S. armed forces, mark Yes or No.
For box 11, marital status at time of death, mark Married, Married, but separated, Widowed, Divorced, Never Married or Unknown.
In box 12, enter the surviving spouseʼs name (if wife, give name prior to first marriage).
13. FATHERʼS NAME to 15c. MAILING ADDRESS
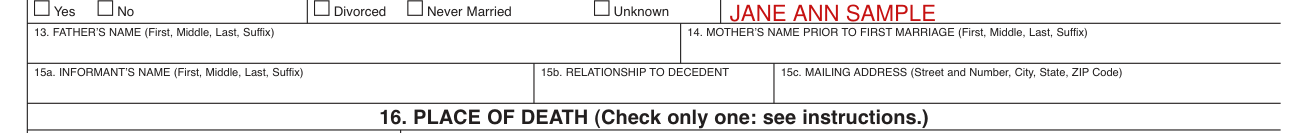
Enter the fatherʼs name in box 13 and the motherʼs name prior to first marriage in box 14, each as First, Middle, Last, Suffix.
Enter the informantʼs name (First, Middle, Last, Suffix) in box 15a, the relationship to decedent in box 15b, and the mailing address (Street and Number, City, State, ZIP Code) in box 15c.
16. PLACE OF DEATH, 17. FACILITY NAME to 19. COUNTY OF DEATH
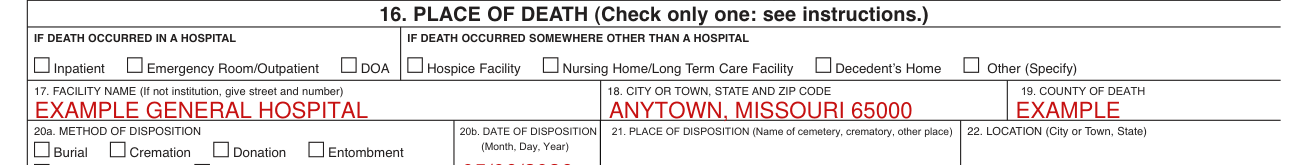
For box 16, place of death, check only one: see instructions.
If death occurred in a hospital, mark Inpatient, Emergency Room/Outpatient or DOA.
If death occurred somewhere other than a hospital, mark Hospice Facility, Nursing Home/Long Term Care Facility, Decedentʼs Home or Other (Specify).
In box 17, enter the facility name (if not institution, give street and number); in box 19, enter the county of death.
In box 18, enter the city or town, state and ZIP code.
20a. METHOD OF DISPOSITION to 22. LOCATION

For box 20a, method of disposition, mark Burial, Cremation, Donation, Entombment, Removal from State or Other (Specify).
In box 20b, enter the date of disposition (Month, Day, Year).
In box 21, enter the place of disposition (name of cemetery, crematory, other place); in box 22, enter the location (city or town, state).
23. NAME AND COMPLETE ADDRESS OF FUNERAL FACILITY to 25. FUNERAL ESTABLISHMENT LICENSE NUMBER

In box 23, enter the name and complete address of funeral facility; box 24 is the signature of funeral service licensee or other person acting as such; in box 25, enter the funeral establishment license number.
26. ACTUAL OR PRESUMED TIME OF DEATH and 27. WAS MEDICAL EXAMINER/CORONER CONTACTED?
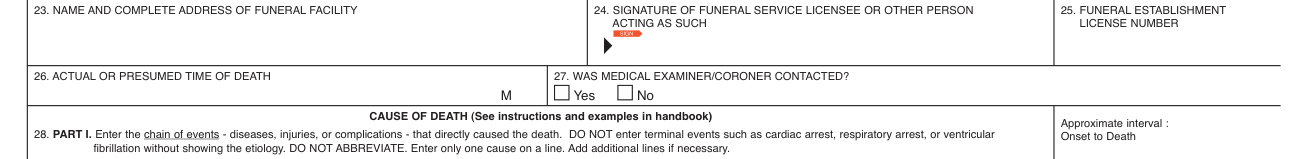
In box 26, enter the actual or presumed time of death.
For box 27, was medical examiner/coroner contacted, mark Yes or No.
28. CAUSE OF DEATH
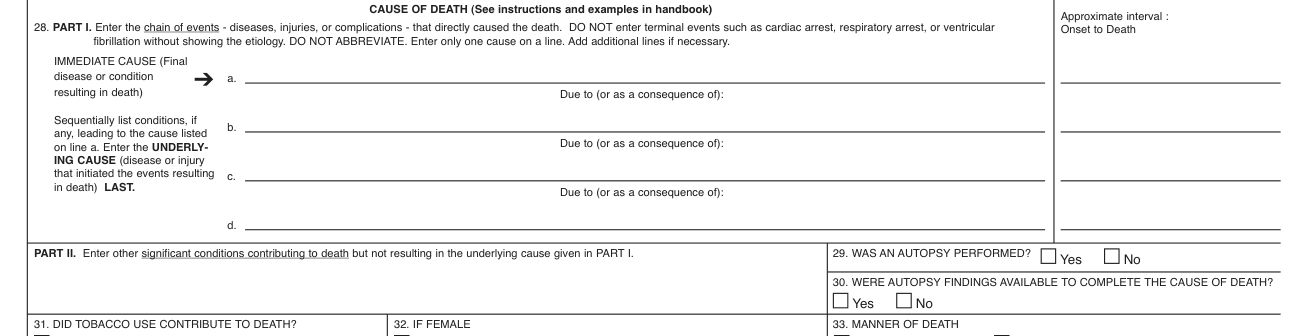
In box 28, Part I, enter the chain of events that directly caused the death; do not enter terminal events such as cardiac arrest, respiratory arrest, or ventricular fibrillation without showing the etiology; do not abbreviate, enter only one cause on a line, and add additional lines if necessary.
Line a is the immediate cause (final disease or condition resulting in death); sequentially list conditions, if any, leading to the cause listed on line a, and enter the underlying cause last.
Enter the approximate interval: onset to death.
In Part II, enter other significant conditions contributing to death but not resulting in the underlying cause given in Part I. For box 29, was an autopsy performed, mark Yes or No.
29. AUTOPSY to 33. MANNER OF DEATH

For box 30, were autopsy findings available to complete the cause of death, mark Yes or No.
For box 31, did tobacco use contribute to death, mark Yes, No, Probably or Unknown.
For box 32, if female, mark Not pregnant within past year or Pregnant at time of death.
For box 32, if female, you can also mark Not pregnant, but pregnant within 42 days of death, Not pregnant, but pregnant 43 days to 1 year before death, or Unknown if pregnant within the past year.
For box 33, manner of death, mark Natural, Homicide, Accident, Pending investigation, Suicide or Could not be determined.
34. DATE OF INJURY to 40. IF TRANSPORTATION ACCIDENT
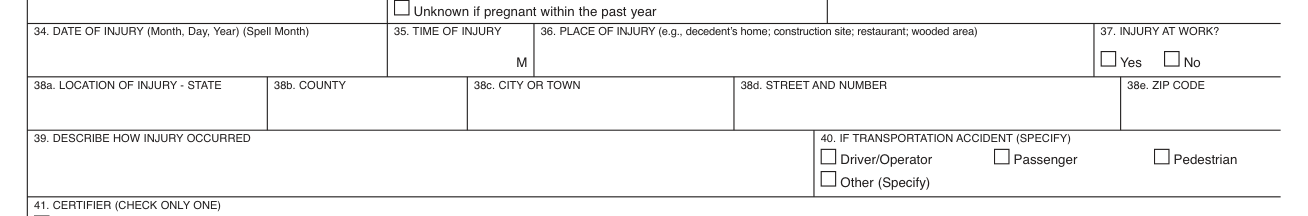
Enter the date of injury (Month, Day, Year) (Spell Month) in box 34 and the time of injury in box 35.
In box 36, enter the place of injury (e.g., decedentʼs home; construction site; restaurant; wooded area); for box 37, injury at work, mark Yes or No.
In boxes 38a to 38e, enter the location of injury: state, county, city or town, street and number, ZIP code.
In box 39, describe how injury occurred. In box 40, if transportation accident, mark Driver/Operator, Passenger, Pedestrian or Other (Specify).
41. CERTIFIER to 46. DATE CERTIFIED

For box 41, certifier, check only one.
Certifying Physician: To the best of my knowledge, death occurred at the time, date, and place, and due to the cause(s) and manner stated.
Medical Examiner/Coroner: On the basis of examination, and/or investigation, in my opinion, death occurred at the time, date, and place, and due to the cause(s) and manner stated.
In box 42, enter the name, address, and ZIP code of person completing cause of death (item 28); in box 43, enter the title of certifier.
In box 44, enter the certifier MO license number; in box 45, the certifier NPI number; in box 46, the date certified (Month, Day, Year).
49. DECEDENTʼS EDUCATION to 53. KIND OF BUSINESS/INDUSTRY

For box 49, decedentʼs education, check the box that best describes the highest degree or level of school completed at time of death.
For box 50, decedent of Hispanic origin, check the box that best describes whether the decedent is Spanish/Hispanic/Latino; check the No box if decedent is not Spanish/Hispanic/Latino.
For box 51, decedentʼs race, check one or more races to indicate what the decedent considered himself or herself to be.
In box 52, enter the decedentʼs usual occupation (indicate type of work done during most of working life); do not use retired. In box 53, enter the kind of business/industry.
STATEMENT BY LICENSED EMBALMER
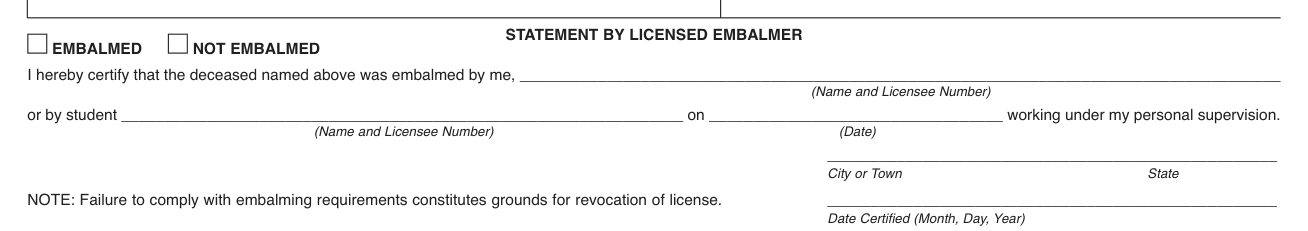
In the statement by licensed embalmer, mark Embalmed or Not Embalmed and enter the Name and Licensee Number.
Or by student (Name and Licensee Number) working under my personal supervision, on (Date).
Enter the city or town, state and date certified (Month, Day, Year). Failure to comply with embalming requirements constitutes grounds for revocation of license.
Sources
[1] Certificate of Death VS 300, MO 580-2211 (1-10), Missouri Department of Health and Senior Services (the Official source link on this page).