


Form PH-1659 at a glance
What it is: This form is the Tennessee Department of Health Certificate of Death.
Who signs: The physician or medical examiner executing cause of death must complete and sign within 48 hours.
A filled-in Form PH-1659 example: a physician certifies a hospital death
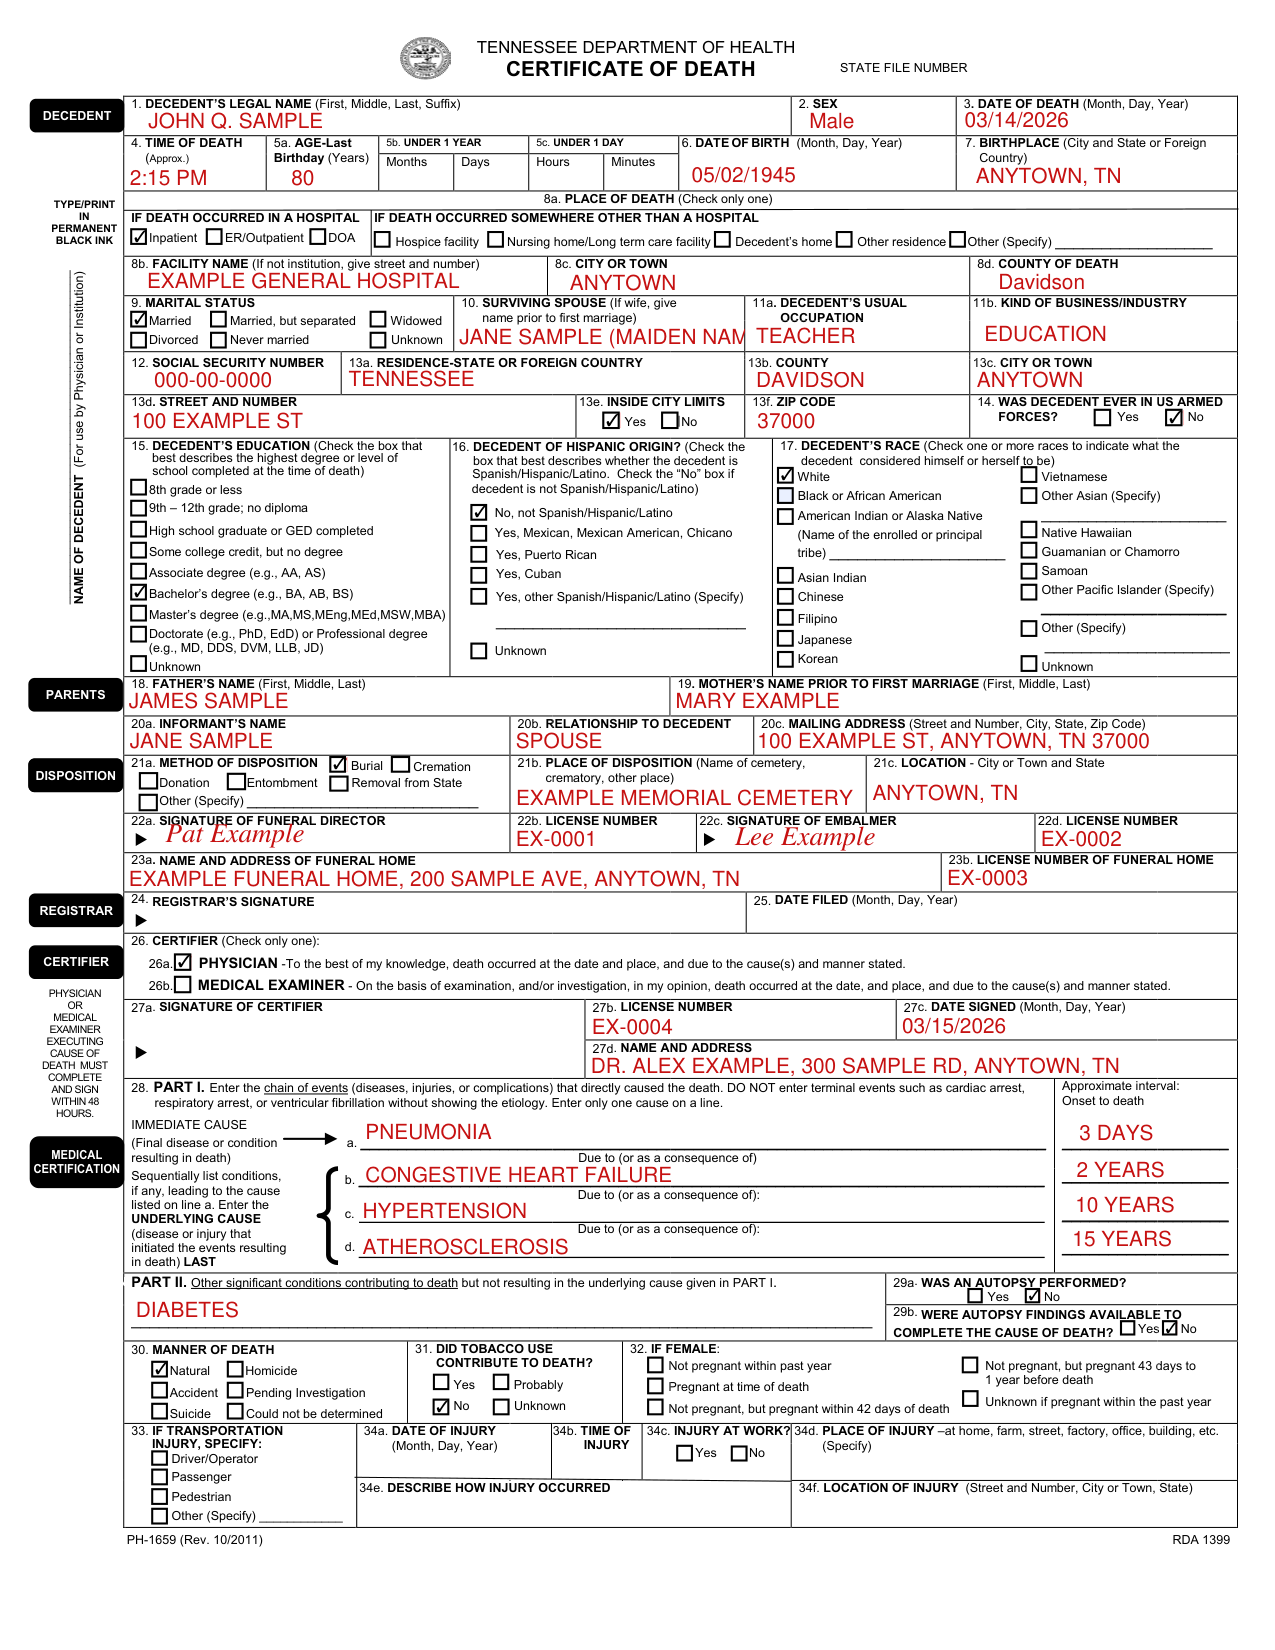
How to fill out Form PH-1659, box by box
Boxes 1 to 7: the decedent
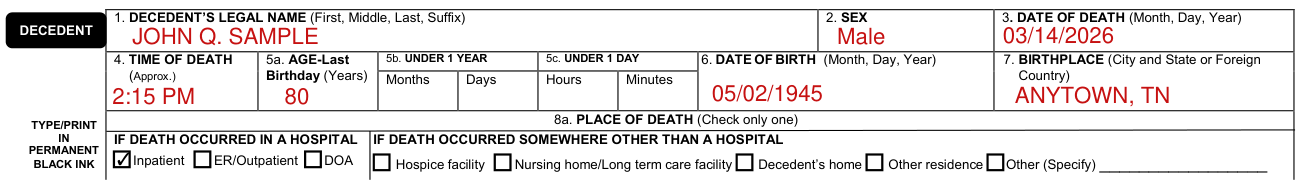
In Box 1, enter the decedent's legal name (First, Middle, Last, Suffix); in Box 2, the sex.
In Box 3, enter the date of death (Month, Day, Year); in Box 4, the time of death (Approx.).
In Box 5a, enter the age, last birthday (Years). Under 1 year, enter Months and Days in Box 5b; under 1 day, enter Hours and Minutes in Box 5c. In Box 6, enter the date of birth (Month, Day, Year).
In Box 7, enter the birthplace (City and State or Foreign Country).
8a. Place of death (Check only one)

In Box 8a, check only one place of death. If death occurred in a hospital, check Inpatient, ER/Outpatient or DOA.
If death occurred somewhere other than a hospital, check Hospice facility, Nursing home/Long term care facility, Decedent's home, Other residence or Other (Specify).
In Box 8b, enter the facility name (If not institution, give street and number); in Box 8c, the city or town; in Box 8d, the county of death.
9. Marital status and 10. Surviving spouse

In Box 9, check the marital status: Married, Married, but separated, Widowed, Divorced, Never married or Unknown.
In Box 10, enter the surviving spouse (If wife, give name prior to first marriage).
Boxes 11 to 13: occupation, social security number and residence
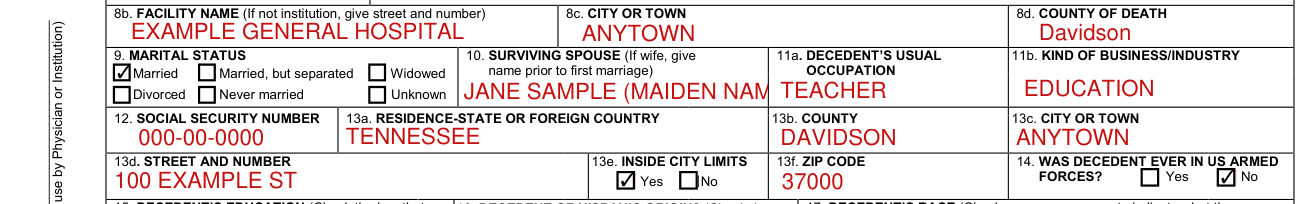
In Box 11a, enter the decedent's usual occupation; in Box 11b, the kind of business/industry.
In Box 12, enter the social security number.
In Box 13a, enter the residence-state or foreign country; in Box 13b, the county; in Box 13c, the city or town; in Box 13d, the street and number; in Box 13f, the ZIP code.
In Box 13e, inside city limits, check Yes or No.
Boxes 14 to 17: armed forces, education, Hispanic origin and race
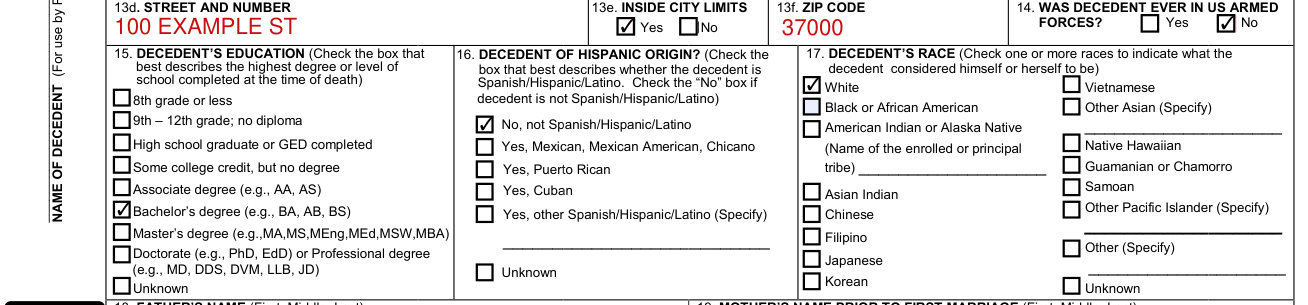
In Box 14, check Yes or No: was decedent ever in armed forces? In Box 15, check the box that best describes the highest degree or level of school completed at the time of death: 8th grade or less, 9th - 12th grade; no diploma, High school graduate or GED completed, Some college credit, but no degree, Associate degree (e.g., AA, AS), Bachelor's degree (e.g., BA, AB, BS), Master's degree (e.g.,MA,MS,MEng,MEd,MSW,MBA), Doctorate or Professional degree or Unknown.
In Box 16, check the box that best describes whether the decedent is Spanish/Hispanic/Latino: No, not Spanish/Hispanic/Latino, Yes, Mexican, Mexican American, Chicano, Yes, Puerto Rican, Yes, Cuban, Yes, other Spanish/Hispanic/Latino (Specify) or Unknown. Check the “No” box if decedent is not Spanish/Hispanic/Latino.
In Box 17, check one or more races to indicate what the decedent considered himself or herself to be: White, Black or African American, American Indian or Alaska Native (Name of the enrolled or principal tribe), Asian Indian, Chinese, Filipino, Japanese, Korean, Vietnamese, Other Asian (Specify), Native Hawaiian, Guamanian or Chamorro, Samoan, Other Pacific Islander (Specify), Other (Specify) or Unknown.
Boxes 18 to 23: parents, informant, disposition and funeral home
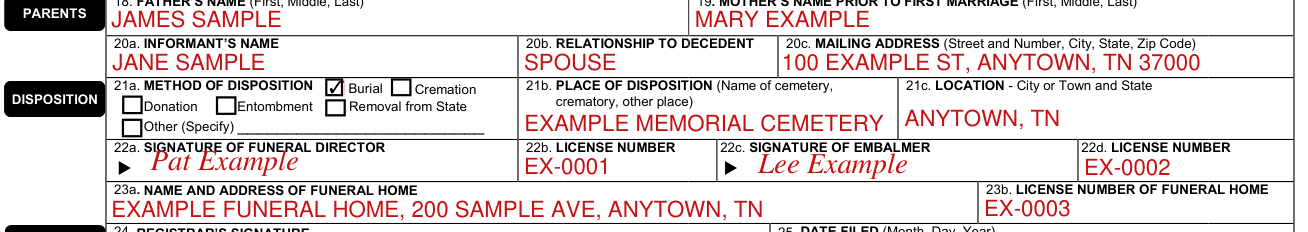
In Box 18, enter the father's name (First, Middle, Last).
In Box 19, enter the mother's name prior to first marriage (First, Middle, Last). In Box 20a, enter the informant's name; in Box 20b, the relationship to decedent.
In Box 20c, enter the mailing address (Street and Number, City, State, Zip Code). In Box 21a, check the method of disposition: Burial, Cremation, Donation, Entombment, Removal from State or Other (Specify).
In Box 21b, enter the place of disposition (Name of cemetery, crematory, other place); in Box 21c, the location - City or Town and State.
In Box 22a, the funeral director signs on the signature of funeral director line; in Box 22b, enter the license number; in Box 22c, the embalmer signs on the signature of embalmer line; in Box 22d, enter the license number. In Box 23a, enter the name and address of funeral home; in Box 23b, the license number of funeral home.
26. Certifier (Check only one)
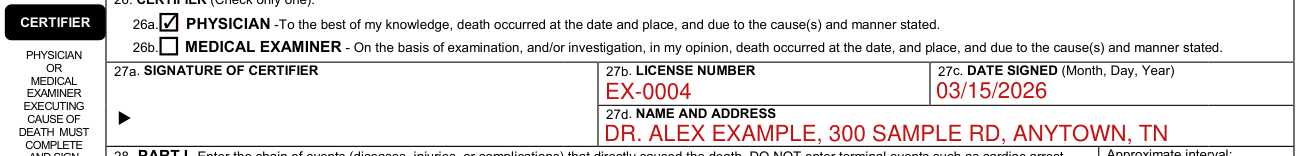
In Box 26, check only one: Physician (To the best of my knowledge, death occurred at the date and place, and due to the cause(s) and manner stated) or Medical Examiner (On the basis of examination, and/or investigation, in my opinion, death occurred at the date, and place, and due to the cause(s) and manner stated).
In Box 27a, the certifier signs; in Box 27b, enter the license number; in Box 27c, the date signed (Month, Day, Year); in Box 27d, the name and address.
28. Cause of death
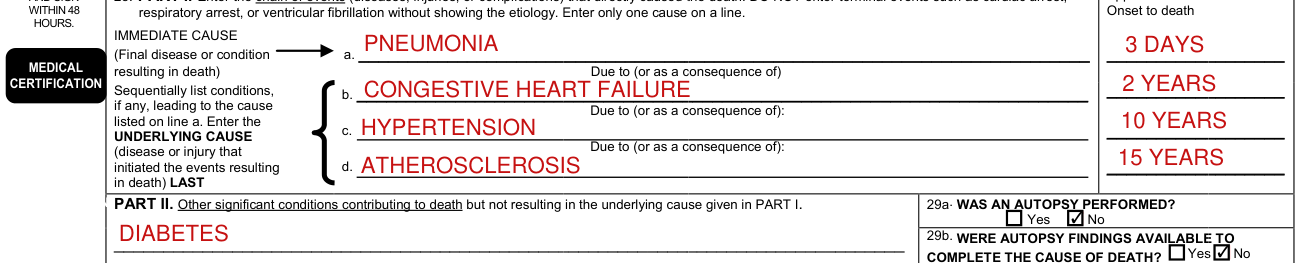
In PART I, enter the chain of events (diseases, injuries, or complications) that directly caused the death. DO NOT enter terminal events such as cardiac arrest, respiratory arrest, or ventricular fibrillation without showing the etiology. Enter only one cause on a line. On line a, enter the IMMEDIATE CAUSE (Final disease or condition resulting in death).
Sequentially list conditions, if any, leading to the cause listed on line a. Enter the UNDERLYING CAUSE (disease or injury that initiated the events resulting in death) LAST.
On each line, enter the Approximate interval: Onset to death.
In PART II, enter other significant conditions contributing to death but not resulting in the underlying cause given in PART I.
29. Autopsy

In Box 29a, check Yes or No: was an autopsy performed? In Box 29b, check Yes or No: were autopsy findings available to complete the cause of death?
30. Manner of death and 31. Tobacco use

In Box 30, check the manner of death: Natural, Homicide, Accident, Pending Investigation, Suicide or Could not be determined.
In Box 31, check Yes, Probably, No or Unknown: did tobacco use contribute to death?
32. If female

In Box 32, if female, check Not pregnant within past year, Pregnant at time of death, Not pregnant, but pregnant within 42 days of death, Not pregnant, but pregnant 43 days to 1 year before death or Unknown if pregnant within the past year.
33. If transportation injury, specify

In Box 33, if transportation injury, specify: Driver/Operator, Passenger, Pedestrian or Other (Specify).
34. Injury

If there was an injury, in Box 34a, enter the date of injury (Month, Day, Year); in Box 34b, the time of injury.
If there was an injury, in Box 34c, check Yes or No: injury at work? If there was an injury, in Box 34d, enter the place of injury -at home, farm, street, factory, office, building, etc. (Specify).
If there was an injury, in Box 34e, describe how injury occurred; in Box 34f, enter the location of injury (Street and Number, City or Town, State).
More rules for Form PH-1659
Type/print in permanent black ink.
Common questions about Form PH-1659
Is there a deadline?
The physician or medical examiner executing cause of death must complete and sign within 48 hours.
Sources
[1] Form PH-1659 (Rev. 10/2011), Tennessee Department of Health Certificate of Death (the Official source link on this page).