


Form NF-5 at a glance
What it is: Form NF-5 is the Hospital Facility Form of the New York Motor Vehicle No-Fault Insurance Law.
Who signs: Enter the signature of patient, parent or guardian and the date. Under Taken by, enter the print name, title and phone no., signature and date. Enter the date taken from records. Under A, signed lines: the signature of patient, parent or guardian, the signature of hospital representative, and the date. Under B, Assignment of no-fault benefits, signed lines: the signature of patient, parent or guardian (Assignor) and the date, and the hospital name (Assignee) and the hospital representative.
A filled-in Form NF-5 example: a hospital clerk completes the form for a passenger

How to fill out Form NF-5, box by box
Insurance company and patient
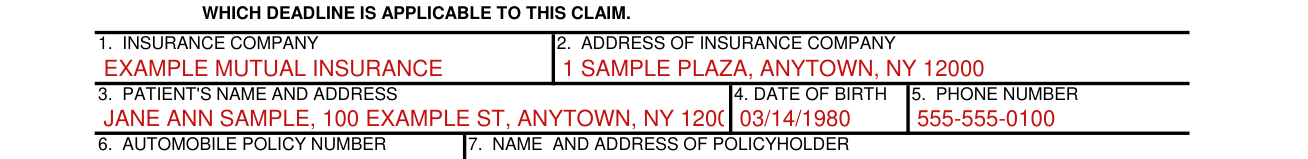
In boxes 1 and 2, enter the insurance company and the address of the insurance company.
In boxes 3, 4 and 5, enter the patient's name and address, date of birth and phone number.
Policy number, policyholder and the accident, admission and discharge dates

In boxes 6 and 7, enter the automobile policy number and the name and address of the policyholder.
In boxes 8, 9 and 10, enter the accident date, admission date and discharge date.
Place and description of accident
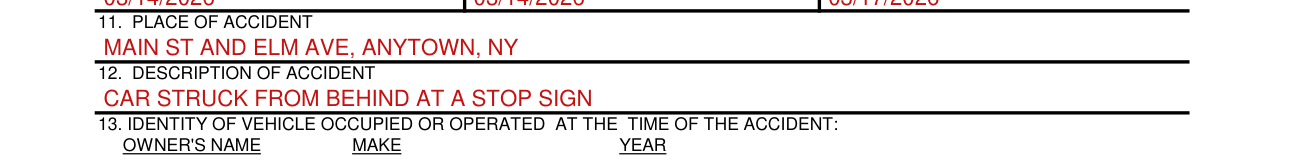
In box 11, enter the place of accident. In box 12, enter the description of accident.
Identity of vehicle occupied or operated
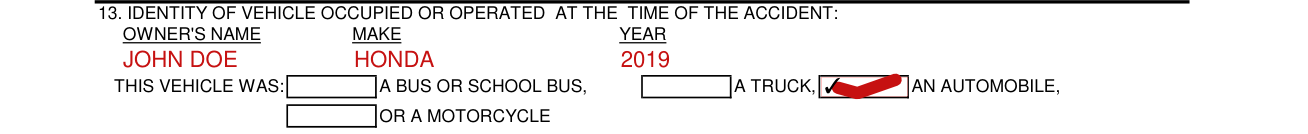
In box 13, enter the identity of the vehicle occupied or operated at the time of the accident: the owner's name, make and year. Mark if this vehicle was a bus or school bus, a truck, an automobile, or a motorcycle.
Was patient the driver, a passenger, a pedestrian or a member of the household
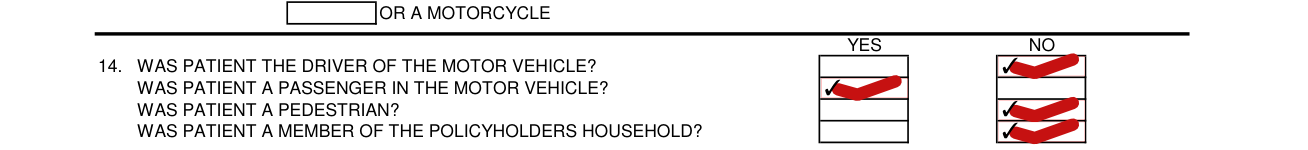
In box 14, Yes or No: was the patient the driver of the motor vehicle, a passenger in the motor vehicle, a pedestrian, or a member of the policyholder's household?
Admitting diagnosis and discharge diagnosis

In box 15, enter the admitting diagnosis. In box 16, enter the discharge diagnosis.
Condition due to injury arising out of patient's employment

In box 17, Yes or No: is the condition due to injury arising out of the patient's employment?
Treatment rendered solely as a result of injuries arising out of the above accident, if no, please explain

In box 18, Yes or No: was treatment rendered solely as a result of injuries arising out of the above accident? If no, please explain.
Operations or procedures performed and the attached report
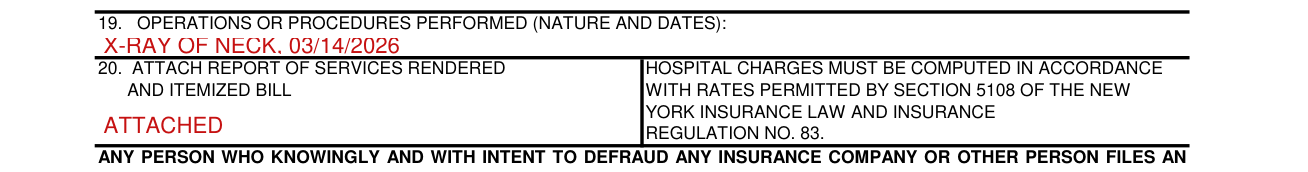
In box 19, enter the operations or procedures performed (nature and dates).
For box 20, attach report of services rendered and itemized bill. Hospital charges must be computed in accordance with rates permitted by section 5108 of the New York Insurance Law and Insurance Regulation No. 83.
Taken by

Under Taken by, enter the print name, title and phone no., signature and date. Enter the date taken from records.
Patient signature under the penalties of perjury

On page 2, the applicant authorizes the insurer to submit any and all of these forms to another party or insurer if such is necessary to perfect its rights of recovery provided for under this act. This form is subscribed and affirmed by the patient as true under the penalties of perjury.
A. Authorization to pay benefits

Your health provider may agree to accept payment for health services performed directly from your insurer (Authorization to Pay Benefits) so that you are not required to make payment to the health provider at the time of service. Such agreement is optional on the part of the health provider and must be signed by both patient and health provider. You may use the optional authorization language provided on the form, by checking off the designated spot in item A.
If you have chosen to authorize the direct payment of benefits by checking this option, you may not also enter into an assignment of benefits contained in item B.
Under A, signed lines: the signature of patient, parent or guardian, the signature of hospital representative, and the date.
B. Assignment of no-fault benefits

Your health provider may agree to have you assign your right to No-Fault benefits from your insurer directly to your health provider (Assignment of Benefits). If you and your health provider agree to an assignment of benefits, you must both sign the agreement contained in item B or the prescribed NF-AOB form or its equivalent. The language contained in the assignment of benefits is mandatory and may not be altered or avoided by any other language added to this agreement or other written agreement.
If you have chosen to assign your benefits to the health provider by checking this option, you may not also enter into an authorization to pay benefits contained in item A.
Original authorization or assignment executed, and signature on file

Yes or No: has an original authorization or assignment previously been executed? Yes or No: is the original signature of the parties on file?
Authorization for release of health service or treatment information

Authorization for release of health service or treatment information: this authorization or photocopy thereof will authorize you to furnish all information you may have regarding my condition while under your observation or treatment, including the history obtained, x-ray and physical findings, diagnosis and prognosis. You are authorized to provide this information in accordance with the New York Comprehensive Motor Vehicle Insurance Reparations Act (No-Fault Law). Enter the signature (patient, parent or guardian) and the date.
Submitting the form and false statements
Submit this completed form
The completed form must be submitted to the insurer as soon as reasonably possible but no later than 45 days or 180 days after treatment date, depending upon the policy endorsement in effect at the time of the accident. If you are unsure of the applicable time requirement, contact the claim representative to determine which deadline is applicable to this claim.
Any person who files a statement of claim containing any materially false information
Any person who knowingly and with intent to defraud any insurance company or other person files an application for commercial insurance or a statement of claim for any commercial or personal insurance benefits containing any materially false information, or conceals for the purpose of misleading, information concerning any fact material thereto, and any person who, in connection with such application or claim, knowingly makes or knowingly assists, abets, solicits or conspires with another to make a false report of the theft, destruction, damage or conversion of any motor vehicle to a law enforcement agency, the Department of Motor Vehicles or an insurance company, commits a fraudulent insurance act, which is a crime, and shall also be subject to a civil penalty not to exceed five thousand dollars and the value of the subject motor vehicle or stated claim for each violation.
Sources
[1] Form NF-5 (Rev 6/2013), Hospital Facility Form, New York State Department of Financial Services (the Official source link on this page).