

Form OMH 11 at a glance
What it is: Form OMH 11 of the State of New York Office of Mental Health is the Authorization for Release of Information.
Who signs: Sign at SIGN on the Signature of Patient or Personal Representative line and enter the Date.
A filled-in Form OMH 11 example: a patient completes the authorization herself

How to fill out Form OMH 11, box by box
Patient's Name, Sex, Date of Birth and Facility Name

Enter the Patient's Name (Last, First, M.I.) and “C” No., the Sex and the Date of Birth, then the Facility Name and the Unit/Ward/Residence No.
Description of Information to be Used/Disclosed

In PART 1: Authorization to Release Information, enter the Description of Information to be Used/Disclosed.
Purpose or Need for Information

Under Purpose or Need for Information, in 1, mark either "by the individual or his/her personal representative for release to a person or entity with a demonstrable need for the information" or Other (please describe) and write the description on the line.
In 2, describe the purpose of the disclosure.
From and To

Under From, enter the Name, Address, & Title of the Person/Organization/Facility/Program Disclosing Information.
Under To, enter the Name, Address, & Title of the Person/Organization/Facility/Program to Which this Disclosure is to be Made. If the same information is to be disclosed to multiple parties for the same purpose, for the same period of time, this authorization will apply to all parties listed here.
Right to revoke

In 4, insert the name of the facility/program: the revocation must be in writing on the form provided by that facility/program.
The revocation will not be effective if the persons authorized to use and/or disclose the protected health information have already taken action because of the earlier authorization.
I do not have to sign this authorization and that my refusal to sign will not affect my abilities to obtain treatment from the New York State Office of Mental Health, nor will it affect my eligibility for benefits.
One-Time Use/Disclosure
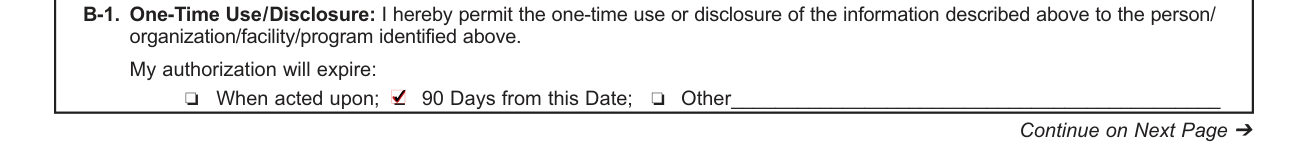
In B-1, One-Time Use/Disclosure, mark when the authorization will expire: When acted upon, 90 Days from this Date, or Other.
Page 2: Facility/Agency Name and Patient's Name

At the top of page 2, enter the Facility/Agency Name, the Patient's Name (Last, First, M.I.) and the “C”/Id. No.
Periodic Use/Disclosure

B-2. Periodic Use/Disclosure: I hereby authorize the periodic use/disclosure of the information described in this form to the person/organization/facility/program identified in this form as often as necessary to fulfill the purpose identified in this form. My authorization will expire: When I am no longer receiving services from the facility/program you name; One year from this date; or Other.
Patient Signature
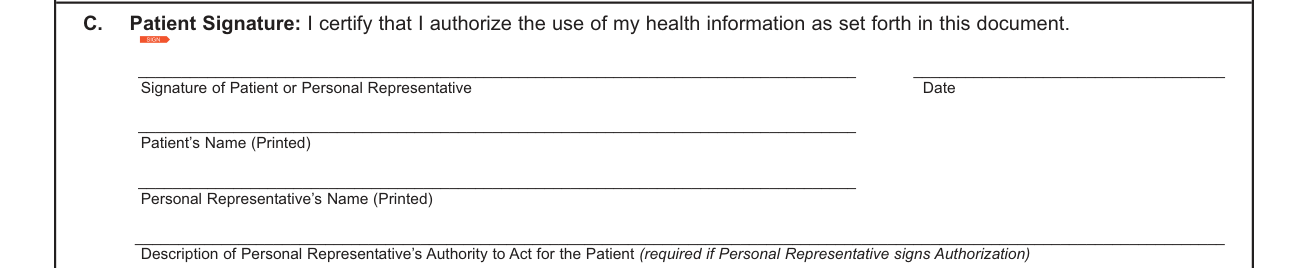
C. Patient Signature: by signing, you certify that you authorize the use of your health information as set forth in this document.
Sign at SIGN on the Signature of Patient or Personal Representative line and enter the Date.
Print the Patient's Name and, if a personal representative signs, the Personal Representative's Name.
Enter the Description of Personal Representative's Authority to Act for the Patient (required if Personal Representative signs Authorization).
Witness Statement/Signature

D. Witness Statement/Signature: I have witnessed the execution of this authorization and state that a copy of the signed authorization was provided to the patient and/or the patient's personal representative.
After WITNESSED BY, enter the Staff person's name and title, then Authorization Provided To and the Date.
To be Completed by Facility
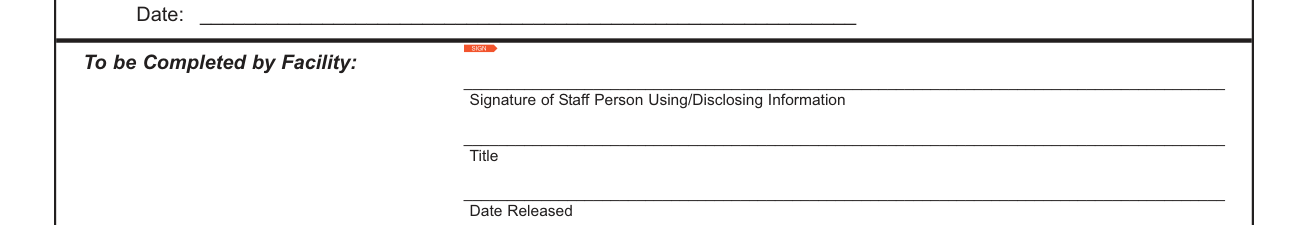
Under To be Completed by Facility, the staff person using/disclosing information signs on the Signature of Staff Person Using/Disclosing Information line and enters the Title and the Date Released.
Revocation of Authorization to Release Information
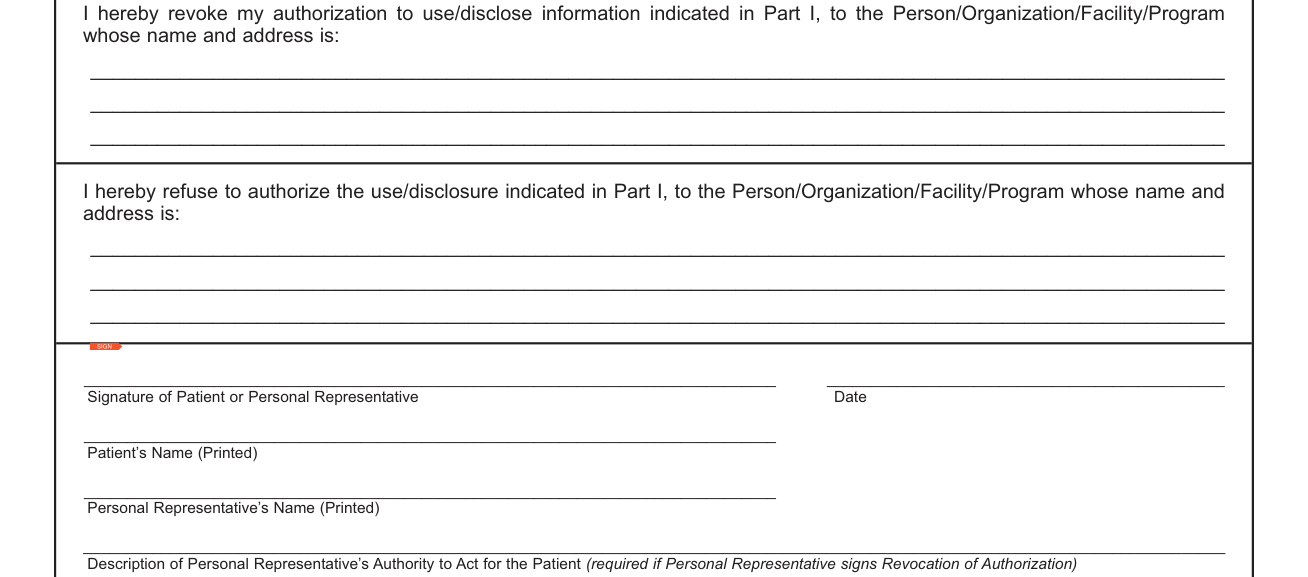
Only to revoke this authorization: in PART 2: Revocation of Authorization to Release Information, under "I hereby revoke my authorization to use/disclose information indicated in Part I", enter the name and address of the Person/Organization/Facility/Program.
Only to refuse the use/disclosure: under "I hereby refuse to authorize the use/disclosure indicated in Part I", enter the name and address of the Person/Organization/Facility/Program.
Sign at SIGN on the Signature of Patient or Personal Representative line with the Date, and print the Patient's Name and, if a personal representative signs, the Personal Representative's Name.
If the Personal Representative signs the Revocation of Authorization, the Description of Personal Representative's Authority to Act for the Patient is required.
More rules for Form OMH 11
A. I hereby permit the use or disclosure of the information described in this form to the Person/Organization/Facility/Program(s) identified in this form. I understand that: 1. Only the information described in this form may be used and/or disclosed as a result of this authorization. 2. This information is confidential and is protected under federal privacy regulations (HIPAA) and the NYS Mental Hygiene Law and cannot legally be disclosed without my permission. 3. If this information is disclosed to someone who is not required to comply with HIPAA, then it could be redisclosed and would no longer be protected by HIPAA. However, this information will still be protected under the NYS Mental Hygiene law, which prohibits this information from being redisclosed by anyone who receives it unless the redisclosure is permitted by the NYS law (Mental Hygiene Law §33.13).
Who completes it and other situations
Sources
[1] Form OMH 11, Authorization for Release of Information, State of New York Office of Mental Health (the Official source link on this page).