


Form PA 635 at a glance
What it is: This Medical Assessment Form (PA 635) is needed to determine whether an individual is able to participate in employment and training activities, what treatment plan(s) could help the individual move towards employment, or determine if the individual is a good candidate for disability benefits or is pregnant.
Who signs: Instructions to Medical Provider: This form may be completed by a counselor, social worker, or mental health therapist, but must be agreed upon and signed by a physician, psychologist, physician assistant or certified registered nurse practitioner.
COMPLETED BY COUNTY ASSISTANCE OFFICE: the boxes below it are completed by the county assistance office. In the Instructions to Medical Provider, the medical provider completes the appropriate section(s) of this form.
A filled-in Form PA 635 example: the county assistance office prepares the form for a client

How to fill out Form PA 635, box by box
Tap a group of boxes to open it, and a picture to see it full size.
County assistance office and case identification
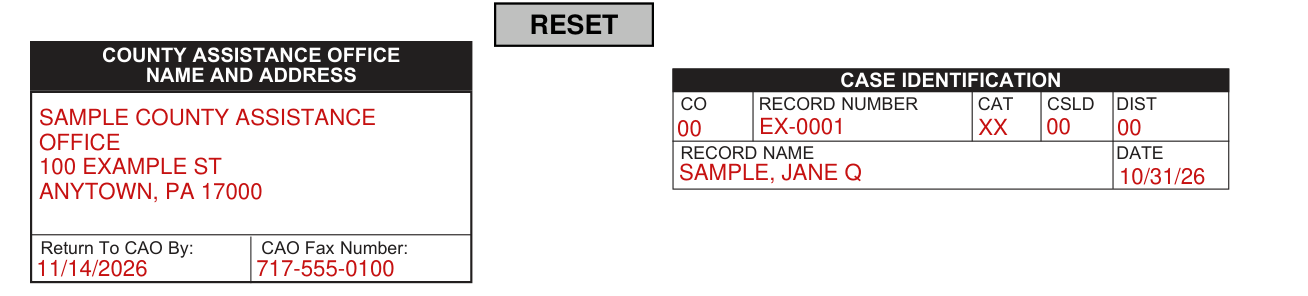
Fill in COUNTY ASSISTANCE OFFICE NAME AND ADDRESS, Return To CAO By and CAO Fax Number.
Fill in CASE IDENTIFICATION: CO, RECORD NUMBER, CAT, CSLD, DIST, RECORD NAME and DATE.
Completed by county assistance office: the client's boxes
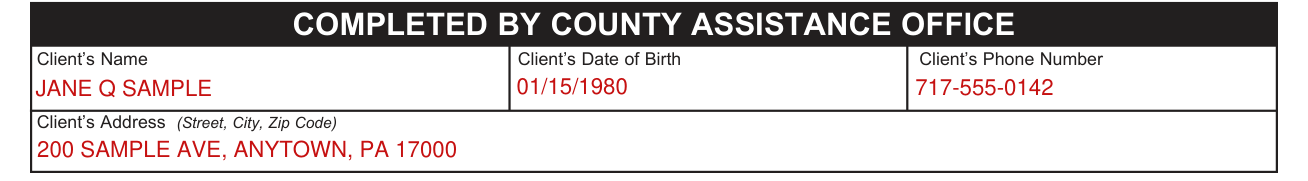
Under COMPLETED BY COUNTY ASSISTANCE OFFICE, fill in Client's Name, Client's Date of Birth, Client's Phone Number and Client's Address (Street, City, Zip Code).
Instructions to Medical Provider

Instructions to Medical Provider: This form may be completed by a counselor, social worker, or mental health therapist, but must be agreed upon and signed by a physician, psychologist, physician assistant or certified registered nurse practitioner.
Complete the appropriate section(s) of this form and return (fax or mail) to the county assistance office (above) by ________________.
Confirmation of Pregnancy
Confirmation of Pregnancy: If this individual is pregnant, give expected delivery date.
Common mistake: NOTE: If pregnancy does not affect this individual's ability to work, only complete Section I of this form.
Section I, Medical Provider Information
SECTION I MEDICAL PROVIDER INFORMATION: Please complete this entire section.
Fill in Printed Name of Medical Provider, Medical License Number, NPI Number (If Applicable), Phone Number and Address.
Certification and signature
The medical provider certifies that all of the information provided on this form is true, correct and complete to the best of the provider's professional knowledge, and that the diagnosis and assessment related to this client's health condition are based on his/her medical condition as determined by examination and knowledge of this client's medical history.
The medical provider understands and agrees that the diagnosis and supporting documentation may be subject to review by the Department of Human Services Medical Review Team.
Common mistake: Signature of medical provider must be original or the form is invalid. Rubber stamps, labels or other reproductions are not acceptable.
Fill in Prepared by and its Date, then, after all of the information provided on this form is complete, sign on the line above Signature of Medical Provider and fill in its Date.
Top of pages 2 and 3
At the top of each of the next two pages, fill in County/Record Number, Client's Name and Date of Birth.
Section II, Employability: select one
Common mistake: SECTION II EMPLOYABILITY: If checkbox 1 is selected for this individual, do not complete Section III.
If employable, this individual will have the requirement to work or participate in training for ______ hours per week. Please select one of the following based on your best estimate of the individual's current capabilities.
Fill in the blank before HOURS PER WEEK: those are the hours that are required per week (see above).
1. Employable
This individual is able to work or participate in training, on a sustained basis, for the hours that are required per week (see above).
Check the box with the following reasonable accommodations and write them on the lines below.
2. Limited employability
Check box 2. Under it, please check all that apply. Please also complete Section III.
This individual is able to work or participate in training, on a sustained basis, for fewer than the hours that are required per week (see above).
Write approximately how many hours the individual can participate per week.
Check the box with the following reasonable accommodations and write them on the lines below.
What is the recommended treatment plan? Check Prescribed Medication, Therapy (fill in hours per week and Type), Follow-up with specialist (fill in Specialty, Name of Physician and Referral Made for Patient?) or Other (describe).
This individual is expected to be limited from being able to work or participate in training for the number of hours indicated above on a sustained basis, until ____ / ____ / ______ (Date).
3. Temporary incapacity
Please also complete Section III.
This individual's physical or mental condition precludes him/her from participating in any form of employment or training activity, on a sustained basis, at this time, but the condition is expected to improve within 12 months.
This individual's temporary incapacity is expected to prevent working or participation in training until ____/____/______ (Date).
What is the recommended treatment plan? Check Prescribed Medication, Therapy (fill in hours per week and Type), Follow-up with specialist (fill in Specialty, Name of Physician and Referral Made for Patient?) or Other (describe).
4. Disabled
Please also complete Section III.
This individual has a physical or mental condition that is expected to last for 12 months or more, and precludes any form of employment, on a sustained basis, of at least 30 hours per week.
The individual is a candidate for Social Security Disability or Supplemental Security Income.
Fill in the disability begin date (Date).
Section III, Diagnosis
SECTION III DIAGNOSIS (ES): Include name of each Diagnosis with ICD-10 code and description.
Please explain how each diagnosis affects the client's ability to work.
Fill in each Diagnosis that applies: Primary Diagnosis, Secondary Diagnosis, Tertiary Diagnosis, Other Diagnosis.
The individual is following the prescribed treatment plan. Mark Yes, No or Don't Know. If No, indicate:
Check Not taking medication as prescribed, Not following up with specialist, Not eligible or appropriate for needed medication or treatment (and Explain), or Other (describe).
Common questions about Form PA 635
Is there a deadline?
Return (fax or mail) to the county assistance office whose name and address are in the box COUNTY ASSISTANCE OFFICE NAME AND ADDRESS by ________________. The form also has a Return To CAO By box. The form does not say which one.
Where do I file it?
Return (fax or mail) the form to the county assistance office whose name and address are in the box COUNTY ASSISTANCE OFFICE NAME AND ADDRESS. To fax it, use the CAO Fax Number box.
Sources
[1] Form PA 635 (SG) (7/17), Medical Assessment Form, Pennsylvania Department of Human Services (the Official source link on this page).