
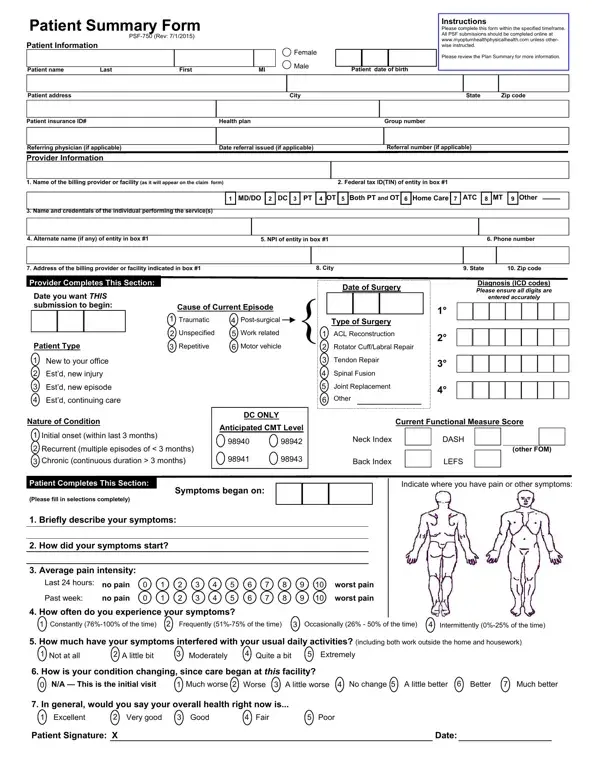

Patient Summary Form PSF-750 at a glance
What it is: The Patient Summary Form is form PSF-750 (Rev: 7/1/2015).
Who signs: Sign at Patient Signature: X and enter the Date.
A filled-in Patient Summary Form PSF-750 example: a patient fills out the form for a referred visit
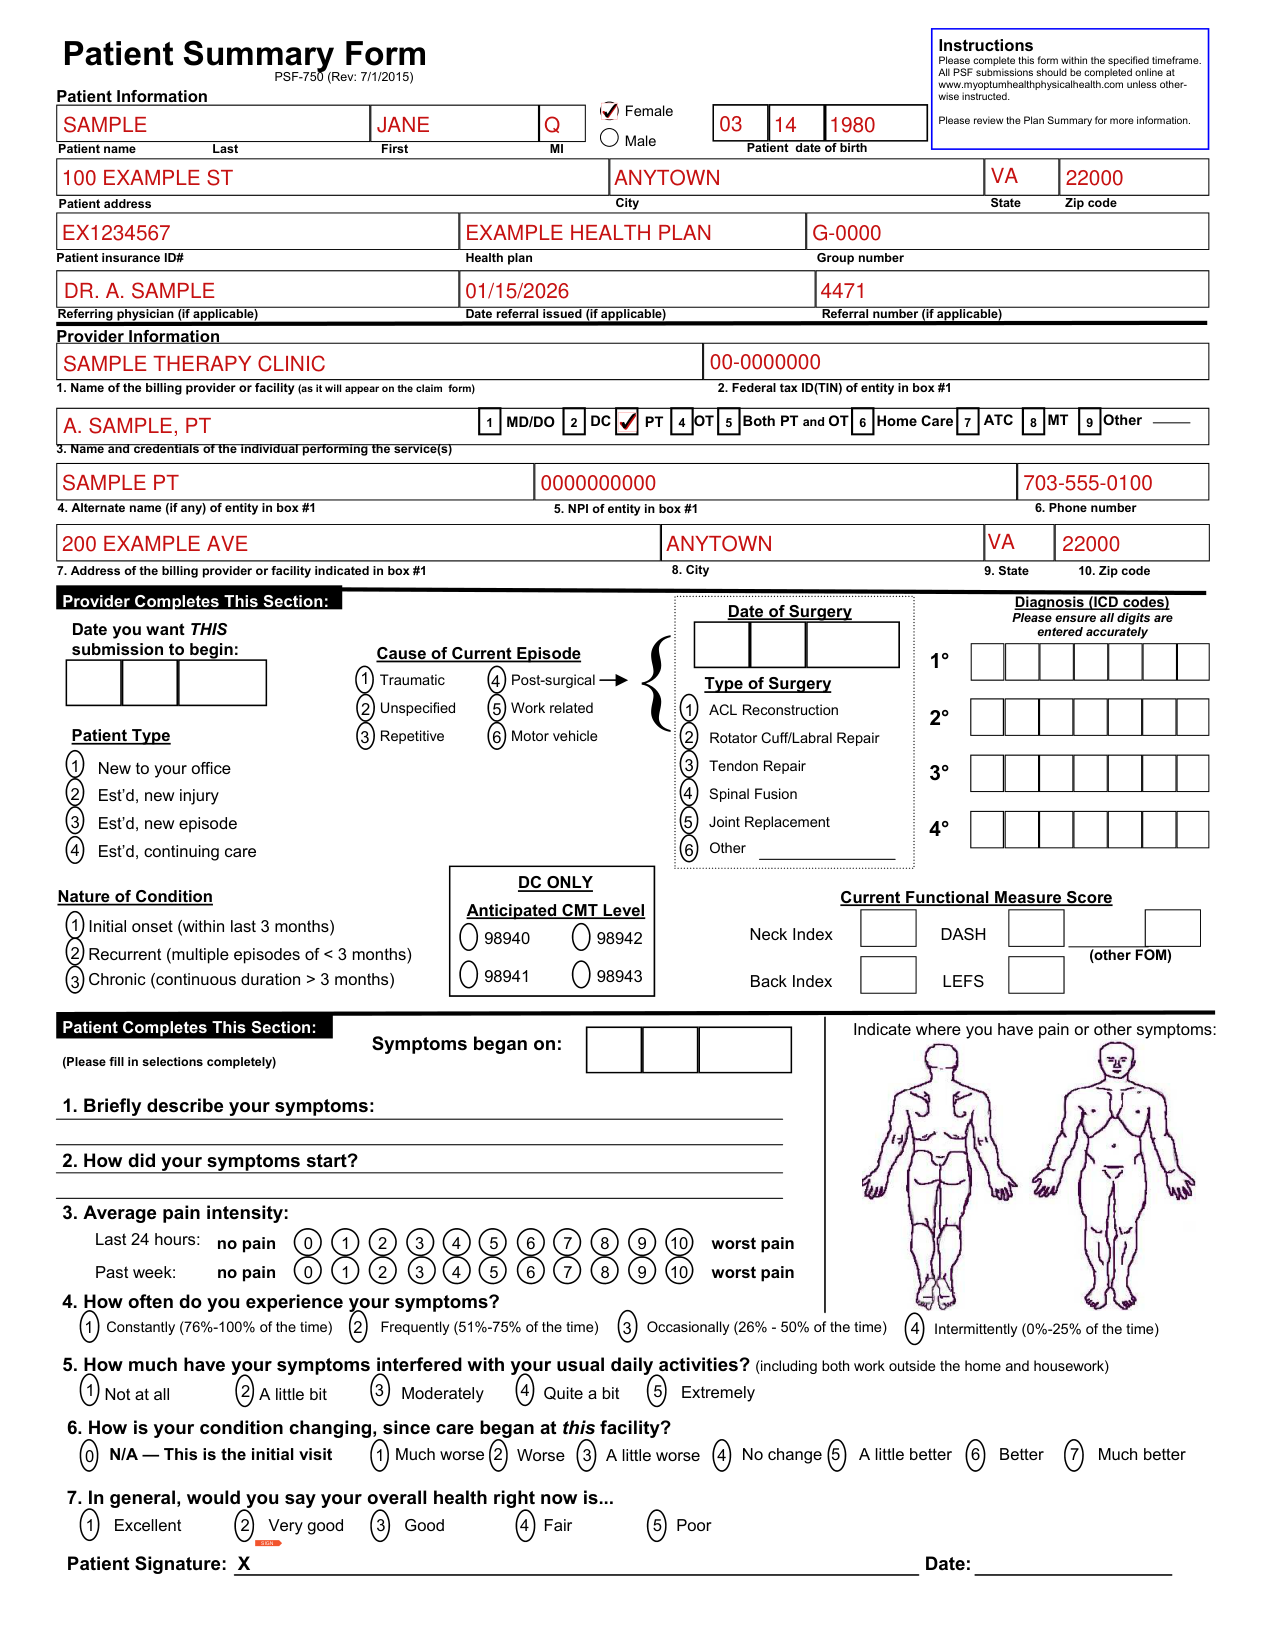
How to fill out Patient Summary Form PSF-750, box by box
Patient Information
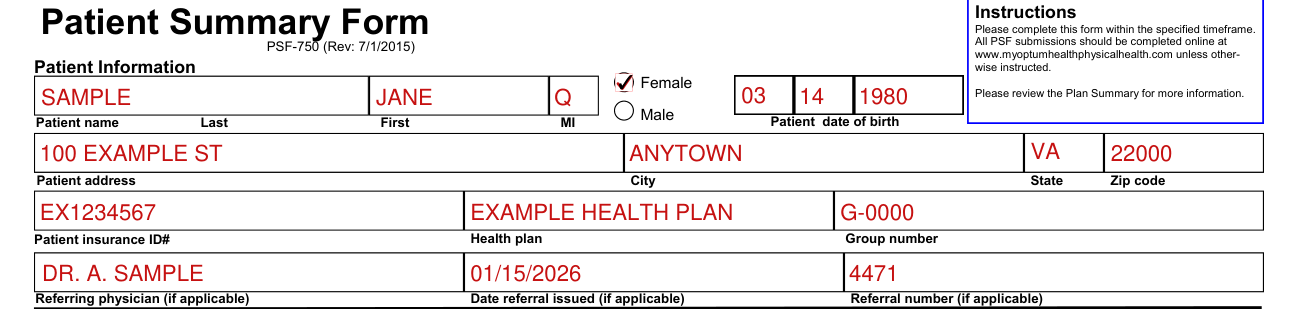
Please complete this form within the specified timeframe. All PSF submissions should be completed online at www.myoptumhealthphysicalhealth.com unless otherwise instructed. Please review the Plan Summary for more information.
Under Patient Information, enter the Patient name (Last, First, MI), mark Female or Male, and enter the Patient date of birth.
Enter the Patient address with City, State and Zip code.
Enter the Patient insurance ID#, the Health plan and the Group number.
Enter the Referring physician (if applicable), the Date referral issued (if applicable) and the Referral number (if applicable).
Provider Information
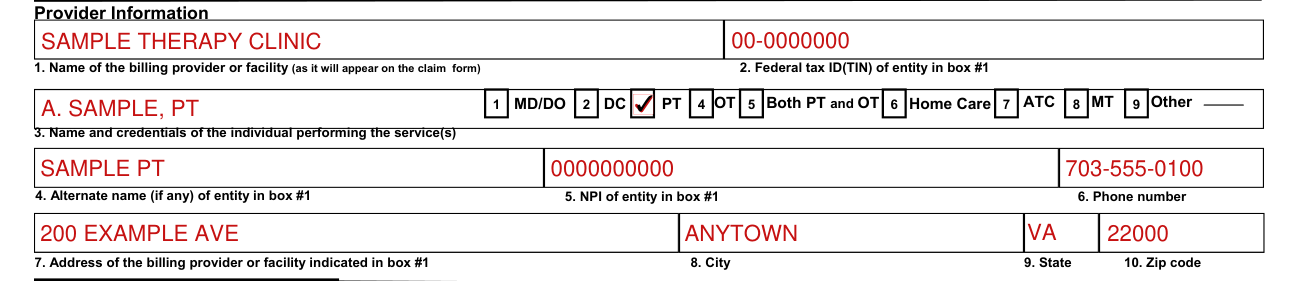
In box 1, enter the Name of the billing provider or facility (as it will appear on the claim form). In box 2, enter the Federal tax ID(TIN) of entity in box #1.
In box 3, enter the Name and credentials of the individual performing the service(s), and mark MD/DO, DC, PT, OT, Both PT and OT, Home Care, ATC, MT or Other.
In box 4, enter the Alternate name (if any) of entity in box #1. In box 6, enter the Phone number.
In box 5, enter the NPI of entity in box #1.
In box 7, enter the Address of the billing provider or facility indicated in box #1, then the City in box 8, the State in box 9 and the Zip code in box 10.
Provider Completes This Section
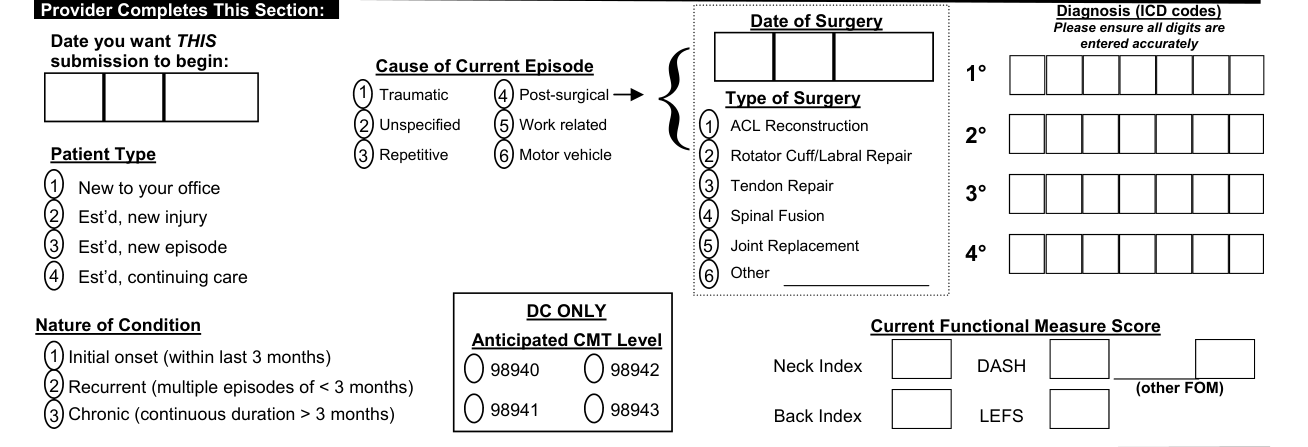
Under Provider Completes This Section:, enter the Diagnosis (ICD codes). Please ensure all digits are entered accurately.
Enter the Date you want THIS submission to begin.
Enter the Date of Surgery and mark the Type of Surgery: ACL Reconstruction, Rotator Cuff/Labral Repair, Tendon Repair, Spinal Fusion, Joint Replacement or Other.
Under Cause of Current Episode, mark Post-surgical, Traumatic, Unspecified, Work related, Repetitive or Motor vehicle.
Mark the Patient Type: New to your office, Est'd, new injury, Est'd, new episode or Est'd, continuing care.
Under Nature of Condition, mark Initial onset (within last 3 months), Recurrent (multiple episodes of < 3 months) or Chronic (continuous duration > 3 months).
DC ONLY: under Anticipated CMT Level, mark 98940, 98941, 98942 or 98943.
Patient Completes This Section
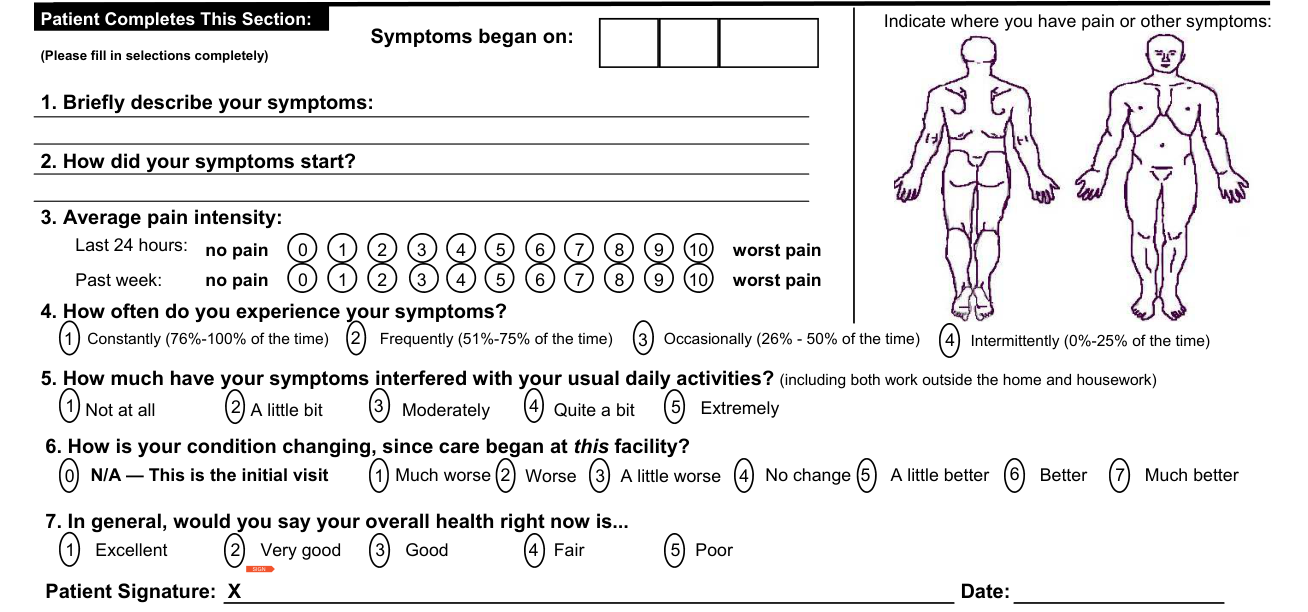
Under Patient Completes This Section:, please fill in selections completely.
Briefly describe your symptoms, enter Symptoms began on and indicate where you have pain or other symptoms.
2. How did your symptoms start?
For 3. Average pain intensity:, mark 0 (no pain) to 10 (worst pain) for Last 24 hours and for Past week.
For 4. How often do you experience your symptoms?, mark Constantly (76%-100% of the time), Frequently (51%-75% of the time), Occasionally (26% - 50% of the time) or Intermittently (0%-25% of the time).
For 5. How much have your symptoms interfered with your usual daily activities? (including both work outside the home and housework), mark Not at all, A little bit, Moderately, Quite a bit or Extremely.
For 6. How is your condition changing, since care began at this facility?, mark Much worse, Worse, A little worse, No change, A little better, Better, Much better or N/A - This is the initial visit.
For 7. In general, would you say your overall health right now is..., mark Excellent, Very good, Good, Fair or Poor.
Sources
[1] Patient Summary Form PSF-750 (Rev: 7/1/2015), the served file (the Official source link on this page).