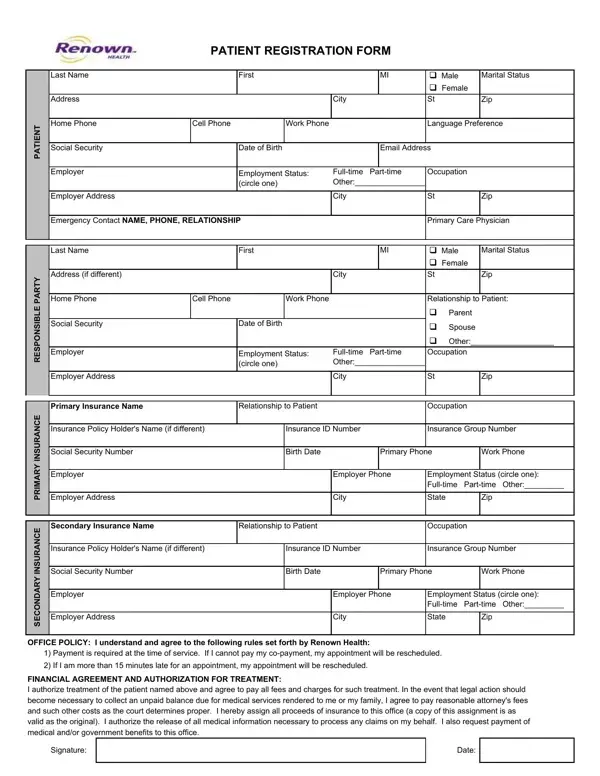
How to Fill Out Patient Registration Form

Patient Registration Form at a glance

What it is: Patient Registration Form, signed to authorize treatment of the patient.

Who signs: You authorize treatment of the patient and agree to pay all fees and charges for such treatment; sign in the Signature box and enter the Date.

A filled-in Patient Registration Form example: an adult patient registers for herself
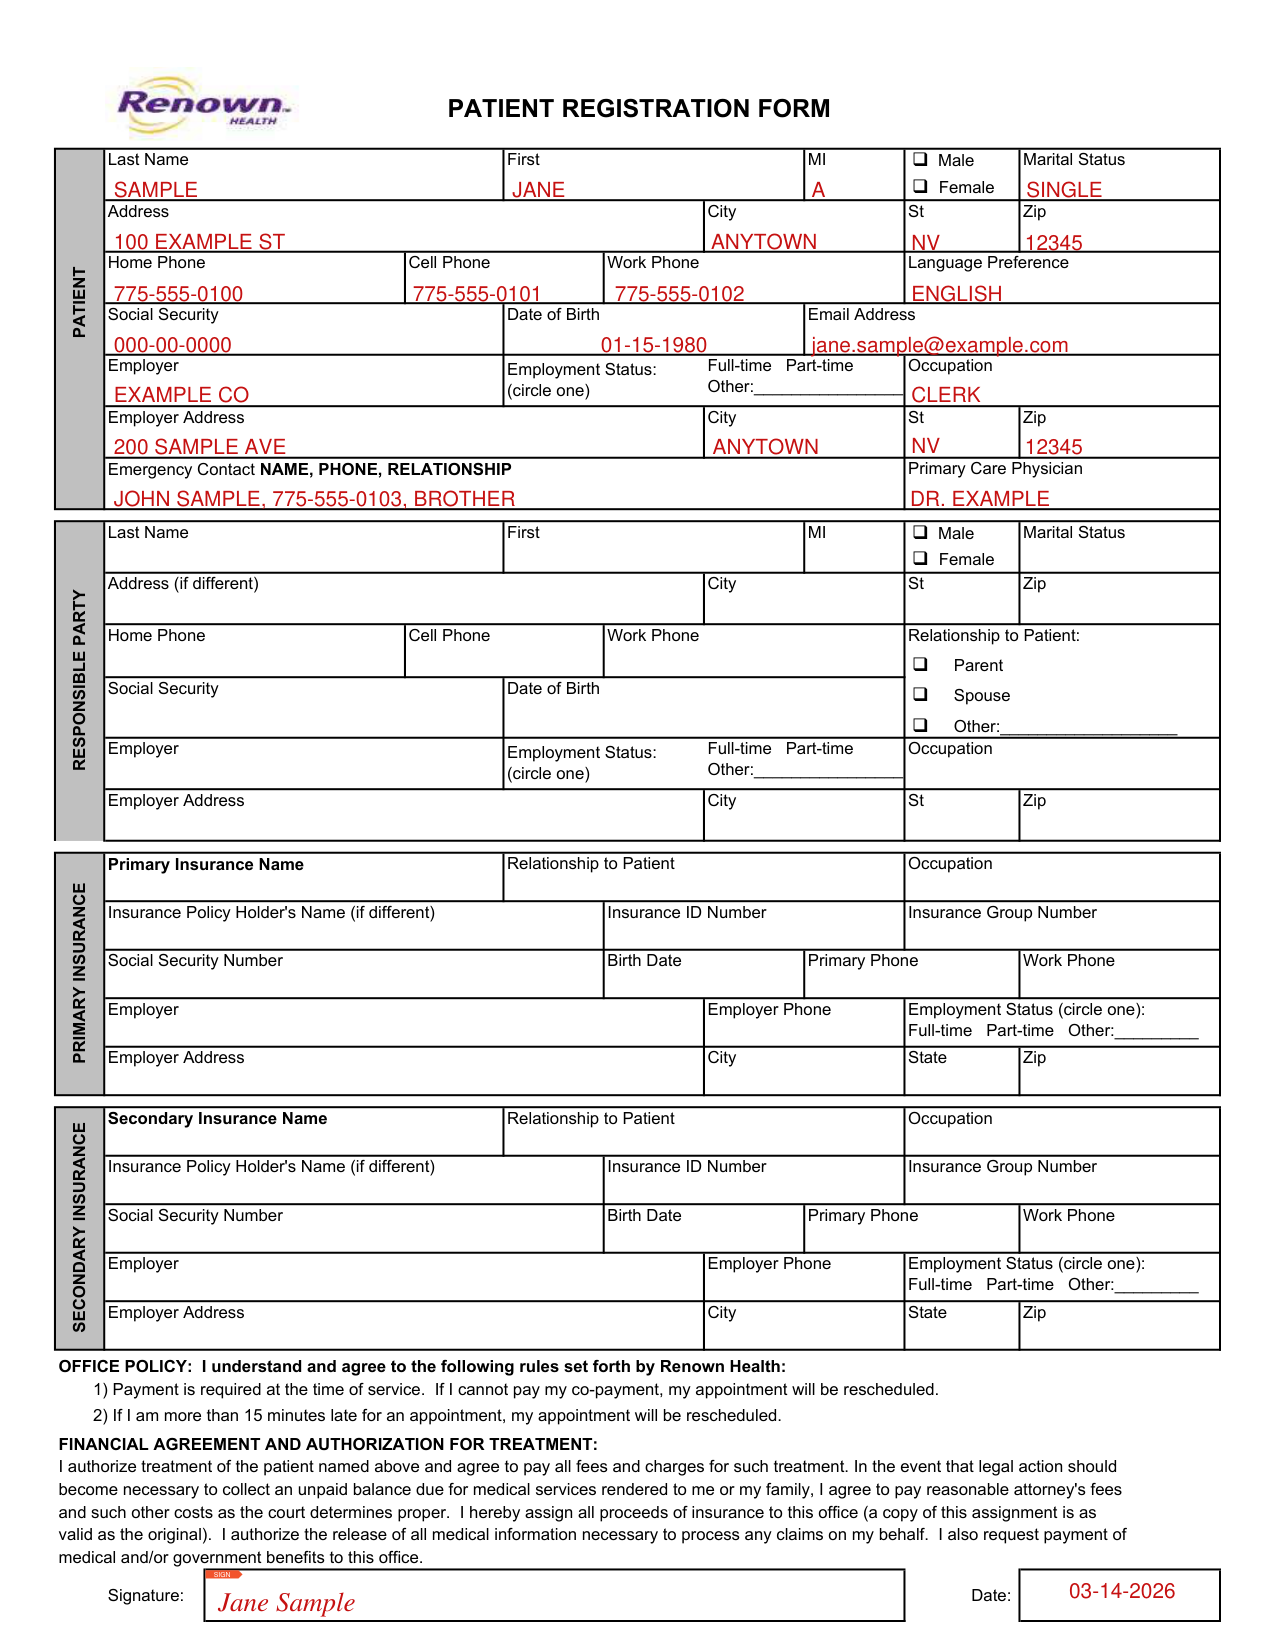
Patient Registration Form example filled out, example: an adult patient registers for herself
Jane Sample fills out the Renown patient registration form for herself. She pays herself and has no insurance, so the Responsible party and insurance groups stay empty. The picture shows the patient part and the signature; every value in it is made up.

How to fill out Patient Registration Form, box by box

Name and address
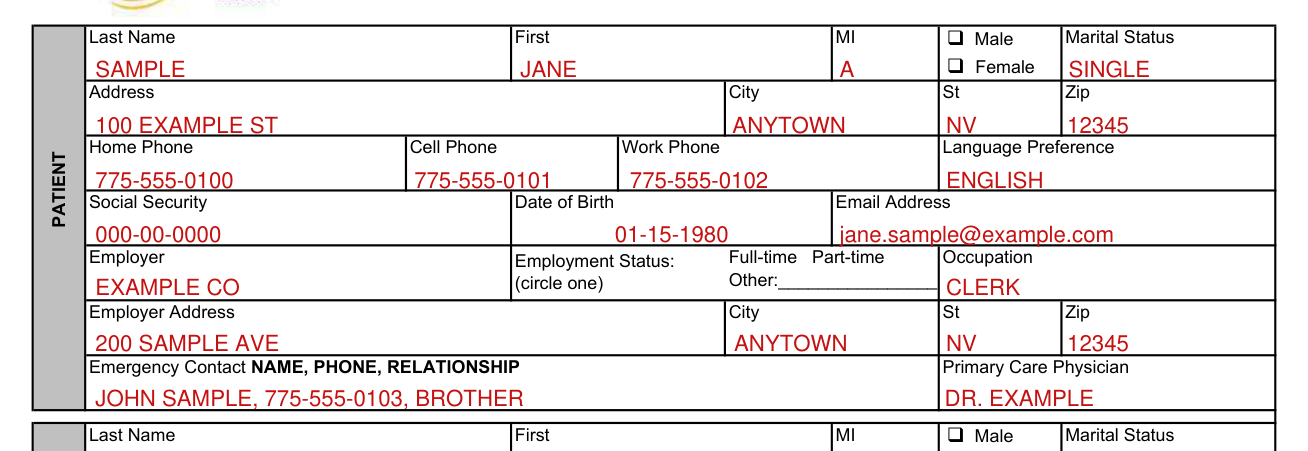
Patient Registration Form example filled out, name and address

Enter the Last Name, First, MI and Marital Status, then mark Male or Female.

Enter the Address, City, St and Zip.

Enter the Home Phone, Cell Phone, Work Phone and Language Preference.

Enter the Social Security, Date of Birth and Email Address.

Enter the Employer and Occupation, and circle one Employment Status: Full-time, Part-time or Other.

Enter the Employer Address, City, St and Zip.

Enter the Emergency Contact NAME, PHONE, RELATIONSHIP and the Primary Care Physician.

Responsible party
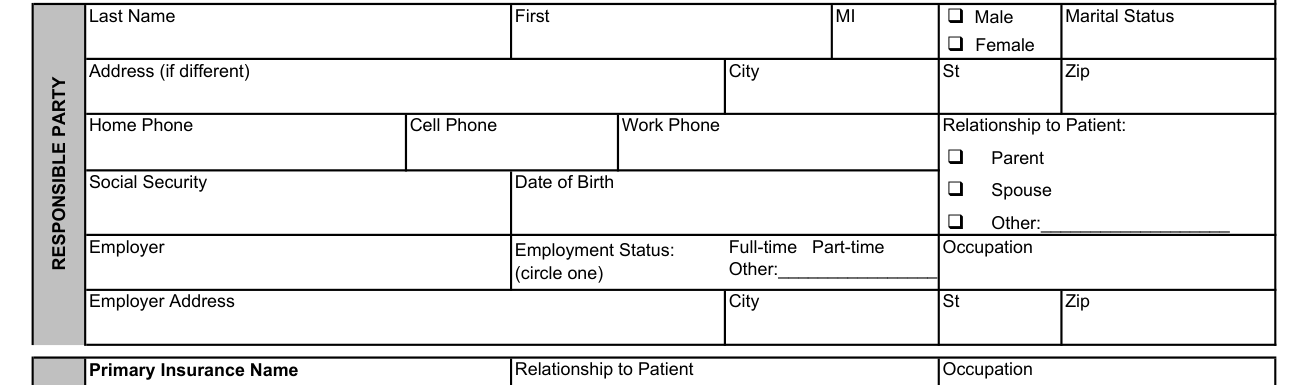
Patient Registration Form example filled out, responsible party

For the RESPONSIBLE PARTY, mark the Relationship to Patient: Parent, Spouse or Other.

Primary and secondary insurance
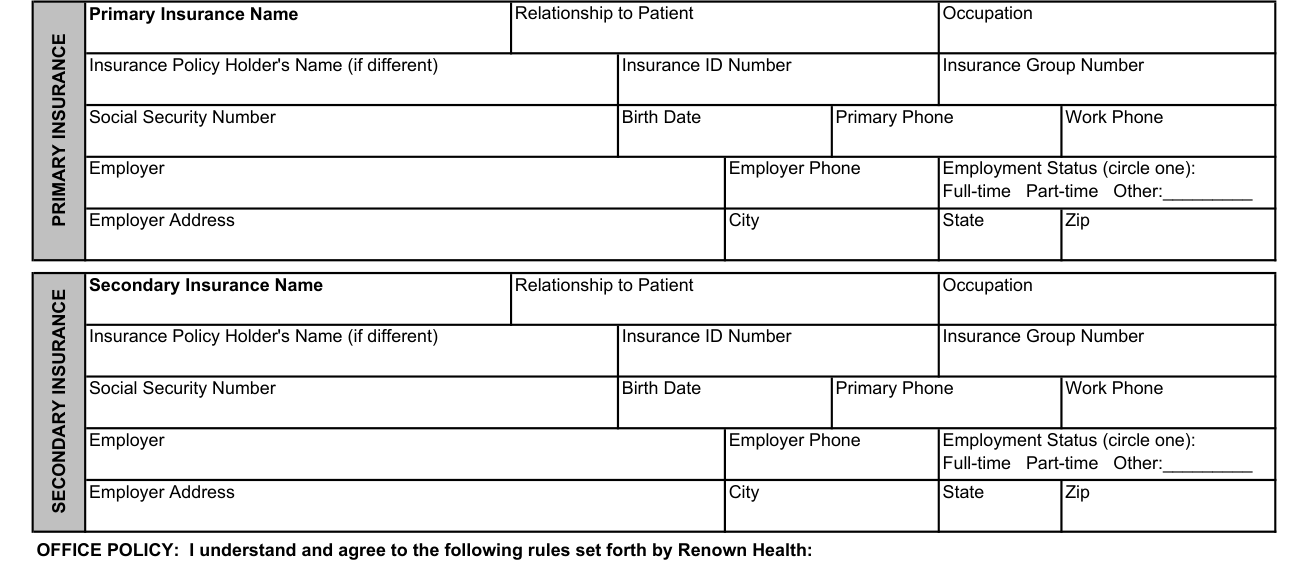
Patient Registration Form example filled out, primary and secondary insurance

Enter the Primary Insurance Name, the Relationship to Patient, the Insurance Policy Holder's Name (if different), the Insurance ID Number and the Insurance Group Number.

For the Secondary Insurance, enter the Name, the Relationship to Patient, the Insurance Policy Holder's Name (if different), the Insurance ID Number and the Insurance Group Number, then the Social Security Number, Birth Date, Primary Phone and Work Phone.

Office policy and signature

Patient Registration Form example filled out, office policy and signature

1) Payment is required at the time of service. If you cannot pay your co-payment, your appointment will be rescheduled.

2) If you are more than 15 minutes late for an appointment, your appointment will be rescheduled.

Signing authorizes treatment of the patient and agrees to pay all fees and charges for such treatment.

If legal action should become necessary to collect an unpaid balance due for medical services rendered, you agree to pay reasonable attorney's fees and such other costs as the court determines proper.

Signing authorizes the release of all medical information necessary to process any claims on your behalf.

Sources

[1] Patient Registration Form, Renown Health (the Official source link on this page).

Renown Patient Registration Form PDF Details

The Renown Patient Registration form is a comprehensive document designed to ensure that all necessary personal, medical, and insurance information is accurately captured for patients seeking health services at Renown Health facilities. This detailed form inquires about a range of personal information, starting with basic identity details such as last name, first name, middle initial, gender, and marital status, extending to contact information that includes address, phone numbers, language preference, social security number, date of birth, and email address. Employment details are also requested, covering employment status, occupation, and employer's contact information, ensuring a thorough understanding of the patient's occupational background. Significantly, the form emphasizes the need for emergency contact details alongside the patient's primary care physician information, enhancing patient safety and care coordination. Moreover, it captures insurance information—critical for billing purposes—including primary and secondary insurance details, policy holder’s names, and corresponding insurance identification to streamline the financial processes involved in patient care. The form also outlines the office and financial policies of Renown Health, explicitly stating the expectations regarding payment at the time of service and appointment punctuality, and includes a section for financial agreement and authorization for treatment, which underscores the patient's commitment to abide by the stated policies and payment obligations. This inclusive form is a key step in ensuring effective patient registration, facilitating a smooth transition into the Renown Health care system, and laying the groundwork for a structured approach to patient care and treatment.

QuestionAnswer
Form NameRenown Patient Registration Form
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namesproceeds, rescheduled, renown pre registration, Renown