
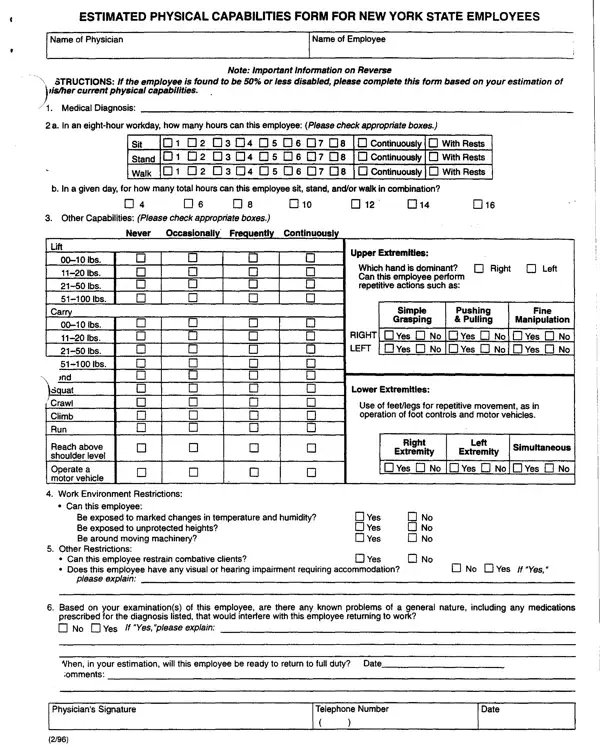
Estimated Physical Capabilities Form at a glance
What it is: Estimated Physical Capabilities Form for New York State Employees.
Who signs: The form has lines for the Physician's Signature, Telephone Number and Date.
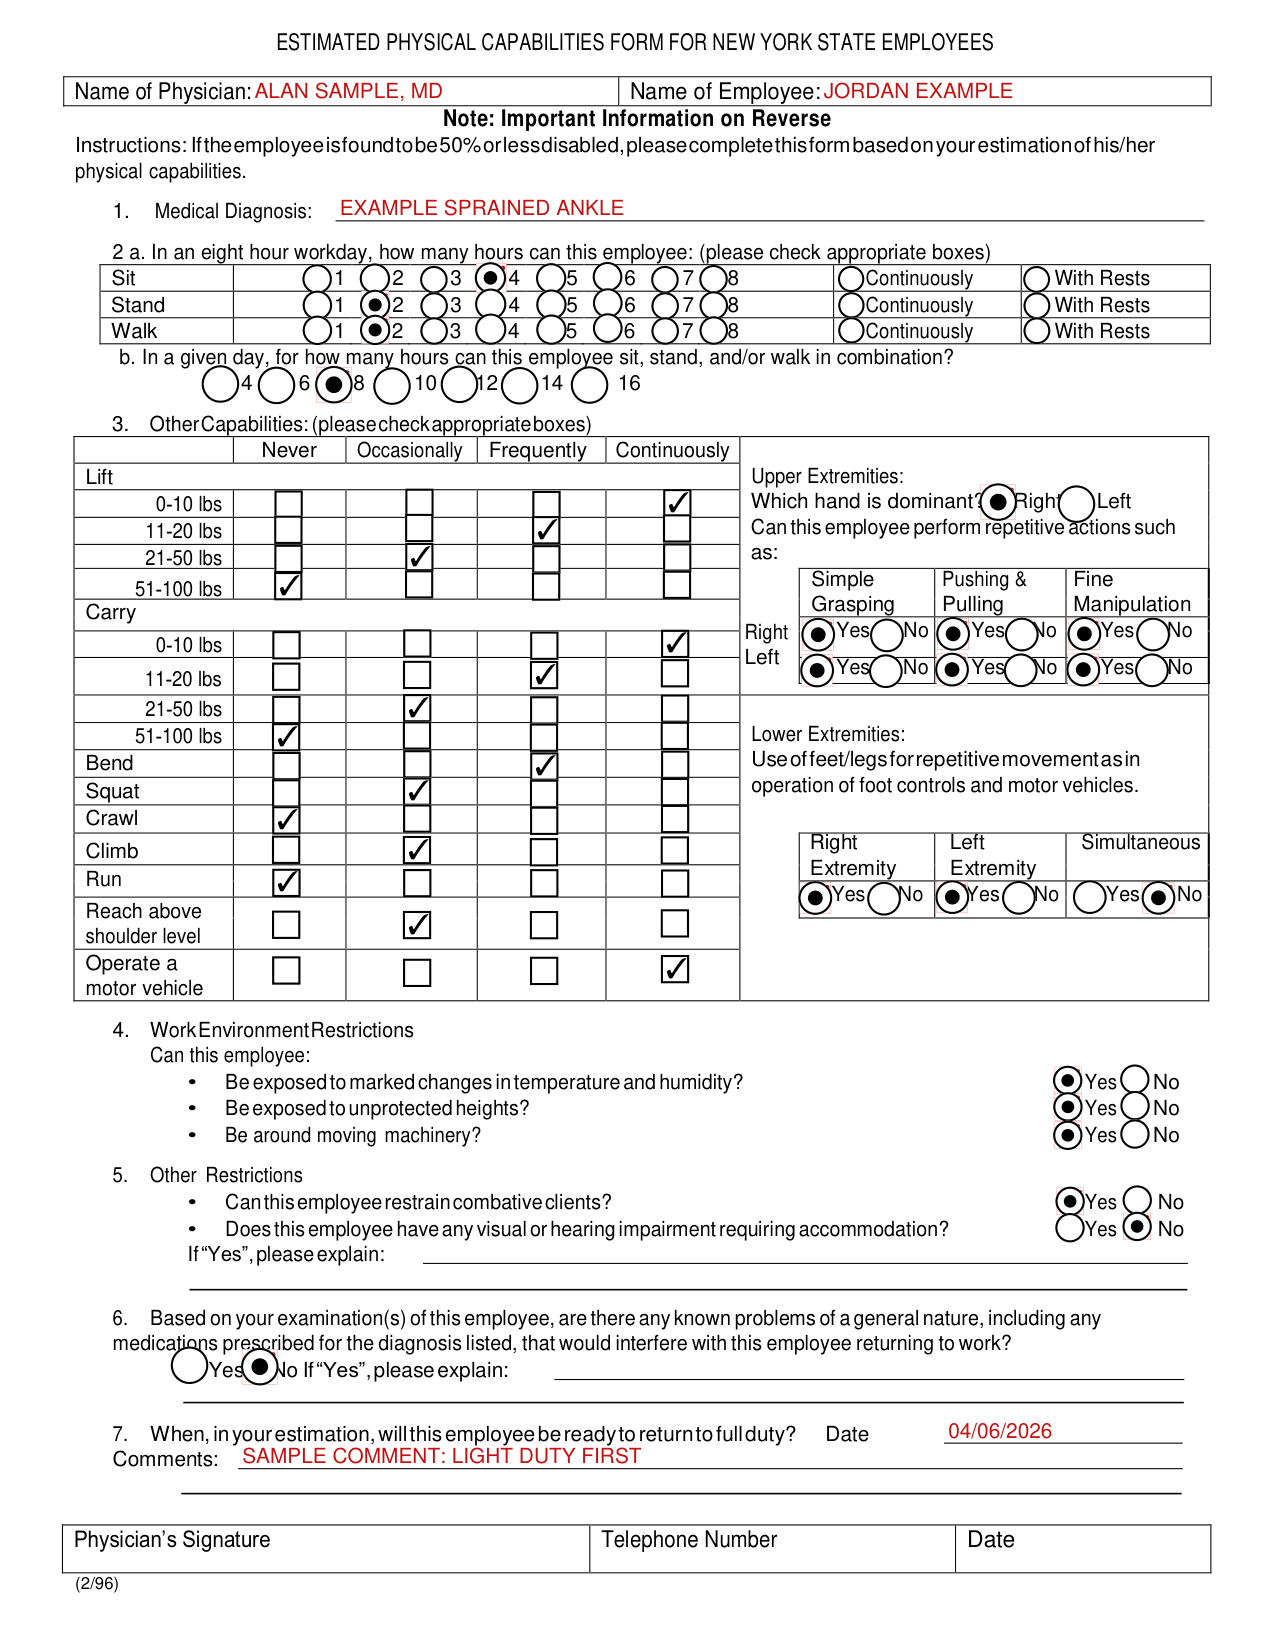
A filled-in Estimated Physical Capabilities Form example: a physician completes the form
How to fill out Estimated Physical Capabilities Form, box by box
Physician, employee and 1. Medical Diagnosis

Enter the Name of Physician and the Name of Employee, then the Medical Diagnosis in box 1.
2 a. In an eight hour workday, how many hours can this employee

In 2a, in an eight hour workday, check the appropriate boxes for how many hours this employee can Sit, Stand and Walk: 1, 2, 3, 4, 5, 6, 7, 8, Continuously or With Rests. In 2b, in a given day, for how many hours can this employee sit, stand, and/or walk in combination: 4, 6, 8, 10, 12, 14, 16.
3. Other Capabilities
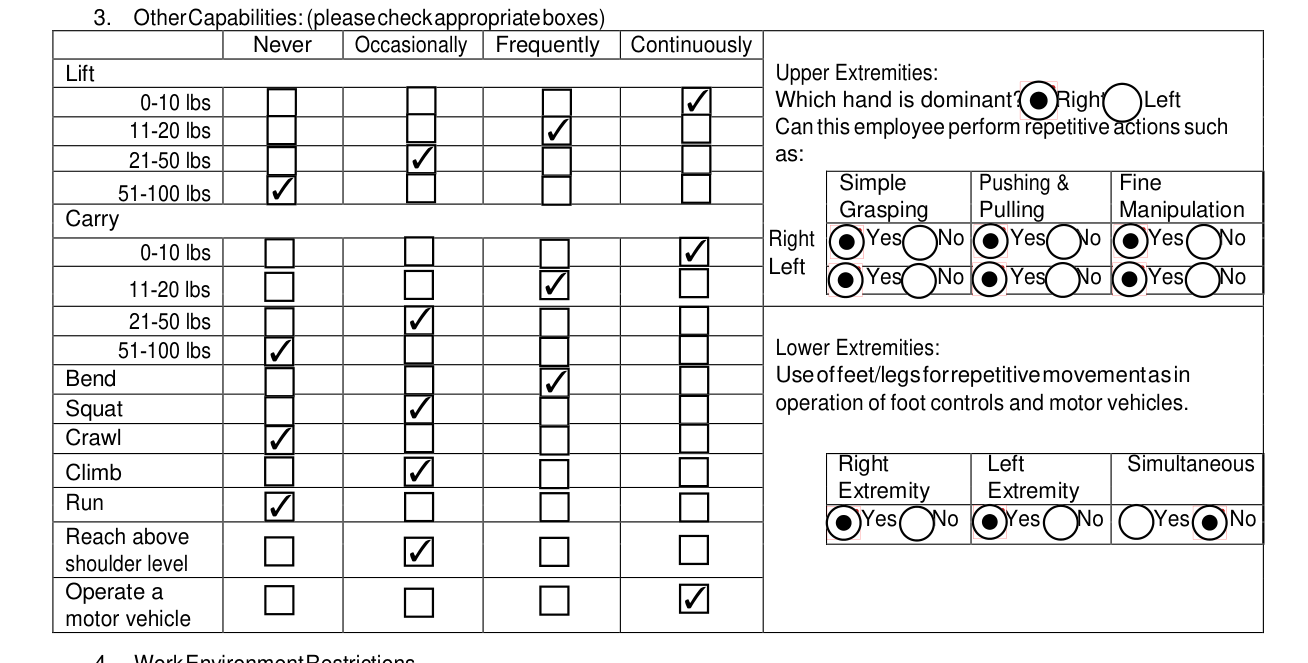
In 3. Other Capabilities, check the appropriate boxes: Never, Occasionally, Frequently or Continuously.
For Lift, check a box for 0-10 lbs, 11-20 lbs, 21-50 lbs and 51-100 lbs.
For Carry, check a box for 0-10 lbs, 11-20 lbs, 21-50 lbs and 51-100 lbs. For Bend, Squat and Crawl, check a box for each.
Under Upper Extremities, mark which hand is dominant, Right or Left. Can this employee perform repetitive actions such as Simple Grasping, Pushing & Pulling and Fine Manipulation, Right and Left: mark Yes or No.
Under Lower Extremities, use of feet/legs for repetitive movement as in operation of foot controls and motor vehicles: mark Yes or No for Right Extremity, Left Extremity and Simultaneous. For Climb, Run, “Reach above shoulder level” and Operate a motor vehicle, check a box.
4. Work Environment Restrictions

In 4. Work Environment Restrictions, mark Yes or No: Can this employee be exposed to marked changes in temperature and humidity, be exposed to unprotected heights, be around moving machinery?
5. Other Restrictions

In 5. Other Restrictions, mark Yes or No: Can this employee restrain combative clients? Does this employee have any visual or hearing impairment requiring accommodation? If “Yes”, please explain.
6. Known problems that would interfere with returning to work

In 6, mark Yes or No: based on your examination(s) of this employee, are there any known problems of a general nature, including any medications prescribed for the diagnosis listed, that would interfere with this employee returning to work? If “Yes”, please explain.
7. Ready to return to full duty

In 7, when, in your estimation, will this employee be ready to return to full duty? Enter the Date and Comments.
When an employee's level of disability is classified at 50 percent or less (mildly or moderately disabled) and the employee is within 60 days of full recovery, he/she is qualified for an alternate duty assignment.
More rules for Estimated Physical Capabilities Form
If the employee is found to be 50% or less disabled, please complete this form based on your estimation of his/her physical capabilities.
The agency will use the information provided on this form to design an assignment that is consistent with the employee's limitations and capabilities.
An assignment will be given to an employee initially for no more than 60 days.
Questions concerning the information on this form should be directed to the evaluating physician at the telephone number listed. Questions concerning the alternate duty assignment should be directed to the employee's agency.
Sources
[1] Estimated Physical Capabilities Form for New York State Employees (2/96) (the Official source link on this page).