
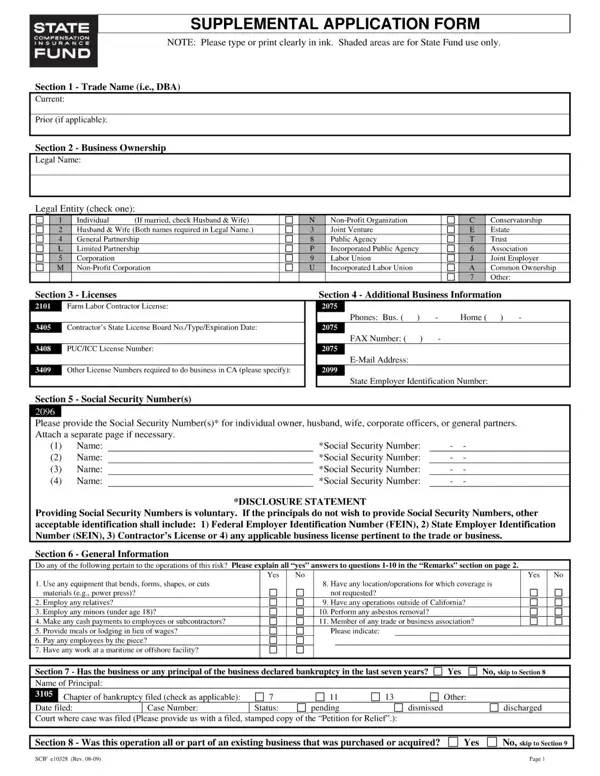

Form 10328 at a glance
What it is: SUPPLEMENTAL APPLICATION FORM: the ACORD and Supplemental Application.
Who signs: To be completed by broker, owner, or an officer/partner (provide your title) of the business.
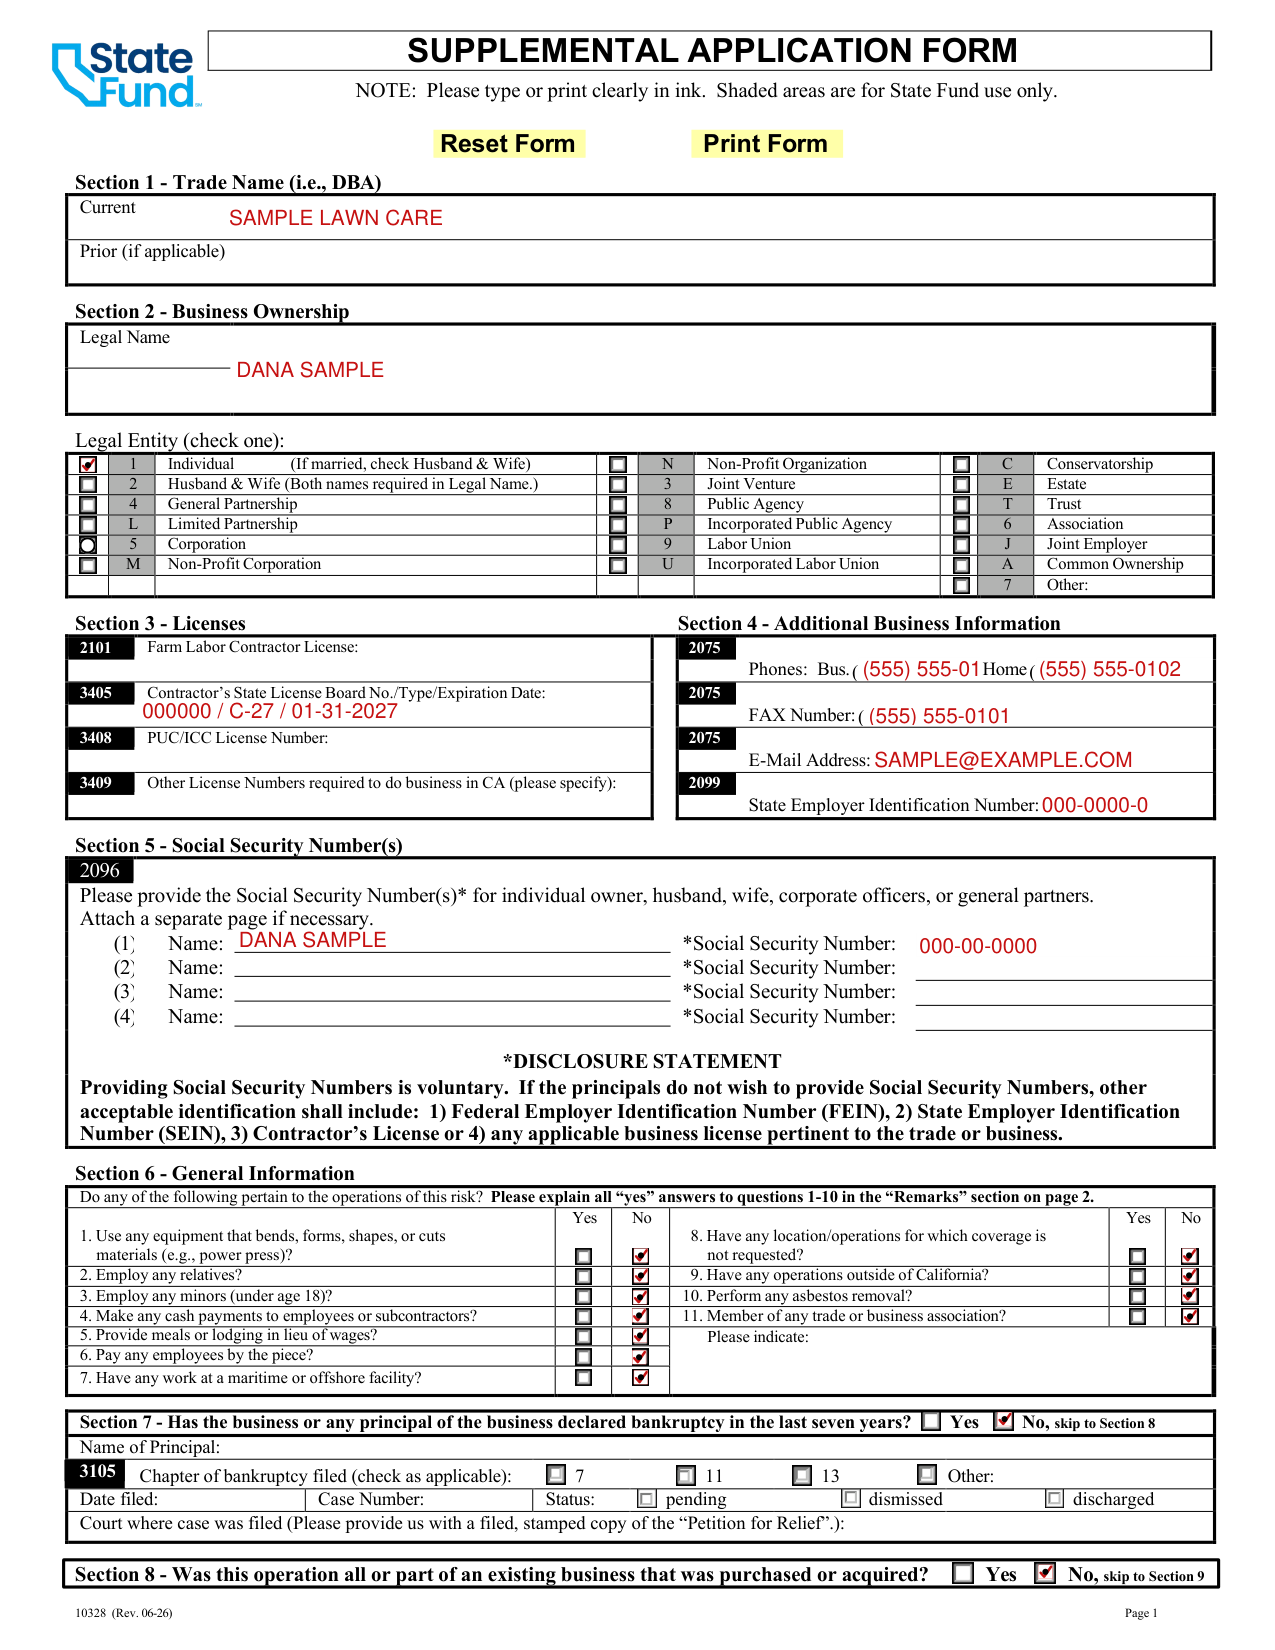
A filled-in Form 10328 example: a sole owner fills out the Supplemental Application Form
How to fill out Form 10328, box by box
Trade Name (i.e., DBA)

Under Section 1 - Trade Name (i.e., DBA), enter the Current trade name and, if applicable, the Prior trade name.
Business Ownership
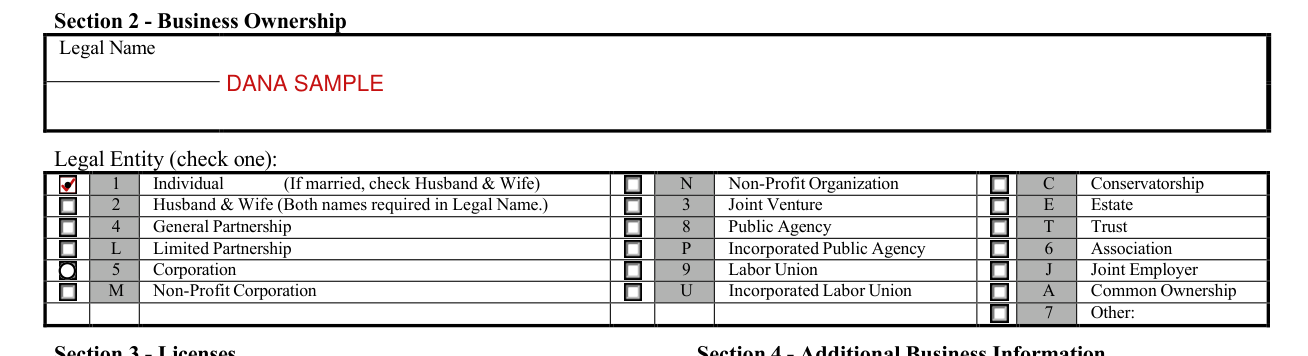
Under Section 2 - Business Ownership, enter the Legal Name.
Legal Entity (check one): Individual (If married, check Husband & Wife), Husband & Wife (Both names required in Legal Name.), Joint Venture, General Partnership, Limited Partnership, Association, Corporation, Non-Profit Corporation, Non-Profit Organization, Conservatorship, Estate, Trust, Public Agency, Incorporated Public Agency, Labor Union, Incorporated Labor Union, Joint Employer, Common Ownership, Other.
Licenses and Additional Business Information
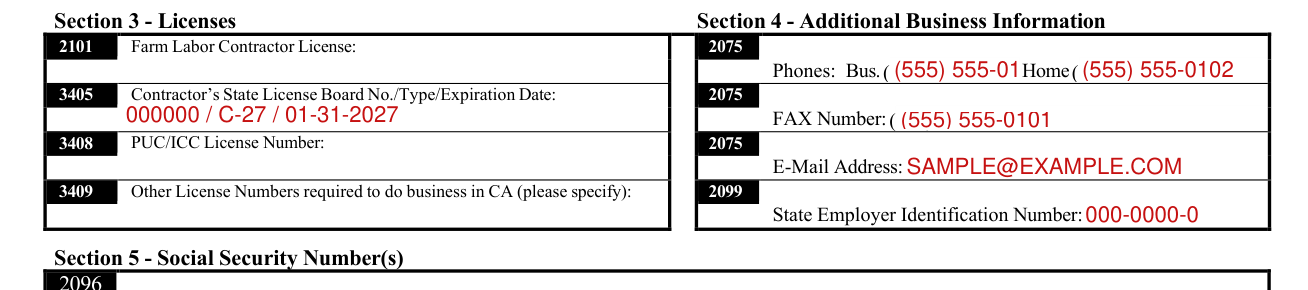
Section 3 - Licenses: Farm Labor Contractor License, Contractor's State License Board No./Type/Expiration Date, PUC/ICC License Number, Other License Numbers required to do business in CA (please specify). Section 4 - Additional Business Information: Phones (Bus., Home), FAX Number, E-Mail Address, State Employer Identification Number.
Social Security Number(s)
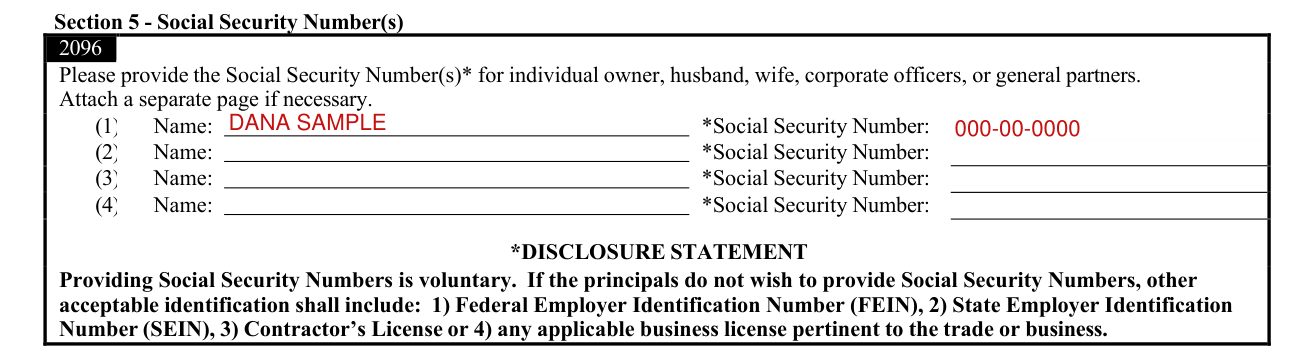
Under Section 5 - Social Security Number(s), 2096 Please provide the Social Security Number(s)* for individual owner, husband, wife, corporate officers, or general partners. Attach a separate page if necessary. Enter each Name with its Social Security Number, (1) to (4). *DISCLOSURE STATEMENT Providing Social Security Numbers is voluntary. If the principals do not wish to provide Social Security Numbers, other acceptable identification shall include: 1) Federal Employer Identification Number (FEIN), 2) State Employer Identification Number (SEIN), 3) Contractor's License or 4) any applicable business license pertinent to the trade or business.
General Information
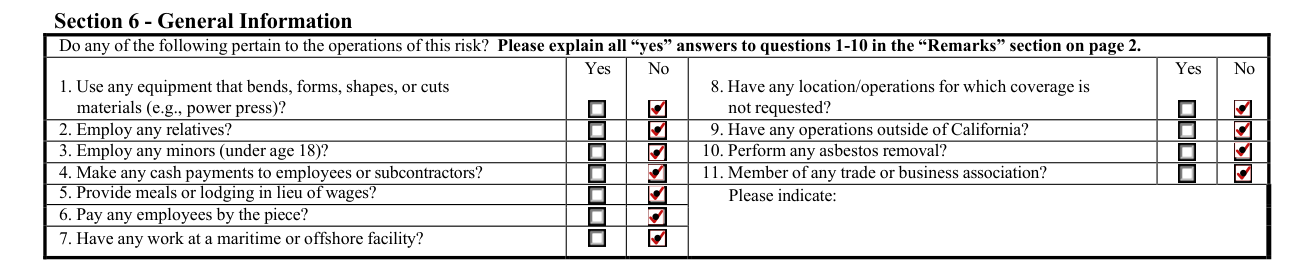
Under Section 6 - General Information, do any of the following pertain to the operations of this risk? Please explain all "yes" answers to questions 1-10 in the "Remarks" section on page 2.
Yes or No for each: 1. Use any equipment that bends, forms, shapes, or cuts materials (e.g., power press)? 2. Employ any relatives? 3. Employ any minors (under age 18)? 4. Make any cash payments to employees or subcontractors? 5. Provide meals or lodging in lieu of wages? 6. Pay any employees by the piece? 7. Have any work at a maritime or offshore facility? 8. Have any location/operations for which coverage is not requested? 9. Have any operations outside of California? 10. Perform any asbestos removal? 11. Member of any trade or business association? Please indicate:
Bankruptcy in the last seven years
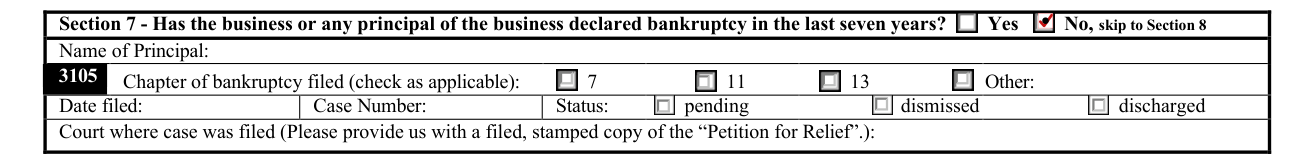
Section 7 - Has the business or any principal of the business declared bankruptcy in the last seven years? Yes, or No, skip to Section 8. If Yes, enter the Name of Principal, check the Chapter of bankruptcy filed (check as applicable): 7, 11, 13 or Other, enter the Date filed and the Case Number, check the Status: pending, dismissed or discharged, and enter the Court where case was filed. Please provide a filed, stamped copy of the "Petition for Relief".
Business purchased or acquired
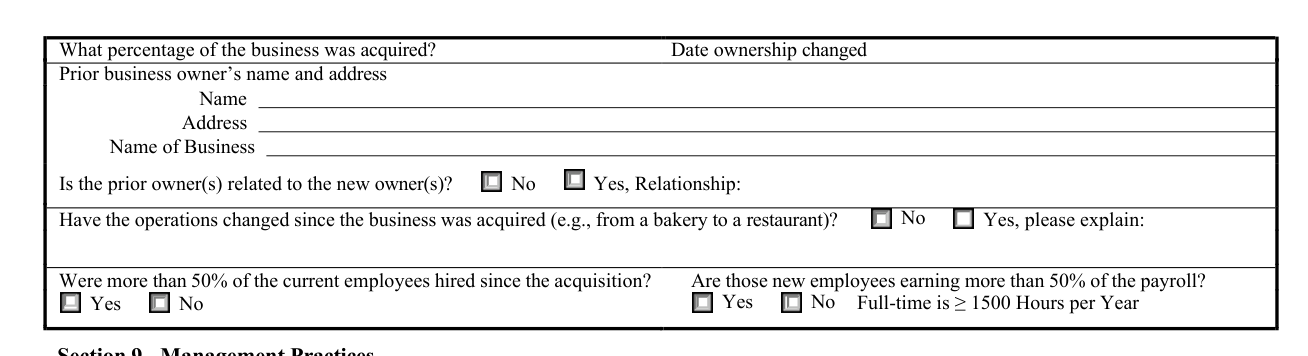
Section 8 - Was this operation all or part of an existing business that was purchased or acquired? Yes, or No, skip to Section 9. If Yes, enter What percentage of the business was acquired?, the Date ownership changed and the Prior business owner's name and address (Name, Address, Name of Business). Is the prior owner(s) related to the new owner(s)? No, or Yes, Relationship:. Have the operations changed since the business was acquired (e.g., from a bakery to a restaurant)? No, or Yes, please explain:. Were more than 50% of the current employees hired since the acquisition? Are those new employees earning more than 50% of the payroll? Yes or No. Full-time is ≥ 1500 Hours per Year.
Management Practices

Under Section 9 - Management Practices, please indicate if you offer: Paid Sick Leave, Employee Assistance Program, Paid Vacations. Do you have a minimum of 2 employees? No, or Yes.
If yes, do you offer the majority of your eligible employees Health Insurance? (eligible = works a minimum of 30 hrs./wk) No, or Yes. If yes, do you pay at least 50% of the Health Insurance premium? No, or Yes, Name of Health Insurance Carrier:
Please check off the hiring practices implemented by your company: Job Descriptions, Pre-placement Medical Screening, Pre-placement Drug Testing, Pre-employment Reference Check, Union Employees, Drug-free Workplace.
No or Yes for each: Do you have an injury and illness Prevention Program? Do you maintain a written Workplace Violence Prevention Plan? Do you have a written early return-to-work program for employees injured on the job? Do you document: Employee Training, Facility Inspections. Describe your housekeeping: Good, Fair, Poor. Describe the condition of your equipment: Good, Fair, Poor.
Have you received any OSHA citations within the past year? No, or Yes (Please explain in "Remarks.") Does the business provide temporary employees? No, or Yes (Please explain in "Remarks.")
Remarks

Section 10 - Remarks: Attach a separate sheet if necessary.
Broker Information
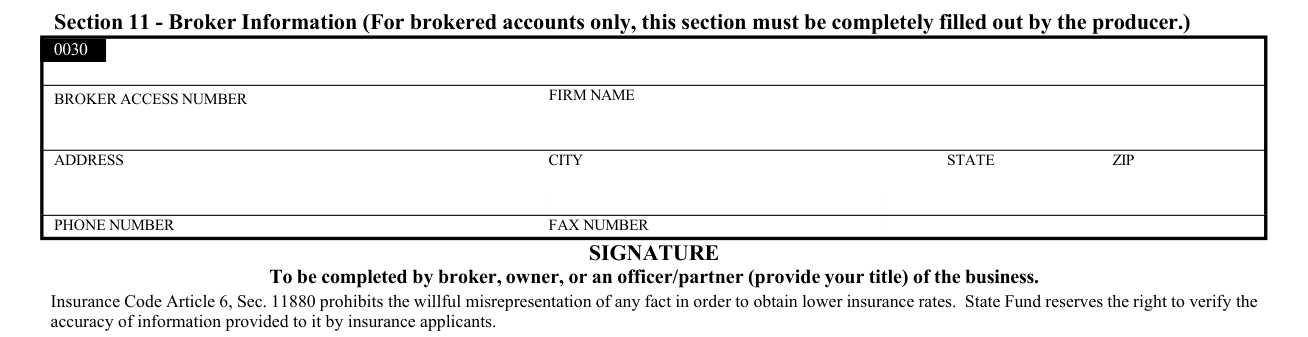
Section 11 - Broker Information: For brokered accounts only, this section must be completely filled out by the producer. Enter the Broker Access Number, Firm Name, Address, City, State, Zip, Phone Number and Fax Number.
Signature and date
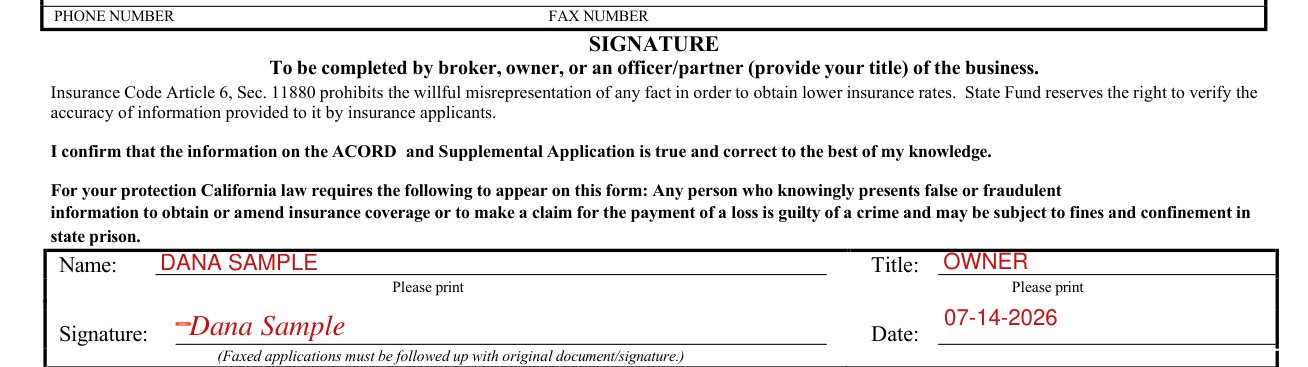
I confirm that the information on the ACORD and Supplemental Application is true and correct to the best of my knowledge.
Please print the Name and the Title, then add the Signature and the Date.
Faxed applications must be followed up with original document/signature.
Insurance Code Article 6, Sec. 11880 prohibits the willful misrepresentation of any fact in order to obtain lower insurance rates.
For your protection California law requires the following to appear on this form: Any person who knowingly presents false or fraudulent information to obtain or amend insurance coverage or to make a claim for the payment of a loss is guilty of a crime and may be subject to fines and confinement in state prison.
State Fund reserves the right to verify the accuracy of information provided to it by insurance applicants.
More rules for Form 10328
Type or print clearly in ink. Shaded areas are for State Fund use only.
It is mandatory to furnish all information requested on this form. Failure to provide the mandatory information may result in an inability to process your request.
Sources
[1] Form 10328 (Rev. 06-26), Supplemental Application Form, State Fund (the Official source link on this page).